Getting Through an EKG Strip Without Losing Your Mind
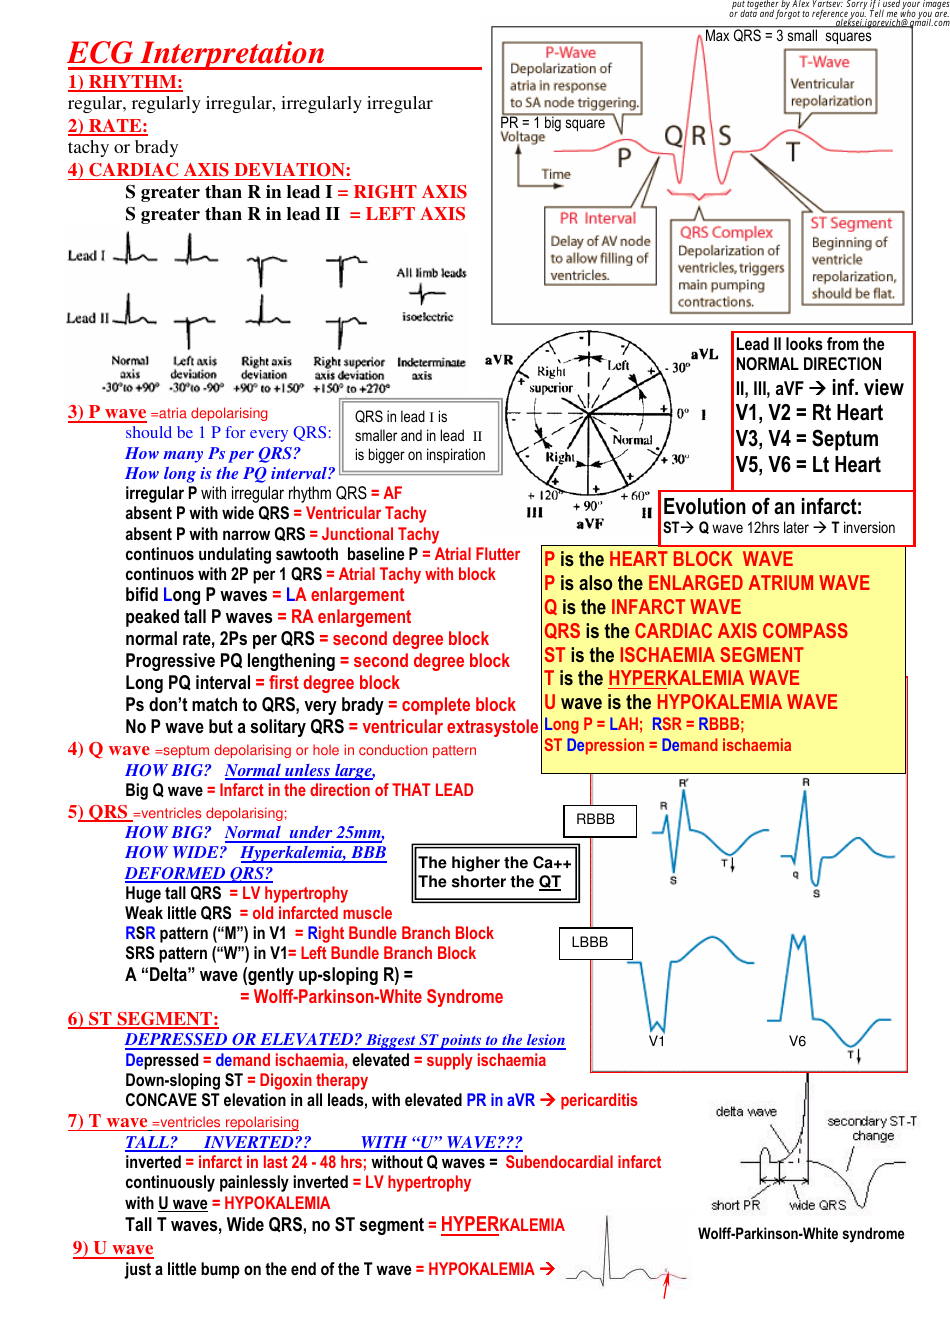
The cheat sheet I actually keep laminated on my desk isn't some glossy infomercial-style poster you download from a med student blog. It's a rough handwritten chart I compiled over about three years of reading strips in a busy hospital floor. The one piece most people skip is the systematic approach, so here's what mine looks like and how I actually use it. Start with heart rate. The quick way is counting R-R complexes between two 3-second markers on the paper. Six-second method is more reliable when the rhythm is irregular. Forget the "300 divided by number of large boxes" trick for anything but a perfectly regular sinus rhythm. It's accurate enough for ballparks but gives you garbage numbers when there's any variation at all. After rate, check rhythm. P wave before every QRS? QRS narrow or wide? Axis first if there's any doubt about the rhythm. Most people flip through leads in order without a plan and miss things. I look at lead II for the rhythm strip, then check I, aVR, and II for axis. Positive in both I and II means normal axis. If aVR is predominantly positive, that's right axis deviation or something else worth noting.
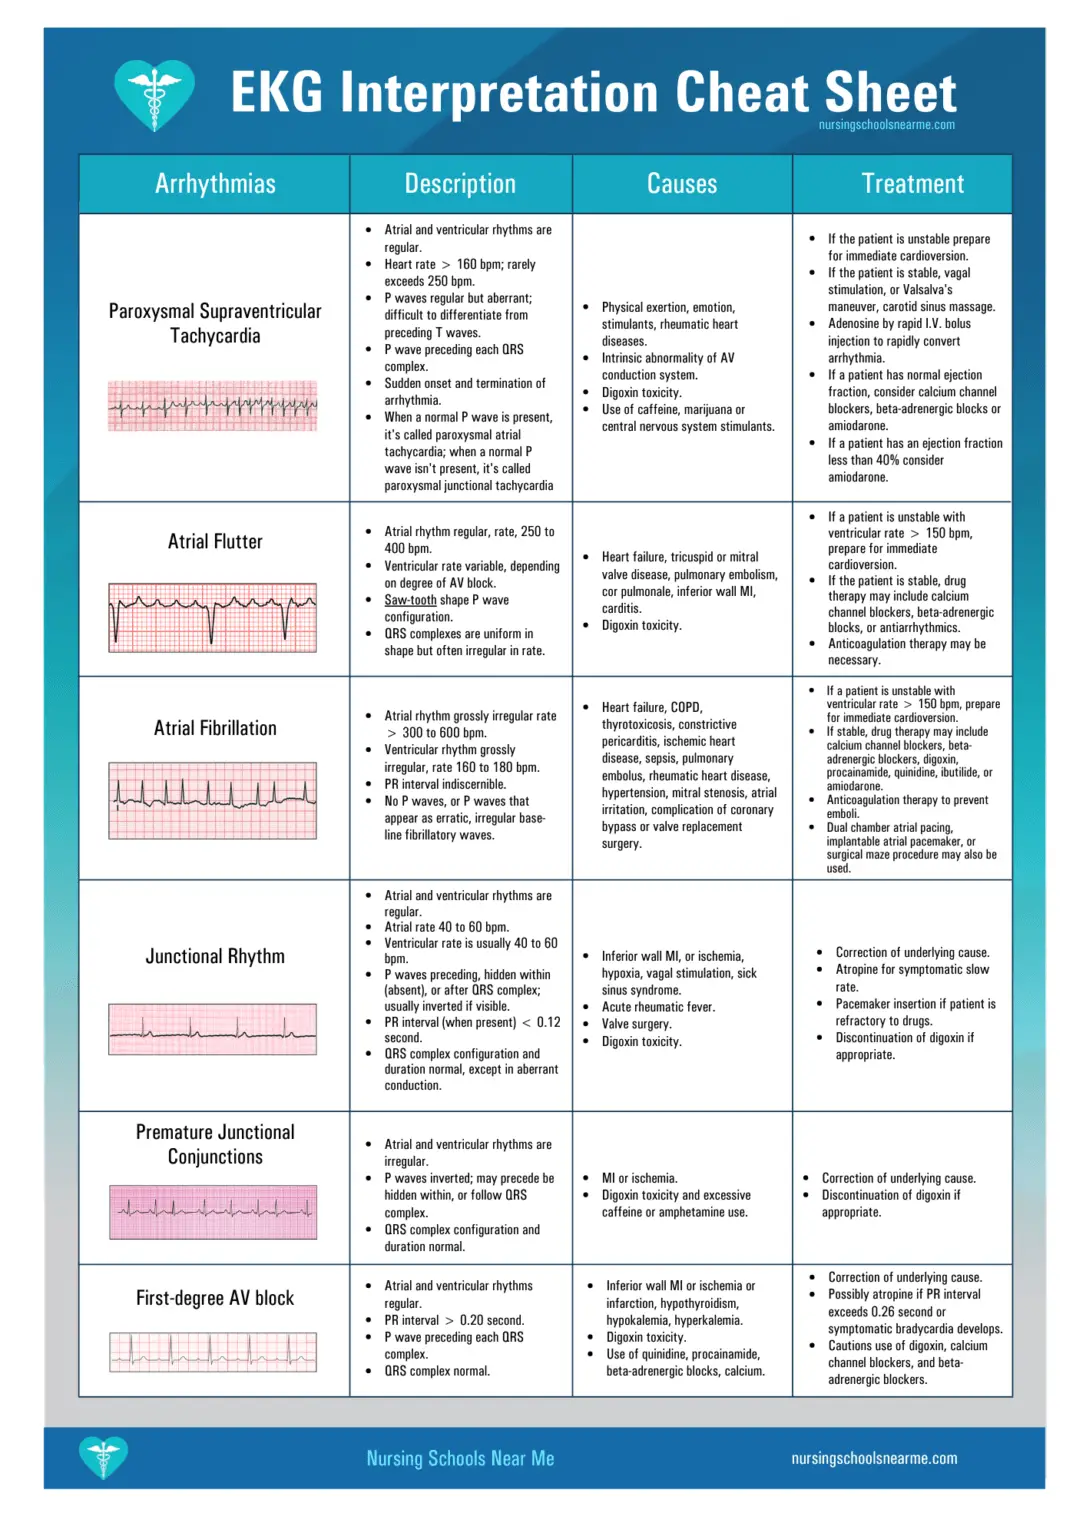
Interval measurements matter but only in context. PR shorter than 3 small squares means pre-excitation or junctional rhythm. Longer than 5 means first-degree block. Don't get hung up on borderline numbers. A PR of 200 milliseconds in an asymptomatic patient is usually nothing. A PR of 180 in someone with syncope might be the whole story. ST segments are where people panic or miss diagnoses. Depression or elevation of a millimeter or two in the right leads can be normal variant, especially in younger patients. But in the posterior leads or in a symptomatic patient, that same amount of change changes everything. Reciprocal changes tell you more than the primary changes sometimes. I always look at the opposite wall of the heart before calling anything a STEMI. T wave changes are the hardest to interpret honestly. Peaked T waves in V2 through V4 mean hyperkalemia until proven otherwise, but they also show up in normal variants called early repolarization. The difference is usually in the QT interval and the clinical picture. Inverted T waves in inferior leads can be normal in some people. Inverted T waves in V1 through V3 can be normal in others. Context is everything here and the cheat sheet can't give you that context.
What the Cheat Sheet Won't Help You With
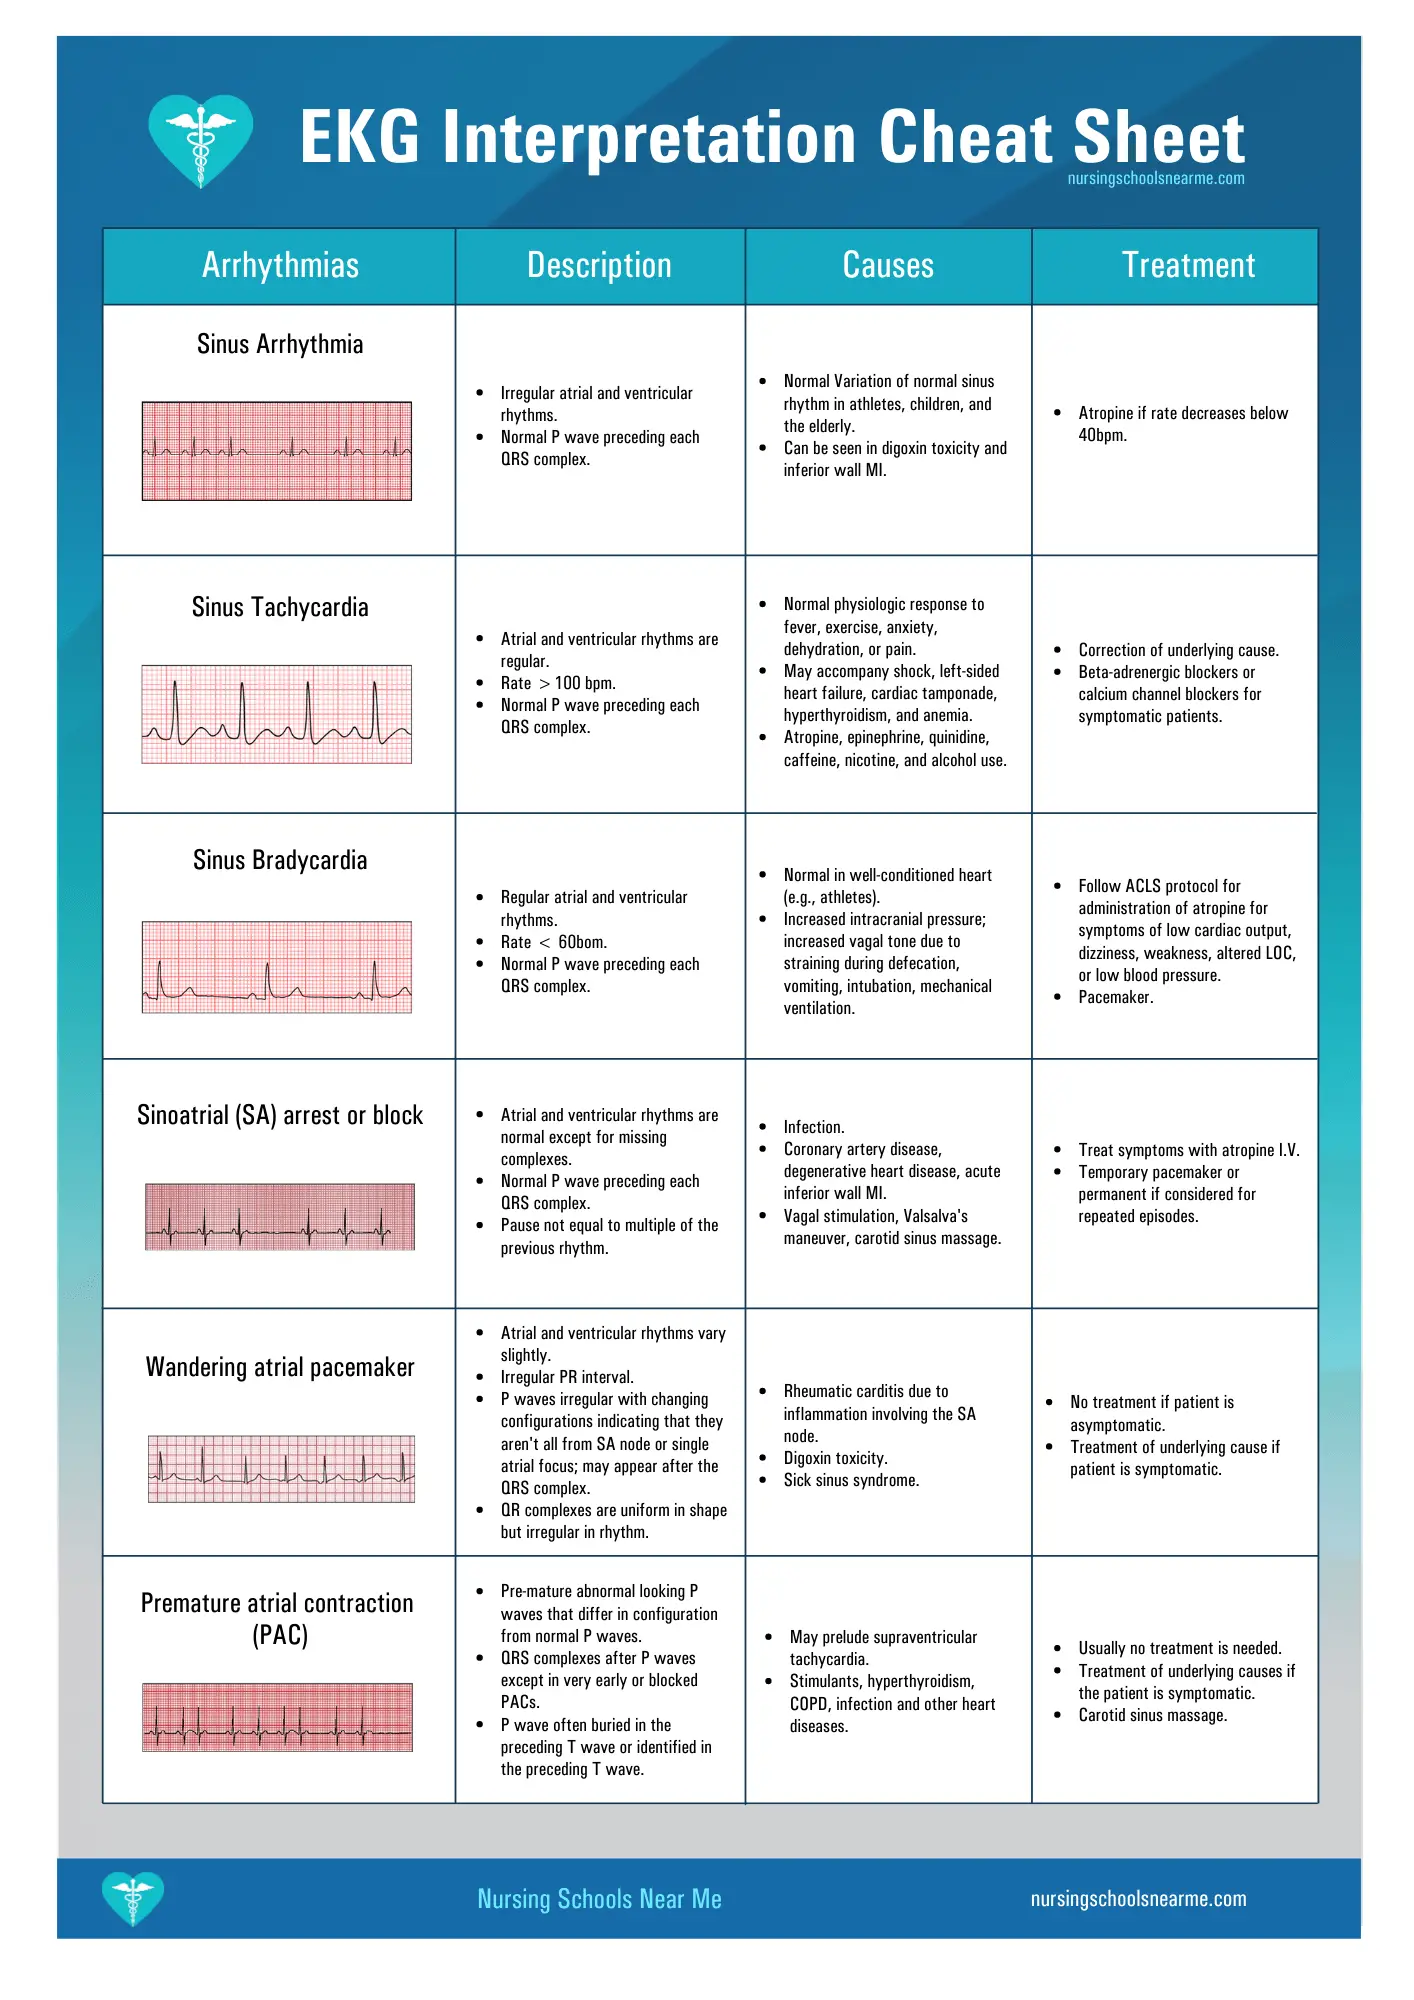
I had a patient come in with vague chest discomfort and the EKG looked basically normal except for a tiny bit of ST depression in V5. The cheat sheet says "non-specific ST changes, possibly ischemic, consider further workup." That's helpful in theory. In practice, that patient turned out to have a pulmonary embolism with right heart strain that wasn't obvious on the initial read. The cheat sheet didn't flag it because the S1Q3T3 pattern was subtle and mixed in with baseline noise from poor electrode contact. I caught it because I was looking at the clinical picture, not just the strips. Another thing the cheat sheet won't save you for: pacemaker rhythms. The P waves and the spikes look completely different depending on the device type and programming. First-generation cheat sheets I've seen just show one example and call it done. Real-world pacer strips are much more variable. My workaround was to add a separate section for paced rhythms with the common configurations I actually saw on the floor, not the textbook examples.
Get the Full Details
The Most Useful Part Is the One Nobody Writes Down
Bottom line, the cheat sheet is a starting point, not a diagnostic engine. It gets you through the mechanical steps quickly so you're not second-guessing basic measurements. But the actual interpretation — knowing when a finding matters and when it doesn't — comes from seeing enough strips to recognize patterns without needing to measure each one individually. The cheat sheet speeds up the process from about 5 minutes per strip down to under a minute for straightforward cases. For complex ones, it still takes time, and that's normal. If you're building one, start simple. Rate, rhythm, axis, intervals, ST segments, T waves, Q waves. That's the standard sequence. Add your own notes for the variations you actually encounter in your practice, not the ones from a textbook chapter you'll never see in real life.