What Ekg Monitor Technician Training Actually Looks Like
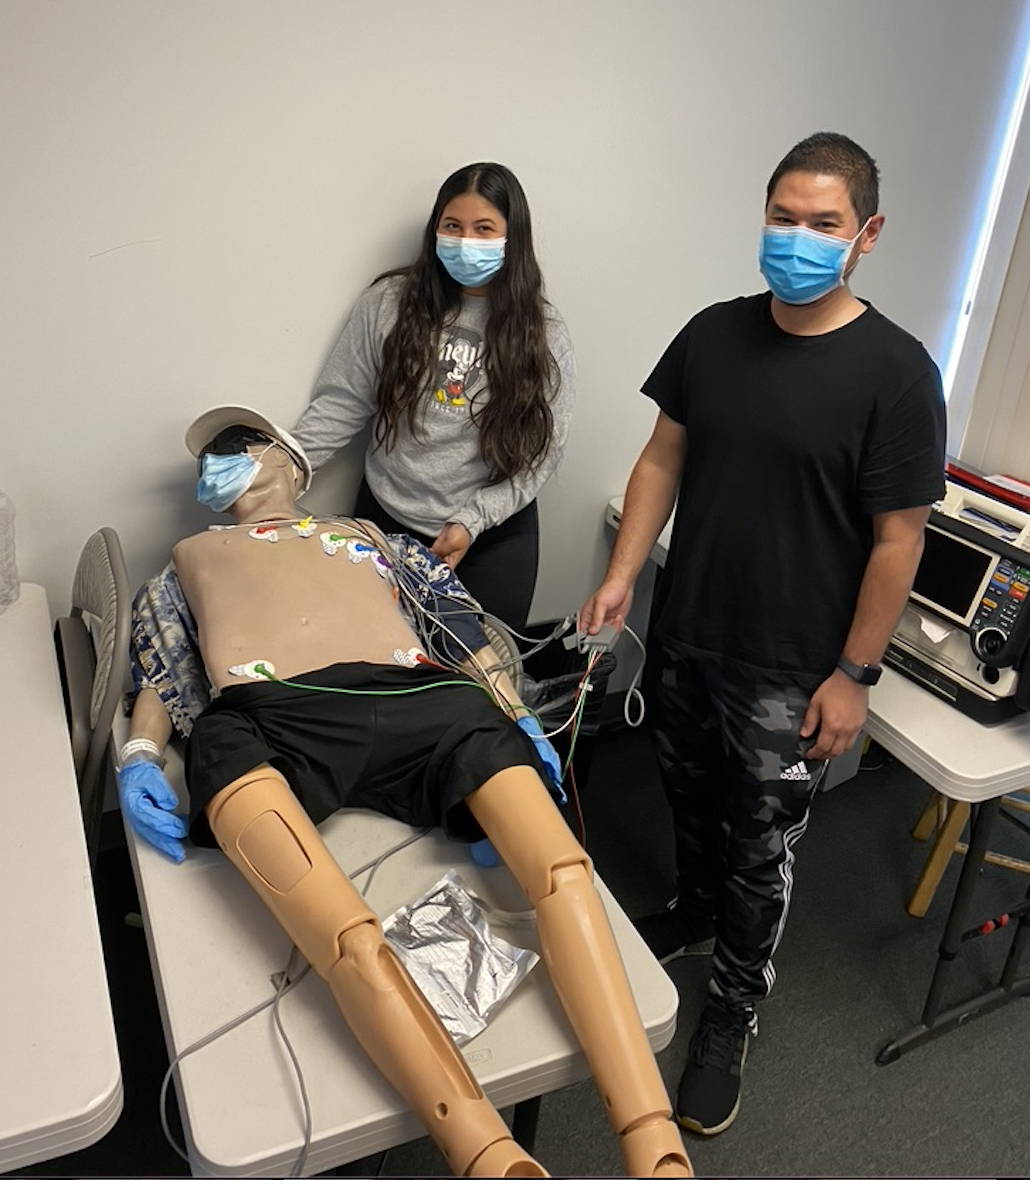
Most programs are six to eight weeks long if you go full-time. Part-time tracks stretch out to twelve weeks. You'll cover cardiac anatomy, rhythm recognition, EKG machine operation, basic pharmacology relevant to cardiac care, and patient communication. The certification exam usually happens at the end and is administered through organizations like the NHA or AMT. Passing requires a written test plus a hands-on practical component where you hook up a patient and produce a readable 12-lead tracing. Community colleges run the most structured courses, though they cost more and take longer. Private vocational schools move faster but quality varies wildly between them. Some hospital systems offer in-house programs that come with a job guarantee afterward. If you're looking at online options, be careful. You can't learn lead placement or artifact identification from a video alone. Any legitimate program will require in-person clinical hours, usually 40 to 80 depending on the state and the certifying body. I went through a program back in 2016 at a community college in Ohio. It was unglamorous. We had four weeks of classroom work, two weeks of lab practice on each other, and then a clinical rotation at a local hospital. The instructor had been a telemetry nurse for twenty years and she didn't sugarcoat anything. She'd look at our tracings and say things like "this is garbage, redo it" and move on. That turned out to be the most useful part of the whole program.
What the Training Covers in Practice
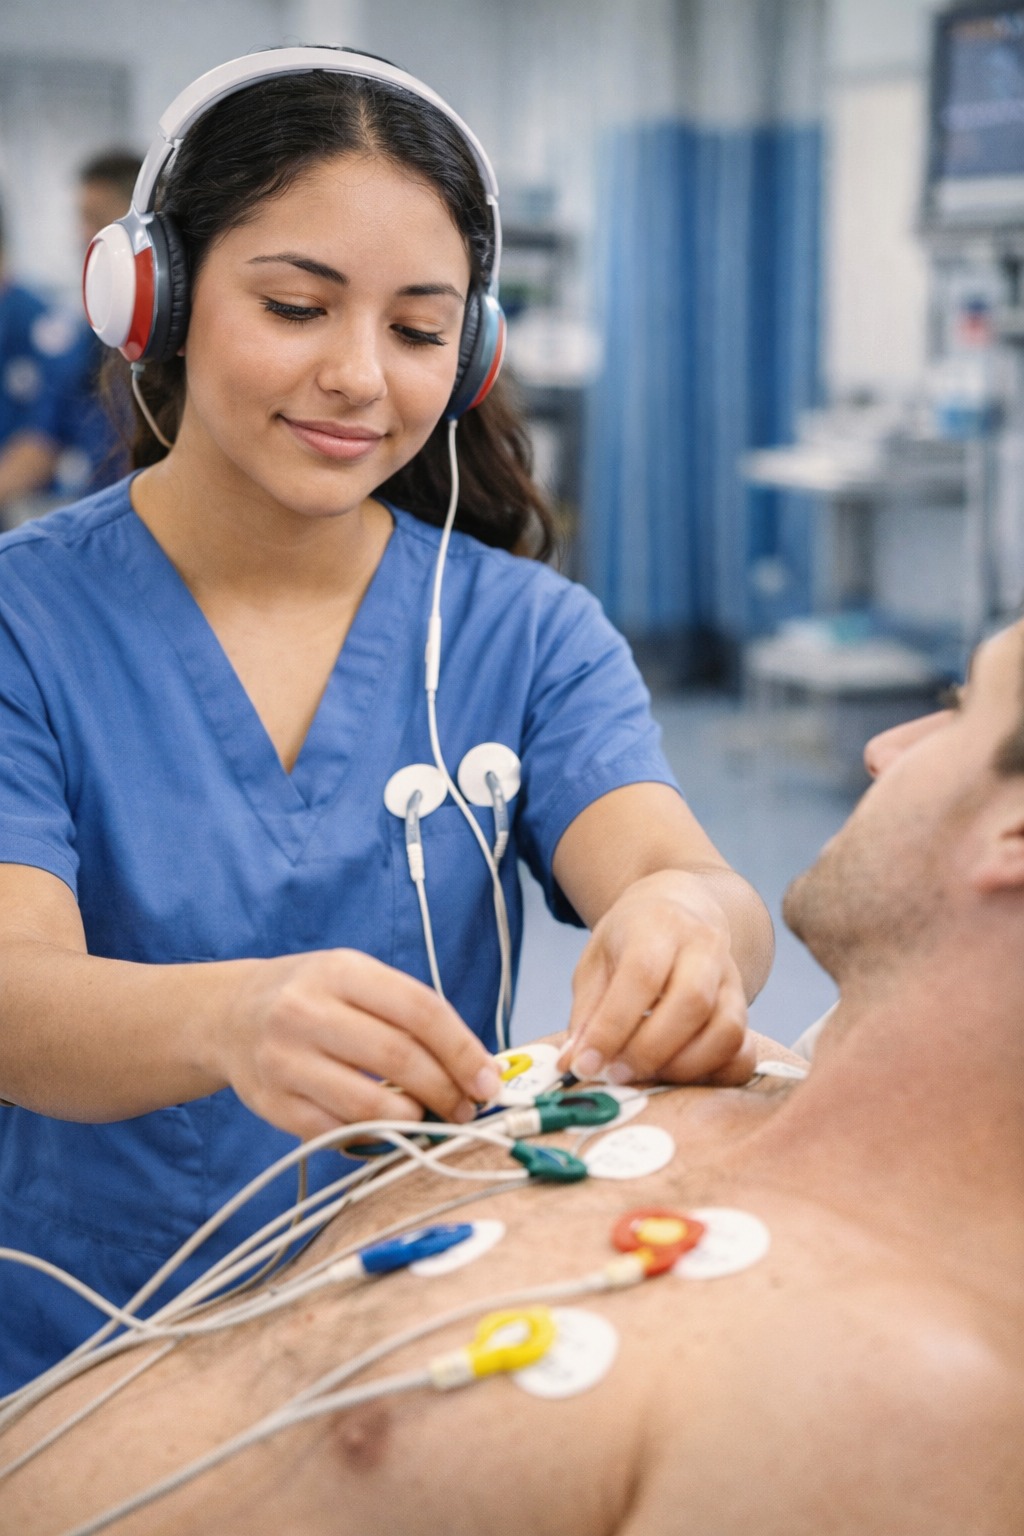
The first thing you learn is that nothing on a 12-lead EKG looks textbook-perfect. Real patients move. Real patients have amputations or breast implants that change lead placement. Real patients are diabetic with neuropathy, so their skin resistance is all over the map. Your training should spend significant time on these edge cases, not just on perfect sinus rhythm strip after perfect sinus rhythm strip. Lead placement is where most people struggle. The rib count matters. If you put V1 and V2 too high, you'll miss inferior wall changes. If you put V5 and V6 too far back, you'll lose lateral coverage. I once had a patient who was a competitive weightlifter with extremely developed pectoral muscles. The standard landmark for V4 was completely unreliable because the muscle belly shifted the anatomy. I ended up placing V4 one intercostal space lower than normal and still got a diagnostic-quality tracing. That kind of problem-solving doesn't come from a textbook. You'll also learn about common artifacts and how to eliminate them. Loose leads, patient movement, electrical interference from nearby equipment, poor skin prep. A bad ground strap can introduce 60-cycle interference that makes the entire tracing unreadable. In the training lab, we spent an entire session just learning how to properly abrade the skin and why alcohol prep isn't enough for patients with thick calluses or heavy body hair. Those details matter more than you'd think when you're trying to get a clean reading on a monitor in an ICU setting.
The Certification Exam
The NHA CET exam has two parts. The written section is multiple choice, about 100 questions, covering cardiac anatomy, rhythm identification, safety protocols, and equipment operation. The practical portion requires you to perform a full 12-lead EKG on a live person, produce a tracing that meets diagnostic quality standards, and identify at least three abnormalities from provided strip samples. You get 25 minutes for the practical, which sounds like a lot until you're dealing with a patient who won't stay still or has edema that makes locating landmarks difficult. Study materials from the certifying bodies themselves are decent but incomplete. I found that third-party practice exams from companies like CardioTec or MedCerts gave me better exposure to the types of rhythm strips they actually show on the exam. The written test loves throwing in question on pacemaker rhythms and artifact differentiation. Make sure you can tell the difference between a true ST elevation and baseline wander before you sit for the exam.
Get the Full Details

Limitations and What They Don't Tell You
Being an EKG monitor technician is not the same as being a cardiologist or even a telemetry nurse. You can recognize rhythms, but you can't diagnose. Your report will say "sinus tachycardia with frequent PVCs" not "patient is having an acute MI." If a physician asks you for a diagnosis, you hand them the tracing and you step away. That boundary gets blurry fast in busy hospitals where everyone is short-staffed and someone always needs "just a quick look" at a tracing. Learn to say no early. The job itself has real limitations. Automation has eaten into a lot of entry-level EKG positions. Many hospitals now use remote monitoring services where a technician in another state reads the tracings. Local EKG tech positions tend to go toward skilled nurses or respiratory therapists who already know the material. If your goal is purely to operate monitors, you might find yourself competing against people with much more clinical experience for the same openings. Pay is another factor. Entry-level EKG technicians in the United States typically make between $15 and $22 per hour depending on location and setting. Hospital positions pay better than outpatient clinics. Night shift differential helps. But don't expect this to be a career that carries you through without further education. Most people I know who stayed in the role for more than a few years eventually moved into sonography, nursing, or cardiac rehabilitation.
A Few Things That Actually Help
Get comfortable with your hands before you start. Lead placement is a motor skill. You'll do hundreds of them during training and the repetition builds muscle memory faster than you'd expect. Practice on friends and family. Ask them to hold still while you count ribs and mark positions. It sounds trivial but it saves you from making embarrassing mistakes in front of actual patients. Download free EKG rhythm libraries and practice identifications daily. There are several good ones online. The American Heart Association has open-access strips. Use them. Spend ten minutes a day looking at strips until you can identify a rhythm without hesitation. This skill doesn't develop overnight and it's the core of what you'll be tested on and doing on the job. Keep a logbook of every tracing you produce during clinical hours. Note the patient's condition, any difficulties you encountered, and what you learned. When you're studying for the practical exam, that logbook becomes your personal reference for the kinds of problems you've already solved. I looked back at mine and realized I'd only ever seen two atrial fibrillations with rapid ventricular response before the exam. The practical threw three at me. I was sweating through the whole thing.
The training works if you put in the hours. It's not particularly hard material but it requires consistent practice and attention to detail. Show up, do the work, and don't skip the clinical rotation no matter how much you want to rush through it. That's where you learn what actually happens when you're standing next to a monitor with a real patient in front of you.