Reading EKG strips isn't as bad as you think if you stop overcomplicating it
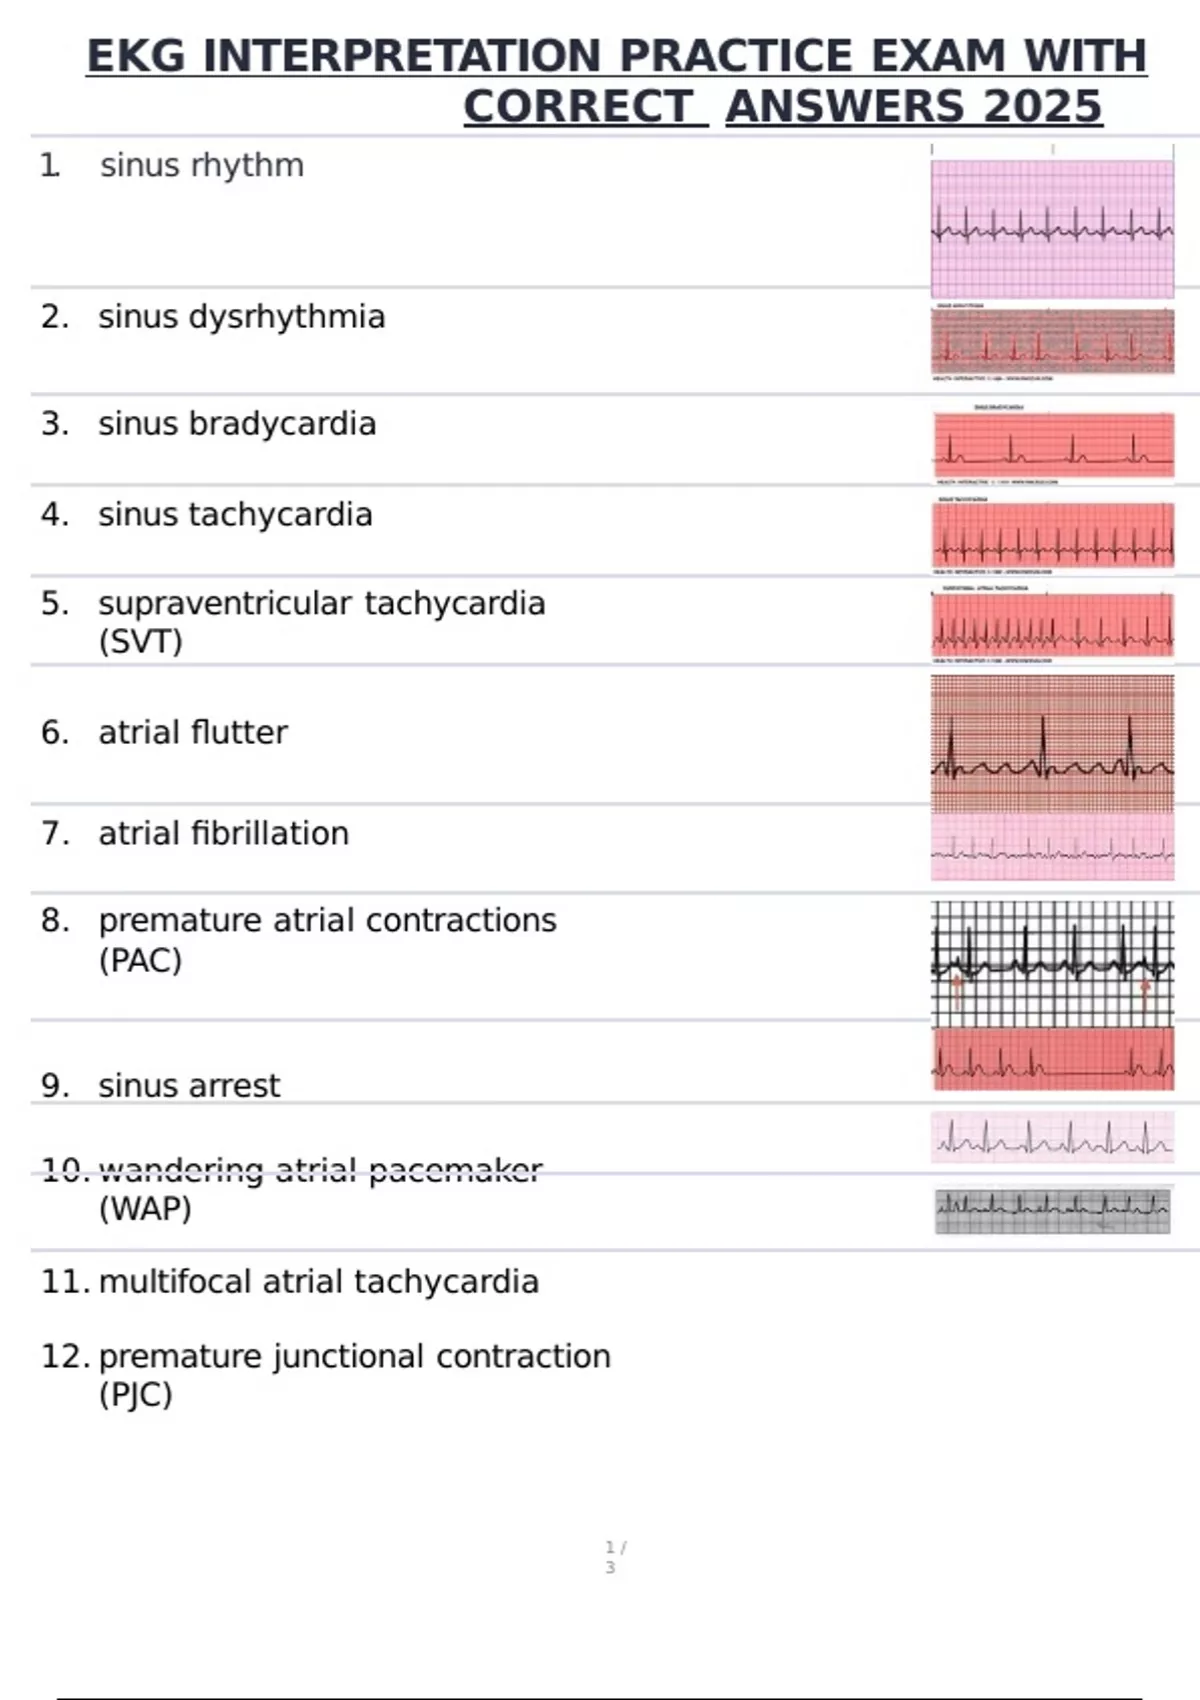
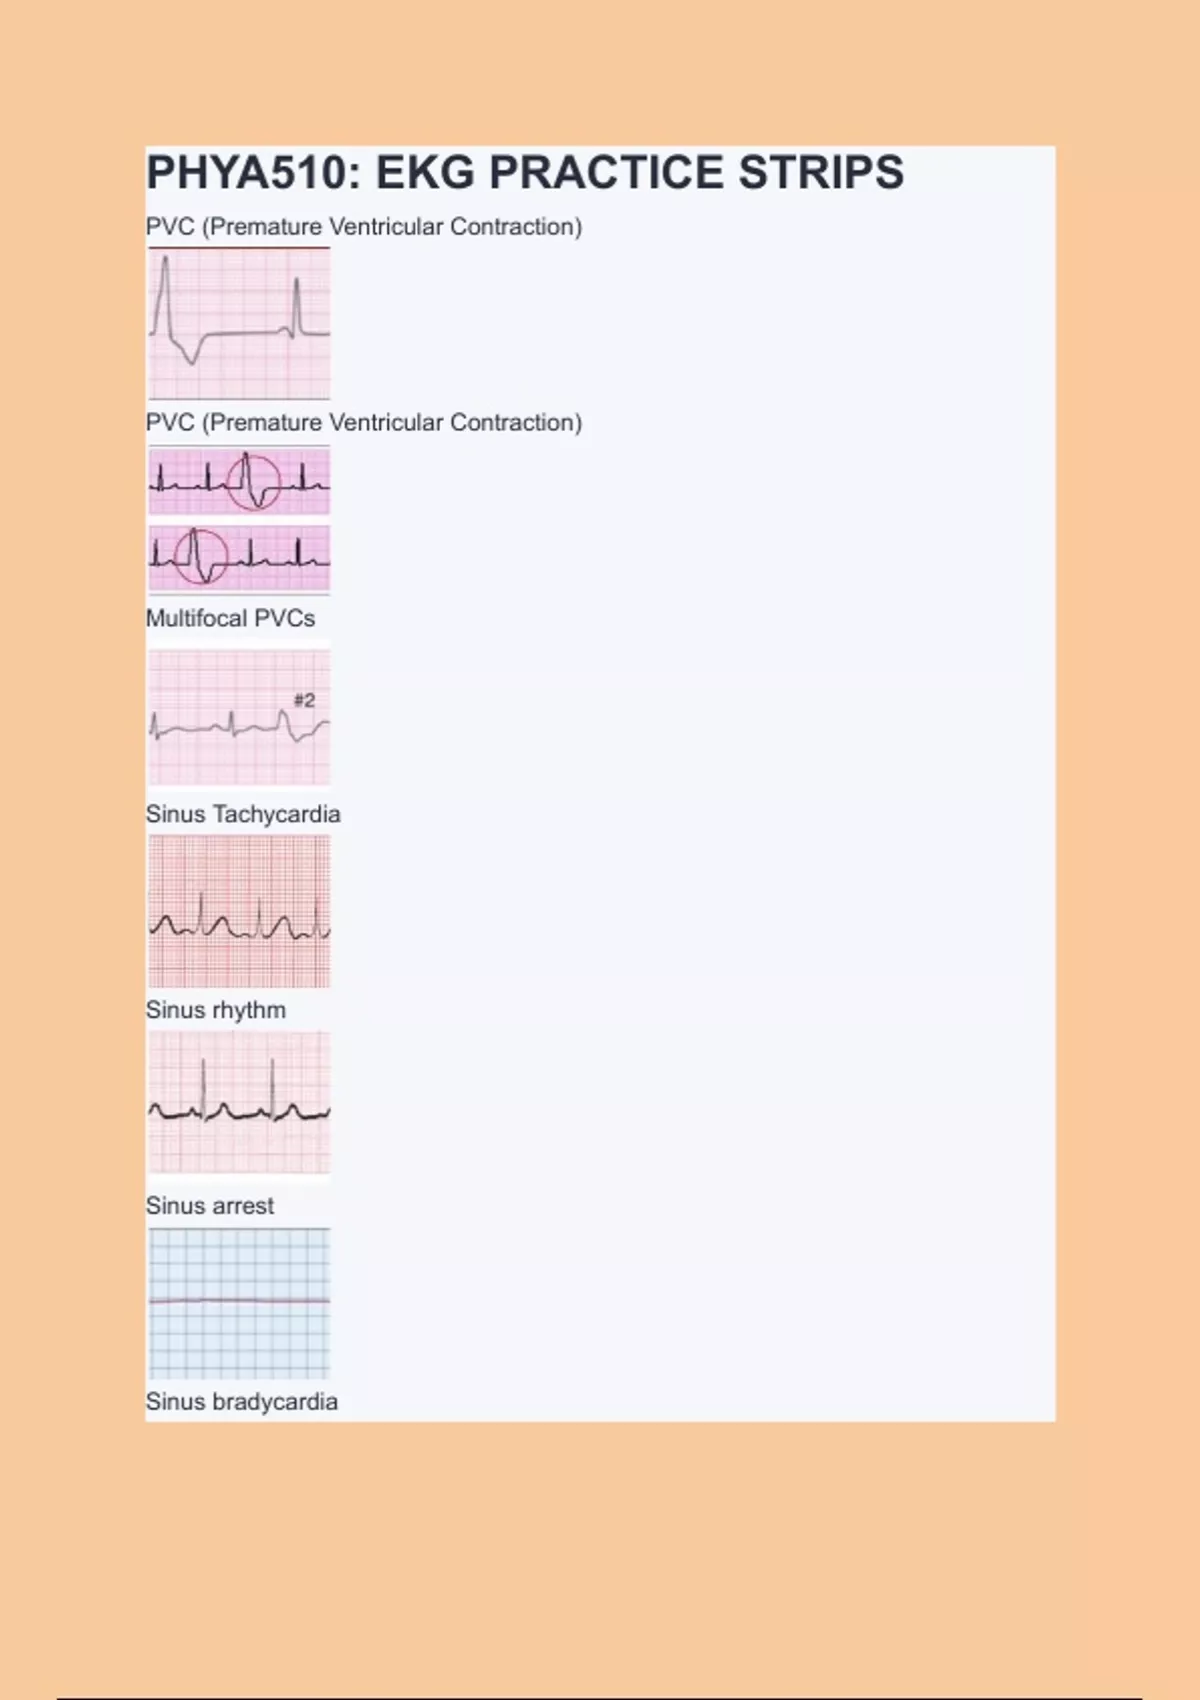
I've spent years going through telemetry and EKG strips at 2 AM when the junior staff panics because they see something that looks like Vtach but is actually just a weird artifact. The difference between a clean reading and a misdiagnosis usually comes down to having solid practice material, and that's where Ekg Practice Strips With Answers actually matters. Most people learn rhythm identification by watching someone else read a strip, or by memorizing textbooks that describe rhythms in abstract terms. Neither approach really works until you're staring at a real strip under pressure. What helps is seeing the exact same strip with a clear breakdown of what's happening, why, and what the treatment pathway should be. That's the whole point of practice strips with answers built into them.
Ekg Practice Strips With Answers for real clinical prep
The most common way I see these being used is either through printed strip books, digital apps that simulate strip review, or shared folders of de-identified patient EKGs with annotated answers. The format varies but the principle stays the same. You look at the strip, you make a call, then you check your work against the provided answer. If your answer matches, you move on. If it doesn't, you go back to the strip and figure out exactly where your reasoning broke down. Here's something most people miss about reading practice strips. The rhythm interpretation is only half the equation. The better ones will also flag the axis deviation, the chamber enlargement signs, the acute ischemia patterns, the drug effects, and any electrolyte abnormalities visible in the tracing. A strip showing peaked T waves is fine to identify as hyperkalemia, but the strip with a prolonged QT and a U wave buried under the T is where you actually learn something useful. I ran into this exact problem last year. A resident brought me a strip that looked like normal sinus rhythm at first glance, maybe slightly bradycardic. The practice answer key marked it as third-degree AV block with a junctional escape. I couldn't see it. Not because I didn't know what third-degree block looked like, but because the P waves were tiny, buried in the QRS, and the PR interval was varying randomly across leads. What finally clicked for me was switching to lead II and going through each beat individually instead of trying to read the whole strip at once. I started marking each QRS with a pencil, then going back and hunting for the P waves between them. Once I did that, the dissociation became obvious. That's the workaround I use now: when a strip resists my initial read, I slow down to single-beat analysis and use a physical marking tool, whether that's a pen on paper or a highlighter on a screen. It sounds tedious but it catches everything.
Another thing worth noting about practice materials. A lot of commercially available strips are too clean. Real patient EKGs have baseline wander, muscle tremor, electrode pop, and lead reversal issues. If your practice strips are all perfect sinus rhythms and textbook arrhythmias, you're training yourself for a hospital that doesn't exist. I specifically look for materials that include noisy strips, artifacts, and incomplete lead sets. The noise forces you to do actual work instead of pattern-matching, and pattern-matching is exactly what fails you during a code. There's also a counter-intuitive thing about pacing spikes that everyone gets wrong. Beginners tend to dismiss any strip with pacing spikes as "non-diagnostic" or too hard to interpret. That's backwards. A paced rhythm is one of the easiest strips to read correctly once you know the rules, and it's far more common in real practice than most arrhythmia strips. I've seen residents hesitate on a clean ventricular paced rhythm because they didn't want to commit to an answer, while simultaneously misreading a messy atrial fibrillation with rapid ventricular response. The paced strip had a pacing spike before every QRS, no P waves, and a wide QRS. Diagnosis: ventricular paced rhythm. The atrial fibrillation strip had an irregularly irregular rhythm with no discernible P waves and a rate around 140. Diagnosis: afib with RVR. The first one is mechanically easier to identify. The second one looks scarier but is actually more straightforward if you stop looking for P waves and accept that they're absent. When it comes to sources for these practice materials, the usual suspects are the American Heart Association rhythm strips, various nursing and paramedic exam prep sites, and some university ECG libraries. There are also PDF compilations that circulate in med student and residency groups that are honestly some of the best because they're curated by people who actually work in the field rather than marketing teams. The caveat with those is that the answer quality varies wildly. Always cross-check. I've seen three separate practice PDFs with the same strip labeled differently, and two of them were wrong.
Get the Full Details
If you're trying to build a personal practice routine, start with basic rhythm identification, then layer in axis determination, then hypertrophy patterns, then ischemia and infarction localization, and finally drug and electrolyte effects. Each of those categories has its own visual signatures that take time to internalize. Trying to learn all five at once slows everything down. I typically spend about two weeks per category on focused practice before mixing them together. That's roughly 30 to 50 strips per category, ideally with answers I can verify against a second source. The biggest bottleneck most people hit is not the identification itself but the speed. Reading a strip correctly takes you thirty seconds. Reading it correctly in three seconds during a code is a different skill entirely. That gap closes with repetition, but only if the repetition is deliberate. Flipping through fifty strips without actively making a diagnosis on each one does almost nothing for your speed. You have to force yourself to commit to an answer before looking at the answer key, every single time. One more practical note. If you're studying for a certification exam like the CCRN, CEN, or NREMT-P, the practice strips they use lean heavily toward high-yield rhythms. You'll see atrial fibrillation, atrial flutter, sinus tach, sinus brady, first-degree block, Mobitz type I, Mobitz type II, third-degree block, Vtach, Vfib, asystole, PEA, and maybe a few junctional rhythms. The less common stuff like Wolff-Parkinson-White or Brugada rarely shows up in those exams. Focusing your practice on the high-yield set first is the faster path to passing, even if it feels incomplete from a clinical standpoint.
The reality is that Ekg Practice Strips With Answers work because they close the feedback loop that most self-study misses. You make a decision, you get immediate verification, you correct the error, and you repeat. That's it. No fancy method. Just a lot of strips, honest mistakes, and a willingness to look at your wrong answers without glossing over them. The ones who improve fastest are the ones who study their incorrect reads the most, not the ones who get the highest initial scores.