Why EKG Practice Tests Feel Different From Real Exams
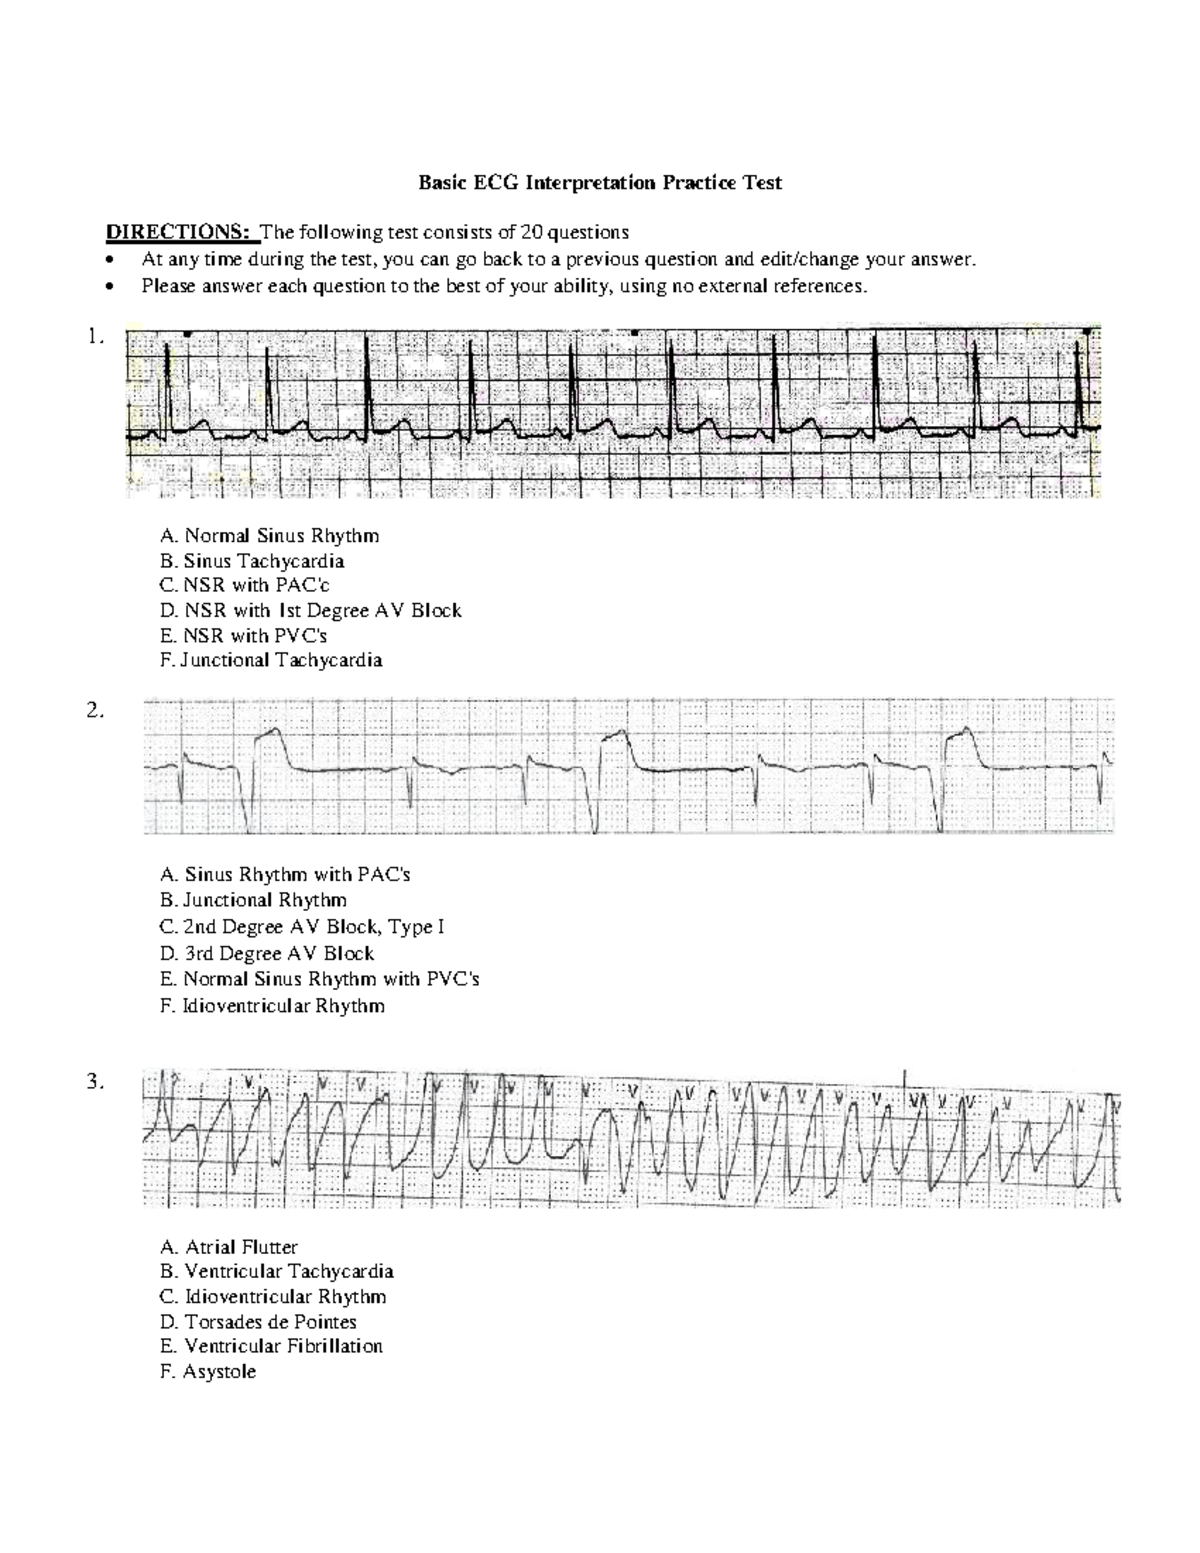
Most people approach EKG practice exams the wrong way. They treat them like trivia questions instead of pattern recognition training. The difference matters more than you'd think when you are under time pressure with a 12-lead strip in front of you. I spent years running these tests in clinical settings before I started teaching others how to work through them efficiently. One thing I learned pretty quickly is that multiple choice EKG practice tests are not about memorizing definitions. They are about developing a visual reading speed that becomes automatic through repetition.
What You Should Know Before Starting Your Ekg Practice Test Multiple Choice Session
Here is the basic setup. You will be shown rhythm strips, sometimes single leads, sometimes full 12-lead layouts. Each question asks you to identify a rhythm disturbance, conduction abnormality, or ischemic change. The options usually include the correct answer alongside two or three plausible distractors that share features with the real diagnosis. The key insight most beginners miss is that distractors are never random. A test writer will put atrial fibrillation next to multifocal atrial tachycardia because both show irregular rhythms. They put first degree AV block next to second degree Type I because both show prolonged PR intervals. Recognizing this pattern helps you eliminate wrong answers faster than you might expect.
The Actual Reading Method I Use
I go through each strip in the same order every time. It looks like this. First I check the rhythm strip, usually lead II, for regularity. Is it regular, irregularly irregular, or regularly irregular? That single observation splits most questions into two groups instead of four. Next I look at the rate. Not the exact number yet, just whether it is below 60, between 60 and 100, or above 100. This eliminates entire categories of dysrhythmias on its own.
Get the Full Details
Then I examine P waves. Do they exist before every QRS? Are they upright or inverted? Do they look normal or abnormal in shape? This step separates sinus rhythms from atrial rhythms and junctional rhythms almost instantly. After that I measure the PR interval if P waves are present. Normal range is 3 to 5 small squares. Longer than that suggests AV conduction delay. Shorter than 3 squares points toward pre-excitation syndromes or junctional rhythms. Finally I look at the QRS width and axis. Wide QRS means ventricular conduction problem. Narrow QRS with abnormal axis means fascicular block or alternate conduction pathway.
That process takes about 20 to 30 seconds per strip once you have done it enough times. On my first few hundred strips it took me about a minute and a half. The difference is purely mechanical at that point.
A Specific Problem I Ran Into
There was a test case that caused me real trouble for about two weeks. It was a strip that showed what looked like atrial flutter with variable block, but the flutter waves were tiny and hidden inside the ST segments. The distractor answers included atrial fibrillation, sinus rhythm with frequent PACs, and junctional tachycardia with retrograde P waves. The solution came from a trick that is not in most textbooks. I placed a caliper or even a piece of paper with evenly spaced marks over the baseline between QRS complexes. When I measured the distance between those hidden undulations, they were exactly 150 milliseconds apart, which translates to a atrial rate of 240 beats per minute. That confirmed atrial flutter. The variable block meant every other flutter wave conducted, which is why the ventricular response looked irregular. If you ever get stuck on a strip that looks like nothing clear, check for hidden atrial activity between QRS complexes. Most of the time it is the answer hiding in plain sight.

How to Structure Your Practice
Random practice is okay for warmups, but systematic practice produces better results. I found that grouping by rhythm category works best. Spend one session on supraventricular tachycardias. Do at least 30 strips. Then switch to ventricular arrhythmias. Do another 30. Then do blocks and conduction abnormalities. After you finish a category, mix everything together. This forces your brain to recognize the diagnostic features instead of relying on context clues from the question order. Mixed sets are closer to actual exam conditions and they reveal gaps in your knowledge faster. One study method that actually works: write down your answer for each strip before you look at the options. This prevents answer choice bias. Most people pick the wrong answer because the first option looks right, not because the strip matches it. Writing your own diagnosis first keeps you honest.
Common Pitfalls That Cost Points
Missing a left bundle branch block because you did not measure the QRS duration. That happens constantly. Any QRS wider than 120 milliseconds with the right morphology is LBBB until proven otherwise. Do not guess based on appearance alone. Measure it. Calling everything irregular atrial fibrillation. Atrial fibrillation has no P waves and no regular pattern. Some other arrhythmias look similar at first glance. Multiform PVCs, sinus arrhythmia, and frequent ectopy can all look chaotic if you do not look carefully at the baseline between QRS complexes. Overcalling ST elevation as acute MI. Early repolarization, pericarditis, and Brugada pattern all produce ST changes that look dangerous but are not the same thing. Look at the morphology. Concave upward ST elevation in multiple leads suggests pericarditis. Convex upward ST elevation in a coronary territory suggests infarction. Reciprocal changes matter too.
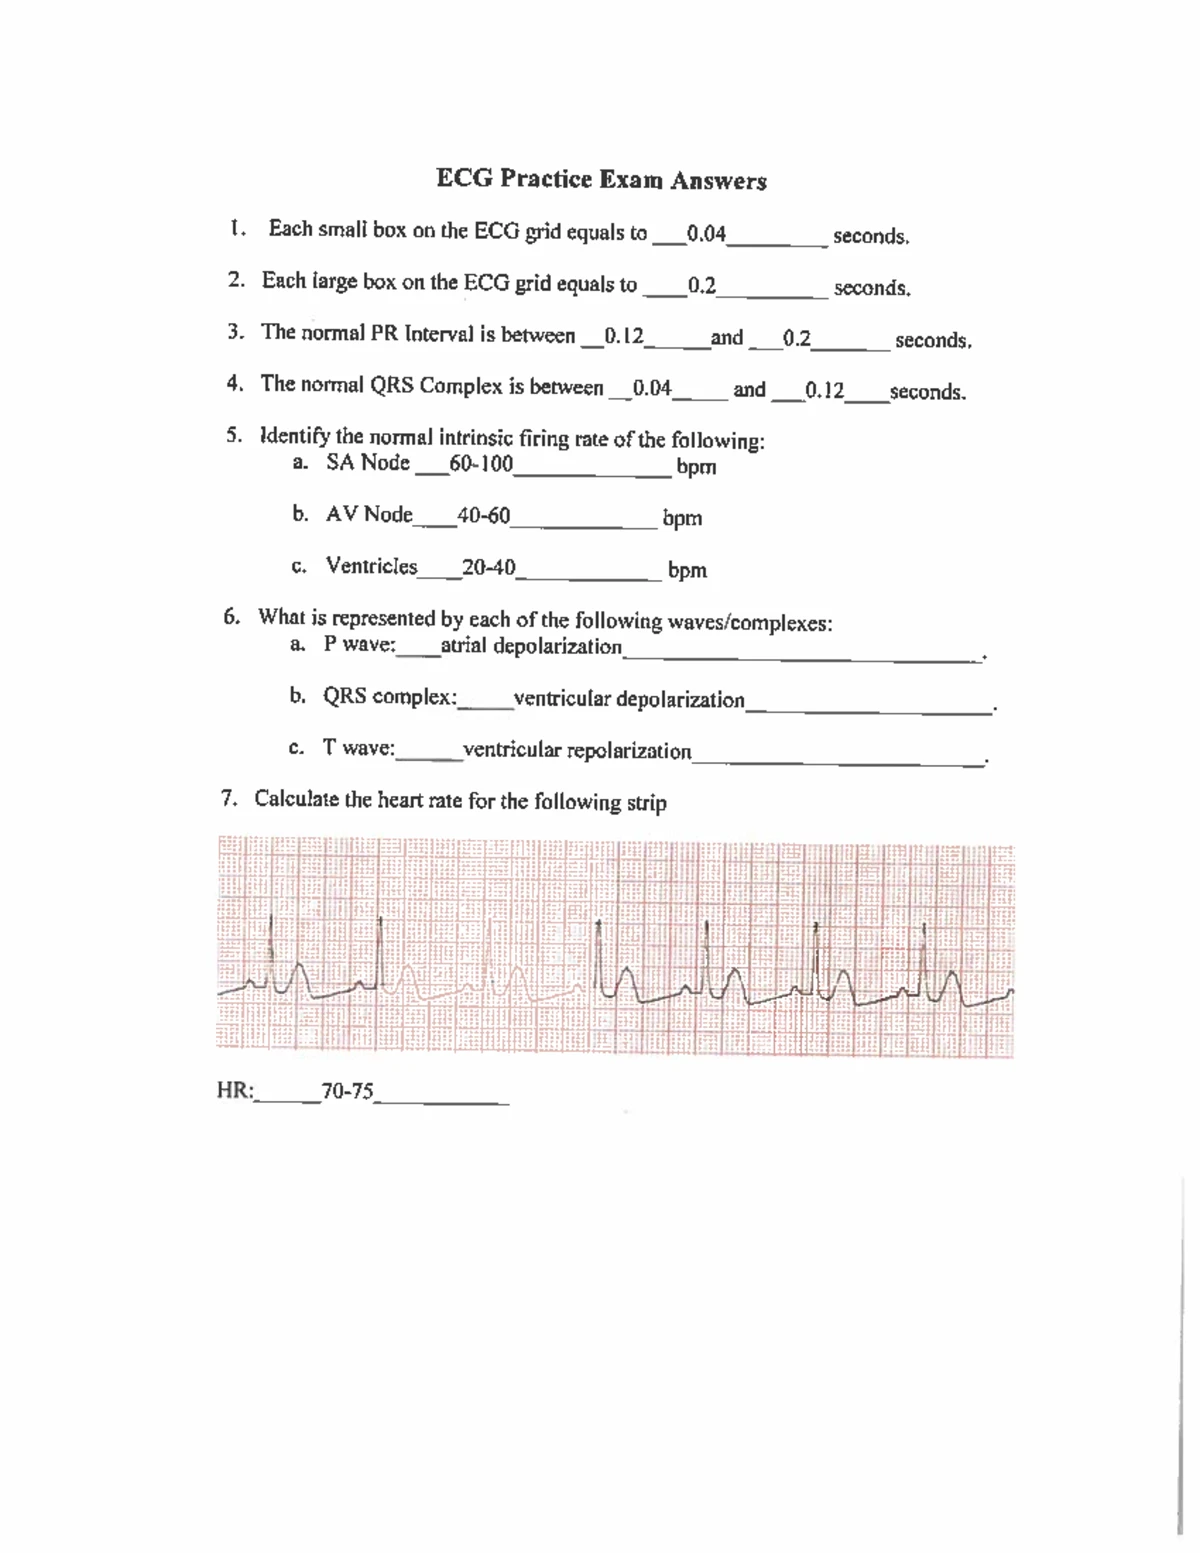
Forgetting to check calibration. Some strips are recorded at half speed or with reduced voltage. If the paper speed is 25 mm per second, each small square is 0.04 seconds and each large square is 0.20 seconds. If it is 50 mm per second, those numbers double. Misreading the calibration throws off every measurement you make after it.
Where to Find Quality Practice Material
There are several sources worth looking at. The American Heart Association publishes sample EKG questions that match the style of certification exams. Cardiology division websites from major medical centers often have free quiz banks with detailed explanations. The book LEADSS 12-Lead ECG: The Method by David Leeb has practice strips with thorough walkthroughs. Another solid resource is Rapid Interpretation of EKG's by Dale Dubin, which has a question bank at the end of each chapter. These are not the same as official exam prep but they build the same skills. Online platforms like ECG Wave-Maven from Harvard and the UC San Diego ECG library provide real patient strips with answers. The benefit here is that the rhythms are not artificially simplified. They show the kind of noise, artifact, and atypical presentations you will actually see on a test.
Limitations of Multiple Choice Practice
Multiple choice practice tests have a real weakness. They strip away clinical context. In real practice, you never see an EKG in isolation. You have the patient's age, symptoms, medications, electrolyte levels, and history. A test question might show ST depression and ask you to identify it as ischemia when the actual cause is tachycardia-induced demand ischemia or digoxin effect. Another limitation is that well-written practice questions teach you to recognize patterns, but they do not teach you what to do after recognition. Knowing the rhythm is one thing. Managing a patient with that rhythm is another. If your goal is clinical competence, pair your multiple choice practice with case-based learning where you have to decide on treatment. Some practice tests also rely heavily on classic textbook examples. Real exams and real patient strips are messier. The rhythms are often borderline or mixed. Preparing exclusively with clean textbook strips can create a false sense of confidence when you encounter the kind of strip that makes you second guess yourself.
Bottom Line
Regular practice with a structured method beats random attempts every time. Focus on the systematic reading approach, write your own diagnosis before looking at options, and mix your practice sets to build true pattern recognition. The material is available, the methods work, and the improvement comes from doing the work consistently rather than looking for a shortcut.