How to Actually Pass the Ekg Rhythm Interpretation Exam
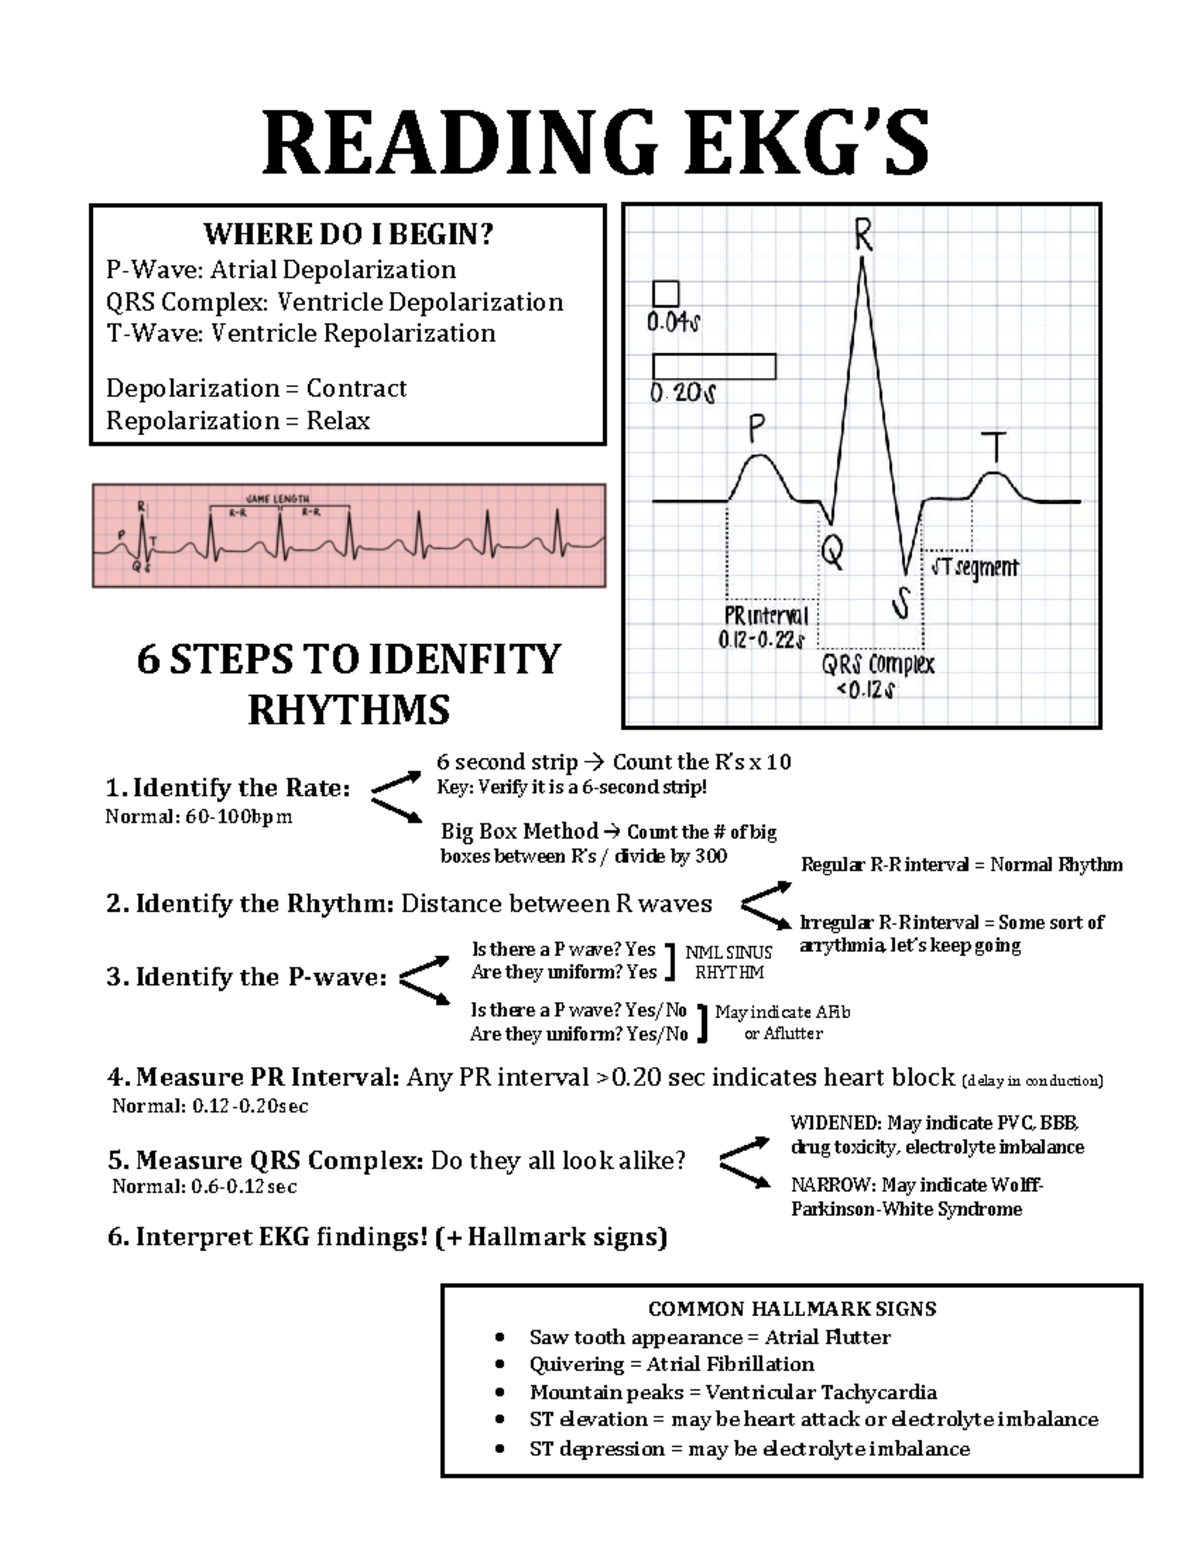
The standard systematic approach to EKG rhythm interpretation is usually taught as a linear checklist: rate, rhythm, P-waves, PR interval, QRS width, axis, then ST segments. Most students learn it that way, memorize the steps, and then freeze when they see an unfamiliar strip under time pressure. That is because the checklist approach assumes every strip will present its features in an orderly fashion, which is not how actual exam questions are designed. I started approaching rhythm interpretation differently during my second year of clinical rotations, and it carried over into my certification exams. The method I use now is not fundamentally different, but the order and priority of steps is shifted. You look at the QRS complexes first to determine if the ventricles are being driven from above or below the bundle branches. Then you check for consistency in the R-R intervals across at least three full cardiac cycles. Only after establishing whether the ventricular rhythm is regular do you move backward to assess atrial activity. This reverse engineering cuts through a lot of the noise that distracts beginners.
Practical Steps for the Ekg Rhythm Interpretation Exam
Start by pulling a caliper or using two fingers to measure the distance between two consecutive R waves on the printed strip. If the distances are identical, the rhythm is regular. If they vary, it is irregular. Write that down immediately before looking at anything else. A regular narrow-complex tachycardia at 170 beats per minute is almost always SVT. An irregular narrow-complex tachycardia is a completely different category and requires a different diagnostic path. Getting that first classification right determines the rest of your analysis. Once you know the basic rhythm character, look for P-waves. Do not hunt for them in every lead. Scan leads II and V1 first. In lead II, P-waves should be upright in normal sinus rhythm. In V1, they may be biphasic, which is normal. If you see a P-wave before every QRS with a consistent PR interval between 0.12 and 0.20 seconds, you are dealing with sinus rhythm and can move on to classification. If the P-waves are absent or appear as flutter waves, you are in a different territory entirely. For the exam itself, the strips are rarely ambiguous in a way that requires you to distinguish between highly similar rhythms like junctional tachycardia versus atrial tachycardia with aberrancy. They tend to test you on the common dysrhythmias you will actually encounter: sinus brady, sinus tach, first-degree block, Mobitz Type I, Mobitz Type II, third-degree block, atrial fibrillation, atrial flutter, PVCs, VTach, and VFib. Your study time is better spent becoming fast and accurate on those rather than drilling rare edge cases.
Here is something most review materials do not emphasize enough: the relationship between the atrial rate and the ventricular rate is often the fastest way to identify high-grade block without getting lost in measuring every single PR interval. In a third-degree AV block, the atria and ventricles beat independently, so the ventricular rate will be consistently slower than the atrial rate, and the PR interval will vary randomly from beat to beat. On an exam strip, if the P-P intervals are regular and the R-R intervals are regular but the two rates are different, you have complete heart block. You do not need to measure every PR interval to confirm it. I ran into a specific problem during a licensing exam a few years back that I still think about. The strip showed what looked like a wandering atrial pacemaker at first glance because the P-wave morphology changed slightly across the leads. I spent about forty-five seconds trying to figure out if the PR intervals were varying or not. What I eventually realized was that the strip had significant baseline wander, which was distorting the P-wave appearance in certain leads. The rhythm was actually normal sinus with artifactual P-wave distortion. My workaround was to stop looking at individual lead morphology and instead trace the rhythm strip with my finger on the paper, focusing only on the timing relationship between each QRS and the preceding deflection. The timing was consistent. The P-waves were real, just visually distorted by the baseline. That strip cost me unnecessary time and mental energy, and it taught me to prioritize timing over morphology when the strip quality is questionable. Another counter-intuitive point that catches people off guard: a wide QRS does not automatically mean ventricular tachycardia. Bundle branch blocks produce wide QRS complexes too, and they have their own recognizable patterns. Right bundle branch block shows an rSR' pattern in V1 with a wide S wave in V6. Left bundle branch block shows a broad monophasic R wave in V5 and V6 with deep S waves in V1. If you see a wide-complex rhythm and immediately label it VTach without checking for these established BBB patterns, you are making a diagnostic error. The exam will test this distinction, usually by giving you a strip with an underlying BBB and asking you to classify the rhythm correctly.
Get the Full Details
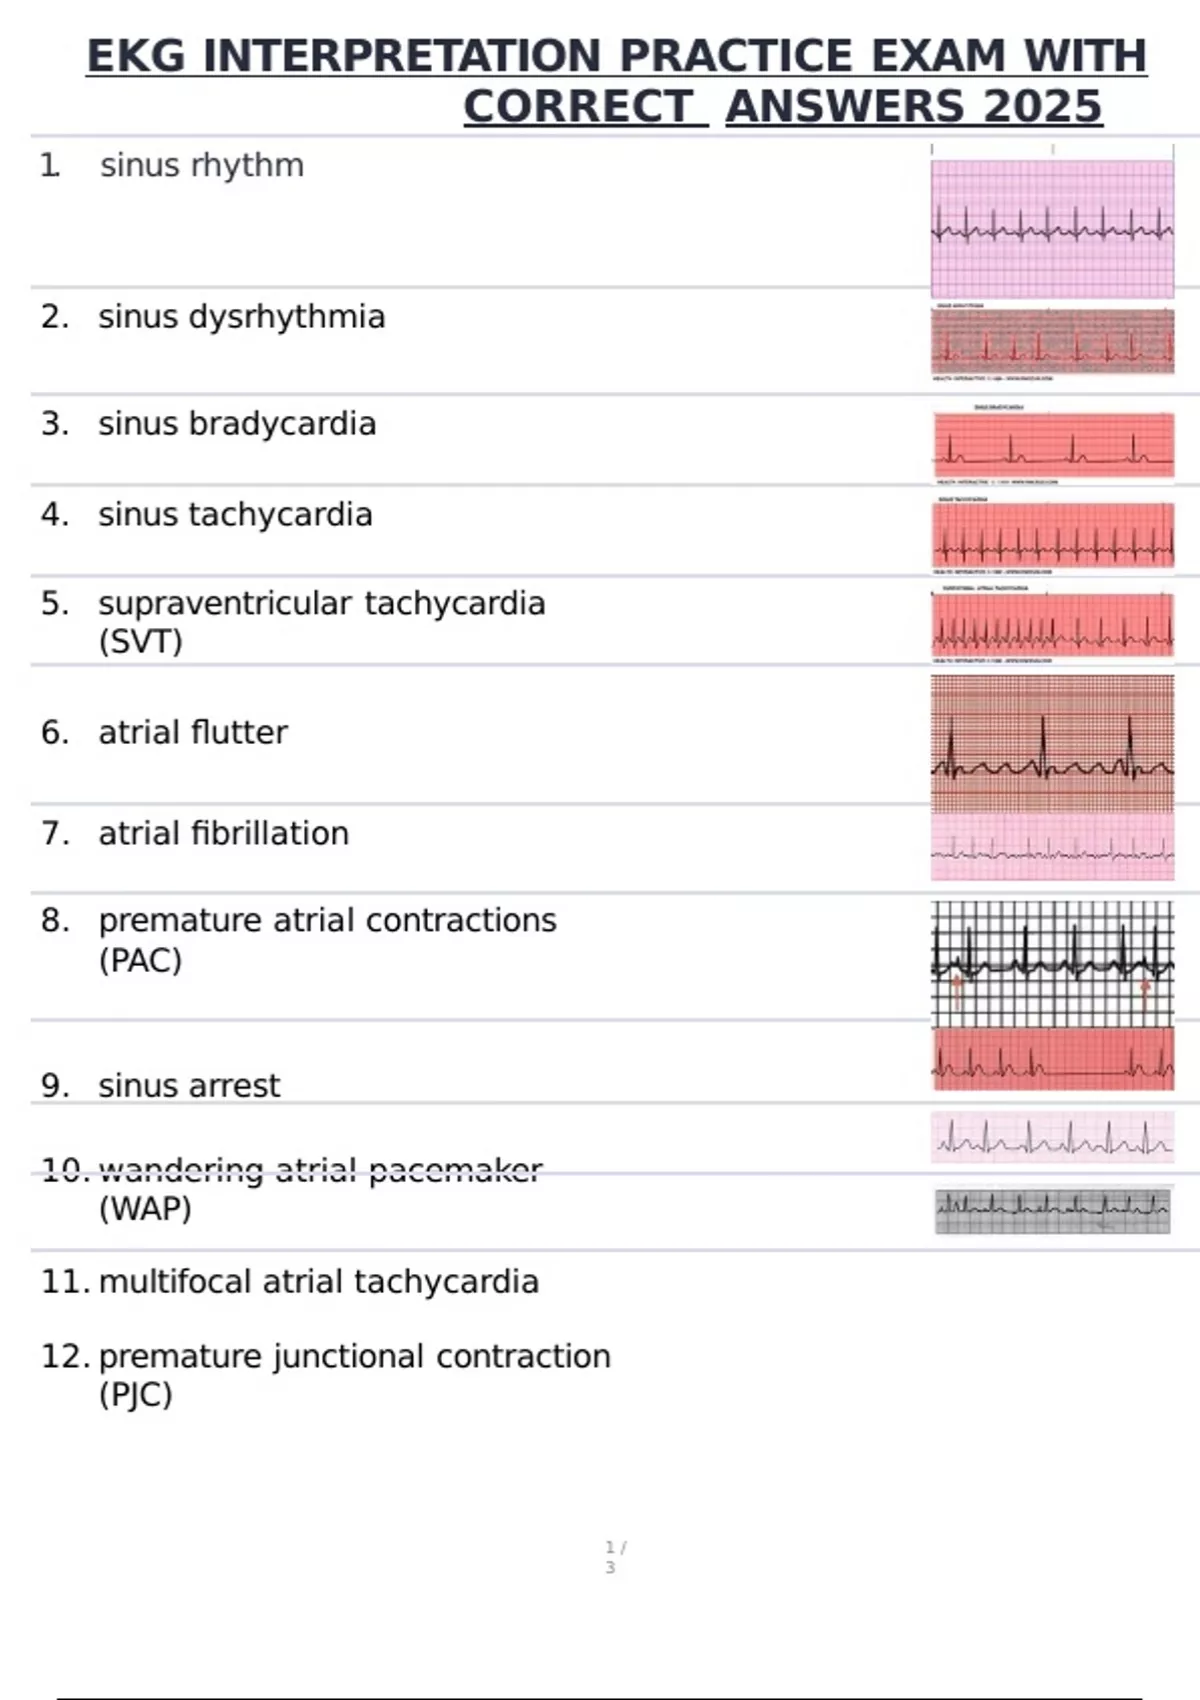
When you are studying, use actual EKG paper strips rather than schematic diagrams. Real strips contain artifact, baseline drift, and subtle variations that diagrams smooth over. Many review books show textbook-perfect runs of VFib or perfectly regular sinus brady, but the exam occasionally includes strips with motion artifact or electrode displacement that can make a normal sinus rhythm look like an arrhythmia at first glance. The workaround is straightforward: check multiple leads. If the apparent arrhythmia disappears in another lead channel, it is artifact. If it persists across all visible leads, it is real. There is a practical limitation to rapid rhythm recognition that you should be aware of. When you are racing against a timer and scanning strips quickly, you become vulnerable to pattern-matching errors. Your brain sees a wide-complex tachycardia and immediately jumps to VTach because that is the most dangerous and most commonly tested diagnosis. But supraventricular tachycardia with aberrant conduction can look nearly identical, and misidentifying it has real consequences. Under exam conditions, this risk is mostly academic since the correct answer is usually the one the question writer intends, but in practice it is a genuine diagnostic challenge. The only reliable safeguard is to verify that the QRS is truly wide by measuring it against the standard grid before committing to a diagnosis. For study resources, the most useful material I found was a combination of free online EKG libraries with searchable rhythm strips and a self-made flashcard system. I created cards that had a rhythm strip image on one side and the diagnosis plus the key identifying feature on the other. The key feature was always something specific and observable, like "irregularly irregular with no discernible P-waves" for atrial fibrillation rather than just the diagnosis name. This forced me to anchor each rhythm to concrete visual criteria rather than relying on rote memorization of labels.
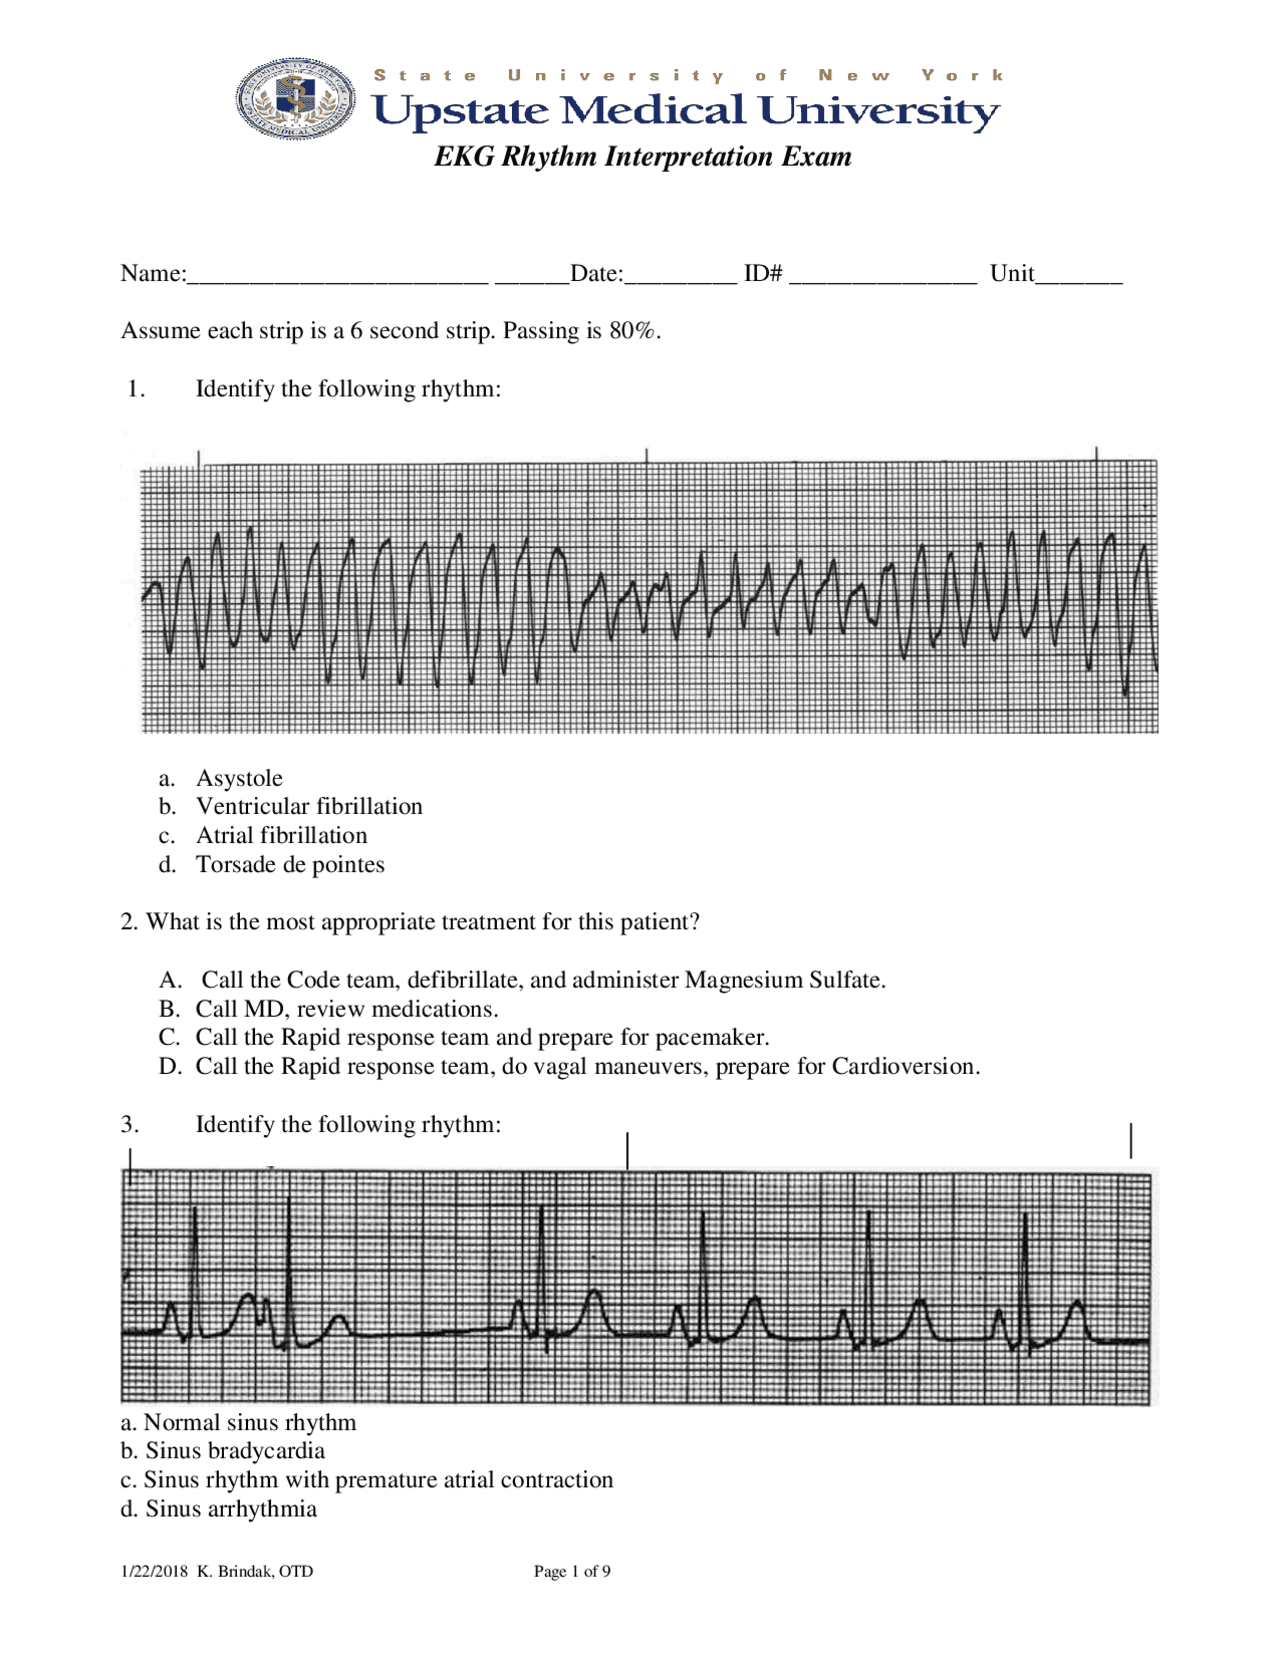
The actual exam format varies by organization but generally presents twenty to forty strips with multiple-choice questions asking you to identify the rhythm, the heart rate, and sometimes the clinical significance. Some versions include clinical vignettes alongside the strip, which adds a layer of interpretation beyond pure rhythm recognition. In those cases, the strip is correct but the question tests whether you know what to do about it. A strip showing stable monomorphic VTach with a pulse requires different management than the same strip in a pulseless patient. Read the full question before answering. One final practical note: do not spend excessive time on axis determination for rhythm interpretation exams. Axis deviation is important for comprehensive EKG analysis, but it is rarely the focus of rhythm-specific questions. The time you save by deprioritizing axis calculations is better invested in distinguishing between second-degree Type I and Type II block, which is one of the most frequently tested concepts and one where the distinction is purely based on the pattern of PR interval behavior, not on any single measurement.