How to Actually Use Rhythm Strip Practice Materials
Most people approach EKG rhythm strips the wrong way. They stare at one strip for ten minutes, try to memorize every feature, and move on. That doesn't build the pattern recognition you need. You need volume and repetition. I spent years watching nurses and med students fumble through the same basic rhythms because they never developed the automaticity required to identify them under time pressure.
Start with a strip. Don't read the answer first. Go through a consistent sequence every single time: rate, rhythm regularity, P waves, PR interval, QRS width, axis if relevant, and then any abnormalities. Write it down. Compare your answer afterward. The act of committing to an interpretation before checking the key forces your brain to actually engage rather than passively absorb.
The problem with ready-made practice materials is that many of them are oversimplified. Real strips have noise, baseline wander, lead mismatch, and artifact. If you only practice on clean, textbook-perfect strips, you'll freeze when you encounter a messy 12-lead in the ICU. I started adding deliberate artifacts to my own practice sets after realizing how often my residents couldn't distinguish atrial flutter from sinus arrhythmia on a poorly recorded strip.
Where to Find Ekg Rhythm Practice Strips
Free sources exist, but quality varies wildly. The American Heart Association and some hospital systems post basic strips, though they rarely include the harder cases. Several nursing education websites offer printable PDF banks with varying accuracy. For a more structured approach, platforms like 12LeadMastery and the Rhythm Academy provide subscription-based banks with full explanations. I've used both. The free resources are fine for learning the absolute basics. If you're preparing for a certification exam or clinical rotation, investing in a well-curated bank saves time because the strip quality is consistent and the answers are vetted.
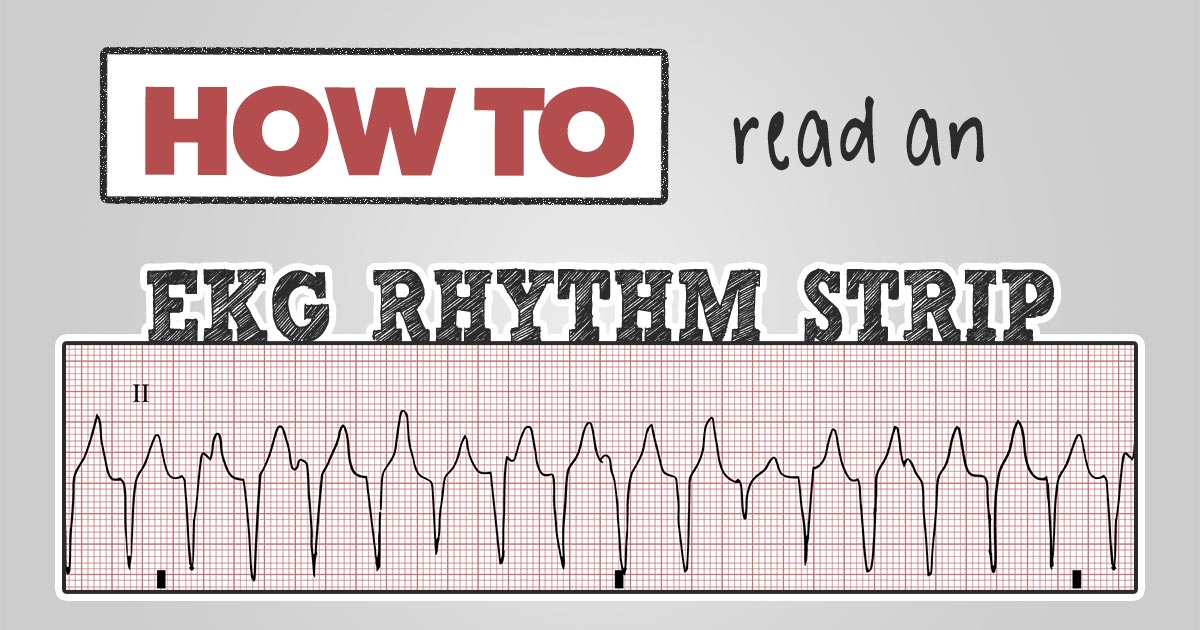
One detail most people overlook: the strip length matters. A 6-second strip at standard speed (25 mm/sec) gives you 150 mm to work with. That's enough for most regular and mildly irregular rhythms. But for distinguishing between sinus arrhythmia and atrial fibrillation, or for catching intermittent conduction blocks, you want at least a 12-second rhythm strip, preferably from lead II. Longer strips reveal patterns that shorter ones hide entirely.
Here's something I learned the hard way. Early in my career, a patient came in with what looked like sinus bradycardia on the monitor. The strip was clean, regular, rate around 45. I signed off on it. Two hours later, the rhythm degraded into complete heart block with a junctional escape at 38. The original strip hadn't shown the dissociation because the P waves were buried in the T waves. If that 12-lead had included a longer rhythm strip at the bottom, I might have caught the AV dissociation. Now I always check for P-QRS relationship on every strip I interpret, even when the rate seems straightforward. That habit came from one missed diagnosis.
A counter-intuitive point about rate calculation: the 300 method (counting large boxes between R waves and dividing 300 by that number) works fine for regular rhythms. But when the rhythm is irregular, like atrial fibrillation, that method gives you a range, not a number. What actually helps is counting the QRS complexes in a 6-second strip and multiplying by 10. It takes two seconds longer and gives you a clinically useful average rate instead of a misleading single value.
Another common mistake is assuming every visible deflection before the QRS is a P wave. Sometimes you're looking at a supraventricular ectopic beat, a fusion beat, or artifact. I remember working through a strip that appeared to show a wandering pacemaker at first glance. The P wave morphology changed across leads, the rate drifted, and the PR interval varied. Turns out it was multifocal atrial tachycardia, not wandering pacemaker, because the rate was over 100. The distinction matters for treatment. MAT requires addressing the underlying lung disease; wandering pacemaker usually doesn't. Without knowing the rate threshold, you misclassify and mismanage.
If you're building your own practice routine, here's what I'd suggest. Dedicate 20 minutes daily to 10 strips. Mix easy and hard cases. Write your interpretation before looking at the answer. Keep a log of the strips you got wrong and review them weekly. Within three weeks, you'll notice a measurable improvement in speed and accuracy. Most people see their interpretation time drop from about four minutes per strip to under ninety seconds without losing correctness, assuming they're doing the repetition properly.
There are also scenarios where practice strips fail you entirely. They can't replicate the clinical context. A strip showing first-degree AV block means something completely different when the patient is on beta-blockers versus when they're septic. Or when the patient has a bundle branch block versus when they don't. Strips are diagnostic tools in isolation. In practice, they're one data point among many. Don't let rote strip identification replace clinical reasoning.
For edge cases, learn to recognize when a rhythm strip is unreadable. Baseline wander from patient movement, 60-cycle interference from nearby equipment, lead reversals, and electrode disconnects can all produce artifacts that mimic real arrhythmias. I once spent five minutes analyzing what I thought was atrial flutter with variable block before realizing the "flutter waves" were actually muscle tremor artifact from a shivering patient. The fix isn't to call it a rhythm. It's to get a clean repeat.
The most useful skill you'll develop isn't identifying individual rhythms. It's recognizing transitions. A patient in sinus rhythm who gradually develops dropped beats isn't just having second-degree block. They're progressing. Noticing the sequence matters more than naming the end state. Practice strips that show progression sequences are rare but valuable. Seek them out or create them from real case files.
Keep a reference card with the basic differential diagnoses for each major category: regular narrow-complex tachycardia, irregular narrow-complex tachycardia, regular wide-complex tachycardia, and bradyarrhythmias. When you encounter a strip, match it to the category first, then narrow from there. This prevents the common error of jumping to a specific diagnosis without establishing the broader framework.
There's no shortcut. The improvement comes from consistent, deliberate practice over weeks, not from cramming before an exam. The human brain recognizes patterns through repetition, and rhythm strips are fundamentally a pattern-matching exercise. Do the work daily. The results are predictable if you stick with it.
Gallery Ekg Rhythm Practice Strips
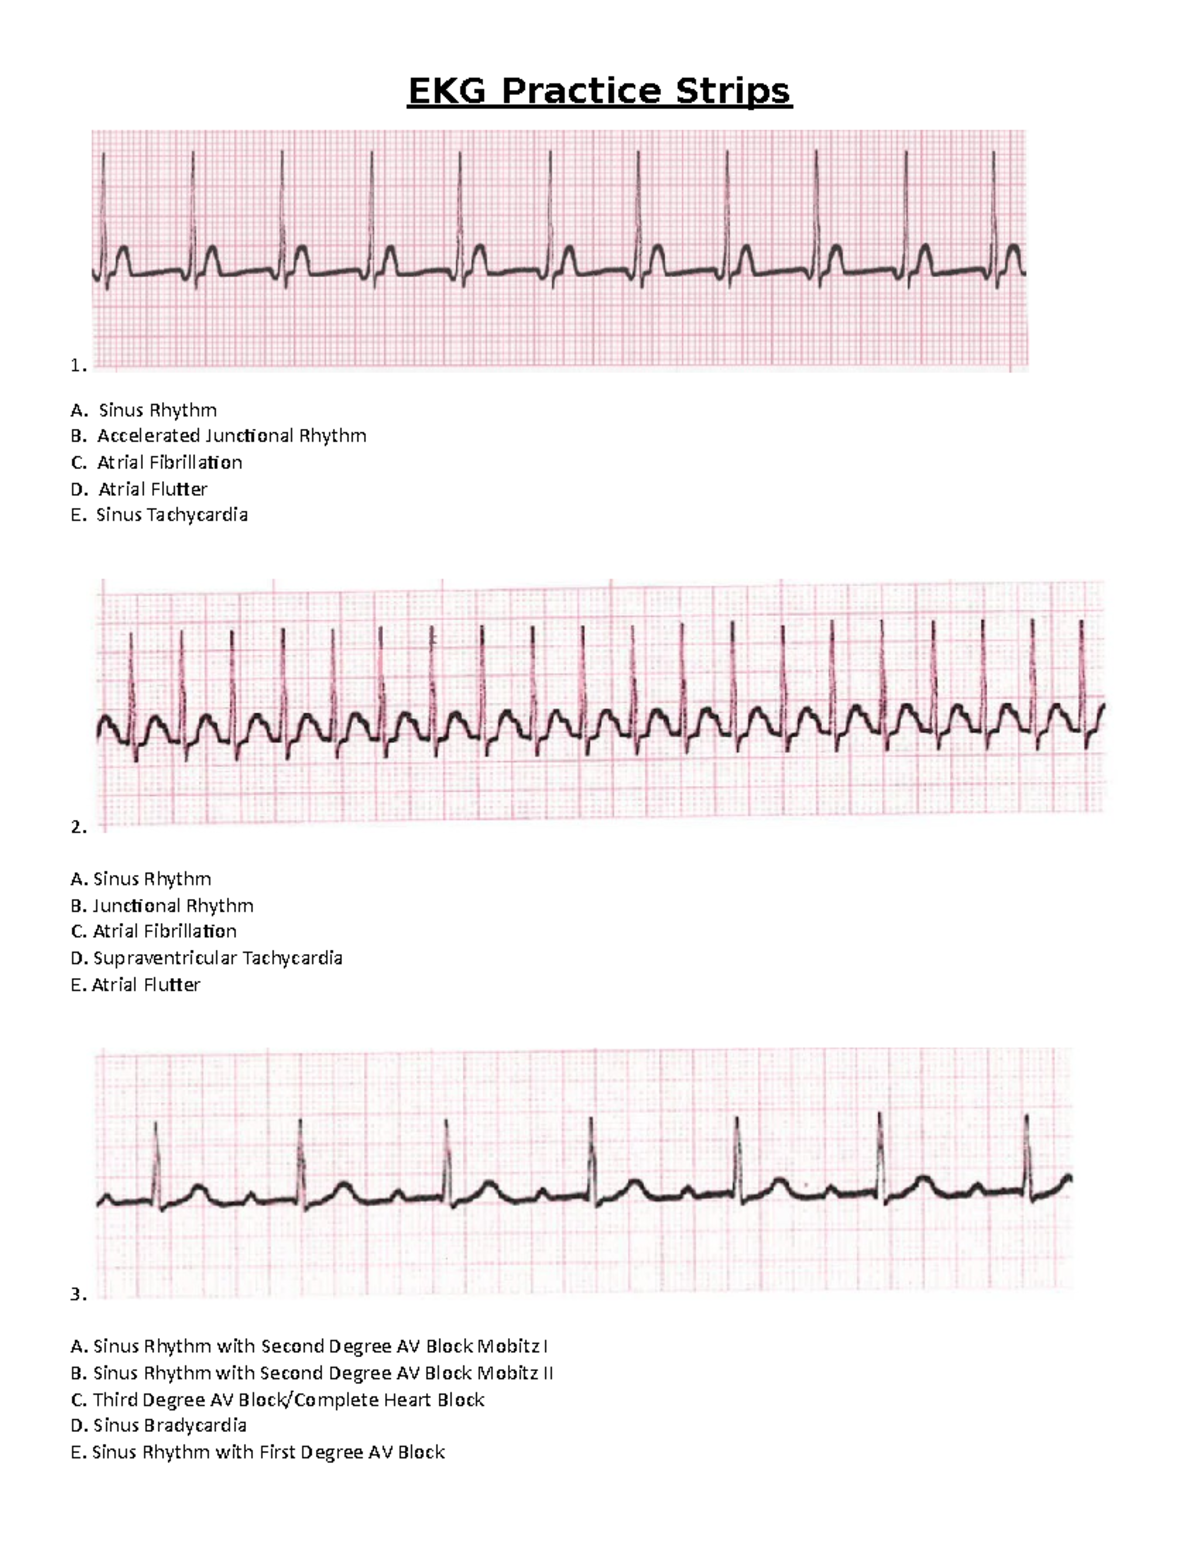
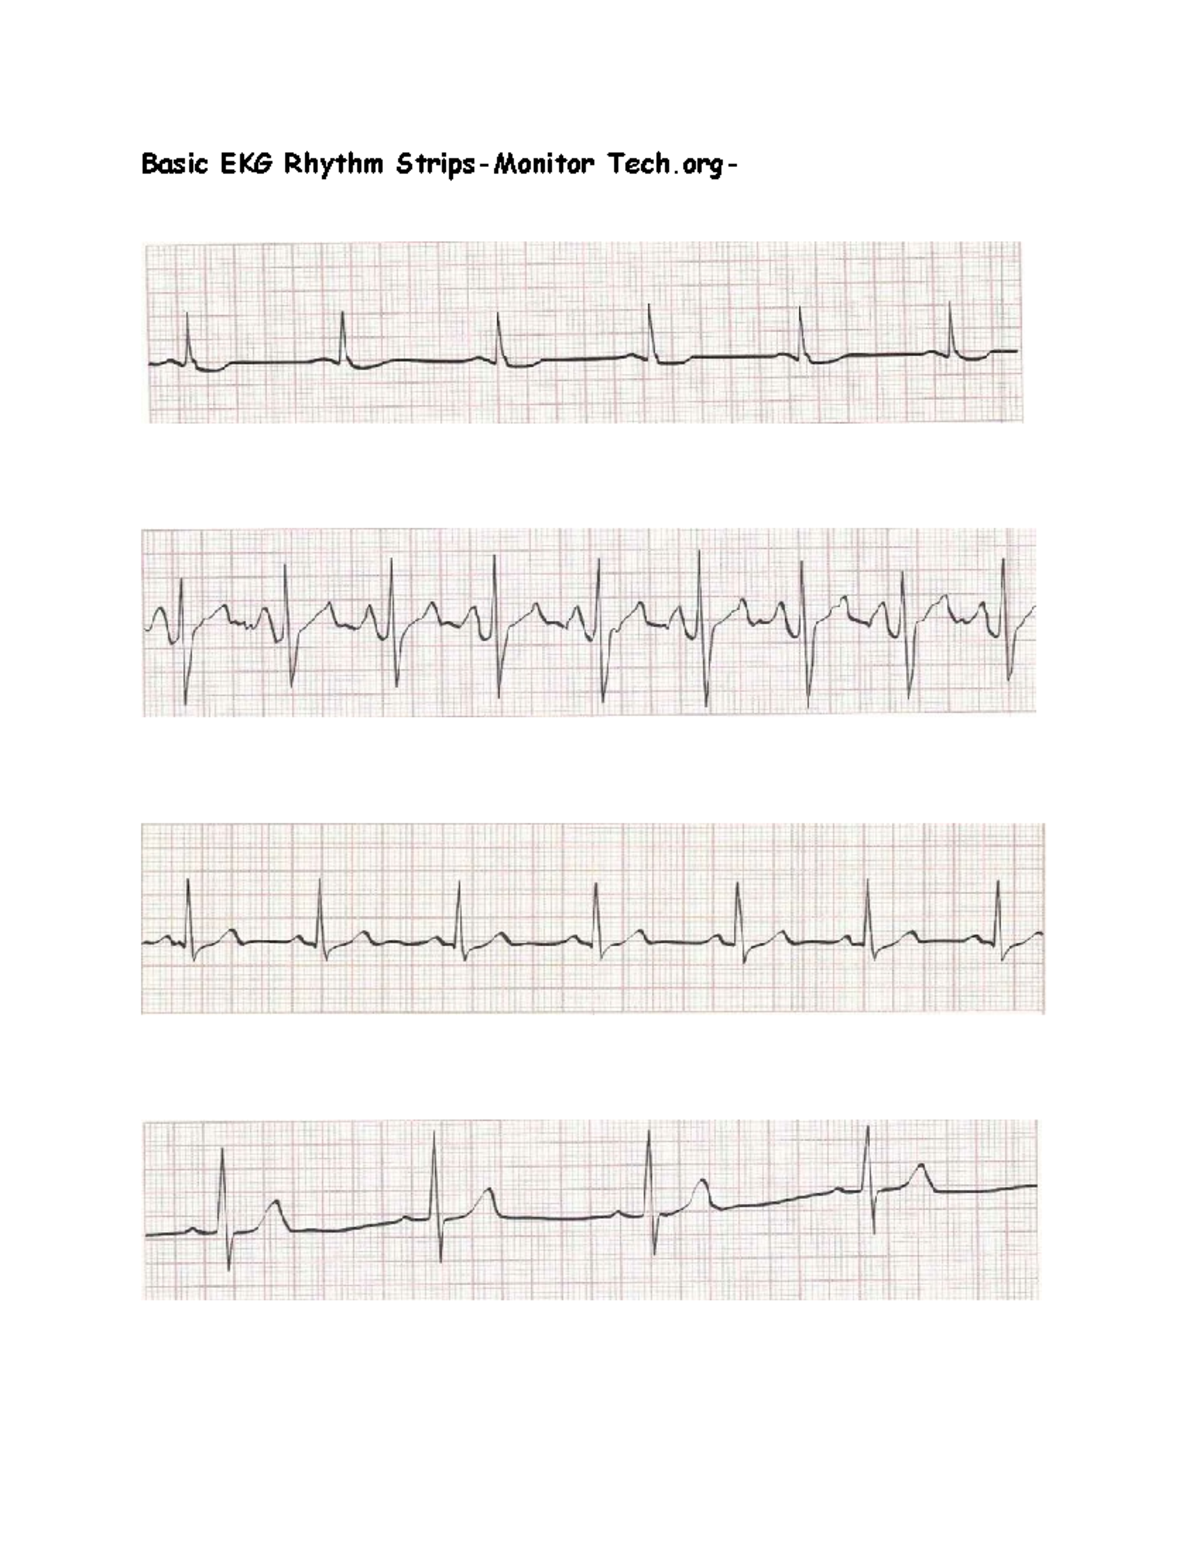
EKG Rhythm Strips Practice for Monitor Tech Students - Studocu
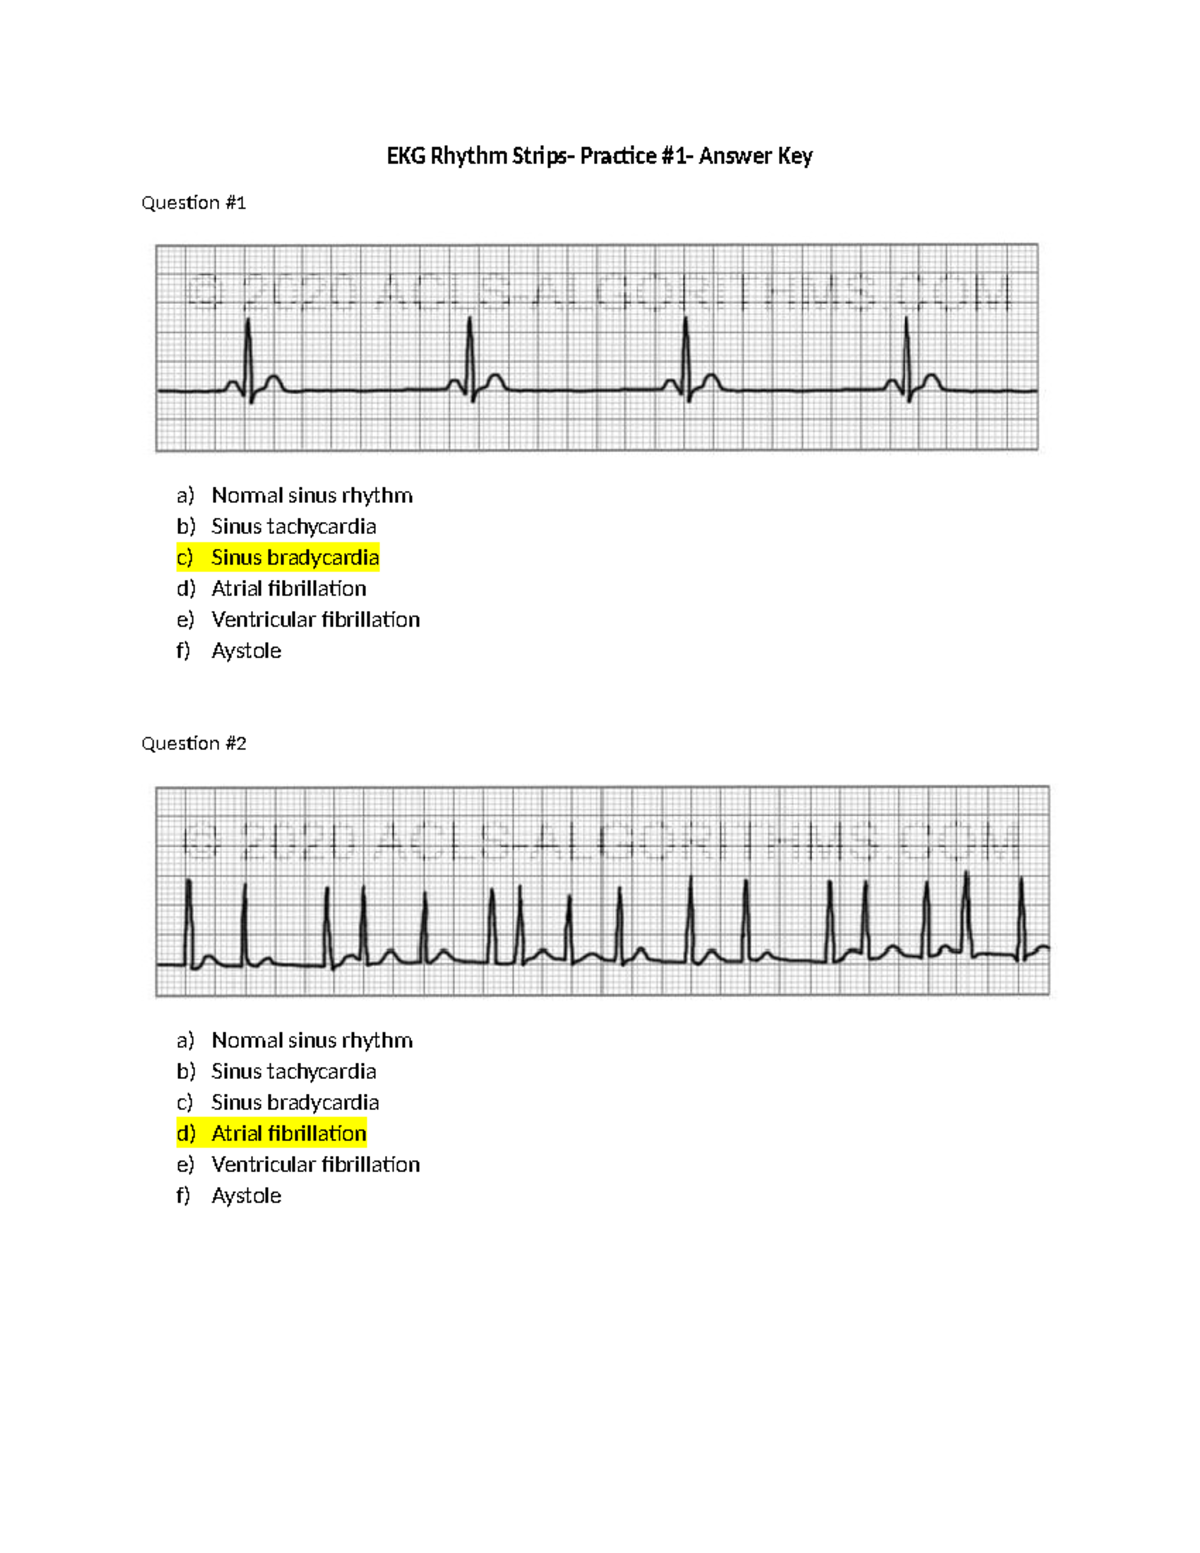
EKG Rhythm Strips Practice #1 - Answer Key and Explanations - Studocu
Ekg Rhythms: Practice Strips Flashcards – QTWWM
Printable Ekg Practice Strips - Printable Calendars AT A GLANCE
Ekg Practice Strips Printable