Reading EKG strips isn't as hard as people make it
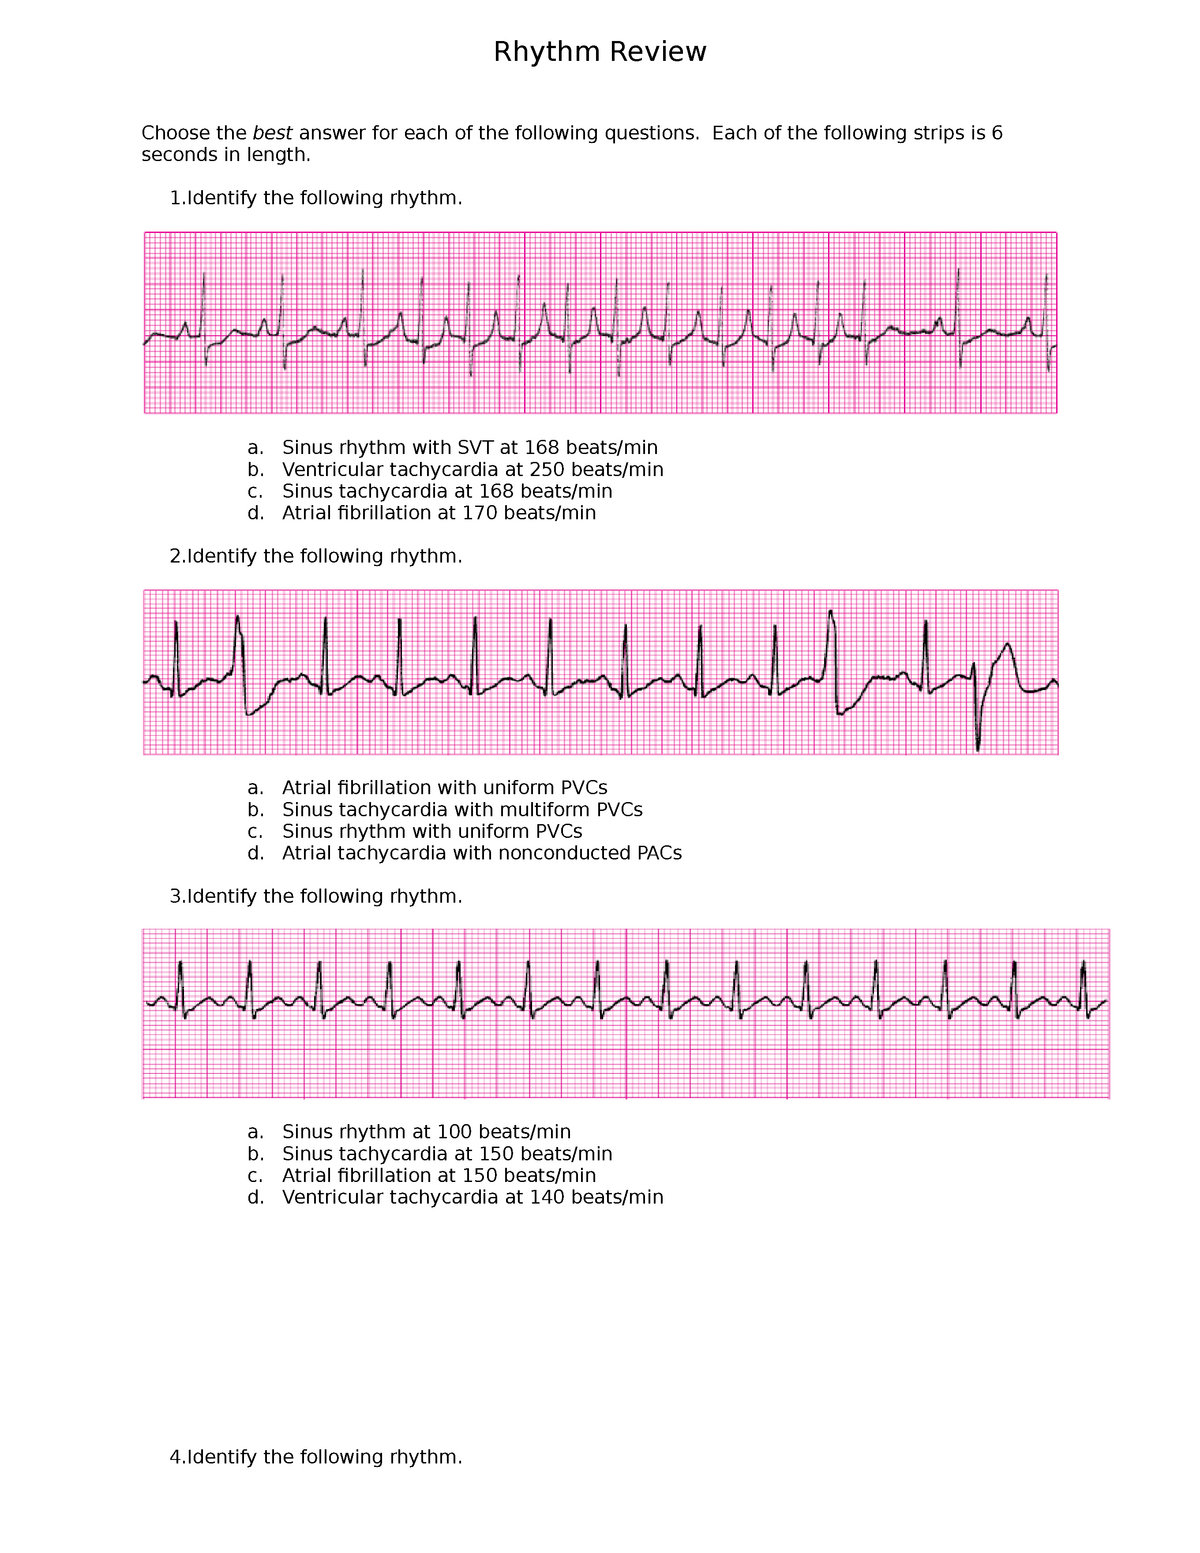
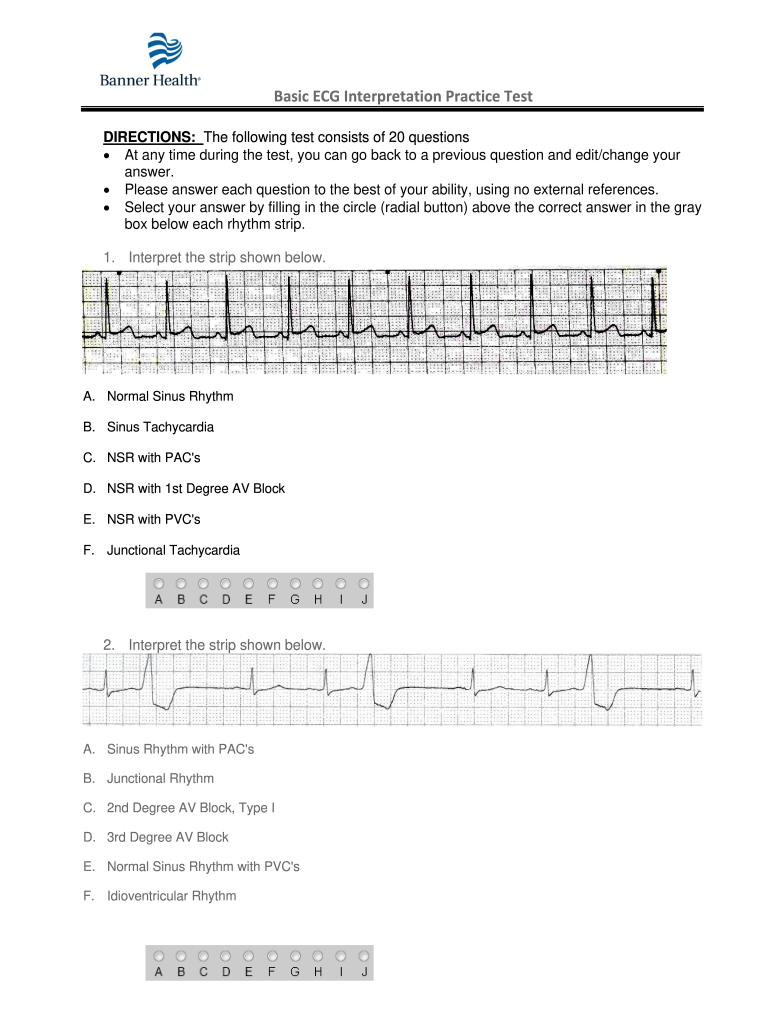
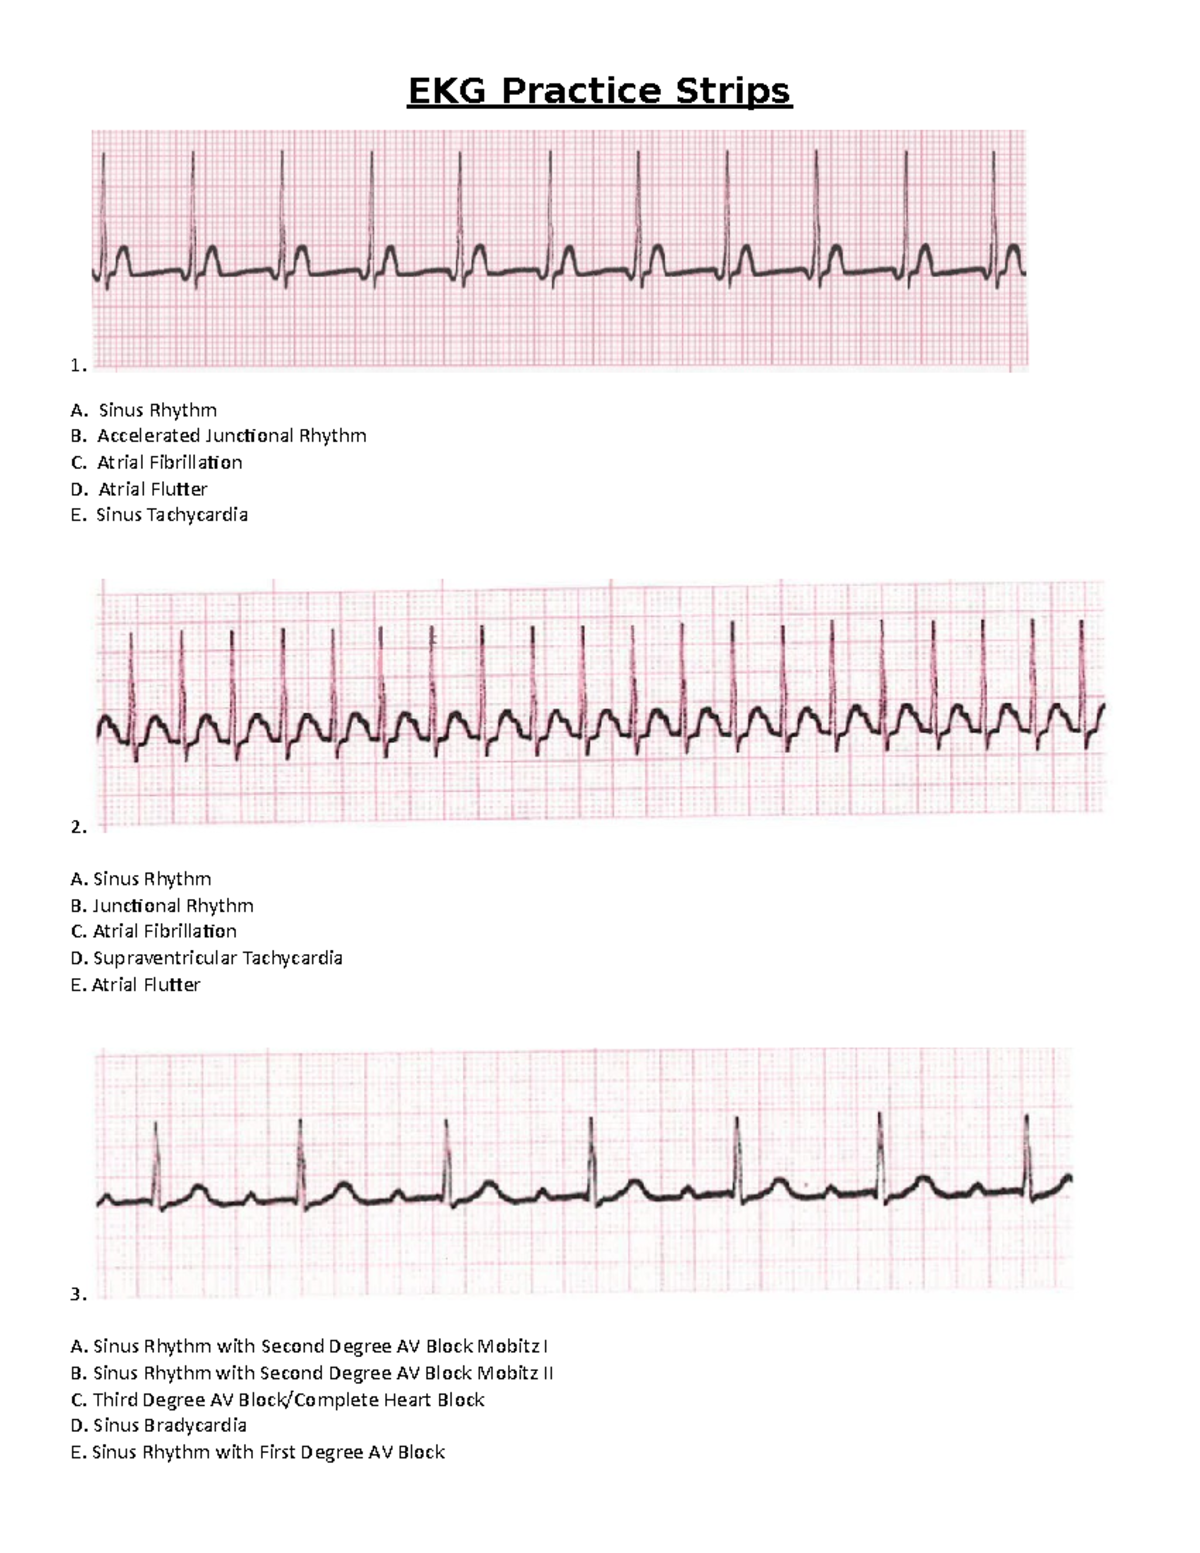
I've been interpreting rhythm strips for years, and the biggest problem I see is that people try to absorb everything at once. They stare at a 12-lead like it's a novel instead of scanning for the specific patterns that matter. Ekg Strips Practice Test resources exist precisely because pattern recognition is the core skill here, not memorizing textbook definitions. When you're actually learning to read strips, start with rate and rhythm before anything else. Figure out the heart rate first. If you can't do that quickly, nothing else matters. Use the 300 method for regular rhythms—count the big boxes between R waves. One box is 300, two is 150, three is 100, four is 75, five is 60. For irregular rhythms, use the six-second method instead: count the QRS complexes in a six-second window and multiply by ten. That last part catches people off guard because most people try to force the 300 method onto atrial fibrillation and wonder why they're getting nonsense answers.
Ekg Strips Practice Test resources you should actually use
The best practice tools give you raw strips without flashy animations or constant hints. You want something that looks like what you'd see on a real monitor—some noise, slight baseline wander, the occasional artifact. Most free resources online are either too clean or too cluttered to be useful. Look for ones that let you check your answers immediately so you can spot your own blind spots fast. I went through about four different platforms before finding one that actually mimicked real clinical strips, and that was when my accuracy jumped from roughly 55 percent to over 80 percent on complex arrhythmias. One thing nobody tells you about interpreting rhythm strips is that lead placement matters more than most practice tests account for. I spent weeks puzzled by what I thought were bizarre atrial rhythms until I realized a practice test I was using had swapped leads V1 and V2 in several strips. The P wave axis looked completely different because the vectors were flipped. Always double-check whether a practice resource has labeled which lead you're reading, especially if it only shows one long rhythm strip. This is the kind of gap that won't show up on your first dozen quizzes but will absolutely cost you on a real exam or in clinical practice. Here's a counter-intuitive point that took me a while to accept: regular-looking rhythms are where people make the most dangerous mistakes. A sinus rhythm with first-degree AV block looks almost identical to normal sinus rhythm at a glance. Missing that P wave before every QRS because the PR interval is just slightly prolonged is a common error, and it's exactly the kind of thing that matters when you're managing a patient on digoxin or beta-blockers. Slow down on the seemingly normal strips. Verify every wave before you label it.
Another pitfall involves distinguishing artifact from true arrhythmia. I once spent three minutes analyzing what I thought was multifocal atrial tachycardia on a monitor strip, only to realize the patient had been moving and the baseline was bouncing between leads. The QRS complexes were perfectly consistent—only the baseline was chaotic. When you're practicing, make sure your test bank includes noisy, messy strips and not just perfect textbook examples. Clean strips teach you to recognize clean examples. Messy strips teach you to actually think. For actual study structure, I'd suggest spending your first week purely on rate and rhythm identification across basic rhythms—sinus tachycardia, sinus bradycardia, sinus arrhythmia, atrial fibrillation, atrial flutter with different blocks, junctional rhythms, and the common ventricular arrhythmias. Don't move into block classifications until those feel automatic. The second week should cover first-degree, Mobitz type one, Mobitz type two, and third-degree AV blocks. Focus especially on differentiating Mobitz type one from type two because that distinction changes management completely and students consistently blur them under time pressure. Week three goes into bundle branch blocks and hemiblocks. Right bundle branch block has that classic rSR' pattern in V1 and a wide S wave in V6. Left bundle branch block is broader and harder to spot at first because the criteria are less visual and more about the overall widened QRS morphology. Learn to recognize these by silhouette rather than by counting milliseconds every time.
Get the Full Details
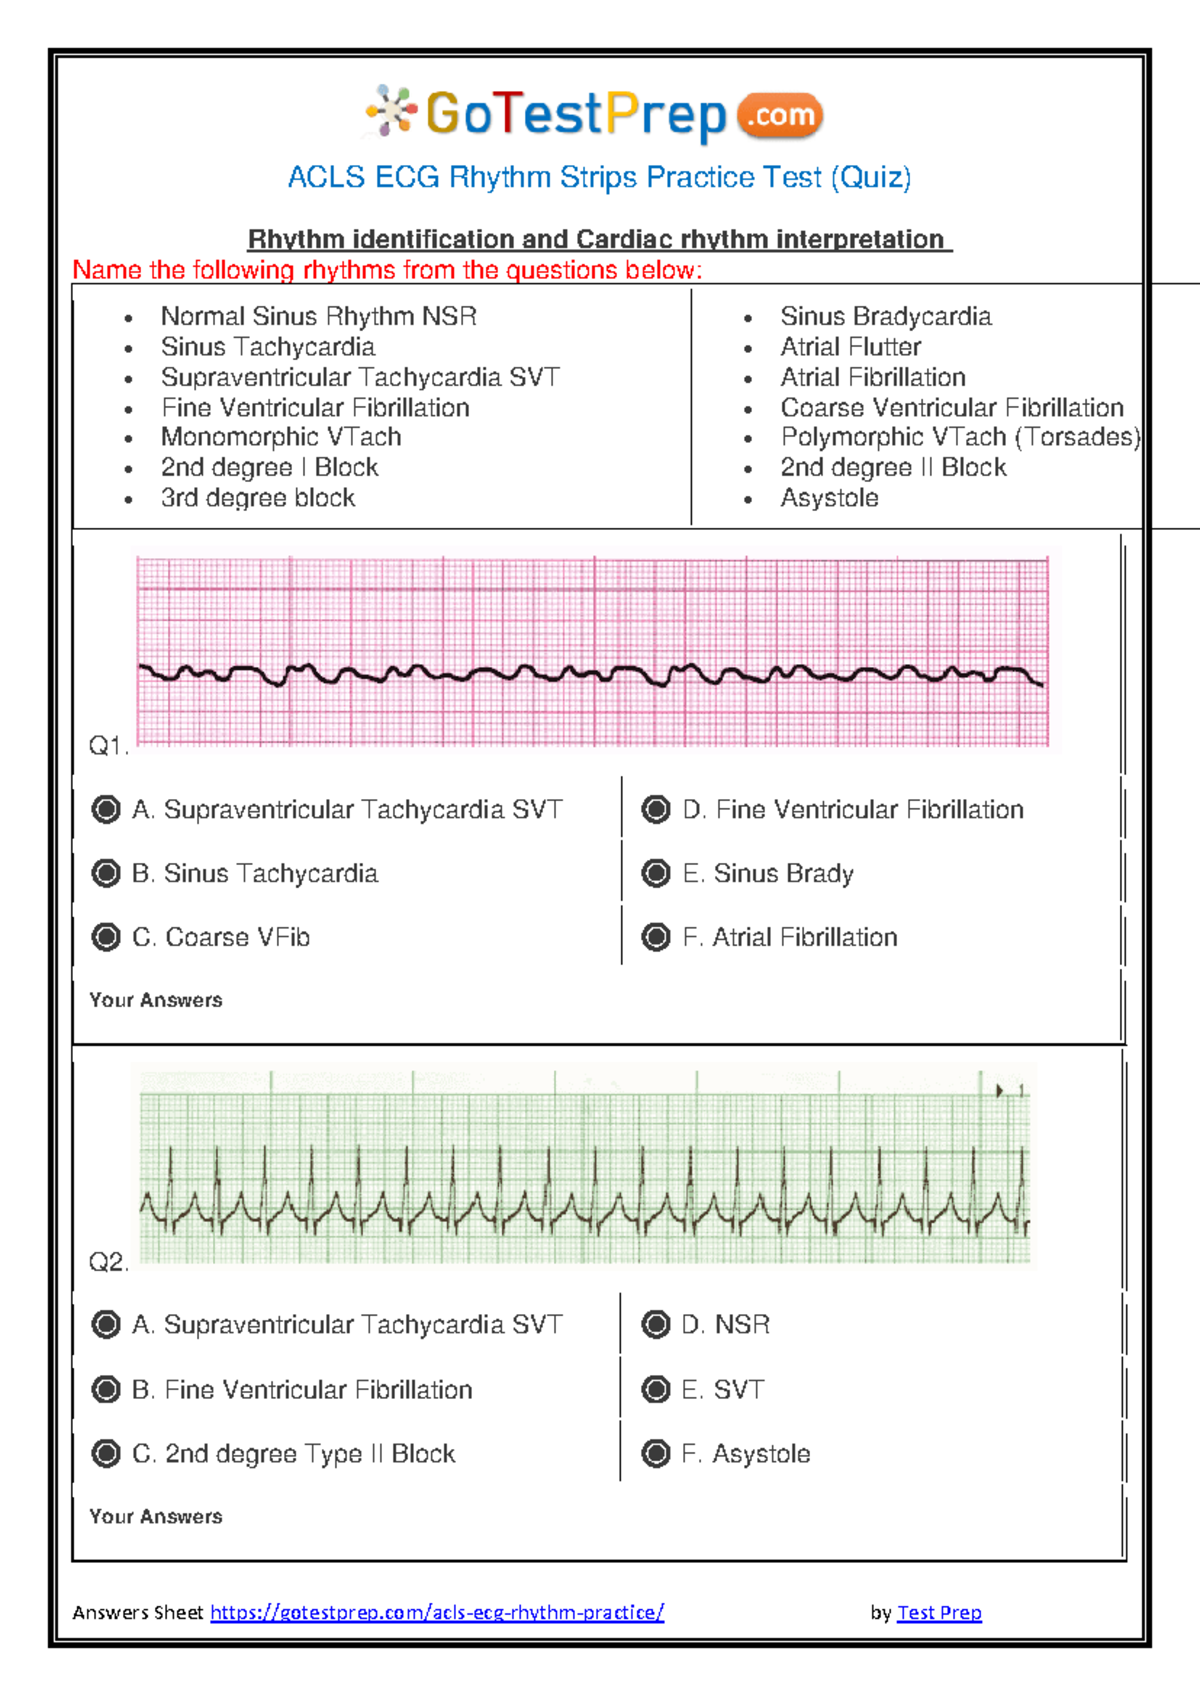
The biggest limitation with most practice test formats is that they present isolated strips without clinical context. In real practice, you're never looking at a strip in a vacuum. A narrow complex tachycardia at 180 beats per minute means something different in a post-op cardiac patient than it does in a dehydrated 22-year-old with sepsis. No amount of strip practice replaces learning to integrate clinical data, but the practice tests still build the foundational pattern recognition you need before that integration becomes possible. If you find yourself stuck on a particular rhythm type, switch to manual tracing. Grab a sheet of paper and physically draw the P waves, QRS complexes, and T waves from a real strip. This forces you to slow down and actually examine the morphology instead of guessing from a quick glance. It sounds tedious, but it takes about twenty minutes per strip and dramatically improves your ability to catch subtle differences during timed testing conditions. Most free practice resources I've encountered are adequate for basic rhythms but fall apart when they get into dysrhythmias with dual mechanisms or paced rhythms with underlying conduction disease. If you're preparing for a professional exam like the CCRN or ACLS, invest in at least one paid question bank that includes those harder cases. The free stuff will get you through the fundamentals. It won't prepare you for the strips designed to trip people up on the final questions.