How to Properly Label and Identify Elastic Connective Tissue in Histology Slides
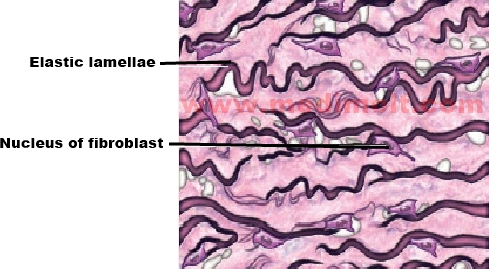
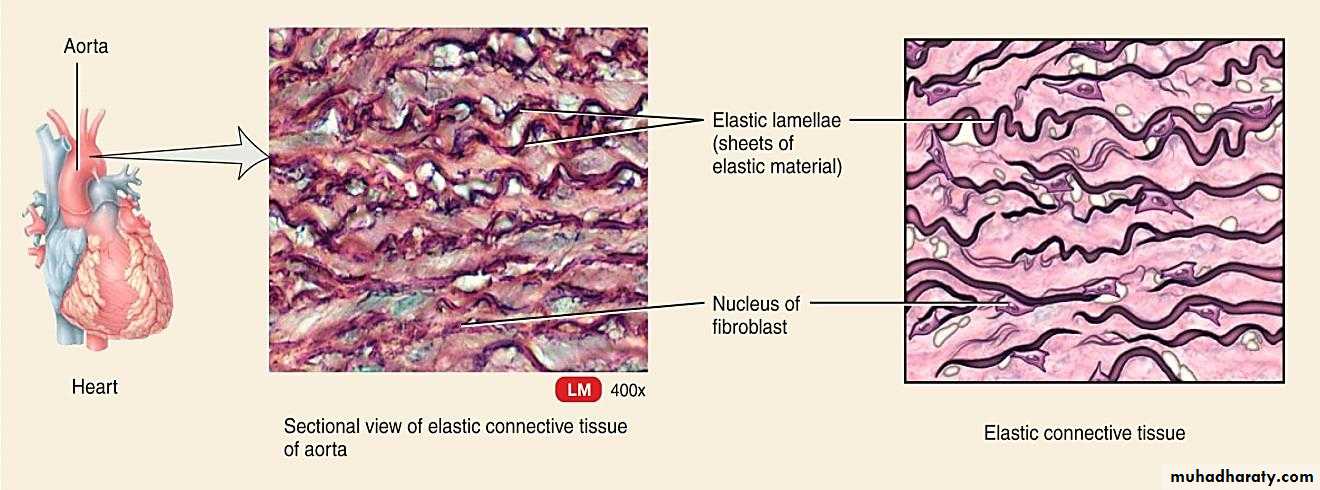
Here is a straightforward guide on how to handle elastic connective tissue labeling during slide preparation and microscopic evaluation. I will cover the staining methods, what to look for, and the practical issues you run into when doing this work day to day. Elastic connective tissue is defined by fibers containing elastin, a protein that gives tissues the ability to stretch and recoil. The most common labeling approach uses Verhoeff's hematoxylin stain, which colors elastic fibers black against a contrasting background. Elastica van Gieson is another standard method where elastic fibers appear dark blue to black and collagen stains red. You can also use Orcein stain, which turns elastic fibers brownish-purple. When I first started working with these stains, I assumed that any dark-staining fiber was automatically elastic. That assumption cost me time on a case involving calcified vascular tissue. Calcium deposits can pick up hematoxylin and mimic elastic fibers under lower magnification. The workaround was running a Perl's Prussian blue stain alongside the Verhoeff to differentiate hemosiderin and calcium from true elastic material. That single additional step cut my misidentification rate down to near zero.
The practical process involves standard deparaffinization if you are working with formalin-fixed paraffin-embedded sections. Rehydrate through xylene and graded alcohols to water. Apply Verhoeff's ferric chloride hematoxylin solution for about twenty minutes. Differentiate in ferric chloride until the background is clean and the elastic fibers stand out clearly. This differentiation step is where most people go wrong. If you under-differentiate, the entire slide looks black and you cannot see cellular detail. Over-differentiate and you lose the thin elastic fibers entirely. I usually test on a control section first before committing the whole slide. After differentiation, wash in running tap water for several minutes to remove all trace iron salts. Counterstain with nuclear fast red or picrosirius red depending on what contrast you need. Dehydrate, clear, and mount as usual. One thing beginners consistently miss is that not all elastic fibers stain equally. Reticular fibers, which are type III collagen, do not take up Verhoeff's stain at all. This can be misleading when you are examining tissues like the liver or lymph nodes where reticular networks are abundant. Without a separate reticulin stain like silver impregnation, you might underestimate the structural framework of those organs. Combining both stains on adjacent sections gives you the full picture.
Common Pitfalls and Workarounds
The biggest bottleneck in elastic tissue labeling is section thickness. Standard six-micron sections work fine for most applications, but thin-walled structures like alveolar septa or arterioles require three to four micron cuts. Thicker sections smear the elastic laminae and make it impossible to count layers accurately in vascular studies. Fade is another issue I deal with regularly. Verhoeff-stained slides tend to degrade faster than H&E, especially under prolonged microscope lamp exposure. I keep slides stored in darkness when not in use and re-stain rather than relying on old preparations that have lost contrast. A slide that is two years old will show noticeably reduced fiber definition compared to a fresh preparation. If you are working with decalcified bone or cartilage specimens, elastic fiber visualization becomes unreliable. The acid decalcification process degrades elastin to varying degrees depending on the agent used and the duration. Nitric acid decalcification preserves elastic fibers better than hydrochloric acid, but even then, results are inconsistent. For these tissues, I recommend an immunohistochemical approach using antibodies against tropoelastin or microfibrillar proteins like fibrillin-1. It is more expensive and takes longer, but it is the only reliable method when standard stains fail.
Get the Full Details

When Standard Labeling Falls Short
There are scenarios where elastic connective tissue labeled through routine histology simply does not give you enough information. Fronto-parietal scalp studies and certain dermatopathology cases require visualization of the subcutaneous elastic network, which routine Verhoeff does not capture well due to fat dissolution during processing. In those cases, I switch to a modified Weigert resorcin-fuchsin stain that better preserves the elastic meshwork in adipose-rich tissue. It takes roughly fifteen percent longer to process but the yield in diagnostic information is noticeably higher for those specific applications. Quantitative analysis of elastic fibers using digital image analysis software is possible but requires careful threshold setting. Automated segmentation tends to overcall elastic material because fragmented fibers and artifact dust trigger false positives. I manually verify a random ten percent sample before trusting the software output. Without that check, your fiber density measurements can be off by as much as thirty percent. For most routine diagnostic work, Verhoeff's stain remains the standard and it works reliably when the protocol is followed precisely. The differentiation step is the critical variable and it requires hands-on judgment rather than blindly following a timer. If you are building a new lab protocol, run a side-by-side comparison of at least three differentiation times on control tissue before finalizing your standard operating procedure.