Where Elastic Connective Tissue Actually Lives
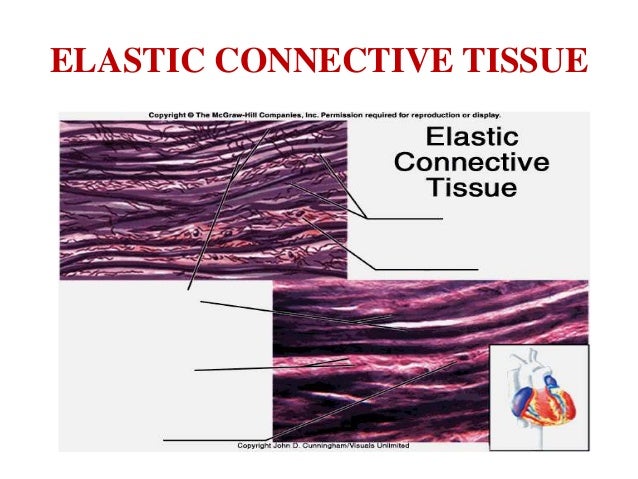
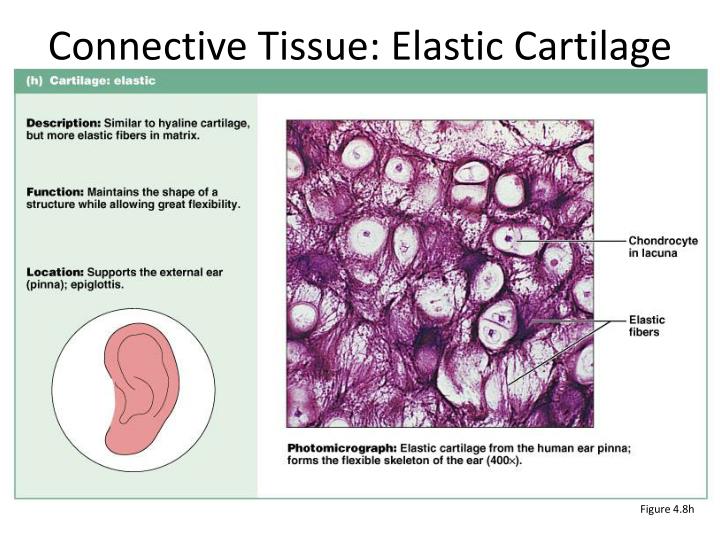
Elastic connective tissue isn't spread evenly through the body. It shows up in specific places where stretch and recoil matter, and the locations are fairly predictable if you know what to look for. The biggest concentration is in the walls of large arteries, especially the aorta and its proximal branches. These arteries need to expand with every heartbeat and snap back during diastole, which is why the tunica media here is packed with concentric sheets of elastic lamellae rather than just smooth muscle. Beyond the arterial system, elastic connective tissue appears in the ligamenta flava connecting adjacent vertebrae, the walls of the bronchi and bronchioles, the elastic ligaments of the larynx including the vocal cords, the dermis of the skin particularly in areas prone to stretching, the lungs themselves where elastic fibers help with passive exhalation, and the outer ear cartilage giving the pinna its ability to return to shape after deformation. When you're studying histology slides, the easiest way to identify elastic fibers is by using a special stain. Standard H&E won't cut it because elastic fibers stain very pale pink and blend right into the background. You need something like Verhoeff-Van Gieson or elastic van Gieson, which stains elastic fibers black against a red or yellow background. Without that, you're basically guessing based on tissue context alone.
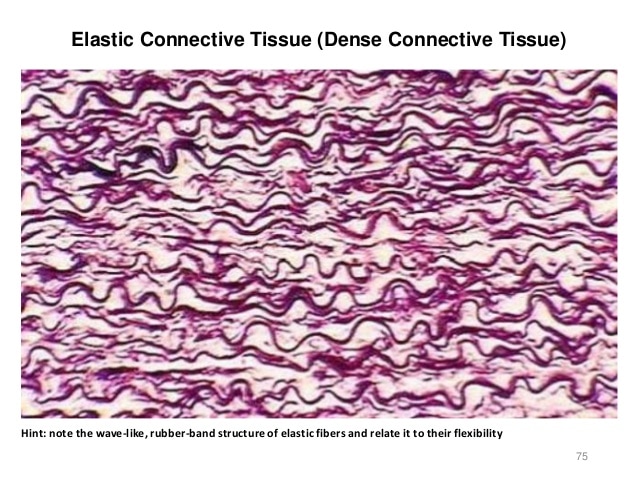
I ran into a problem last year working on a pulmonary pathology case where the lab's Verhoeff stain was running old and the elastic fibers in the small muscular arteries weren't picking up cleanly. The contrast was terrible, and distinguishing elastic laminae from basement membrane thickening was nearly impossible. What actually worked was switching to Weigert's iron hematoxylin followed by picrosirius red, which gave better differentiation between elastic and collagen fibers in that particular tissue fixation. The trick was that the formalin fixation had been longer than usual, which cross-links proteins in a way that can mask elastic fiber visibility on standard stains. One thing most people miss is that elastic tissue isn't just about elasticity. In the aorta, the elastic fibers are arranged in concentric fenestrated lamellae separated by smooth muscle cells and ground substance. This creates a layered structure that's fundamentally different from the random meshwork you see in the dermis. Confusing these two architectures leads to misinterpretation on exams and in practice. The lamellar units in large arteries are modular, and when hypertension causes damage, it typically starts at the junctions between lamellae rather than within them. Another nuance is that elastin content changes with age. Newborns have relatively less elastin in their arterial walls compared to adults, and after around age 40, elastin gradually fragments while collagen increases. This is why arterial stiffening is partly an elastic tissue issue, not just a calcium or smooth muscle problem. In histology slides from elderly patients, you'll often see fragmented, wavy black strands on Verhoeff stain instead of the clean parallel lines you see in younger tissue.
There are limitations to keep in mind. Special stains for elastic tissue are finicky. Over-differentiation during the staining process will strip the elastin stain completely, and under-differentiation leaves the background too dark to read anything. The quality of the fixative matters enormously. Bouin's fixative generally preserves elastic fibers better than neutral buffered formalin, though it's less common now due to picric acid handling issues. If you're reviewing a slide and the elastic fibers just don't look right, the problem might not be the tissue itself but the staining protocol that was used. For quick reference, the main locations break down roughly like this: large elastic arteries, medium-sized arteries where elastic fibers appear at the internal and external borders, bronchial walls as irregular sheets, ligamentum flavum as densely packed parallel fibers, dermis as a network in the reticular layer, lung parenchyma as alveolar septal fibers, and the external elastic lamina at the boundary between tunica media and tunica adventitia in muscular arteries. That last point about the external elastic lamina is worth emphasizing because it's a reliable landmark. In muscular arteries, you'll typically see a distinct wavy elastic sheet separating the media from the adventitia. Not all vessels have it clearly developed, and in smaller arteries it may be absent entirely. When you're trying to identify a vessel type and can't find a clear internal elastic lamina either, the presence or absence of these elastic boundaries becomes one of the few reliable ways to classify it.
Get the Full Details