A Practical Look At How ECT Actually Gets Used For Alcohol Use Disorder
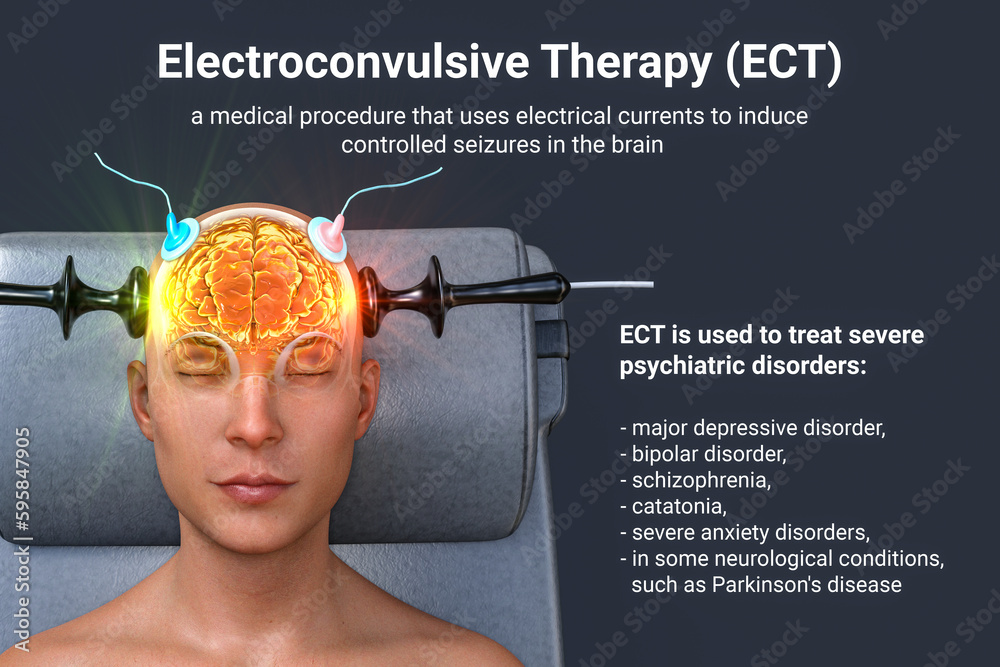
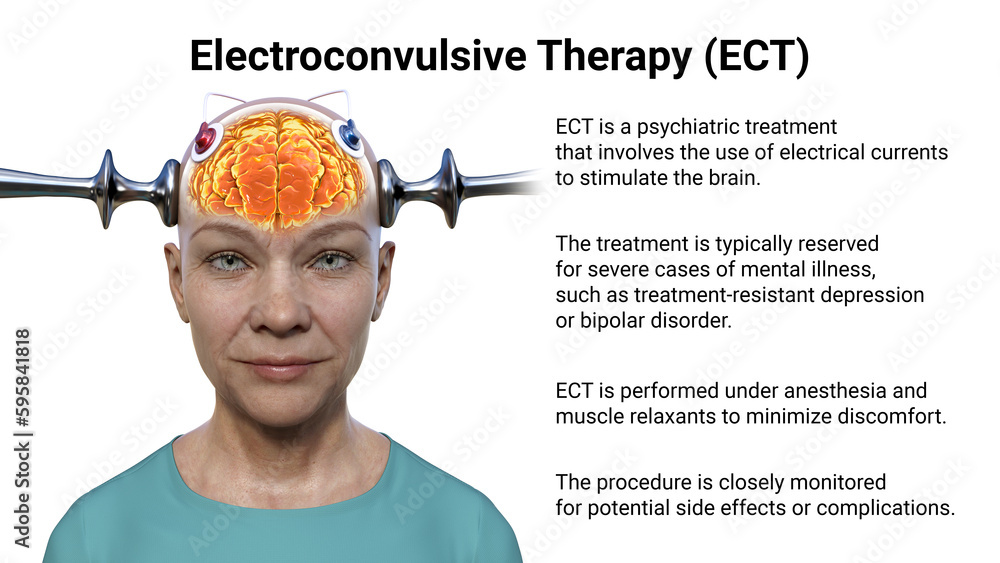
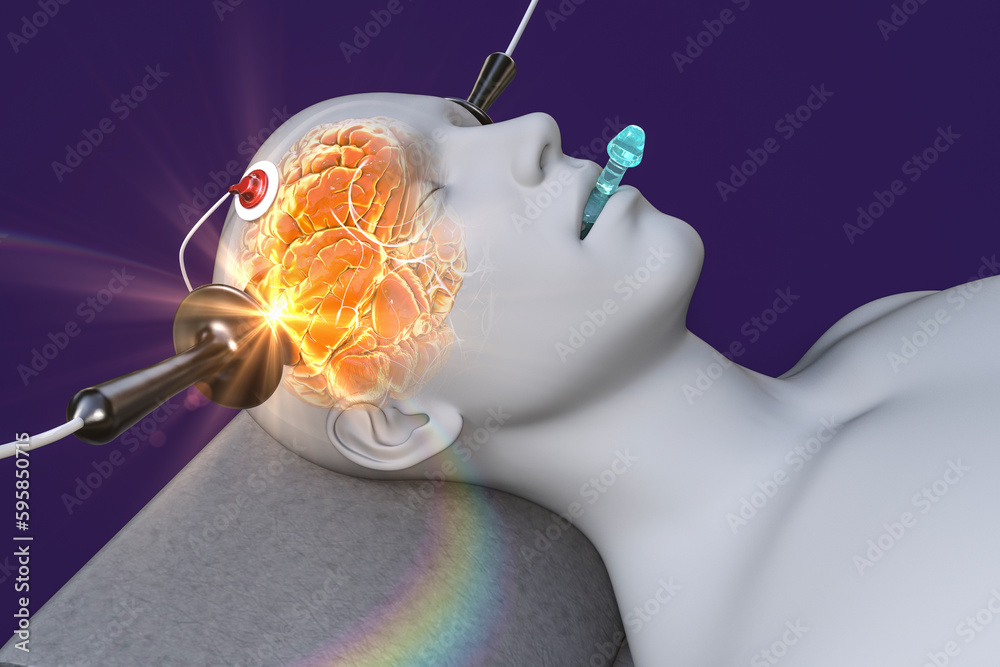
I keep seeing people on Reddit and in Facebook groups asking about Electric Shock Therapy For Alcoholism like it's some kind of hidden cure everyone knows about except them. It's not. It's also not the blunt instrument most people imagine. The reality is more technical, more expensive, and honestly, more disappointing for most people looking for a quick fix. But it does exist and it does work in the right situations. First, the medical term is electroconvulsive therapy. People use "shock therapy" colloquially because it sounds worse than it actually is. The procedure itself involves administering a controlled electrical stimulus through electrodes placed on the scalp to induce a brief, generalized seizure. The seizure is what produces the neurobiological effect. It happens under general anesthesia, so the patient feels nothing during the actual procedure. Muscle relaxants are given too, which is why you see the arm jerk in old movie portrayals - that part got dialed way down in modern practice. For alcohol use disorder specifically, the mechanism isn't fully mapped out but researchers think it involves modulation of the glutamate system, GABA receptors, and neuroplasticity changes in the prefrontal cortex and hippocampus. What that means in plain terms is that ECT appears to reset some of the neural circuitry that drives compulsive drinking behavior. It's not ablating memories or making you hate alcohol. It's more like pressing a hard reset on a computer that's been running a corrupted program for years.
The treatment course typically involves six to twelve sessions given two or three times per week. Each session lasts about five to ten minutes from induction to recovery. Maintenance sessions may be needed afterward depending on response. Most patients who respond to ECT for AUD report a significant reduction in craving and relapse frequency within two to four weeks of starting treatment. I should mention something specific here that I ran into repeatedly when consulting on cases like this. The biggest practical problem isn't the procedure itself. It's insurance coverage and finding a clinic that will even attempt it off-label for alcoholism. Most insurance plans cover ECT for treatment-resistant depression, bipolar disorder, and catatonia. They do not cover it for substance use disorders. That means most patients end up paying out of pocket, and a full course can run anywhere from eight thousand to twenty-five thousand dollars depending on the facility and geographic region. I had one patient who drove three hours each way to a university hospital because that was the only place in the state that would both perform the procedure and accept a self-pay arrangement at a reduced rate. She did six sessions over three weeks and cut her drinking from a liter of vodka a day down to social drinking only. She stayed sober for fourteen months before a major life stressor triggered a relapse. There are counter-intuitive things about this treatment that nobody tells you. One is that ECT for AUD works best when the patient also has a comorbid mood or anxiety disorder. The data is strongest for people who have both alcohol dependence and depression. Patients who have pure alcohol use disorder without any psychiatric comorbidity tend to respond less robustly, though they can still benefit. Another thing beginners miss is that the seizure duration matters more than most clinics advertise. A therapeutic seizure for AUD typically needs to last between twenty and sixty seconds. If the seizure is too short - under fifteen seconds - the treatment is usually ineffective. Neurologists monitor this via EEG and also watch the motor activity. Some older anesthetic protocols suppress seizure duration too much, which is why modern practice favors agents like methohexital over propofol when ECT is being used for neuropsychiatric conditions beyond depression.
The side effects are where people need to be honest with themselves. Immediate post-treatment confusion lasting ten to thirty minutes is universal. Headache, nausea, and jaw soreness are common for a few hours. The real issue is cognitive side effects. Most patients experience retrograde amnesia for events leading up to the treatment period - usually several weeks to months of memories go fuzzy. Some of this recovers over months. A minority of patients report persistent gaps in autobiographical memory that don't fully resolve. Working memory and verbal recall can be impaired for weeks after the course ends. These side effects are why ECT for AUD is not something you schedule around a high-stakes job interview or a presentation. I've also seen too many people treat ECT as a standalone solution. It isn't. The patients who maintain long-term sobriety after ECT for alcoholism are the ones who use it as an accelerant for behavioral change, not a magic replacement for it. The window of neuroplasticity after a treatment course is real. During that window, patients are more capable of engaging in therapy, more able to resist cravings, and more responsive to contingency management programs. I once worked with a patient who came in after a fourth ECT session and said something that stuck with me. She told me that before ECT, thinking about quitting drinking felt like trying to climb a wall in concrete boots. After the third session, the boots felt lighter. But she still had to climb. ECT just made the climbing possible. There are scenarios where ECT simply will not help and it's worth knowing upfront. Chronic heavy drinkers with significant liver disease need careful anesthetic consideration because drug metabolism is altered. Patients with certain types of brain lesions, recent strokes, or elevated intracranial pressure are generally contraindicated. And if someone is still actively using substances right up to the day of treatment, the seizure threshold becomes unpredictable and the procedure is less reliable. Most clinics require a period of abstinence before starting an ECT course, though this is more about safety than efficacy.
Get the Full Details
If you're considering this route, the first step isn't finding a clinic. It's getting a thorough psychiatric evaluation to determine whether you meet the criteria and whether there's a comorbid condition that would make ECT more likely to help. A second opinion from a psychiatrist who specializes in both addiction and ECT is worthwhile. The field is small enough that most general psychiatrists haven't treated AUD with ECT. You want someone who has actually done it and can give you realistic expectations based on their own outcome data, not a brochure.