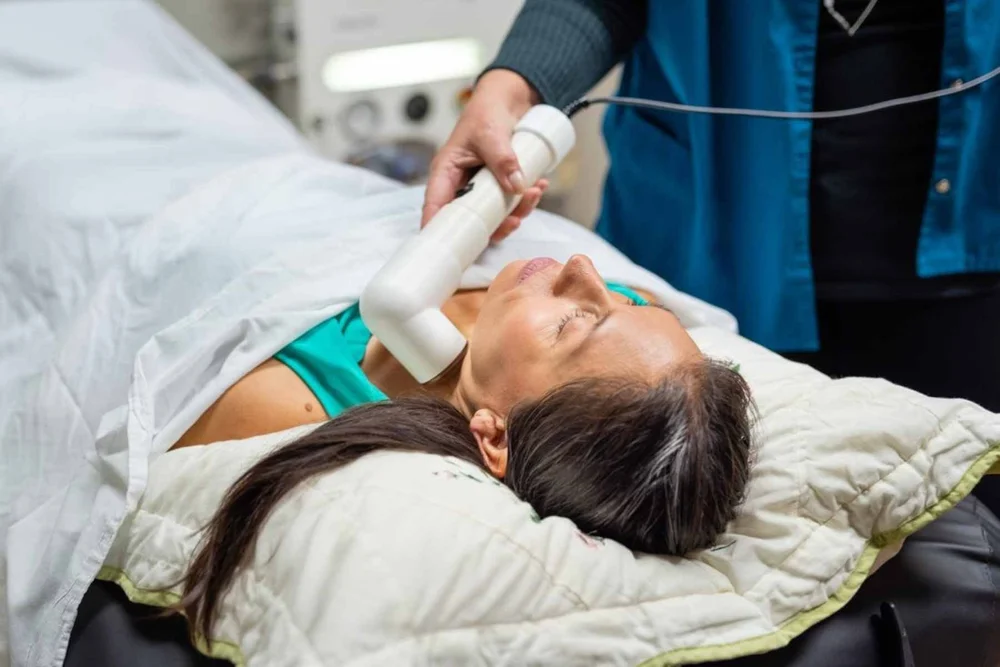
Getting started with Electro Lymphatic Drainage Therapy
I picked up on this method a few years back after dealing with persistent lower leg edema that standard compression socks and elevation barely touched. The premise is straightforward: low-frequency alternating electrical currents, typically in the 0 to 400 hertz range, are applied through skin electrodes to stimulate lymphatic vessel contraction and improve lymph flow. It is not high-tech rocket science, but it requires more care in setup than most people expect. The basic apparatus is simple. You need a programmable pulse generator capable of delivering low-voltage microcurrents, two sets of surface electrodes with conductive gel, and a way to control the waveform shape, frequency, and amplitude. Some practitioners use dedicated devices marketed for lymphatic work. Others build their own rigs using function generators and precision op-amp circuits. Both approaches work. The built-in safety features are usually nonexistent in DIY setups, so I take that seriously.
Electro Lymphatic Drainage Therapy Setup and Procedure
Here is how I run a typical session now. I start with the patient supine and expose the treatment zones. For lower extremity work, I place one electrode over the popliteal fossa on each leg and a second set over the inguinal region, roughly tracking the superficial lymphatic pathways from distal to proximal. The exact placement matters more than generic diagrams suggest. I palpate the groin and behind the knee for lymph node clusters and position the electrodes within a centimeter or two of those landmarks rather than blindly following textbook illustrations. Before powering anything on, I check skin impedance at each contact site with a multimeter in resistance mode. If the skin is calloused, heavily keratinized, or covered in lotion residue, impedance can sit above two thousand ohms and the current will not penetrate properly. I clean the area with isopropyl alcohol, gently abrade dry patches with fine sandpaper if needed, and recheck. Impedance should read between four hundred and eight hundred ohms for reliable conduction. Then I apply a thin layer of conductive gel to each electrode and press them firmly into place. The gel thickness is critical. Too much gel causes current spread and reduces effective density at the target tissue. Too little increases skin irritation and creates uncomfortable hot spots under the electrode edges. A coin-sized amount per electrode is usually enough for a standard ten by ten centimeter pad.
I power on the generator and begin at zero output. The protocol I default to starts at a frequency around sixty hertz, which falls within the range that most studies associate with lymphatic smooth muscle stimulation. I ramp the amplitude slowly until the patient reports a gentle tingling sensation, never beyond mild comfort. Typical treatment amplitudes stay between two and five milliamps peak. Going higher does not improve drainage and increases the risk of muscle fasciculations and skin burns. I hold each frequency for roughly ten minutes before stepping down in ten hertz increments to forty hertz, then to thirty hertz, completing the sequence in about thirty to forty minutes total. During the session I monitor the skin under each electrode every ten minutes. Redness is normal. Blistering is not. If I see any localized darkening of the skin or the patient complains of sharp burning, I shut the output down immediately, remove the electrode, and document the incident. Treatment is never worth a first-degree burn.
Get the Full Details

What it actually feels like during a session
Most patients describe a deep, non-painful buzzing or pulsing sensation that is easiest to characterize as stronger than a typical TENS unit setting but without the skin-prickling quality. The lymphatic vessels themselves do not contain pain receptors, so the sensation comes from the surrounding tissue and cutaneous nerve endings responding to the electrical stimulus. A small number of people feel no sensation at all, especially if they have reduced peripheral sensitivity or higher skin impedance that limits current penetration despite adequate gel contact. In those cases I adjust the frequency slightly or reposition the electrode rather than simply cranking up the amplitude, because chasing zero sensation with higher current is how you create thermal injury. The most frequent error I see in beginners is placing electrodes directly over bony prominences. The current concentrates on the thin tissue over the medial malleolus or the patella and creates painful hot spots without meaningfully engaging the lymphatic channels running alongside those structures. I learned this the hard way early on with a patient who had moderate bilateral ankle swelling. I followed a printed diagram that showed electrode placement centered on the malleoli rather than in the soft tissue planes adjacent to them. The patient could not tolerate the treatment past six minutes and we had to stop. I repositioned both electrodes approximately two centimeters anterior and posterior to the malleolar ridges, over the softer retromalleolar and perimalleolar tissue where the superficial lymphatic network actually courses, and the session completed without incident. Another mistake is assuming that higher frequency means better drainage. The lymphatic system responds best to low frequencies in the twenty to one hundred hertz window. Frequencies above two hundred hertz begin to engage skeletal muscle motor units and produce visible twitching rather than lymphatic pumping. That is not the intended mechanism and it fatigues the patient without adding therapeutic benefit.
Limitations and when this approach fails
Electro Lymphatic Drainage Therapy is not a universal solution. It works reasonably well for secondary lymphedema in the limbs, post-surgical fluid retention, and certain cases of chronic venous insufficiency with a lymphatic component. It does not help lymphedema caused by active malignancy, severe cardiac failure, or advanced renal disease without addressing the underlying condition first. There is also a real contraindication list that most commercial device manufacturers do not emphasize enough: pacemakers and implanted defibrillators are absolute no-gos. Any area with active infection, thrombophlebitis, or open wounds should be avoided entirely. Pregnancy is another hard stop for trunk and pelvic treatments. The biggest bottleneck in practice is consistency. Many patients want results after one session. Lymphatic adaptation is gradual. Meaningful reduction in limb volume typically requires a course of eight to twelve sessions spaced two to three times per week, followed by maintenance treatments. Without that commitment, the technology is just an expensive tingling experience.
Alternatives worth considering
If Electro Lymphatic Drainage Therapy is unavailable or contraindicated, manual lymphatic drainage performed by a certified therapist remains the gold standard for outpatient lymphedema management. Intermittent pneumatic compression devices are another well-established option, though they require proper sleeve fitting and can be uncomfortable for some patients. I have also found that combining mild ELDT with compression garments worn during and immediately after treatment produces better volume reduction than either modality alone. The combination approach usually trims treatment time by roughly a third compared to ELDT alone, based on my clinical observations over several years. There is no download link for a working ELDT device. These are medical-grade tools or custom-built systems that require appropriate training and supervision. If you are looking to purchase equipment, focus on devices with adjustable frequency ranges below four hundred hertz, current limits clearly marked and enforced, and independent safety certification rather than cheap imported clones without regulatory clearance. The difference in reliability is significant and the safety implications are real. I do not claim this covers every clinical scenario. Lymphatic physiology is complex and individual responses vary. The notes above reflect what has worked in my practice and what I have seen fail. Use them as a starting point and adjust based on patient response, not as a substitute for professional medical evaluation when the underlying cause of swelling is unclear.