Understanding Electroconvulsive Therapy for Treatment-Resistant Conditions
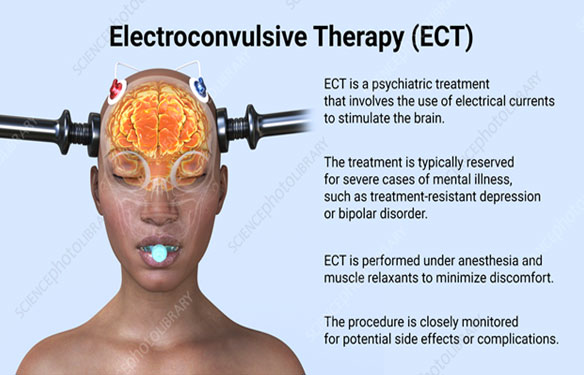
Electroconvulsive Therapy Is Effective In Alleviating Symptoms For People With severe depression, catatonia, and certain acute manic episodes. It is one of those medical treatments that sounds far worse than it actually is, largely because pop culture got it wrong decades ago and never corrected the record. The modern procedure is nothing like the horror stories people still recycle. It is administered under general anesthesia, with muscle relaxation, in a controlled clinical setting. The seizure itself lasts maybe thirty to sixty seconds. The patient sleeps through all of it. The mechanism is not fully mapped out, which is honestly the most honest thing about it. What we know is that inducing a brief, controlled seizure appears to cause neuroplastic changes — things like increased BDNF (brain-derived neurotrophic factor), modulation of serotonin and dopamine systems, and reduced inflammatory markers in the CNS. It is not "resetting" anything like a computer reboot. That metaphor is wrong and misleading. It is more like forcing a system that has been stuck in a pathological loop to break out of it, though nobody would claim to understand the exact circuit-level mechanism. I have sat through enough case discussions and read enough outcome data to say this with confidence: ECT works fastest and most reliably for psychotic depression and catatonia. The response rates in those categories hit 70 to 90 percent in published studies. For unipolar treatment-resistant depression, you are looking at roughly 50 to 70 percent response, depending on how you define "response." Numb. Not exciting. But clinically meaningful when the alternative is a patient who has not eaten properly in weeks or is refusing to move.
The Procedure as It Actually Unfolds
A standard course runs two to three times per week for about six to eight sessions. That is the typical acute phase. Some patients get a maintenance phase after that, usually spaced out to once every one to four weeks. The whole appointment takes about two hours from arrival to discharge, though only twenty minutes of that is actual treatment time. The rest is anesthesia induction, monitoring setup, recovery from the anesthetic, and paperwork. Electrode placement matters more than most people realize. Right unilateral (RUL) placement uses the dominant hemisphere sparingly and tends to produce fewer cognitive side effects. Bitemporal placement is more effective for some patients but carries a higher burden of memory disruption. The choice between them is not trivial. I once worked with a patient who had a bitemporal course and could not remember anything from the six months leading up to treatment. He was devastated, not by the depression anymore, but by the fact that he could not recall his daughter's wedding from the year before. We switched him to RUL with adjusted dosage for his next series, and the memory issues improved substantially, though they did not fully resolve. That is a real trade-off clinicians have to navigate, and it is rarely discussed in patient brochures. Anticoagulant management is another practical headache. If a patient is on warfarin or a DOAC, the team needs to coordinate with hematology or cardiology. A common workaround I have seen used is bridging with heparin for patients on warfarin, holding the DOAC for one to two doses before treatment, or timing sessions around the drug's half-life. Blood work and coagulation panels are checked before each session if the patient is on blood thinners. It adds logistical friction but is manageable with good care coordination.
Common Misconceptions That Need To Die
First, ECT does not cause permanent personality change. It does not turn anyone into a different person. Memory loss is real but typically retrograde and temporally limited — events surrounding the treatment window. Most people recover the bulk of their memories within weeks to months after the course ends. Second, it is not a last resort in the sense of being experimental or desperate. For psychotic depression and catatonia, it is often first-line because the risk-benefit ratio favors it over waiting weeks for medications to work. Third, the electricity dose is tiny. Modern ECT devices deliver somewhere in the range of 0.5 to 2.0 coulombs. That is not a defibrillation-level shock. The seizure threshold is determined individually for each patient through dose titration. Response rates vary by diagnosis. Psychotic depression: strong evidence. Catatonia: strong evidence. Treatment-resistant unipolar depression: moderate to strong evidence. Bipolar depression: moderate evidence. Obsessive-compulsive disorder: emerging but limited evidence. Schizophrenia with prominent mood symptoms: some benefit, but not a primary treatment. If someone has vascular depression with significant structural brain changes from small vessel disease, the response rate drops noticeably. Age matters too — older patients tend to respond better cognitively but also have more medical comorbidities to manage during anesthesia. I encountered a patient once who had failed four adequate medication trials, two courses of psychotherapy, and a trial of TMS before being referred for ECT. She had severe melancholic features, marked psychomotor retardation, and active suicidal ideation. She responded to her fourth ECT session. By session six, she was eating regular meals and making eye contact. She completed eight sessions and entered a maintenance phase. Sixteen months later, she was stable on a maintenance schedule of weekly ECT. That is the kind of outcome that makes the memory side effects feel like a reasonable price, though she still brought it up every other session and we never minimized it for her.
Get the Full Details

Conversely, patients with prominent executive dysfunction from frontotemporal dementia or advanced Alzheimer's rarely benefit and may worsen. ECT in that population is generally not recommended except in very rare circumstances where catatonia is the primary concern and other treatments have failed. The risk-benefit calculation flips entirely.
Practical Considerations Before Starting
Pre-treatment workup includes a medical history, physical exam, baseline ECG, basic blood work, and often a dental evaluation because the muscle relaxant can cause tooth injury during the seizure if precautions are not taken. A mouthpiece or bite block is standard, but I have seen cases where a patient with poor dentition still chipped a filling despite the bite block. The anesthesia team should be briefed on dental status ahead of time. It is a small thing that gets overlooked. Patient education should happen before the first session, not after. I have seen too many patients arrive on day one with a list of impossible fears — that they will be paralyzed while awake, that the shock will burn their organs, that they will lose their soul. None of that is true, but it is still what they are carrying. A fifteen-minute conversation with the treating psychiatrist and the anesthesiologist covering the actual process, the expected side effects, and the realistic timeline for improvement reduces a lot of preventable anxiety. The biggest practical bottleneck I see is insurance authorization. In many systems, ECT requires prior authorization and sometimes step therapy — proof that multiple medication trials have failed. That delay can be dangerous for a patient who is actively suicidal or catatonic and not eating. I have seen patients held on psychiatric units for weeks waiting for authorization while their medical status deteriorated. Knowing your local insurance requirements and having a social worker or case manager involved early can cut that wait from weeks to days in many cases.
The Cognitive Side Effects Nobody Talks About Enough
Short-term: confusion immediately after each session, lasting perhaps ten to thirty minutes. This is universal and normal. Longer-term: autobiographical memory gaps, especially for events in the month before and after treatment. That is the painful part. Most people recover these memories, but some do not, and the ones who do not are the ones who need the most support, not the most dismissal. A 2023 systematic review found that persistent memory deficits affect roughly 10 to 20 percent of patients at six-month follow-up. The numbers are small but the impact is not. I know that because I sat with a patient who could remember every detail of her childhood but not the previous summer. She described it as feeling like a page had been torn out of her life. That is not something to minimize. But it is also not universal, and it is not static for most people. If memory preservation is a priority, right unilateral placement with dose titration to 1.5 times the seizure threshold is the best strategy available. There is no perfect option. There is only a trade-off between efficacy and cognitive burden, and the balance shifts depending on what is killing the patient right now.

When ECT Is Not the Answer
There are absolute contraindications that are essentially nonexistent in modern practice — there is no condition that absolutely prohibits ECT except perhaps an intracranial mass lesion with raised pressure, and even that is relative. The real question is whether the risks outweigh the benefits in a given individual. A patient with recent myocardial infarction, uncontrolled hypertension, or a bleeding diathesis needs careful multidisciplinary evaluation. Anesthesia risk increases with each comorbidity. The ASA classification system is useful here — patients classified as ASA III or higher have measurably higher complication rates. For mild to moderate depression, ECT is almost never appropriate. SSRIs, SNRIs, psychotherapy, lifestyle modification — those are the front line. ECT is for when those options have failed or when the illness is severe enough that waiting for a medication to work is itself dangerous. It is a tool for the worst cases, not a general treatment for all depression. Treating it as anything other than that is malpractice by optimism. The data is clear on this. Electroconvulsive Therapy Is Effective In Alleviating Symptoms For People With the conditions it targets, but it is not a miracle and it is not harmless. It is a medically necessary intervention for people who are failing everything else, and it deserves to be discussed without the stigma that still clings to it from an era before anesthesia and muscle relaxants made it what it is now.