Working Through Electrolyte Imbalance in Clinical Practice
Electrolyte imbalances show up constantly on medical-surgical floors, and the nursing diagnosis portion is where most documentation falls apart. The labs look like a foreign language at 2 AM, and by the time you figure out what's actually wrong, the physician has already seen the numbers. Writing a proper Electrolyte Imbalance Nursing Diagnosis requires connecting lab values to actual patient presentation, not just copying textbook definitions into your notes. Here is how I approach it in practice. First, grab the most recent BMP or CMP and pull out sodium, potassium, calcium, magnesium, and chloride. Then check the patient's actual condition against those numbers. A potassium of 3.1 with muscle cramps and an abnormal ECG tells a completely different story than a potassium of 3.1 on an asymptomatic patient who happens to be on losartan. The diagnosis needs to reflect what is happening to the person in front of you, not just what the lab slip says.
Electrolyte Imbalance Nursing Diagnosis: The Practical Framework
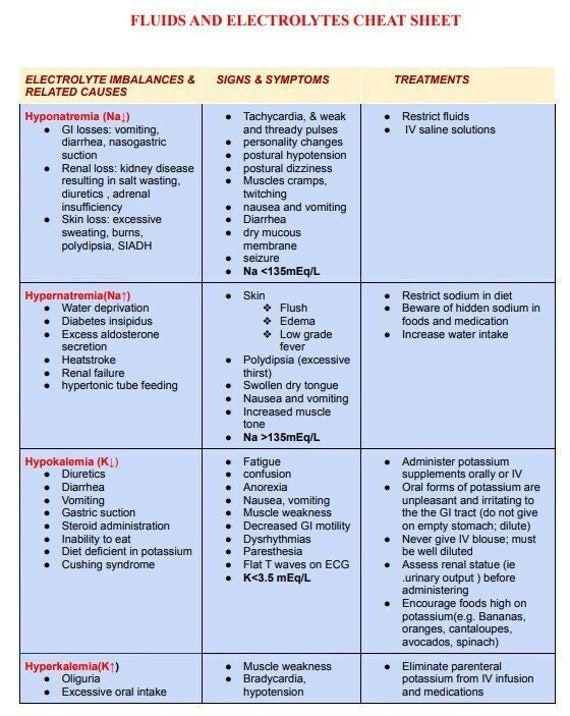
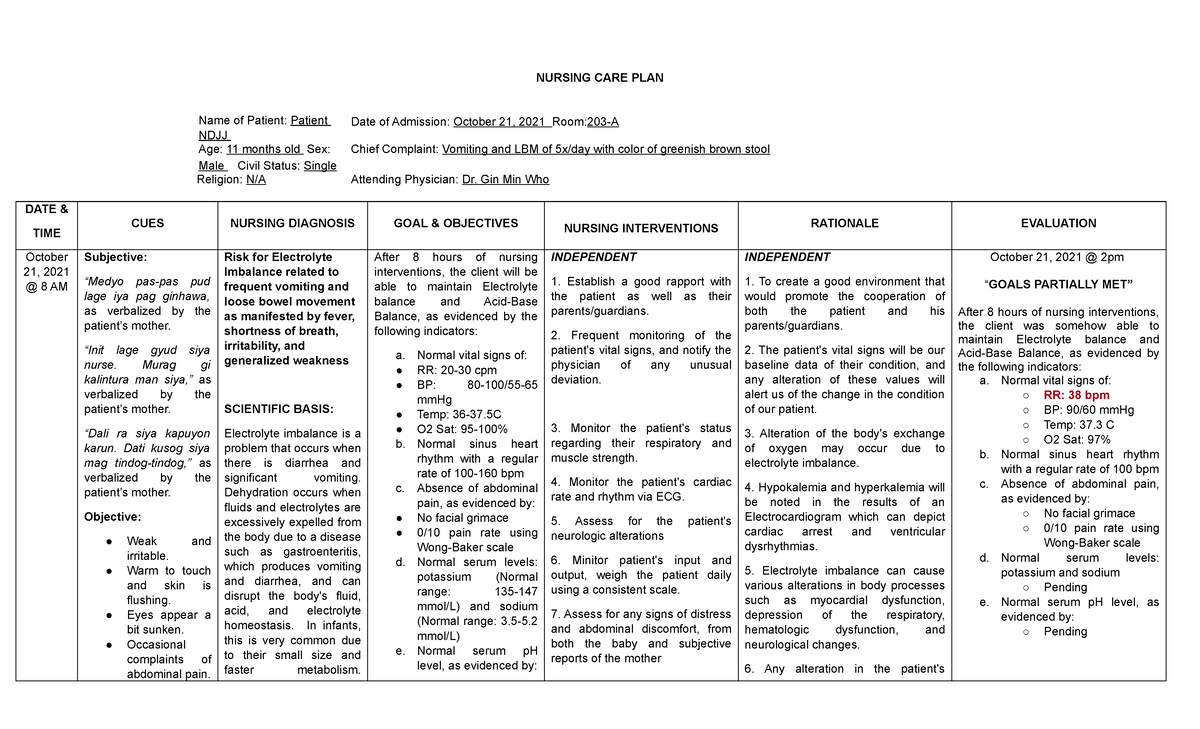
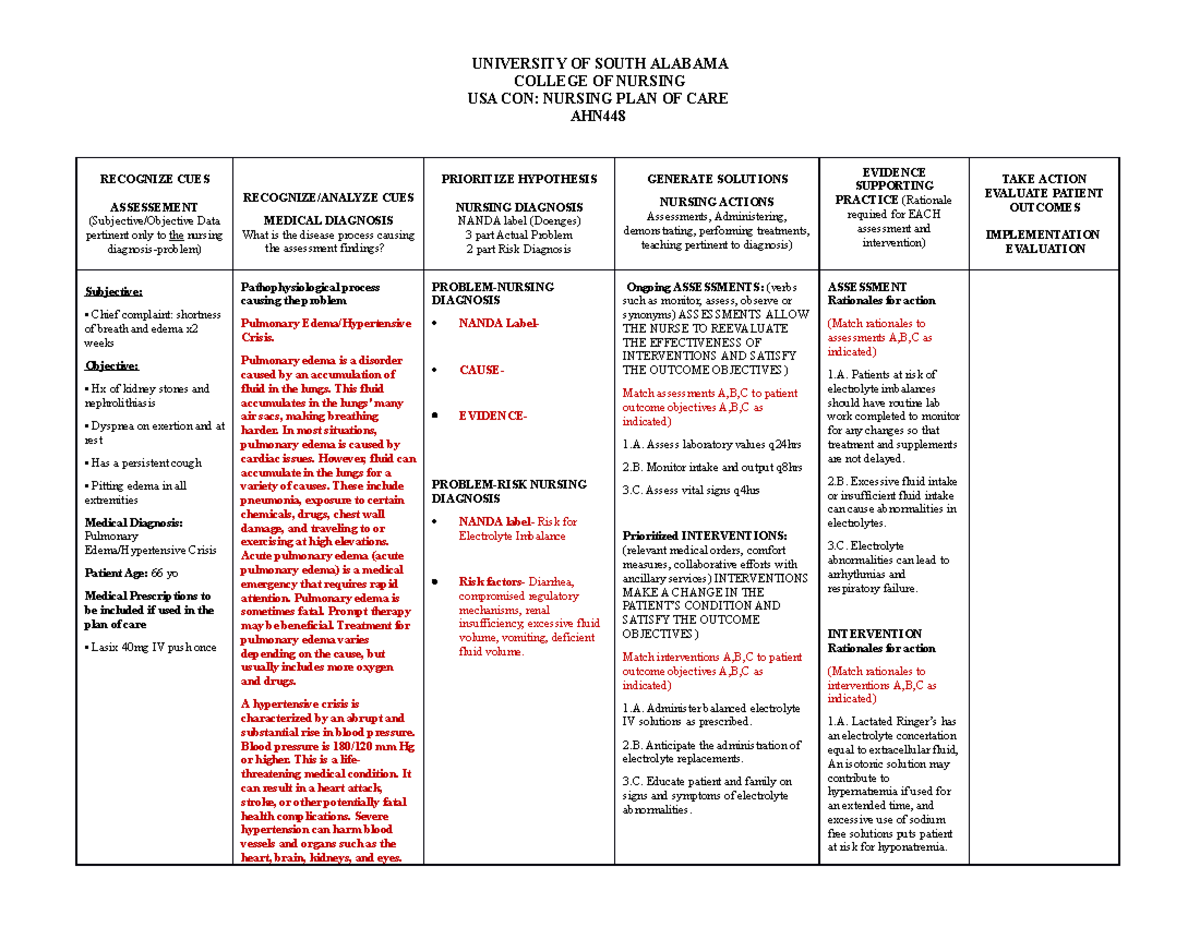
The NANDA framework for electrolyte issues usually centers on two main diagnoses. Deficient Fluid Volume and Excess Fluid Volume cover a lot of ground when it comes to sodium and water shifts. Risk for Electrolyte Imbalance is the safer bet when labs are trending in the wrong direction but haven't crossed a critical threshold yet. Then there is Risk for Falls tied directly to the imbalance itself, which is often overlooked but critically important for documentation. What most people miss is the related-to and as-evidenced-by components. Those are not optional filler. The related-to portion needs to point at a specific cause that you can actually intervene on. "Related to fluid volume deficit secondary to diuretic therapy" gives you a clear treatment pathway. "Related to imbalance" is useless because it doesn't tell anyone what to do next. The as-evidenced-by section should reference objective data from the chart. Lab values, vital sign trends, intake and output records, physical assessment findings. I keep a running list of acceptable evidence criteria in my chart so I am not wasting time looking up normal ranges every shift. Potassium below 3.5 with ECG changes showing U waves. Sodium below 135 with altered mental status. These are the things that carry clinical weight.
I ran into a case last year that tested how rigidly you should follow the textbook definition. A post-op thyroidectomy patient came in with calcium at 7.8, borderline low. She had no Chvostek sign, no Trousseau sign, no perioral numbness, no muscle twitching. Nothing clinically. The textbook would suggest a nursing diagnosis of Deficient Fluid Volume or Risk for Injury related to hypocalcemia, but the patient was entirely asymptomatic. What actually happened was her albumin was 2.8, which meant the total calcium was artificially low. Her ionized calcium was normal. I documented Risk for Electrolyte Imbalance related to post-surgical state as evidenced by low total calcium with concurrent hypoalbuminemia, and I flagged it for the attending. That turned out to be the right call because her calcium dropped to 6.9 the next morning once the albumin effect faded. If I had gone with a standard Hypocalcemia diagnosis, I would have started unwarranted calcium supplementation and potentially caused hypercalcemia. That edge-case highlights something important about this work. Lab values are starting points, not conclusions. You have to understand what is driving the abnormal number before you write a diagnosis that guides the entire care plan.
Get the Full Details

Common Pitfalls and Where the Method Breaks Down
The biggest problem with electrolyte nursing diagnoses is that they become checkbox exercises. You see an abnormal lab, you pick a NANDA label, you copy-paste the evidence from the last nurse's notes, and you move on. The diagnosis sits in the record doing nothing. It never translates into actual interventions or reassessment priorities. Another frequent mistake is writing diagnoses that are impossible to measure. Imbalanced Nutrition: Less Than Body Requirements related to hypokalemia sounds reasonable until you realize there is no measurable outcome criterion attached to it. How do you know if the nutrition intervention worked? You need specific, time-bound outcomes. Potassium above 4.0 within 48 hours. Resolution of muscle weakness. Normal cardiac rhythm on telemetry. Without those endpoints, the diagnosis is just paperwork. Potassium disorders deserve special attention because the margin between safe and dangerous is extremely narrow. A potassium of 5.8 might look manageable on paper, but combine that with renal failure, digoxin use, and an ECG showing peaked T waves and you are dealing with a situation that can deteriorate in minutes. The nursing diagnosis should capture that urgency. Risk for Decreased Cardiac Output related to hyperkalemia as evidenced by peaked T waves on cardiac monitor and potassium level of 5.8 mEq/L. That diagnosis demands continuous cardiac monitoring, avoiding potassium-containing IV fluids, and immediate provider notification if the potassium rises further. Anything less understates the actual clinical risk.
Sodium disorders are the opposite problem. They deteriorate slowly and quietly. A sodium of 128 does not usually make a patient look critically ill. They might be slightly fatigued, slightly confused, slightly off. Write a diagnosis of Acute Confusion related to hyponatremia as evidenced by sodium level of 128 mEq/L and intermittent disorientation during assessment. That documentation creates a baseline. When the sodium climbs too fast during correction, you have already established that neurologic status was the assessment priority, and rapid correction complications become immediately apparent.
Building a Care Plan That Actually Works
Once the diagnosis is written, the care plan needs to be actionable and measurable. Interventions should flow directly from the related-to factor. If the imbalance is diuretic-induced, the interventions include monitoring intake and output hourly, weighing the patient daily, administering replacement electrolytes as ordered, and assessing for signs of overcorrection. If the imbalance is secondary to poor oral intake, the focus shifts to dietary consultation, supplement administration, and monitoring for refeeding syndrome in malnourished patients. Reassessment frequency matters more than people realize. A patient with an active electrolyte imbalance should be reassessed at least every four hours during the acute phase. Neurologic checks for sodium disorders. Cardiac rhythm monitoring for potassium and magnesium abnormalities. Neuromuscular assessments for calcium and magnesium issues. Documentation of these reassessments proves whether your interventions are working or whether the patient is deteriorating despite treatment. One thing that surprises people is how frequently electrolyte imbalances coexist. Hyponatremia with hypokalemia is common in patients on thiazide diuretics. Hyperkalemia with hypocalcemia shows up in renal failure patients. Writing separate nursing diagnoses for each imbalance and addressing them individually produces a fragmented care plan. A single comprehensive diagnosis that addresses the interaction between the abnormalities produces better outcomes. Risk for Electrolyte Imbalance and Fluid Volume Deficit related to diuretic therapy and renal compromise as evidenced by sodium of 131, potassium of 3.2, and BUN to creatinine ratio of 35:1.
The interdisciplinary communication piece is where this all breaks down in most hospitals. The nursing diagnosis sits in the nursing note, the physician writes a different diagnosis in the progress note, and the two documents never intersect. Share your nursing assessments during handoff and make sure the physician is aware of the specific electrolyte concerns you have identified. A potassium trend from 3.4 to 3.1 over 24 hours might not trigger a page at 3.1, but it absolutely deserves attention when someone knows the trajectory.
What This Approach Does Not Solve
Writing a strong Electrolyte Imbalance Nursing Diagnosis does not fix systemic problems in your facility. If you are short-staffed and carrying six patients with complex electrolyte issues, no amount of documentation will give you the time you need for proper reassessment. If your hospital does not have continuous telemetry for floor patients with known potassium abnormalities, the diagnosis becomes a liability rather than a protection. If electronic health record templates force you into checkbox diagnoses with no room for narrative detail, you are fighting the system rather than helping the patient. The diagnosis itself cannot replace physician collaboration. It is a nursing tool for organizing assessment data and guiding nursing interventions. It does not order labs, it does not prescribe replacement therapy, and it does not determine the rate of correction. Those decisions belong to the medical team. What the nursing diagnosis does is ensure the nurse is actively monitoring, documenting trends, and escalating concerns appropriately. The most reliable workaround I have found is keeping a one-page electrolyte reference sheet at the nurses' station. It covers the major abnormalities, their ECG manifestations, safe correction rates, and the nursing interventions most likely to help. Ten minutes of reference checking prevents three hours of chart diving later. It also standardizes documentation across the unit so that different nurses write comparable diagnoses rather than varying wildly in terminology and specificity.