EMT and Who Shouldn't Be Treated
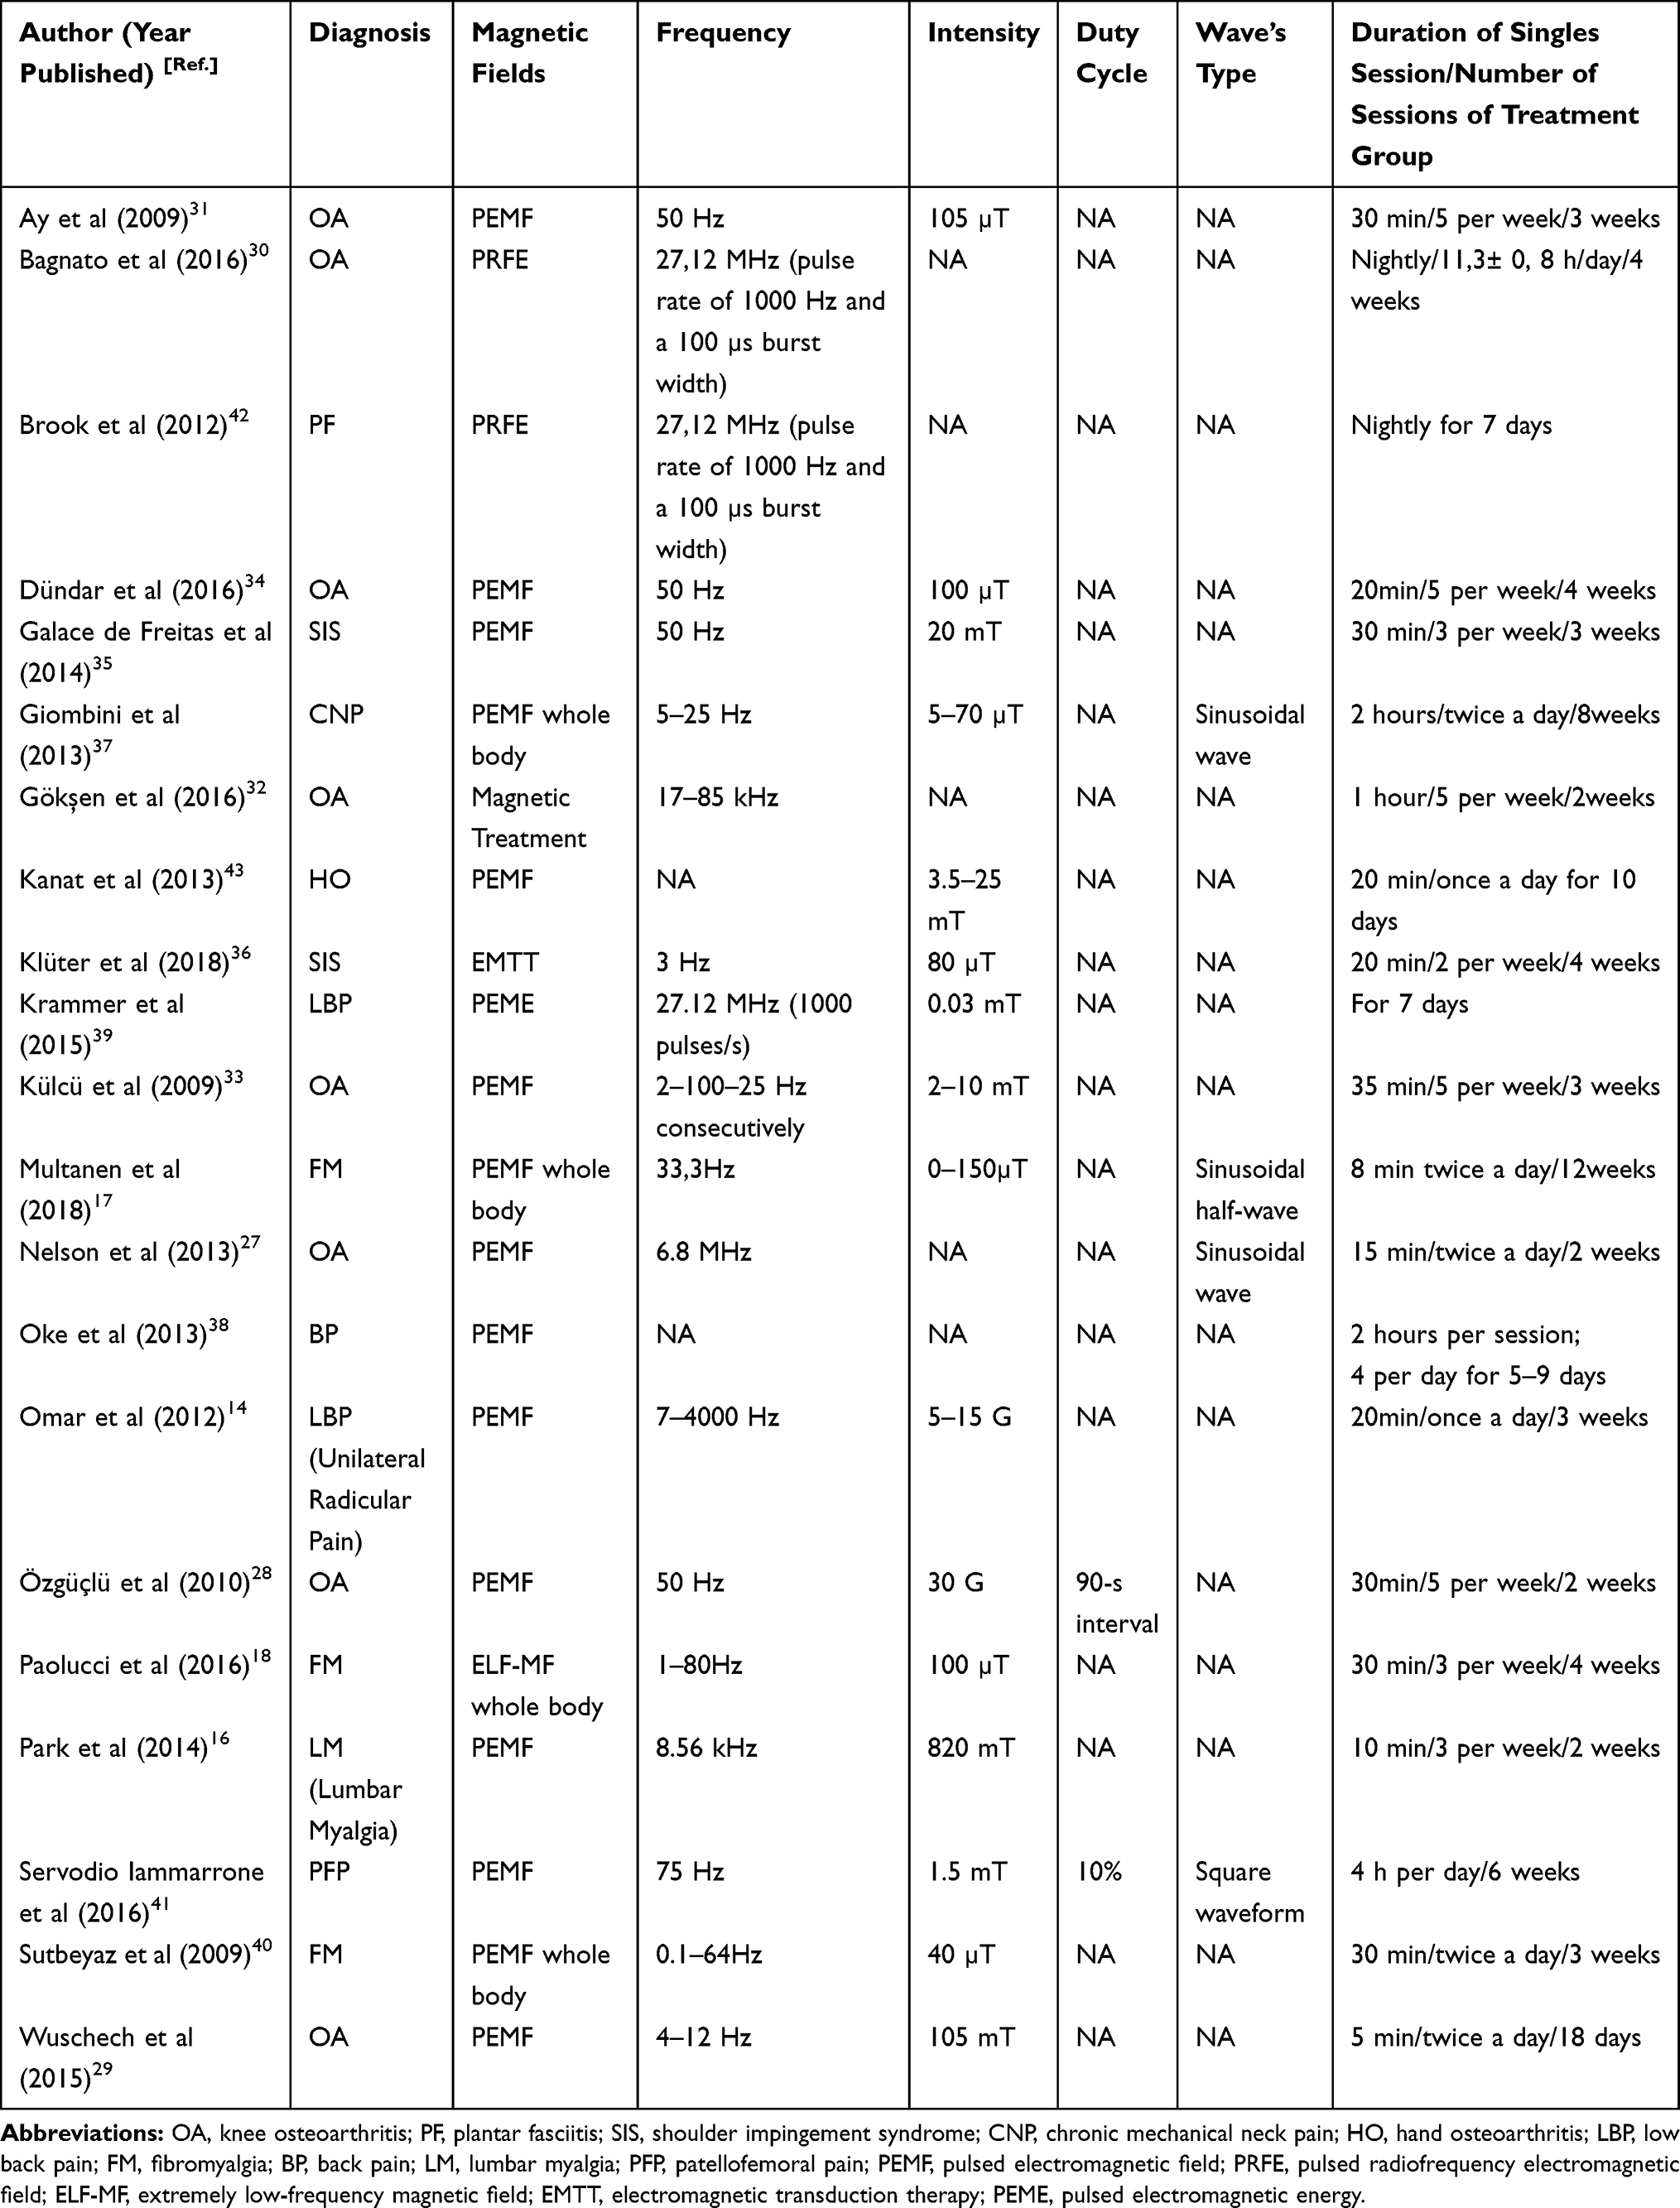
When you're running pulsed electromagnetic field sessions on patients, the first question nobody likes to ask is who gets burned by ignoring the contraindications. I've seen this go wrong more than once in clinical practice, and it's almost always the same story: someone skipped the screening form because the patient looked fine and now they're dealing with a pacing artifact or a bleeding episode that could've been prevented. Electromagnetic Field Therapy Contraindications fall into two buckets — absolute, meaning you don't touch the device, and relative, meaning you adjust the parameters or get clearance from the patient's physician first. The absolute list is short but important.
Pacemakers and Implanted Electronics
This is the big one. If your patient has a pacemaker, ICD, deep brain stimulator, spinal cord stimulator, or any other implanted electronic device, you're not doing EMT on them without explicit cardiology or neurology sign-off. The fields from therapeutic EMF devices can induce currents in the lead wires of these implants, causing reprogramming, inhibition of pacing, or inappropriate shocks. I ran into this with a 68-year-old male who'd had a biventricular CRT-D placed two years prior. His physiotherapist wanted to treat his diabetic neuropathy with PEMF. I reviewed the device literature — the Medtronic Advisa MRI-conditional system has specific SAR limits, but those apply to diagnostic MRI, not necessarily therapeutic PEMF coils operating at 15-50 Hz. We cleared it with his electrophysiologist, kept the intensity below 2 mT at the skin surface, and monitored his telemetry during the first session. Nothing happened, but we wouldn't have known if we hadn't checked. No EMT on pregnant patients. Period. The evidence base is thin — there are no large randomized trials showing harm, but there are also no trials proving safety. That's not an acceptable risk profile when you're talking about fetal tissue. The developing nervous system is highly sensitive to environmental stimuli, and while therapeutic EMF intensities are low, the precautionary principle applies. I've had patients ask me about using handheld PEMF units at home during early pregnancy for restless leg symptoms. I tell them no and point them toward magnesium supplementation and compression stockings instead. EMF can influence cell proliferation and angiogenesis. There's no clean evidence that it causes cancer to grow, but there's also no evidence that it doesn't. If a patient has an active, untreated tumor or a history of malignancy within the past five years without medical oncology clearance, you don't apply EMT over or near the tumor bed. The theoretical concern is that enhanced local blood flow and cellular signaling could facilitate metastatic spread. I work with an oncology rehab group and the protocol is clear: radiation and chemotherapy patients are off the table until their hematologic counts recover; survivors in remission need written approval from their oncologist before any field therapy near the original disease site.
EMF increases local circulation. If someone has an active GI bleed, recent hemorrhagic stroke, hemophilia, or is on therapeutic anticoagulation with an INR above 3.0, you're amplifying a problem that already exists. I've seen post-surgical patients try to speed up their recovery with PEMF pads while still on enoxaparin bridges. The bruising patterns were extensive and the surgical site oozed longer than expected. Not causal, maybe, but unnecessary risk when the alternative is waiting six weeks post-op. These aren't hard stops, but they require modification of your treatment approach. Seizure disorders come first — certain frequency ranges, particularly in the 20-40 Hz gamma band, can theoretically lower seizure threshold in susceptible individuals. I keep the frequency below 15 Hz for any patient with a history of epilepsy and avoid gamma-frequency protocols entirely unless a neurologist has explicitly approved it. Acute inflammation is another gray area. Early-stage soft tissue injury benefits from reduced-intensity EMF to limit swelling, but high-intensity protocols during the first 72 hours of an acute sprain can worsen edema. The literature on this is mixed, but clinically I've found that starting at 1 mT and ramping over three sessions works better than jumping straight to 4 mT on day one. Patient feedback matters — if they report increased warmth or throbbing at the treatment site, drop the intensity immediately.
Get the Full Details
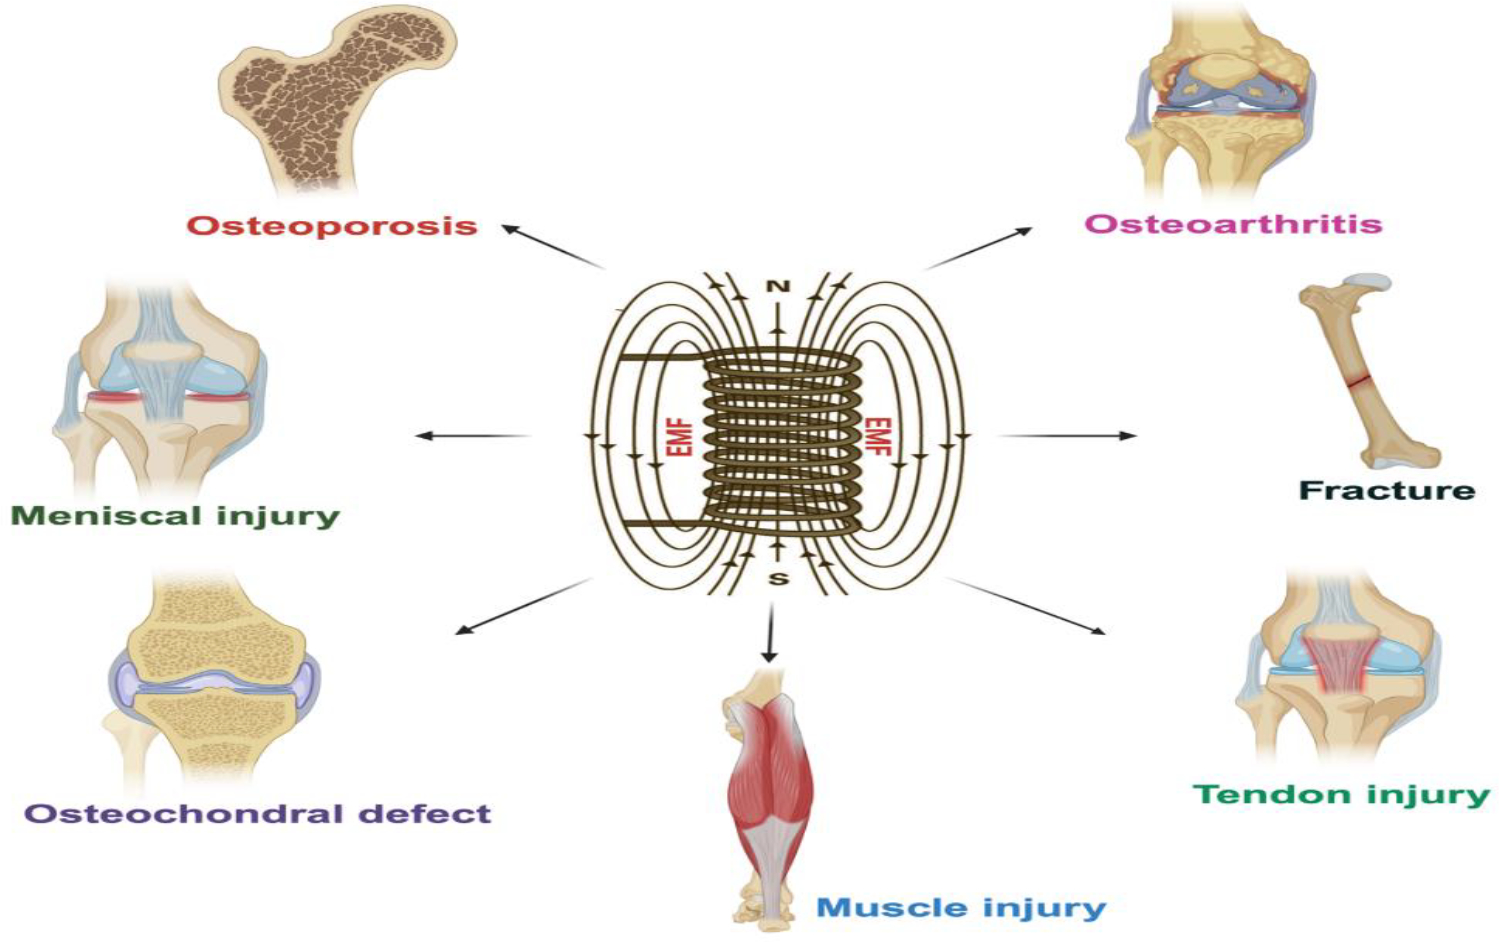
Metal hardware — plates, screws, rods, joint replacements — isn't an absolute contraindication, but it changes the field distribution. Ferromagnetic materials concentrate flux lines and create hot spots. I avoid direct placement of the coil over orthopedic hardware and increase the distance by at least 5 cm. For titanium implants, which are non-ferromagnetic, the effect is minimal and standard protocols apply.
Electromagnetic Field Therapy Contraindications: Practical Screening
Here's what I actually do before every session. It takes about 90 seconds and has saved me from three potential adverse events in the last two years. I ask five questions: Do you have any implanted electronic devices? Are you currently pregnant or trying to conceive? Have you been diagnosed with cancer in the last five years? Are you on blood thinners or have a bleeding disorder? Have you ever had a seizure or epilepsy diagnosis? If any answer is yes, I stop and document the finding before proceeding. I also check the device's own manual. Most PEMF systems list their own contraindications, and some go beyond the standard medical guidelines. The Bemer devices, for example, specify that patients with thyroid implants should not be treated — a restriction that isn't in the broader literature but exists for liability and caution reasons. You follow the manufacturer's instructions because if something goes wrong, that manual is the first thing a lawyer will produce. The bottom line is that EMT is generally safe when you respect the contraindications. Most adverse events I've encountered or read about trace back to skipping the screening step, not to the physics of the treatment itself. A systematic check before every session costs nothing and prevents the kind of complications that turn a routine therapy into a lawsuit or an ER visit.