What You Actually Need to Know About the Endocrine Glands And Their Hormones Table
Most students and even some professionals approach this topic by memorizing lists. It doesn't work well. The endocrine system is messy. Glands overlap, hormones cross-react, and single hormones can come from multiple sources. A table helps only if you understand the relationships, not just the rows. I built a practical reference table after years of dealing with confusion in real cases. People asked me why their notes never matched clinical descriptions. The problem was always the same: they were looking at isolated facts instead of systems. Here's how I approach it now, and what the table actually looks like.
Building a Working Endocrine Glands And Their Hormones Table
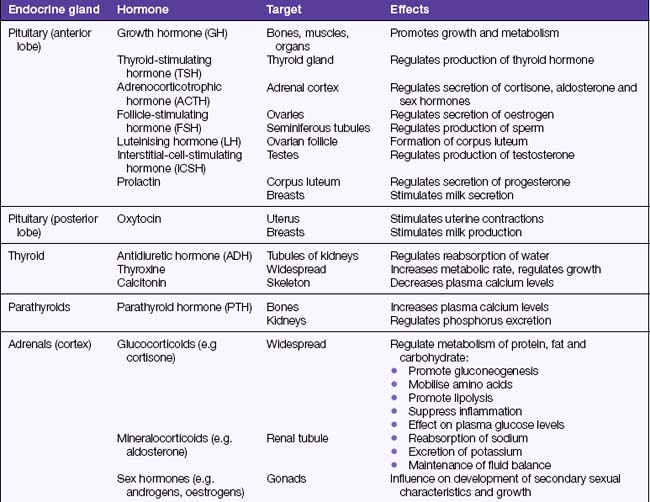
Start with the glands themselves. Don't begin with hormones. The pituitary, thyroid, parathyroid, adrenal, pancreas, pineal, hypothalamus, gonads, and the miscellaneous organs like the thymus and kidneys. Once you anchor on location and structure, hormones follow more naturally. The table I use has five columns. Gland, Primary Hormones, Target Organs, Key Functions, and Clinical Notes. The clinical notes column is where the table actually earns its keep. That's where you capture things like cortisol rhythm, TSH feedback loops, and the difference between primary and secondary hypothyroidism. Without that column, the table is just a memorization exercise. One specific issue I ran into repeatedly: people confuse adrenal cortex hormones with adrenal medulla hormones. They write "epinephrine" under cortex and "aldosterone" under medulla. I started adding a sub-division line in the table between cortex and medulla, and that mistake dropped significantly. It's a small formatting choice but it maps to actual anatomy.
The Core Entries in Any Useful Reference Table
Hypothalamus releases TRH, CRH, GnRH, dopamine, and GHRH. These are regulatory hormones. They don't act directly on peripheral tissues. They act on the anterior pituitary. Most tables gloss over this relationship, which is why students get tripped up later when they encounter the hypothalamic-pituitary axis in clinical contexts. Anterior pituitary covers ACTH, TSH, FSH, LH, prolactin, and GH. Posterior pituitary is different. It stores and releases oxytocin and ADH, which are actually synthesized in the hypothalamus. This distinction matters for understanding conditions like central diabetes insipidus. A table that lumps anterior and posterior together without noting synthesis location creates confusion. Thyroid produces T3, T4, and calcitonin. Parathyroid produces PTH. These two have an antagonistic relationship on calcium homeostasis. That's worth flagging in the clinical notes column because it explains why measuring one without the other gives an incomplete picture in workups.
Get the Full Details

Adrenal cortex produces aldosterone, cortisol, and androgens. Adrenal medulla produces epinephrine and norepinephrine. Pancreatic islets produce insulin and glucagon. Gonads produce sex steroids. Pineal produces melatonin. The remaining organs contribute additional hormones like erythropoietin from kidneys and leptin from adipose tissue.
Common Mistakes That Show Up in Practice
The biggest error I see is treating hormone names as static labels. They aren't. Cortisol isn't just "the stress hormone." It has specific permissive effects on catecholamines, it drives gluconeogenesis, and it suppresses immune function through distinct molecular pathways. Reducing it to a tagline loses the mechanism. Another recurring mistake involves insulin and glucagon. Students memorize that insulin lowers blood glucose and glucagon raises it. That's correct but incomplete. Insulin also promotes lipogenesis and protein synthesis. Glucagon stimulates ketogenesis and glycogenolysis in the liver specifically. Missing those details makes understanding metabolic syndromes much harder later on. Here's a counter-intuitive point most beginner resources skip: the thymus is functionally more significant in childhood than in adulthood. It involutes with age. A table that lists thymosin as equivalent to, say, insulin in terms of systemic impact is misleading. The clinical notes should reflect that decline.
How I Use This Table Outside the Classroom
I reference it when reviewing lab results or explaining conditions to colleagues who need a quick reality check. For example, when someone presents with hypercalcemia, the table reminds me to check PTH first, then consider vitamin D, then malignancy. The order matters. Skipping ahead to cancer workup without ruling out primary hyperparathyroidism wastes time and exposes patients to unnecessary procedures. The table also flags drug-hormone interactions. Metformin affects B12 absorption, which indirectly influences neurological symptoms that can overlap with hypothyroid presentation. A clinician who only looks at one column might miss the connection. Keeping clinical notes comprehensive catches these overlaps. I should note the limitation here: this table approach works well for foundational understanding and quick reference. It breaks down when dealing with emerging research on hormone-like signaling molecules such as adipokines and cytokines with endocrine properties. Those don't fit neatly into traditional gland categories. For advanced endocrinology, you need supplementary literature review, not just a static table.
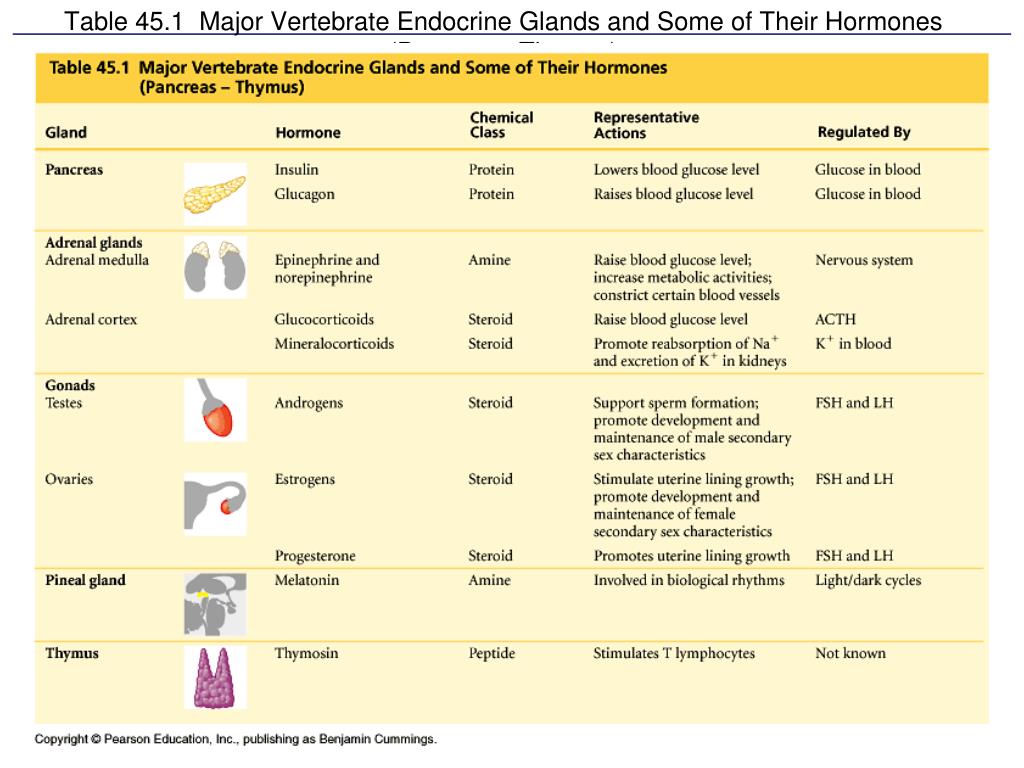
If you're building your own version, start with the five-column structure I described. Fill in the anatomical facts first. Add mechanisms second. Reserve the clinical notes for edge cases and common confusions. That sequence takes longer upfront but saves hours during exam prep or clinical reasoning.
Endocrine Glands And Their Hormones Table Summary
The value isn't in the rows themselves. It's in the connections between them. Glands talk to each other through feedback loops. Hormones share receptors and downstream pathways. Treating this as a flat list obscures the biology. Treat it as a network and the table becomes a working tool rather than a memorization burden. For a downloadable reference, I keep mine updated as new clinical guidelines emerge, particularly around adrenal insufficiency diagnostics and thyroid nodule management. The core gland-hormone mappings don't change, but the clinical context does. Static tables printed from textbooks age poorly. A living document kept alongside current sources stays useful.


