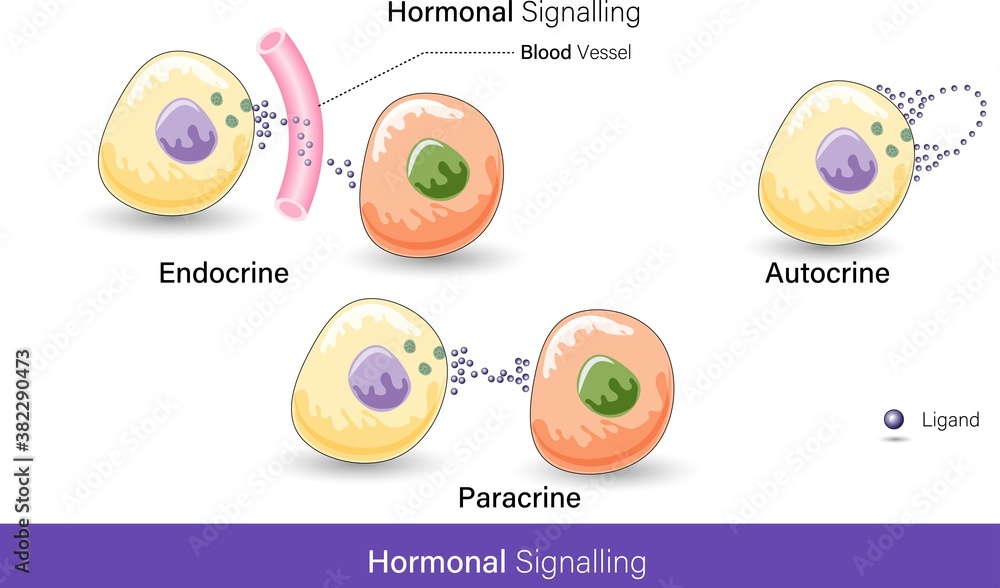
How Signaling Actually Works Outside a Textbook
I spent three years studying receptor desensitization in adipose tissue and honestly, the first time I truly understood the difference between endocrine, paracrine, and autocrine signaling wasn't in a lecture hall. It was when my cell culture plates kept giving me inconsistent insulin response data and I had to figure out whether the signals I was measuring were coming from the media, the cells themselves, or contaminants in the serum. Here is the straightforward breakdown of how these three signaling modes function, what they look like in practice, and where people routinely mess up their experiments or their understanding.
The Endocrine Paracrine And Autocrine Distinction
Endocrine signaling is the long-distance broadcast. A cell releases a hormone into the bloodstream, and that hormone travels throughout the body until it finds target cells with the right receptor. Insulin from the pancreas, thyroid hormones from the thyroid gland, cortisol from the adrenal cortex. The key feature is distance and systemic distribution. The signal dilutes as it goes, which is why endocrine signals typically require relatively high concentrations at the source and why the body needs feedback loops to prevent runaway effects. Paracrine signaling is local. A cell releases signaling molecules that diffuse through the extracellular fluid to affect nearby cells. The classic example is neurotransmitter release at a synapse, though technically that is often classified separately as synaptic signaling. More typical paracrine examples include histamine release from mast cells during inflammation affecting neighboring blood vessels, or the signaling molecules used during embryonic development where a gradient of morphogens tells cells what to become based on their distance from the source. Autocrine signaling is self-signaling. A cell produces a signaling molecule that binds to receptors on its own surface. This sounds like a loop that would cause infinite amplification, but it is tightly regulated. Immune cells like T-cells use autocrine signaling through interleukin-2 to stimulate their own proliferation after encountering an antigen. Cancer cells frequently hijack autocrine pathways to drive their own uncontrolled growth. That is one reason why many anticancer drug targets focus on autocrine growth factor loops.
What Nobody Tells You About Experimental Design
The biggest pitfall I see, both in student labs and in published research, is failing to account for paracrine contamination when you think you are measuring pure endocrine or autocrine effects. I had a project where I was studying leptin signaling in hypothalamic neurons. I wanted to measure autocrine leptin effects. But the astrocytes in my mixed culture were secreting leptin in response to the same stimuli, and that leptin was acting on my neurons through paracrine signaling. My "autocrine" results were mostly paracrine. It took me about six weeks and a switch to pure neuron cultures to get data that actually meant anything. Here is how I fixed it. I moved to primary neuron cultures without glial support, used conditioned media transfer experiments to distinguish autocrine from paracrine contributions, and validated everything with receptor blocking antibodies. The conditioned media approach is particularly useful. You grow cells in one medium, collect that medium, and apply it to fresh cells. If the signal carries over, it is soluble and extracellular. If it does not, you may be dealing with membrane-bound signaling or contact-dependent mechanisms. Another thing that catches people off guard is that the classification is not always clean. Many signaling molecules function through all three modes depending on context and concentration. Nitric oxide is a paracrine signal at synapses but can also act in an endocrine-like fashion when produced systemically during inflammatory responses. Growth factors like EGF can be autocrine in cancer cells, paracrine in wound healing, and neither in normal quiescent tissue. The molecule itself does not determine the category. The concentration, the distance to the target, and the presence of receptors on nearby cells determine that.
Get the Full Details

Practical Considerations That Matter
If you are working with these signaling types in a lab setting, here are the concrete things you need to handle properly. For endocrine studies, you need to account for half-life. Peptide hormones like insulin degrade rapidly in circulation, typically with a half-life of minutes. Steroid hormones like cortisol have half-lives measured in hours because they are lipid-soluble and bind to carrier proteins. Your experimental timing needs to match the pharmacokinetics of what you are studying. For paracrine work, the diffusion distance is your main constraint. Most paracrine signals are effective within a range of about 1 to 2 cell diameters. Beyond that, the concentration drops off according to the diffusion equation and enzymatic degradation in the extracellular matrix. If you are studying a paracrine pathway, you need to verify that your source and target cells are actually close enough for diffusion to be the delivery mechanism. Cell culture spacing matters more than most people realize. Autocrine signaling requires careful controls because every cell in your culture is both producer and responder. This creates positive feedback loops that can amplify signals exponentially. I have seen papers where researchers attributed effects to a specific autocrine pathway without knocking down the receptor or using neutralizing antibodies to confirm the self-signaling claim. Without those controls, you cannot distinguish autocrine signaling from simple cell density effects or from paracrine signaling between identical cells.
Where This Framework Falls Short
The endocrine-paracrine-autocrine classification is useful but incomplete. It does not account for juxtacrine signaling, where the signal requires direct cell-to-cell contact through membrane-bound molecules like Notch ligands. It does not handle intracrine signaling, where molecules act inside the cell that produced them without being secreted at all. It also breaks down in complex tissues where multiple signaling modes operate simultaneously and interact in non-linear ways. A single cytokine in a tumor microenvironment might be acting autocrinely on the cancer cell, paracrinely on immune cells, and even endocrinely if it enters the circulation at sufficient concentration. For clinical applications, the distinction matters less than the receptor occupancy and downstream pathway activation. Whether a growth factor reaches its receptor through endocrine or paracrine delivery is secondary to understanding whether the receptor is present, whether it is functional, and what the downstream cascade looks like. Drug development in oncology has largely shifted toward targeting specific receptors and pathways rather than trying to manipulate the signaling distance category itself. The practical takeaway is that you should understand all three modes thoroughly, but you should also be ready to move past the classification when the biology demands it. The body does not care about your categories. It just uses whatever signaling distance is most efficient for the job.


