What You Need to Know About the Endocrine System Study Guide Scf
The Endocrine System Study Guide Scf is a review resource that cycles through hormonal pathways, gland functions, and clinical correlations. It's aimed at students preparing for nursing exams or introductory biology courses. I've seen a lot of versions floating around, but most of them have the same structural problems. The one I use strips out the fluff and focuses on high-yield connections between hormone clusters and their feedback loops. Here's the practical breakdown of how to actually get value from it instead of just highlighting half the pages.
How to Use the Endocrine System Study Guide Scf Effectively
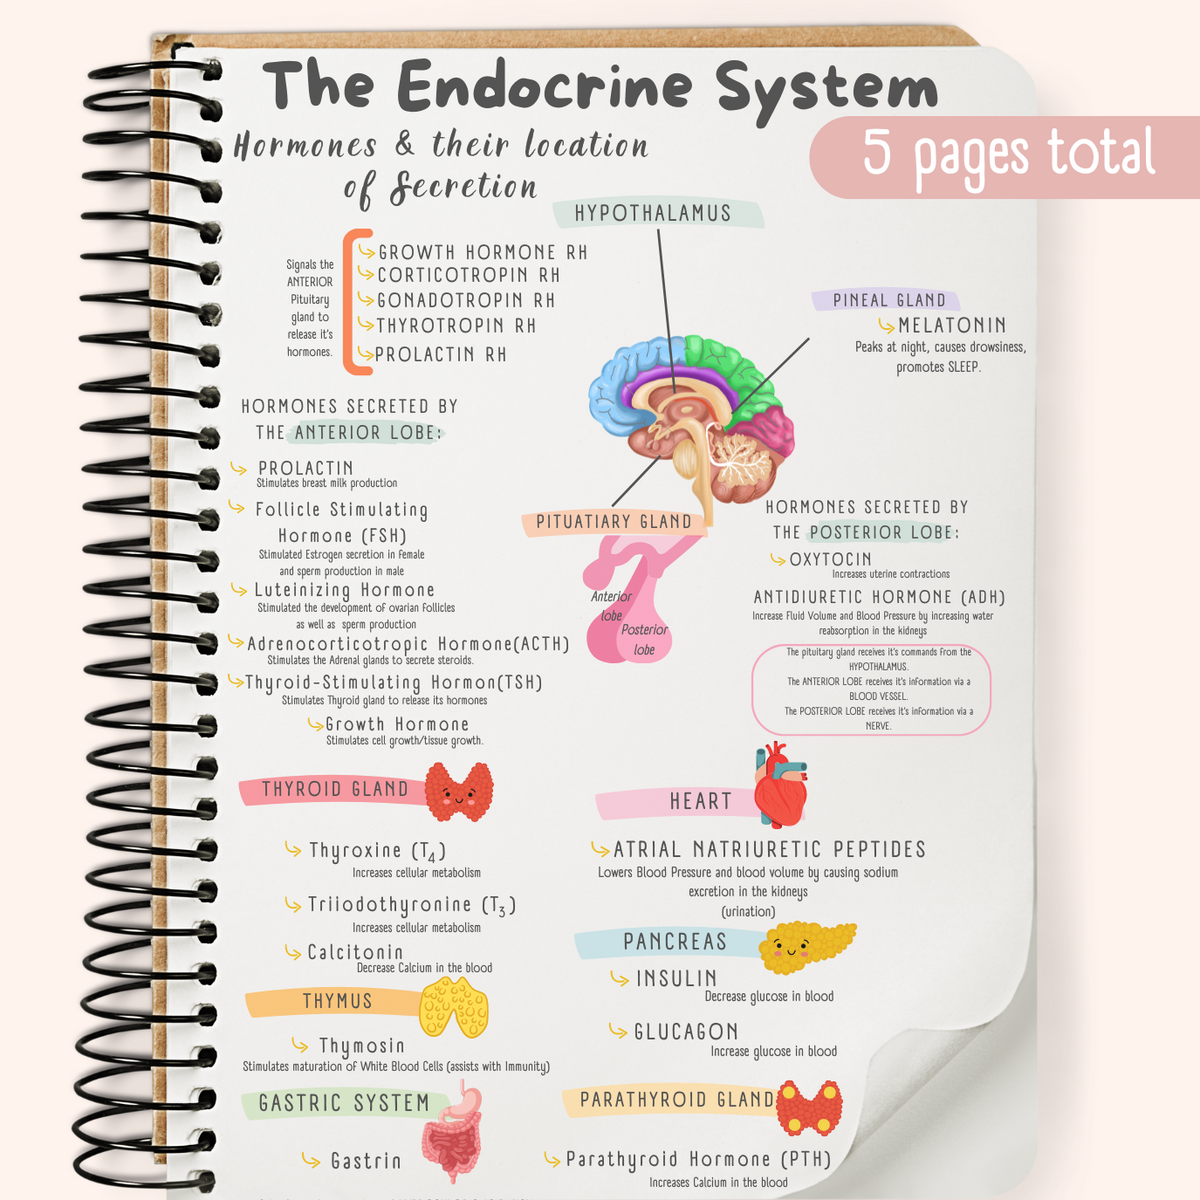
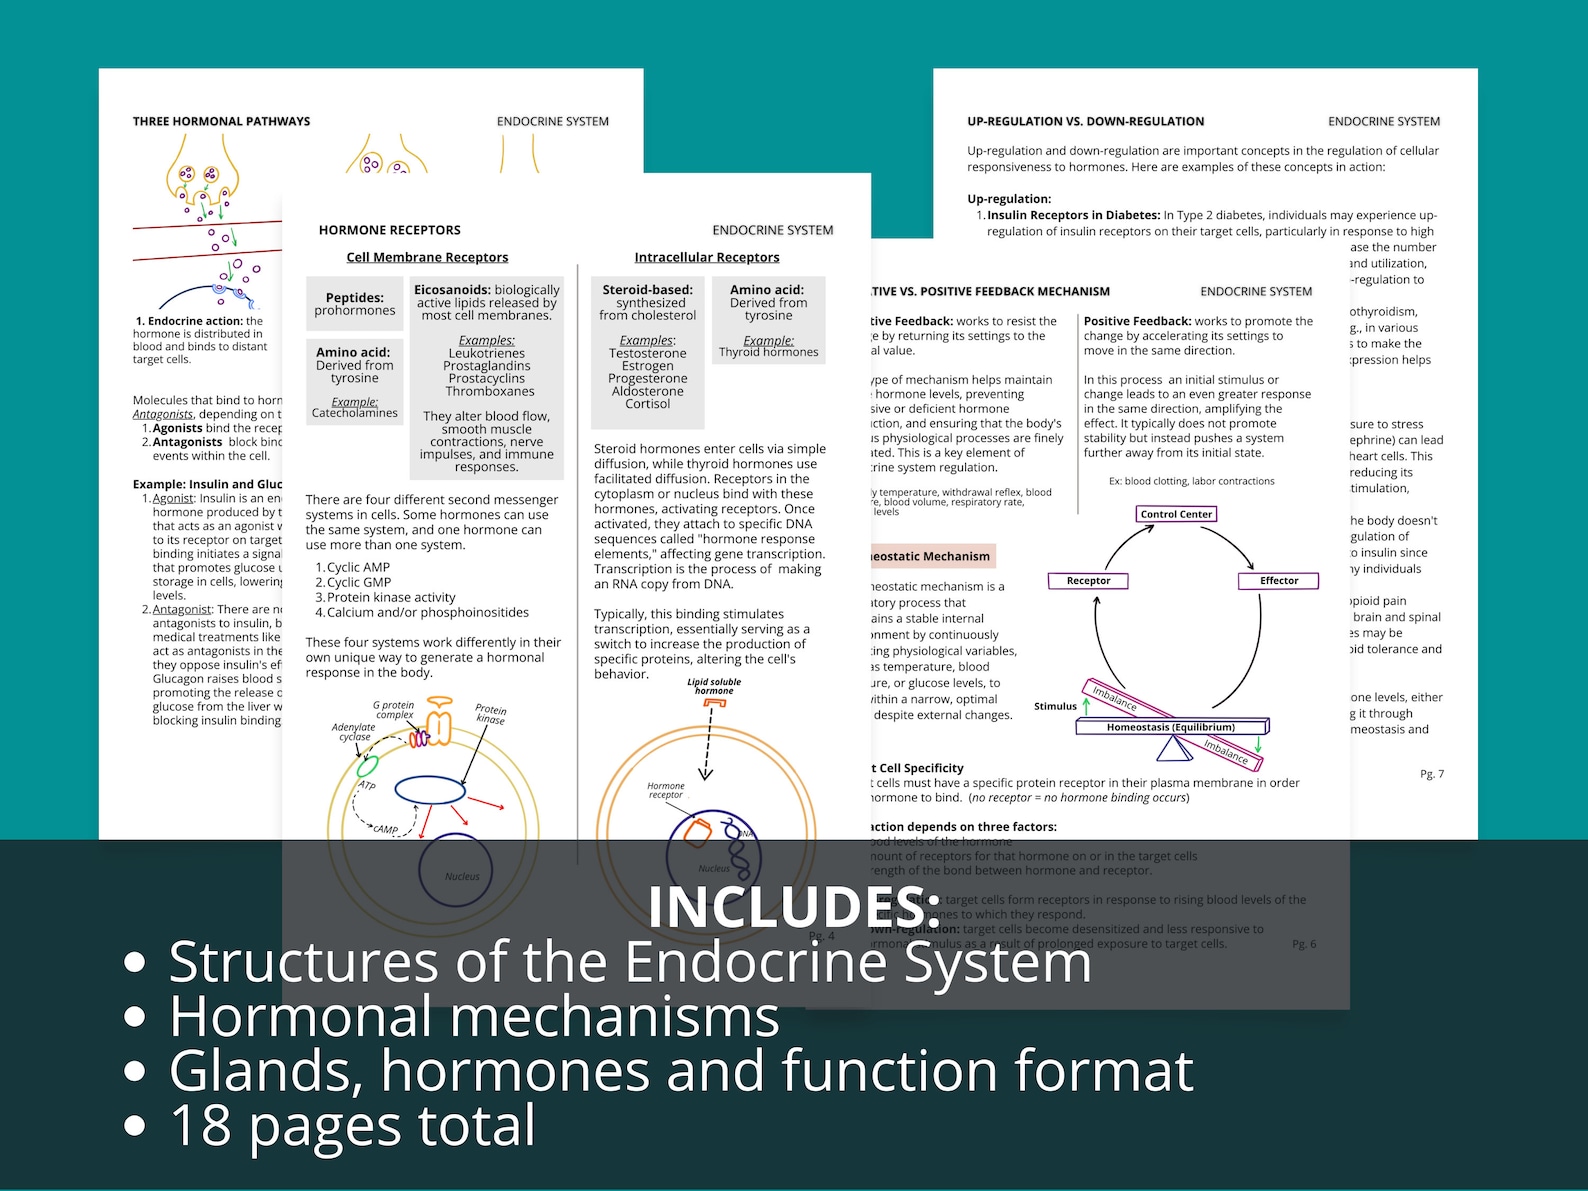
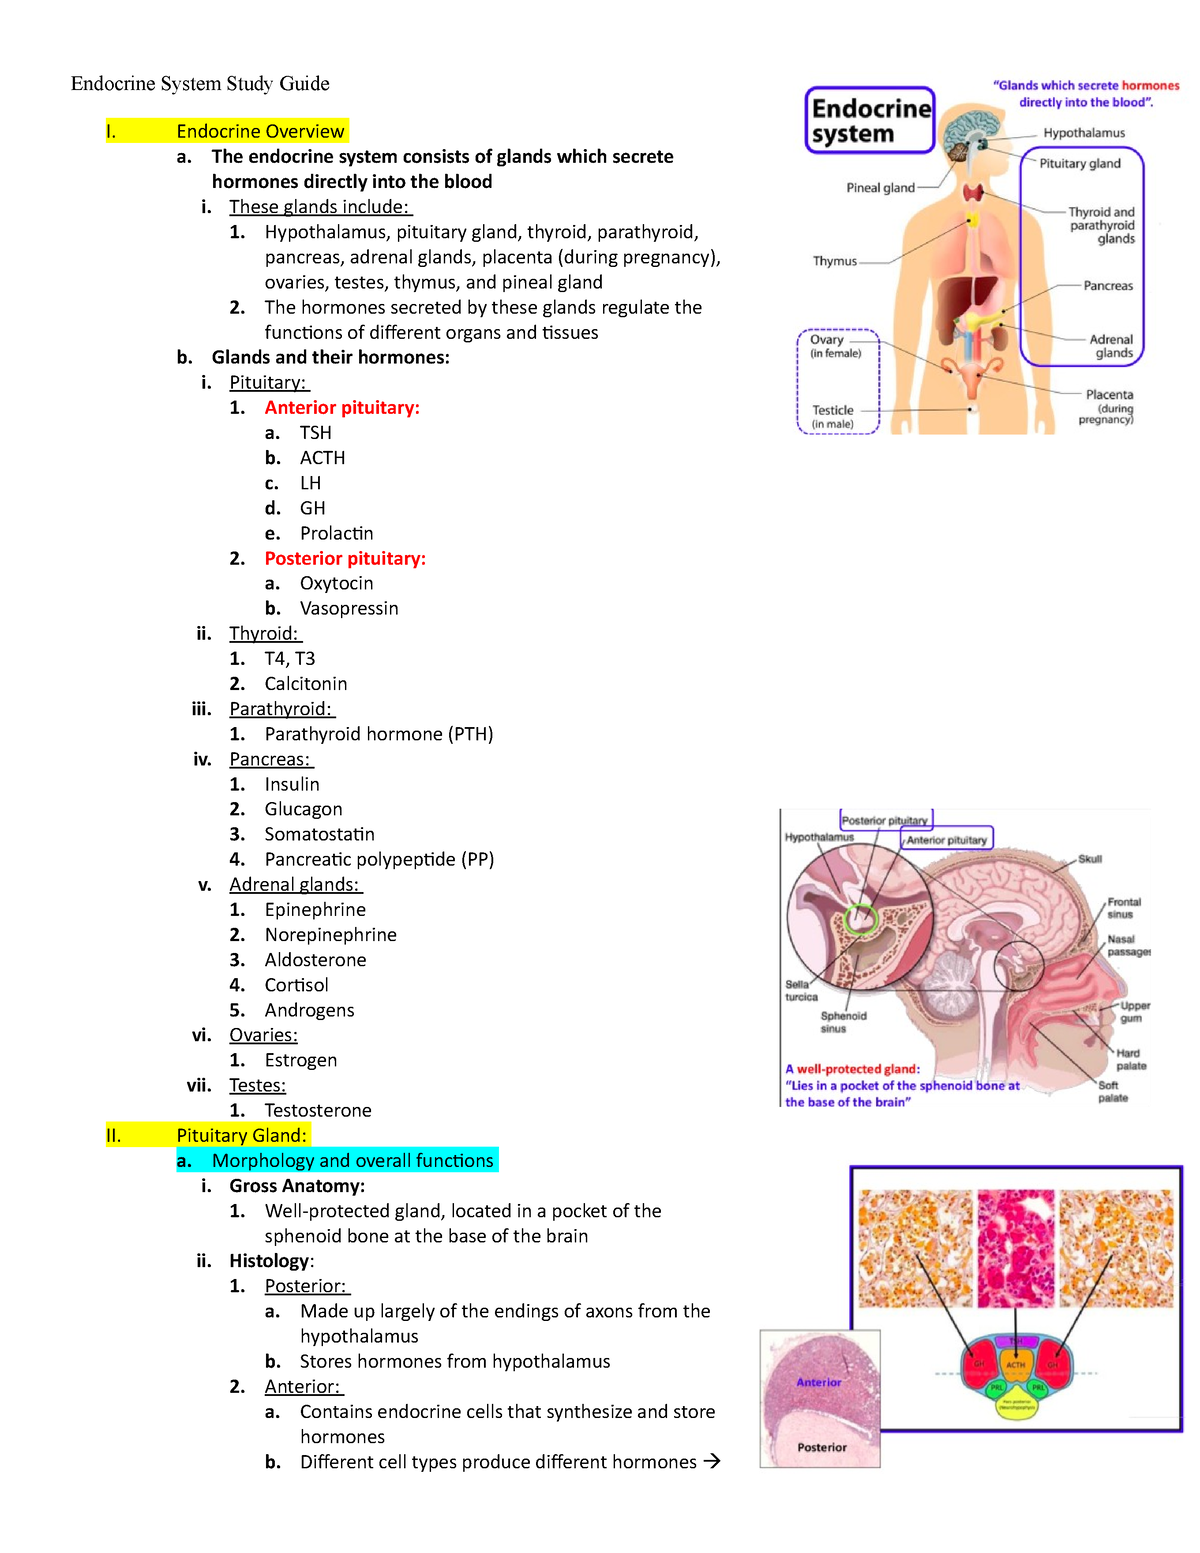
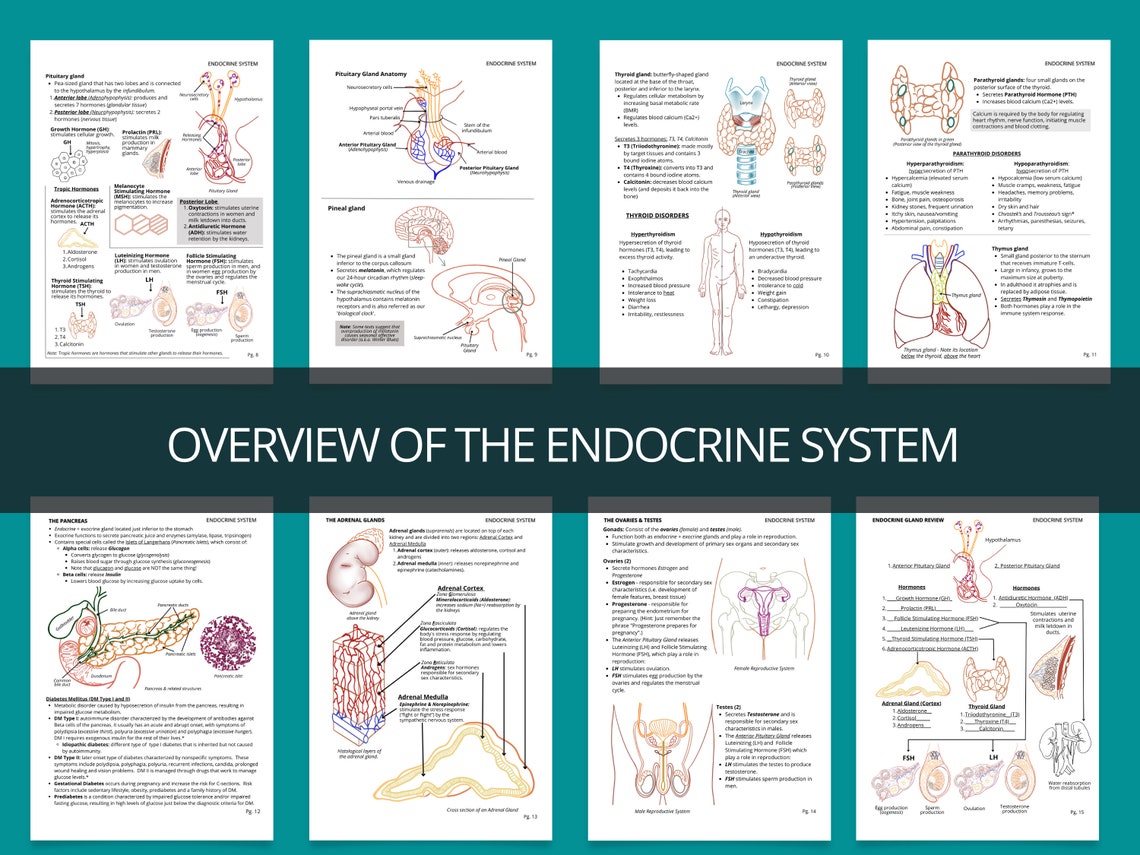
Start with the pituitary section. That's where everything branches off, and most guides bury it under thyroid content because they want to cover something flashier first. The anterior and posterior pituitary each have their own regulatory logic. Anterior pituitary hormones run through the hypothalamic-pituitary axis with releasing and inhibiting factors. Posterior pituitary hormones are made in the hypothalamus and stored down there. If you conflate those two, you'll lose points on pretty much every exam that touches this material. From there, move to the thyroid and parathyroid. The thyroid story is straightforward enough: T3 and T4 respond to TSH in a classic negative feedback loop. The parathyroid is where people get sloppy. PTH raises blood calcium by pulling it from bone, increasing renal reabsorption, and activating vitamin D for gut absorption. Calcitonin does the opposite but is clinically minor in adults. Don't overstudy calcitonin unless your exam specifically calls for it. The adrenal section is the most clinically relevant part of the guide. Cortex versus medulla matters because they produce entirely different classes of hormones. The cortex handles corticosteroids through three zones: zona glomerulosa for aldosterone, zona fasciculata for cortisol, and zona reticularis for androgens. The medulla releases catecholamines. Cushing's syndrome, Addison's disease, and pheochromocytoma all map directly onto these anatomical distinctions. If you're studying for a nursing exam, spend more time here than any other section.
Pancreatic hormones wrap up the major players. Insulin and glucagon are textbook negative feedback for blood glucose. The guide will also touch on somatostatin and pancreatic polypeptide, but those are lower yield. Diabetes management questions tend to focus on the insulin-glucagon relationship and the effects of exogenous insulin administration.
Get the Full Details
A Problem I Ran Into and How I Worked Around It
The SCF version I first used had a major gap in the renin-angiotensin-aldosterone system coverage. It mentioned aldosterone briefly in the adrenal cortex section but never connected it to renal regulation or blood pressure management. For a student trying to understand hypertensive pharmacology downstream, that's a significant blind spot. I ended up cross-referencing with a pharmacology text on RAAS inhibitors and built my own supplemental notes linking aldosterone back to kidney function. If your guide has the same omission, don't assume it's intentional. Fill it in yourself. Another issue is the pacing of the feedback loop diagrams. They present them as static illustrations rather than showing the temporal dynamics. In practice, the time delay between hypothalamic release factor secretion and anterior pituitary hormone output is what creates the oscillatory patterns you see in cortisol diurnal rhythms. The guide doesn't address this, but it shows up on case-based questions. Understanding that cortisol peaks around 8 AM and troughs near midnight changes how you interpret lab results in clinical scenarios.
Counter-Intuitive Points Beginners Miss
Most students treat hormone names as arbitrary labels. They memorize that ADH comes from the posterior pituitary and move on. What they miss is that ADH has two distinct receptor types with completely different effects. V1 receptors on vascular smooth muscle cause vasoconstriction. V2 receptors in the collecting ducts trigger aquaporin insertion and water reabsorption. Desmopressin works on V2 selectively, which is why it's used for diabetes insipidus without causing significant blood pressure changes. If you're only memorizing "ADH = water retention," you're leaving points on the table for questions about hypertensive emergencies or SIADH management. Another common gap involves the distinction between tropic and non-tropic hormones. The guide will list ACTH, TSH, FSH, and LH as tropic hormones without clearly explaining why that classification matters. It matters because tropic hormones have their own target glands, which means you're dealing with multi-level feedback loops rather than simple direct regulation. When a question describes a patient with elevated TSH and elevated T4, that's primary hyperthyroidism territory only if the labs point elsewhere. Actually, that pattern suggests secondary hyperthyroidism from a pituitary adenoma. Most students immediately default to Graves' disease without checking the TSH first. The TSH value is your first diagnostic filter, not an afterthought.
What the Guide Doesn't Cover Well
The scf endocrine system study guide material generally underweights melatonin and pineal function. It's an easy section to skim, but questions about circadian rhythm disruption, jet lag protocols, and seasonal affective disorder keep appearing on newer exam banks. Seasonal affective disorder relates directly to melatonin dysregulation, and knowing that light exposure suppresses melatonin secretion is useful clinical context. Adipose tissue hormone production is another neglected area. Leptin and adiponectin come from fat cells and influence insulin sensitivity, appetite regulation, and inflammatory responses. Metabolic syndrome questions increasingly reference these pathways. If your curriculum includes any nutrition or endocrine metabolism crossover, you'll need knowledge beyond what the guide provides. The guide also skimps on calcitonin gene-related peptide (CGRP). It's produced by thyroid C cells alongside calcitonin but has significant vasodilatory properties and plays a role in migraine pathophysiology. Triptan medications target serotonin receptors related to CGRP pathways. Again, clinical correlation questions may reach beyond the text.
Download and Access
Search for the Endocrine System Study Guide Scf on academic resource sites or instructor-shared drives. Some universities post their versions in course management systems. Make sure you're using a recent edition since endocrinology question banks have shifted toward clinical vignettes rather than pure recall over the past few years. An older version might still cover the correct hormone names but miss the applied reasoning style that newer exams demand. If you can't find a clean copy, look for course syllabi from programs that list SCF as a required resource. Professors sometimes upload study guides directly to their class pages. The version from community health nursing programs tends to be the most clinically oriented, which is useful if you're aiming for practical application rather than pure theoretical knowledge.
Time Estimate for a Solid Review Pass
Plan for roughly 3 to 4 hours if you're working through the guide methodically and taking your own supplemental notes on the gaps I mentioned. A first pass without note-taking will take about 90 minutes, but you'll retain significantly less. The pituitary-thyroid-adrenal sequence takes about 75 minutes. Pancreas and accessory glands take another 45. The remaining time goes toward practice questions and filling in the RAAS and melatonin sections from outside sources. Don't rush through the feedback loop diagrams. Each one represents a testing pattern that repeats across different question formats. Understanding the loop mechanics rather than memorizing individual hormone functions will serve you better when you encounter unfamiliar clinical scenarios on the exam.