Getting Into ENT as a Nurse Practitioner Isn't as Cut-and-Dry as You Think
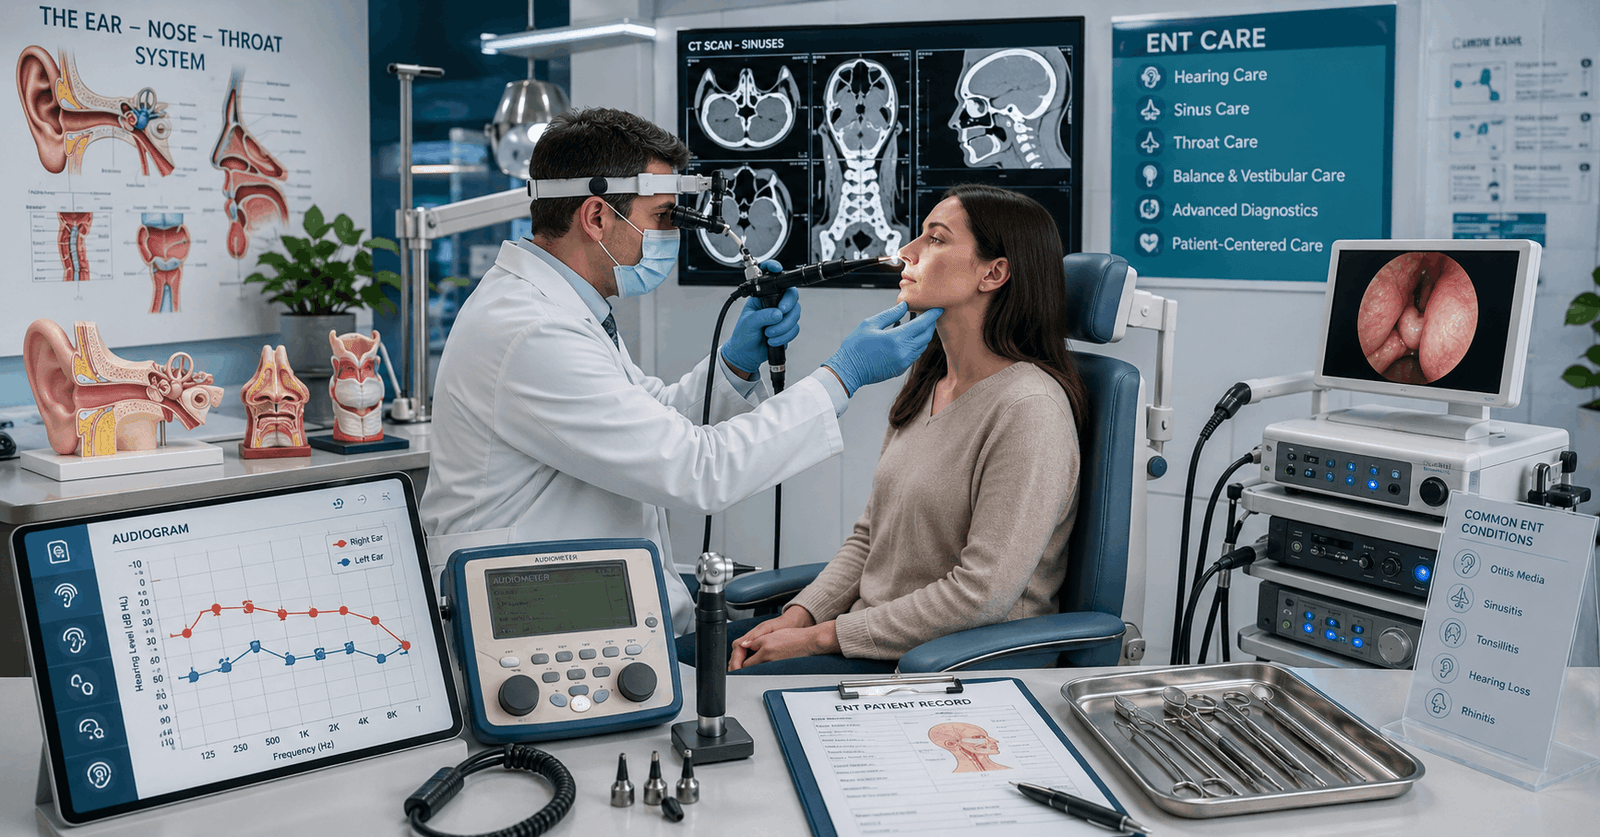
Most people come at this assuming it's just another NP specialty with slightly bigger drills. It's not. The procedural intensity is real, the anatomical density is brutal, and the credentialing landscape is a mess that will waste three months of your career if you don't plan around it. I went through an ENT NP fellowship and spent the next two years working in a hospital-based practice before moving to private practice. Here's what I actually learned, not what the brochures say. The formal pathway starts the same as every other NP track: you get your Master's or DNP with a family nurse practitioner or adult-gerontology primary care certification. There are no standalone NP certificates specifically for ENT that are accredited by ACGME or CNME. What exists are post-certification fellowships and certificate programs, usually 12 to 24 months, offered by individual hospitals or university systems. Some are more structured than others. The program I trained in had eight weeks of didactic classroom time, six months of clinic precepted hours, and then a surgical rotation where you were basically allowed to hold retractors and learn to tie knots before anything else. The core curriculum covers otology, rhinology, laryngology, head and neck surgery, pediatric ENT, and sleep medicine. You'll spend a lot of time on skull base anatomy. Not just "know it" level. I'm talking being able to identify the carotid artery course through the middle ear on a high-resolution CT scan without looking at a legend. That came up in my first month of independent practice when a patient with a glomus jugulare tumor presented with pulsatile tinnitus and we needed to distinguish tumor vascularity from venous congestion on imaging. Most NPs haven't seen a glomus tumor before their first week on the job. I had.
The procedural expectations vary wildly by state and by employer. Some programs push you toward scope time — flexible laryngoscopy, nasal endoscopy, microsuction, foreign body removal. Others treat you as a post-op management provider who occasionally does ear lavage. The ones that don't guarantee a minimum number of in-service procedures before you graduate are the ones you should avoid. I've seen NP grads from two different fellowship programs walk into the same job and have completely different competency levels because one program logged 200 scopes per resident and the other logged 60. Credentialing is the part nobody talks about. Your state NP license doesn't automatically qualify you to perform certain procedures. Facility privileging is separate. Hospital committees want to see documented case logs, proctor evaluations, and often a minimum volume threshold before they'll let you run a flexible laryngoscope in their OR or procedure suite. I had a colleague who finished her fellowship, got her job offer, and then spent four months waiting on credentialing because her program didn't have a standardized template for the competency documentation the hospital wanted. She couldn't do any scopes during that entire window. Factor in at least three months of credentialing time between accepting a job and actually practicing independently. Board certification is another confusing layer. The ANCC offers Family NP and Adult-Gerontology NP boards, but nothing ENT-specific. Some states accept ENT specialty certification through the American Board of Otolaryngology, but that's primarily for physicians. What actually matters in practice is whether your state allows you to scope and whether your malpractice carrier will cover the procedures you're attempting. One of my preceptors lost a malpractice claim over a tympanic membrane perforation during microsuction because the insurer determined the procedure fell outside her documented scope of practice, even though she'd performed it dozens of times. The case log from her fellowship wasn't thorough enough to establish competency.
Here's a specific thing that tripped me up and probably will trip you up too: the difference between medical and surgical ENT NP roles is not a minor distinction. It's a career-defining one. Medical ENT is clinics, scopes, medical management of chronic rhinosinusitis, allergy testing, hearing aid fittings, sleep apnea workups. Surgical ENT is pre-op optimization, post-op management, minor in-office procedures, and then assisting in the OR. A lot of programs blur these together and you don't realize until you're actually working which one you trained for. I entered a program thinking I'd be doing otologic surgery. My first real ear surgery experience was suturing a post-mastoidectomy incision while the attending did everything else. It took me about eighteen months to get comfortable assisting with my own cases, and even then I was only scrubbed in for tympanoplasties and mastoidectomies, not skull base work. If you're serious about this, here's what I'd do differently if I were starting over. Pick a fellowship with a published case log and minimum procedure requirements, not just a description. Ask for the actual numbers from recent graduates. Verify that the program provides structured proctoring for flexible laryngoscopy, otoscopy, and microsuction — not just observation time. Get your own set of scopes early. The rental departments at most hospitals charge per case and you'll burn through your procedural budget fast if you're renting every time. A used Karl Storz or Olympus scope runs about two to four thousand dollars and holds up for years. I bought one after month three and it saved me roughly two hundred dollars per case in rental fees over my remaining fellowship time. The job market itself is surprisingly solid in most regions. Otolaryngology practices are desperate for NP coverage because the physician workforce is aging and fellows aren't graduating in sufficient numbers. But the compensation structure is often built around RVU productivity in a specialty where procedural RVUs are lower than you'd expect. A single sinus surgery codes higher than a month of chronic rhinosinusitis visits, so if your practice is visit-heavy, your productivity numbers will look thin. I saw a colleague leave a hospital-employed position after six months because her bonus structure was based on surgeon-relative RVUs and the medical management side of her panel was mathematically impossible to make competitive.
Get the Full Details

The documentation burden is heavier than most NPs expect. ENT encounters are detail-heavy. You're charting nasal polyposis grading, tympanic membrane findings, vocal cord mobility, hearing thresholds across multiple frequencies, CT sinus scores. One bad note audit from an ENT practice I consulted for resulted in a billing flag that required manual review of forty-two encounters and cost the practice three weeks of administrative time. Learn ICD-10 coding for ENT before you start. Specifically, learn the difference between chronic sinusitis, recurrent acute sinusitis, and acute exacerbation of chronic sinusitis. Getting those codes wrong won't get you fired, but it will make your preceptors question whether you understand the clinical picture. One more thing that caught me off guard: pediatric ENT is its own world inside ENT. Adenotonsillectomy is the bread and water, but the airway cases, the laryngotracheal stenosis, the congenital neck masses — those require a completely different mental model from adult practice. My fellowship had a dedicated pediatric block, but I wish we'd had more simulation time on pediatric airway management before we touched real patients. The first time I assisted with a pediatric tracheostomy, I was green enough that I froze during the critical dissection step and the attending had to verbally walk me through what my hands should be doing. I've never forgotten that feeling and I've been very careful about setting realistic expectations since. If you want a realistic timeline, here it is: NP program plus certification takes two to three years. A fellowship takes one to two years. Credentialing takes three to four months. Full independent procedural competency in a surgical practice takes eighteen to twenty-four months after you start working. Anyone telling you otherwise is selling something.