Practical Guide to Environmental Modification Occupational Therapy
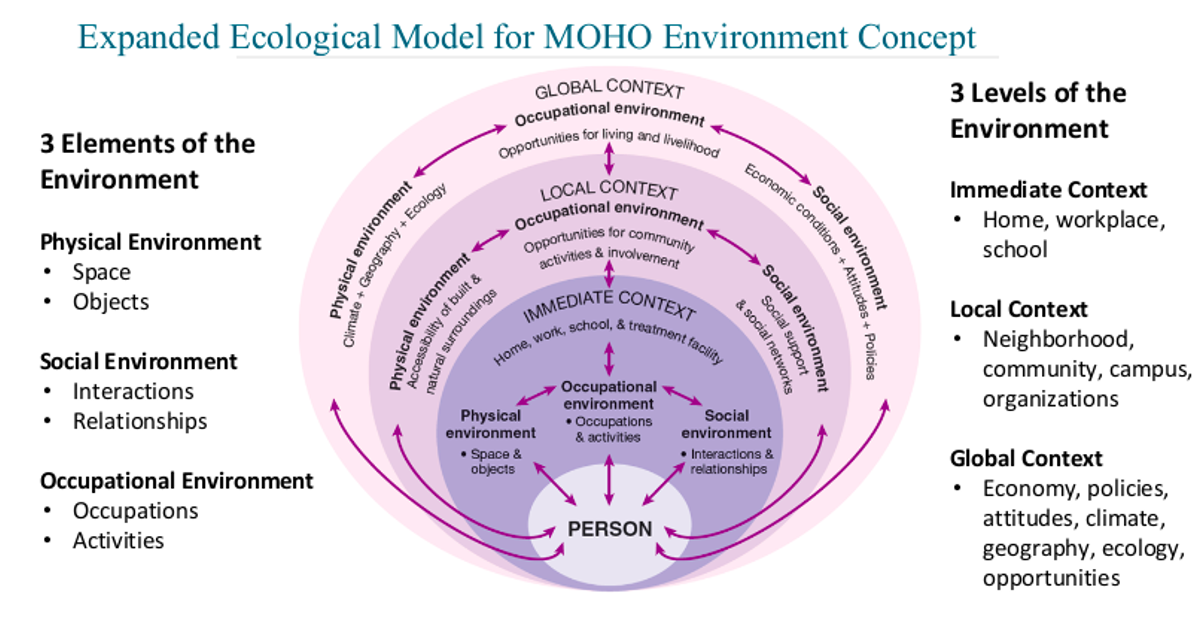
Environmental Modification Occupational Therapy is a practice where clinicians assess and alter physical spaces so people with physical, cognitive, or sensory disabilities can function more independently. This isn't about installing a grab bar and calling it a day. It involves understanding biomechanics, behavioral patterns, regulatory requirements, and the gap between what a floor plan says and what actually happens when someone navigates it with limited mobility or cognition. The process starts with a functional assessment of the actual environment, not the architectural drawings. I watch how someone moves through their space under real conditions. That means observing transfers from bed to chair, reaching overhead for medications, navigating from the bedroom to the bathroom at night with impaired vision. Most assessments take between two and four hours depending on the complexity of the space and the degree of impairment. A straightforward bedroom and bathroom retrofit might be done in an hour after the initial walkthrough, but a full home modification for someone with advanced multiple sclerosis could require a full day of observation across multiple days. The core tool in any modification assessment is the National Research Council's Person-Environment-Occupation model. You're mapping three variables simultaneously. The person has specific impairments - range of motion limits, balance deficits, visual field cuts, fatigue thresholds. The environment has measurable characteristics - doorway widths, floor friction coefficients, counter heights, lighting levels in lumens. The occupation is whatever the person actually needs to do - cooking, toileting, dressing, working. The intersection where those three overlap determines what modifications are necessary and which are just nice-to-have.
Most people doing this work for the first time make the same mistake. They assess the space before understanding the person's actual daily routine. You can have the most perfectly modified bathroom in the world and it will still fail if the person using it gets exhausted from a three-step transfer sequence before they even reach the toilet. I had a client recently who needed a shower chair and handrails installed, which we identified in the first twenty minutes. The actual problem turned out to be that the hallway to the bathroom had a section of high-pile carpet she couldn't navigate with her walker. She was spending forty-five minutes just getting to the bathroom, which meant she was dehydration-avoiding and holding urine because the effort was too high. The modification wasn't in the bathroom at all. It was a fifteen-minute floor replacement job in the hallway that took precedence over everything else.
Assessment Methods and Tools
The primary instrument is the Home Environment Assessment Protocol (HEAP), adapted from the Hospital of St. John and St. Elizabeth's versions. It rates the home on a standardized scale across seven domains: accessibility, safety, comfort, privacy, social interaction, support services, and finances. Each domain gets scored from zero to four. A total score below eight indicates a home environment that is significantly restricting independent function and requires systematic modification. Another critical tool is the Physical Environment Assessment Scale (PEAS), which quantifies environmental barriers using objective measurements rather than subjective observation. Doorway clearance in centimeters, step heights, floor surface type, lighting measurements at task areas, water temperature at fixtures. These numbers matter because they remove the guesswork from recommendations. When you tell a contractor that a doorway needs to be thirty-six inches minimum, that's a code requirement. When you say it needs to be wider, the contractor will ask how much wider and you need to have an answer that's based on measurement, not opinion. I use a modified version of the Kates Instrumental Activities of Daily Living (IADL) scale to track whether environmental changes are actually improving function. The standard IADL scale measures things like shopping, cooking, housekeeping, managing medications, using transportation. The modification angle requires tracking the same activities but specifically noting whether environmental barriers or enablers are the determining factor in success or failure. If a person can cook when the stove knobs are replaced with lever handles but cannot cook with the original knobs, that is a direct environmental modification outcome measure. You're proving causation, not correlation.
Get the Full Details

Common Modifications and When They Apply
Grab bars are the most commonly prescribed modification and the most frequently installed incorrectly. A grab bar placed at the wrong height or anchored into drywall without proper blocking is worse than useless. It gives a false sense of security and can actually increase fall risk if it fails under load. Grab bars for transfer support must be anchored into wall studs or using certified behind-the-wall anchor systems that can sustain at least two hundred fifty pounds of force. The bar should be positioned at the point of maximum load during the transfer, which varies by person. I measure this by having the person perform their actual transfer while I note where their hand lands naturally. Then I measure the vertical distance from the floor to that hand position and install the bar at that height minus two inches to account for the downward gripping motion. Ramps are another area where installation errors are common. The maximum recommended slope for a residential ramp is one inch of rise per twelve inches of run. That is a federal requirement under the Fair Housing Act for accessible design. Anything steeper creates a tipping hazard for wheelchair users and a strain hazard for walkers. A ten-inch step requires a ramp that is at least ten feet long. Most people try to fit a six-foot ramp and call it acceptable. It is not acceptable. The landing at the top and bottom of every ramp must be at least five feet by five feet. This is where people get tripped up in tight entryways where a full landing is physically impossible. In those cases, you modify the approach instead - lowering the threshold, reconfiguring the door swing, or creating a level platform before the ramp begins. Lighting modifications are the most overlooked category. Many home modification programs focus exclusively on mobility and completely ignore the visual environment. For someone with macular degeneration, a poorly lit kitchen is as disabling as a locked door. Task lighting at cooking surfaces should be at least five hundred lux. General ambient lighting should be three hundred lux minimum in areas where navigation occurs. Motion-activated lights in hallways and bathrooms reduce the friction of nighttime transfers for people with balance issues because they eliminate the step of finding a light switch. I once evaluated a home where the occupant had fallen twelve times in three months. All the falls happened in the hallway between the bedroom and bathroom at night. The fix was two battery-operated LED strip lights under the baseboards, installed for about eighteen dollars total. The falls stopped completely after the first week.
Documentation and Justification
If you are writing prescriptions for environmental modifications, you need documentation that will survive insurance review and contractor interpretation. The evaluation report must include: specific functional limitations identified, the environmental barriers directly related to those limitations, the proposed modification with exact specifications, the expected functional improvement from each modification, and the clinical rationale linking the barrier to the proposed solution. Insurance companies routinely deny claims because the justification is vague. A note saying "grab bar needed for safety" will be rejected. A note saying "patient demonstrates inability to safely transfer from wheelchair to toilet without bilateral upper extremity support due to bilateral shoulder rotator cuff pathology with ninety-degree range of motion limitation, and no stable surface exists within arm's reach of the toilet seat" will be approved. The difference is not semantics. The difference is whether the payer can map the diagnosis to the intervention using their medical necessity criteria.
Where This Approach Breaks Down
Environmental modification has hard limits that clinicians sometimes forget. You cannot modify a space that does not exist. Renters with landlord restrictions face structural barriers that no amount of clinical expertise can overcome. A tenant cannot install a ramp in a common stairwell without written permission, and most landlords will not grant that. In those cases, the modification shifts from permanent environmental change to temporary compensatory strategy - using a portable shower chair, rearranging furniture to create a single-floor living space, negotiating with the landlord for specific accommodations under the Fair Housing Act. Budget is another hard limit. A complete kitchen modification with lowered counters, pull-out shelving, and modified appliances can run between four thousand and twelve thousand dollars depending on the scope. Most people are not going to access that through insurance unless the modification is deemed medically necessary for a recent injury or acute disability onset. Pre-existing conditions often fall into a gray area where insurance denies coverage and out-of-pocket costs are prohibitive. In those situations, prioritization becomes the clinical skill. I help clients rank modifications by impact-to-cost ratio. A shower chair and grab bar combination costs under two hundred dollars and can restore independent bathing. A walk-in tub conversion costs eight to fifteen thousand and achieves a similar outcome through a different mechanism. The choice depends entirely on the person's funding situation, living situation, and severity of mobility impairment. There is also a cognitive dimension that most modification protocols handle inadequately. Environmental modification for dementia patients requires a different framework than for physical disability. The concerns shift from mobility and transfer to wayfinding, safety monitoring, and reducing confusion triggers. Simple modifications like contrasting tape on step edges, color-coded doors, and reduced visual clutter at decision points can have significant functional impact. But these interventions are not well-standardized. There is less research and fewer established protocols. Clinicians working in this space often have to piece together evidence from multiple domains - gerontology, neuropsychology, environmental design - and adapt guidelines that were never meant to be combined.