What Actually Works When You're Trying to Eat With EoE
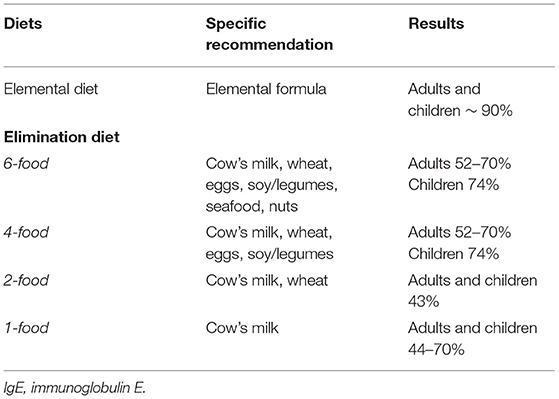
I spent about two years figuring this out the hard way, mostly because nobody sitting in my gastroenterologist's office seemed to have more than a printed pamphlet and a shrug to offer. Eosinophilic Esophagitis Nutrition Therapy isn't a single diet. It's a toolkit, and knowing which tool to reach for in any given situation is what separates people who manage their symptoms from people who end up back in the endoscopy chair every six months. The six-food elimination diet (SFED) is the standard first-line intervention most guidelines will push on you. You remove dairy, wheat, egg, soy, nuts, and shellfish cold turkey. It gives you the highest remission rates in the literature, somewhere around 70 to 80 percent when followed strictly. The catch is that it's brutally restrictive and practically impossible to sustain without a lot of structure. Most patients bounce back off it within a few months because they forget what they can actually eat. You'll find yourself at a restaurant reading ingredient labels on bread and panicking because everything has flour in it.
Eosinophilic Esophagitis Nutrition Therapy
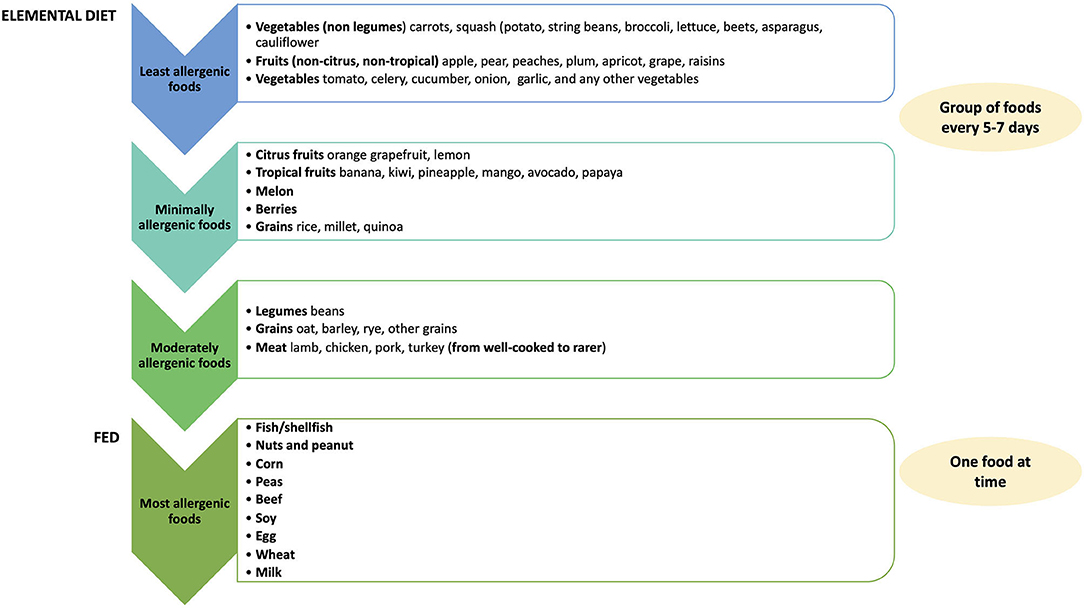
Within the broader framework of nutrition therapy for EoE, the SFED is just the beginning. Once you're in remission on the elimination diet, you do an oral food challenge. You reintroduce one food at a time, usually every two weeks, and watch for the return of symptoms or a positive repeat endoscopy. That tells you exactly what your personal trigger list looks like. Two weeks is the standard window, but I found that stretching it to three weeks gave me a clearer signal. A lot of people bounce back at the two-week mark and assume they're still reacting, when the inflammation was already there from the previous challenge. The one-food elimination diet is the other major option. That's the steroid approach where you take a swallowed flare of PPI or topical steroid like budesonide or fluticasone and then systematically eliminate foods based on response. The PPI-responsive eosinophilic esophagitis subtype is real, and a meaningful portion of patients respond to acid suppression alone. But if you're not one of those people, or if you relapse when you taper off, you're still on the elimination diet track.
The Empirical Elimination Diet Without the Six-Food Wipeout
Sometimes the SFED is overkill, especially if your endoscopy and biopsy results point toward a smaller group of offenders. The empiric elimination diet lets you start with just dairy and wheat, which are the two most commonly implicated triggers across the studies. If you clear those and stay in remission, great. If you flare, you add eggs or soy to the hit list. It's slower than the six-food protocol, maybe four to six months to full remission instead of eight to twelve weeks, but the long-term compliance is better because you're eating more normal food while you work through it. I ran into a specific problem with the elimination diet that nobody warned me about: cross-contamination in shared kitchens and food packaging. I was meticulously avoiding dairy, thinking I was safe, until I realized that many brands of oats and rice cakes are processed on the same equipment as wheat products. The label won't say it in bold letters. I ended up flaring for no reason I could explain and had to go back to square one. The workaround was calling manufacturers directly and asking about shared production lines. Some companies will give you a straight answer. Others won't, in which case you either avoid the brand or accept the risk.
Get the Full Details

Elemental Diet as a Last Resort
The elemental formula diet is about as far from normal eating as you can get. You drink a commercially prepared amino acid-based formula for four to six weeks and nothing else. Remission rates hit close to 90 percent because you're eliminating every single food antigen by definition. It's not practical long-term. People tolerate it poorly, lose weight, and develop eating disorders around food in some cases. I know a handful of patients who used it as a bridge therapy to get inflammation under control before transitioning to a step-down elimination diet. That's where it makes sense. It's not a standalone solution for most adults, and pediatric patients sometimes need a feeding tube to make it work because they simply can't consume enough volume to meet their calories. Getting into remission is the easy part. Staying there is where the failure rate sits. The reintroduction phase determines whether you actually know what you're dealing with or whether you're just guessing. Every single patient I've talked to who stuck with a structured reintroduction plan ended up with a much shorter list of restricted foods compared to the initial elimination diet. That's the goal, really. You don't want to be on the six-food elimination diet forever. You want to find your personal triggers and eliminate only those. Here's a counter-intuitive thing that isn't widely discussed: some patients report symptom improvement when they introduce fiber-rich foods like cooked vegetables and whole grains during the maintenance phase, even if those foods were eliminated early on. The theory is that a diverse gut microbiome can modulate the local immune response in the esophagus. It's not proven, but the anecdotal signal is strong enough that it's worth considering if your biopsies are clear and you're having residual dysphagia without visible inflammation. I tried adding roasted carrots and well-cooked quinoa back into my diet once I'd confirmed remission through repeat endoscopy, and my swallowing felt noticeably easier even though the foods themselves shouldn't theoretically help. Your mileage will vary, and I'm not suggesting you do this before your doctor confirms remission, but it's something I wish someone had mentioned to me.
Practical Day-to-Day Management
Food texture matters a lot more than most sources acknowledge. Chewed into a fine paste, many trigger foods pass without issue even when the formal allergy test says they should cause problems. This isn't a recommendation to change your eating habits entirely, but it's a real phenomenon. I've seen patients eat a small amount of yogurt and feel fine as long as they don't swallow it whole, which doesn't surprise anyone who's dealt with an inflamed esophagus. The mechanics of swallowing change when the tissue is thickened and less compliant. Portion size and meal frequency are equally important. Large meals increase the transit time and the mechanical stress on the esophageal wall. I switched to five small meals a day and my dysphagia dropped significantly, even before I identified any specific food triggers through the elimination protocol. You're not treating the allergy here. You're reducing the physical trauma to an already compromised organ.
Supplements You Should Actually Consider
When you're eating this restricted, you fall behind on certain nutrients fast. Vitamin D deficiency is extremely common in EoE patients, and low levels have been linked to worse inflammatory activity in several studies. I got my level checked after six months on the elimination diet and it was borderline low. I started supplementing and haven't looked back. Calcium and vitamin K2 are also worth monitoring since dairy is such a frequent trigger and a major dietary source of calcium for most people. If you cut dairy and don't replace it, your bone density will suffer within a year if you're not careful about it. Probiotics don't have strong evidence for EoE specifically, but the emerging data around the gut-esophagus axis makes them worth a conversation with your doctor. I tried a multi-strain probiotic for three months during the maintenance phase and didn't notice anything significant either way. That doesn't mean they won't help someone else, but I'm not going to oversell the connection.

What Doesn't Work and What You Should Avoid
Alternative elimination diets found on social media are not evidence-based. I've seen protocols that eliminate only gluten, or only nightshades, or some combination that sounds clever but has zero peer-reviewed support behind it. Those approaches tend to create more confusion than clarity. You're restricting foods without knowing whether they're actually causing your symptoms, and you're missing the ones that are. TheSFED and the two-food elimination diet are the only protocols with published remission data. Everything else is speculation dressed up as strategy. Also, do not attempt an elimination diet without endoscopic confirmation of your baseline status. I've watched people go on restrictive diets because of vague symptoms like occasional heartburn or mild difficulty swallowing, only to find later that they didn't have EoE in the first place. That's a lot of unnecessary dietary restriction for nothing. Your gastroenterologist should order biopsies before you commit to any elimination protocol. It takes ten minutes to order and the results save you months of guesswork.
When Nutrition Therapy Isn't Enough
Surgery and dilation are not nutrition therapy, but they exist in the same treatment ecosystem and you need to know when nutrition therapy is failing. If you've been on a proper elimination diet for three months and you're still having weekly dysphagia episodes, or if your follow-up endoscopy shows persistent eosinophilia above fifteen per high-power field, the nutrition approach needs adjustment. That might mean switching from a two-food to a six-food elimination, adding or adjusting medication, or evaluating for esophageal strictures that need mechanical dilation. Food alone won't fix a stricture. Some patients with ringed esophagus or concentric narrowing respond dramatically to dietary modification because the ring is inflammatory rather than fibrotic. Others have a fixed fibrotic ring that won't budge regardless of how perfectly they eat. You won't know which one you have until you get scoped. I learned that the hard way when I spent four months obsessing over my diet while my underlying stricture went untreated. The nutrition therapy was doing its job, but the mechanical problem required a different intervention entirely.
Tracking What You Eat
A food and symptom diary is the single most useful tool in this process, and most people abandon it within two weeks because they think it's pointless. Keep it for at least six weeks minimum. Write down everything you eat, the approximate portion, and any symptoms that follow within the next twelve hours. I used a simple notebook and just wrote the food in shorthand. It took me about thirty seconds per entry. When you're doing the reintroduction phase, the diary becomes the only objective record you have. Your memory of what you ate three weeks ago is unreliable, and if you flare, you'll need to know whether you recently reintroduced eggs or if something completely unrelated happened. I also logged my swallowing difficulty on a simple one to ten scale each morning before eating anything. This gave me a consistent baseline that wasn't influenced by what I'd just eaten. A lot of patients only track right after meals, which means a bad lunch skews their perception of the day. The fasting morning rating is more reflective of your actual esophageal status.
Working With a Dietitian Who Actually Knows EoE
Most registered dietitians have never encountered EoE in their training. If your provider doesn't know what an eosinophil is, you need a different provider. A proper EoE-literate dietitian can help you design a reintroduction schedule that matches your calendar, plan safe restaurant meals, and catch nutritional gaps before they become problems. I found mine through a patient advocacy group rather than my gastroenterologist's referral list, and the difference in the quality of advice was immediately apparent. The referral list dietitian wanted me to eliminate gluten and dairy and call it a day. The specialist I found through the advocacy group had me on a structured reintroduction plan within the first appointment and spent twenty minutes explaining the difference between a true IgE-mediated allergy and the non-IgE pathophysiology of EoE. That context matters because it changes how you approach food challenges.