What Epidemiology 101 Actually Covers and How to Get Through It
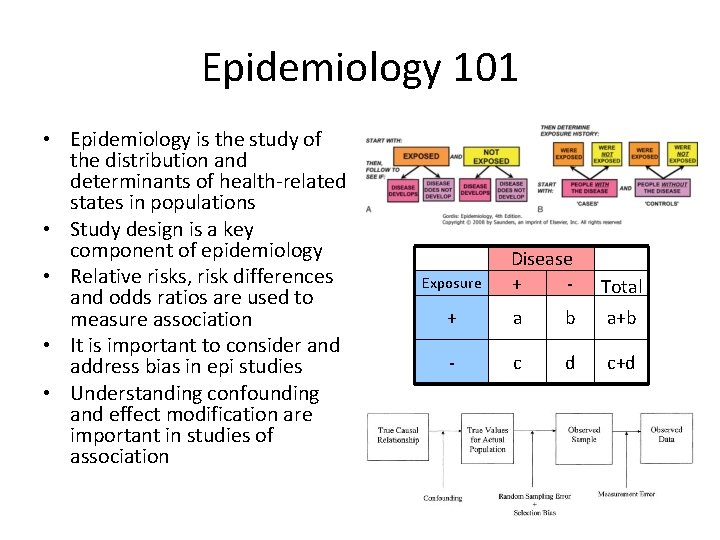
Epidemiology 101 is typically the introductory college-level course that introduces students to the foundational principles of disease distribution, determinants, and control within populations. The curriculum covers study designs like cohort and case-control studies, measures of disease frequency including incidence and prevalence, confounding and bias, and basic infectious disease dynamics. It is not a statistics course, though it borrows heavily from biostatistics. The math is manageable at this level, but the conceptual shift from individual patient care to population-level thinking trips up a lot of students. JBLearning is an educational platform that hosts a variety of college-level courses, and the Epidemiology 101 course on that platform follows a self-paced, online structure. You work through modules, complete readings, and take quizzes or assignments as you go. The content itself is standard for an intro epidemiology class — the delivery method is what makes it different from sitting in a lecture hall.
Epidemiology 101 Jblearning Com: Navigating the Platform
When you log into the JBLearning portal for this course, you will see a module-based layout. Each module contains learning objectives, required readings, lecture materials, and assessment items. The pacing is entirely up to you, which sounds liberating until you realize that no one is checking in on your progress. I have seen students complete three modules in a single weekend and then stall out for two weeks because the structure collapses without external accountability. The most practical thing you can do is treat it like a traditional semester course. Set a schedule. Log in at the same time each week. Complete one module per sitting if possible. The material builds sequentially, and skipping around will create gaps in your understanding that compound over time. One specific issue I encountered while working with this platform involved the quiz timing settings. The course instructor had configured quizzes with a strict time limit and a single attempt only. A student in my cohort missed a quiz by roughly twelve minutes due to a browser timeout issue on their end. Because there was only one attempt allowed and no backup window, that missing score dropped their overall grade significantly. The workaround was straightforward but only because the instructor was responsive: they provided an alternative assignment that carried the same weight. If your instructor does not offer flexibility on timing issues, document everything — browser errors, submission timestamps, communication logs — and escalate through the proper academic channels. JBLearning does have a help desk, but their support for course-specific grading disputes is limited.
The readings are generally the primary source of new information. Textbook chapters on study design, confounding, and disease measurement carry the most weight. Lecture videos, where available, tend to reiterate rather than add depth. Spend your time on the readings and use the videos as a secondary review tool, not a substitute.
Get the Full Details

Core Concepts That Matter Most
Several topics in this course require genuine comprehension rather than memorization. The distinction between incidence and prevalence is the first major hurdle. Incidence measures new cases over a specific time period. Prevalence measures all existing cases at a given point in time. Confusing these two leads to incorrect interpretations of public health data, and you will see this mistake repeated in news articles and policy briefs long after the course ends. Study design is the second critical area. You need to understand when to use a cross-sectional study versus a prospective cohort versus a case-control study. Cross-sectional studies capture a snapshot — they are useful for estimating prevalence but cannot establish temporality. Cohort studies follow a group over time and can demonstrate that exposure preceded disease. Case-control studies look backward from disease status to prior exposure and are efficient for rare diseases but vulnerable to recall bias. A counter-intuitive point that beginners consistently miss: case-control studies are not inherently less valid than cohort studies. They answer a different question more efficiently. The problem arises when students try to calculate incidence rates from case-control data, which is mathematically impossible without additional information about the source population. Odds ratios are the correct measure here, and understanding why requires grasping the underlying sampling frame, not just plugging numbers into a formula.
Confounding is another concept that students approach incorrectly. They learn the mechanical definition — a third variable associated with both the exposure and the outcome — but they struggle to identify it in practice. The real skill is recognizing confounding when you see a crude association that changes substantially after adjustment. If the adjusted measure differs meaningfully from the unadjusted measure, confounding is likely present. The size of that change matters more than the direction. Bias is broader and messier. Selection bias occurs when the relationship between exposure and outcome differs between those who participate in a study and those who do not. Information bias arises from systematic errors in how data are collected. Both are harder to detect than confounding because they do not always produce a clean numerical shift. A selection bias can actually push an estimate in either direction, which makes it more dangerous than students realize.
Practical Workflows for Success
Work through the calculations by hand before relying on any software or online calculator. The standard formulas for relative risk, odds ratio, attributable risk, and population attributable fraction follow straightforward patterns, but the setup matters. Identifying which cell of a 2x2 table corresponds to a, b, c, or d determines whether your final answer is correct or meaningless. I used to do this quickly on paper, then verify with a calculator. The paper step alone cut my calculation errors from roughly one in five attempts down to one in twenty. Draw the 2x2 tables every time. Do not skip this step even when the problem seems simple. A neatly organized table prevents substitution errors and makes it easier to catch when a question is asking for something different than what you initially assumed. Students lose points more often from misreading the question than from not knowing the formula. For the epidemiologic methods modules, focus on understanding the strengths and limitations of each study design rather than trying to memorize every possible variation. The exams tend to present a scenario and ask you to identify the study design, the appropriate measure of association, and potential sources of bias. This requires applied knowledge, not regurgitation.

One practical tip that applies across the board: practice interpreting results in context. A relative risk of 2.5 is not automatically important. A relative risk of 1.1 might be if the disease is common and the exposure is modifiable. Context determines whether a statistical finding translates into a public health action. The course will test your ability to make this distinction, and it is also the distinction that separates competent public health practice from amateur interpretation of research findings. Assignment deadlines are usually clearly posted, but self-paced courses can blur the line between "due" and "whenever." If the course has weekly milestones, treat them as hard deadlines. If it does not, create your own schedule and stick to it. The material is not difficult, but it is cumulative, and falling behind creates a compounding problem that is harder to solve the further you go.
Limitations and Realistic Expectations
The JBLearning format has a structural weakness: minimal live interaction. Discussion boards exist, but they are often underutilized. Office hours, if offered, are typically asynchronous or limited in availability. This means you are largely responsible for clarifying confusion on your own. If you encounter a concept that does not click after the second attempt at the reading, seek out supplementary resources rather than waiting for an instructor response. The course itself is designed as an introduction, which means it covers breadth over depth. You will not gain advanced competency in biostatistical methods or complex causal inference frameworks from this course alone. It provides the foundation. Building on that foundation requires additional coursework or independent study, particularly if you plan to work in public health research or epidemiology practice. Some students find the quiz format frustrating because questions can be phrased ambiguously. The answer choices sometimes include multiple plausible options, and the test writer's intent is not always transparent. In these situations, eliminate the clearly wrong answers first, then choose the option that best aligns with the epidemiologic principles emphasized in the readings. Overthinking a question usually leads to a wrong answer. Underthinking it does too. A deliberate, principle-based approach is the most reliable middle ground.
If you are using this course as a prerequisite for more advanced study, pay particular attention to the study design and bias modules. Those topics carry the most weight in subsequent courses and in professional practice. The calculation-heavy modules are important but more procedural in nature, and procedural knowledge tends to be easier to recover if you need to revisit it later. The course materials and grading policies are subject to change depending on the instructor and term. What applies to one section may not apply to another. Always confirm current requirements through the syllabus and course announcements rather than relying on general descriptions or past experience with similar courses. The platform itself is stable, but the course content within it is not static.