How Epigenetic Therapy For Cancer Actually Works in Practice
What Epigenetic Therapy For Cancer Means Clinically
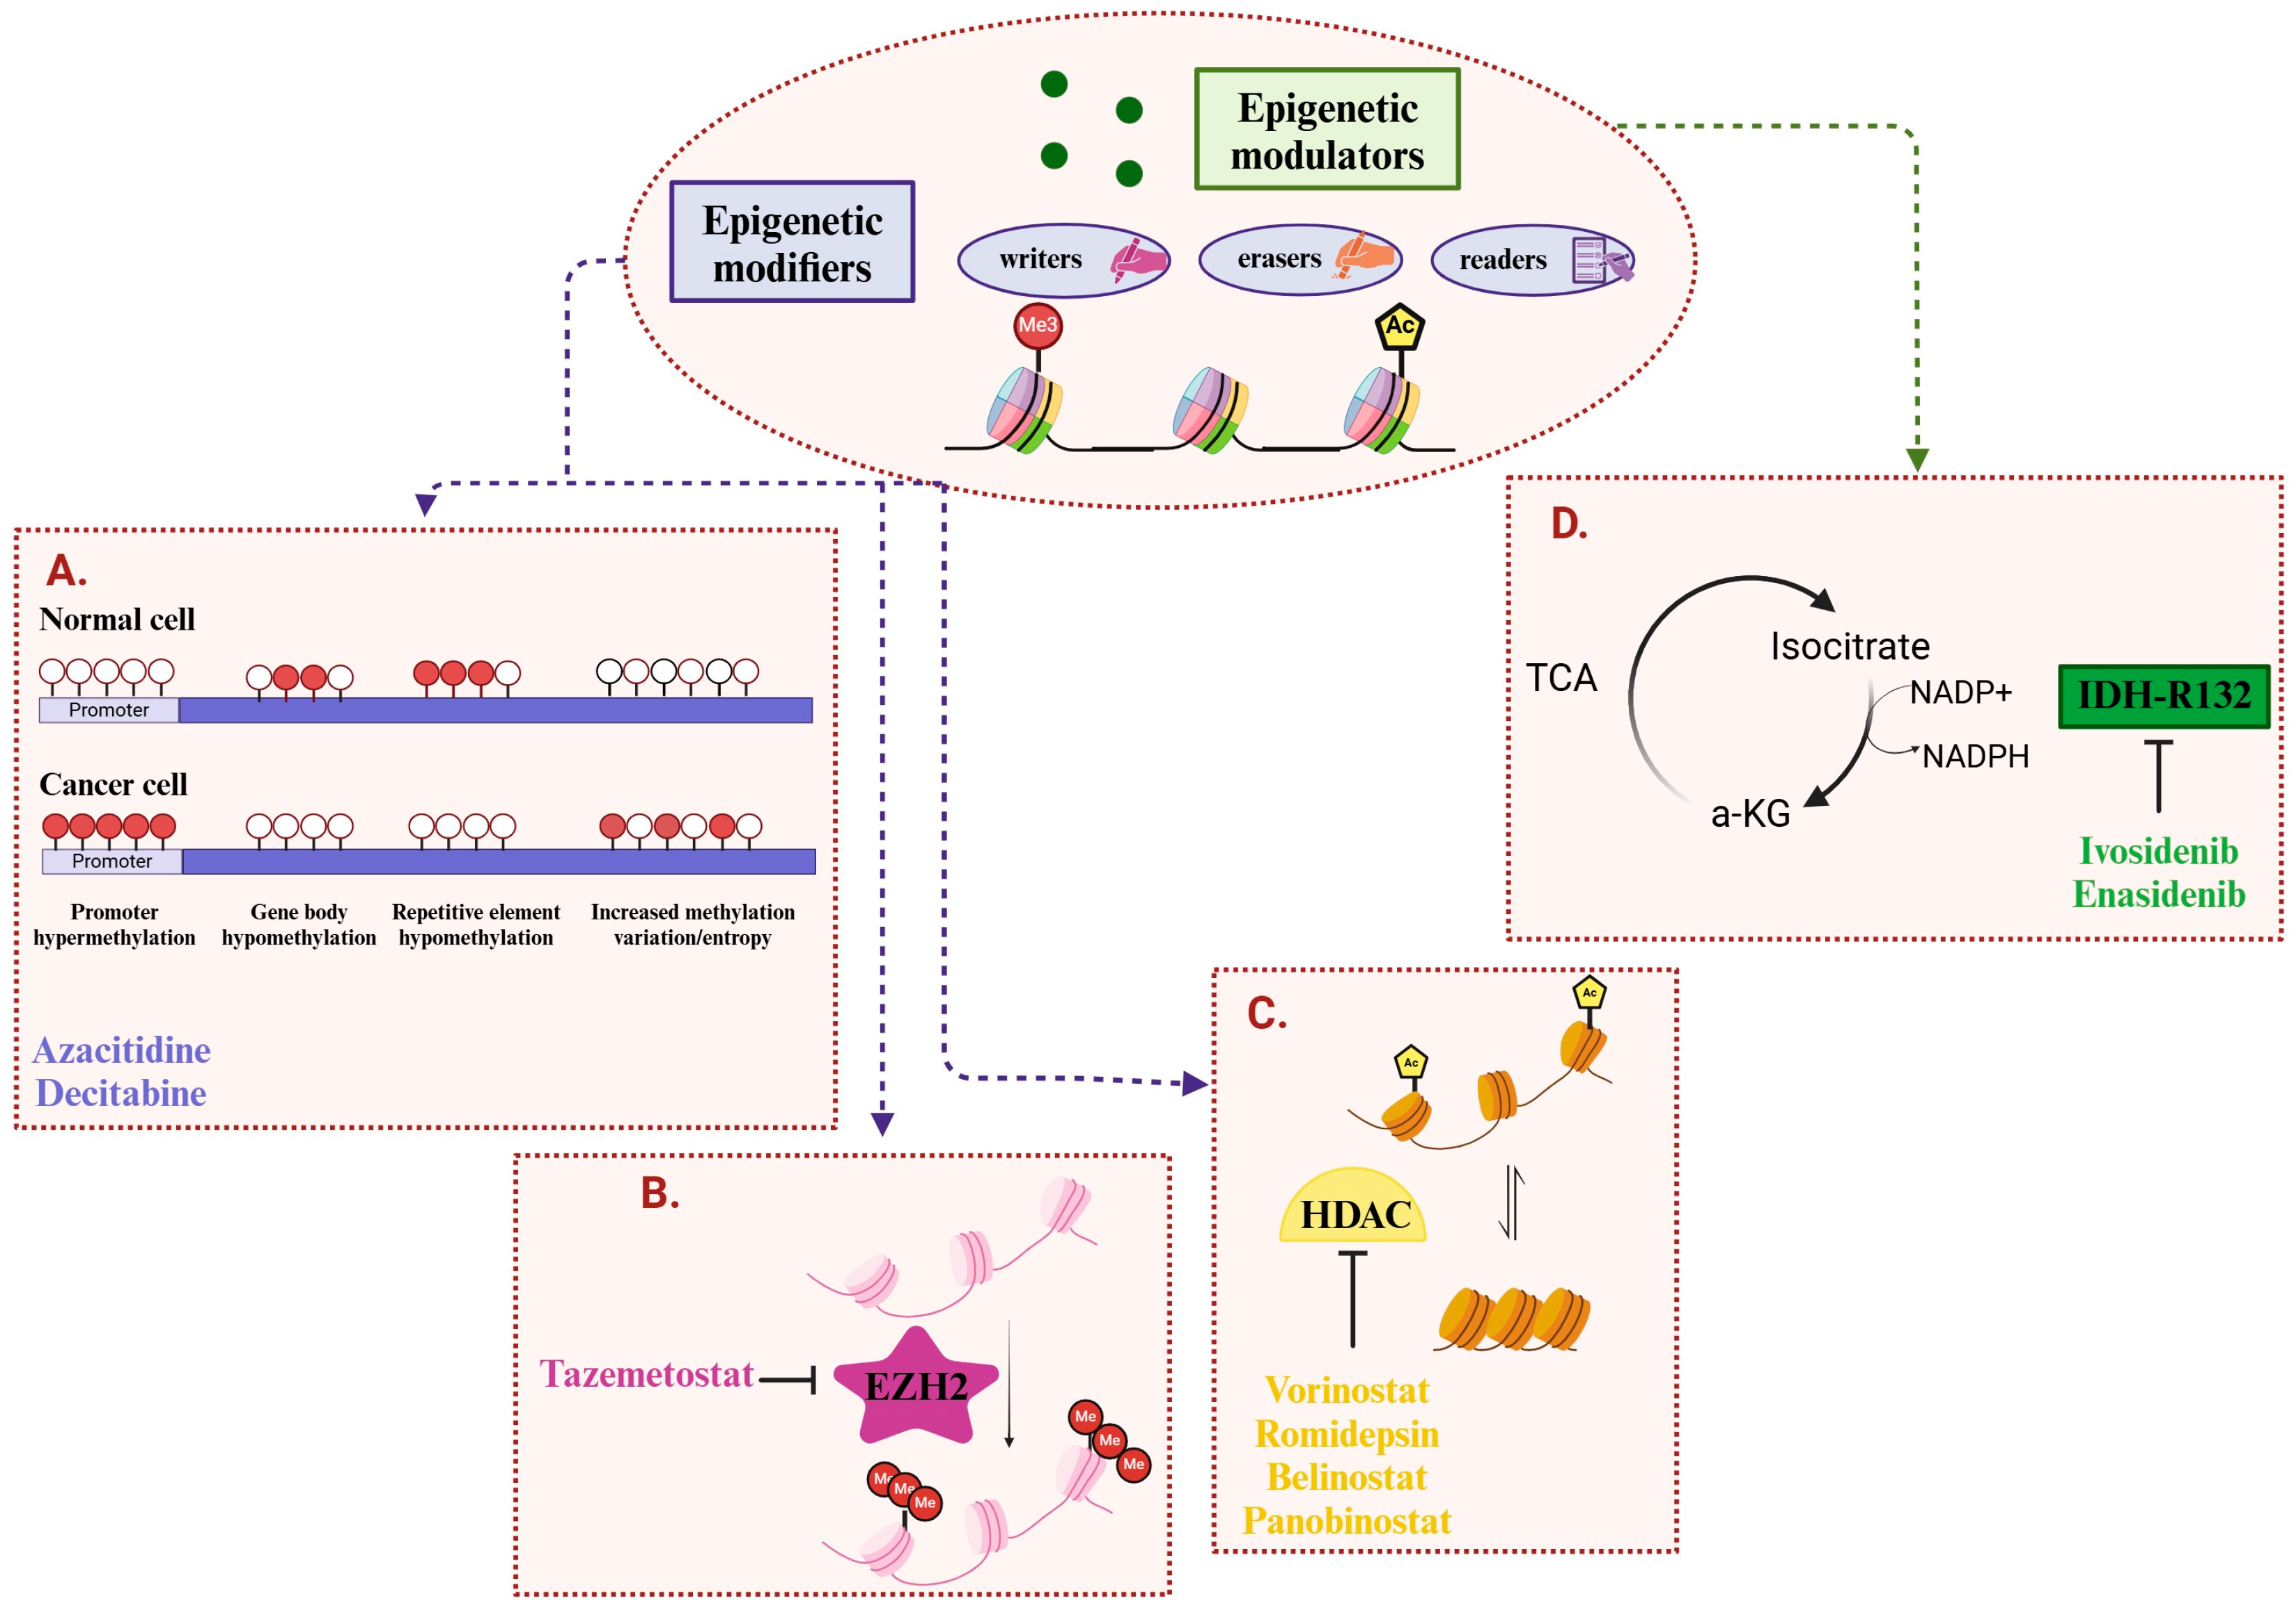
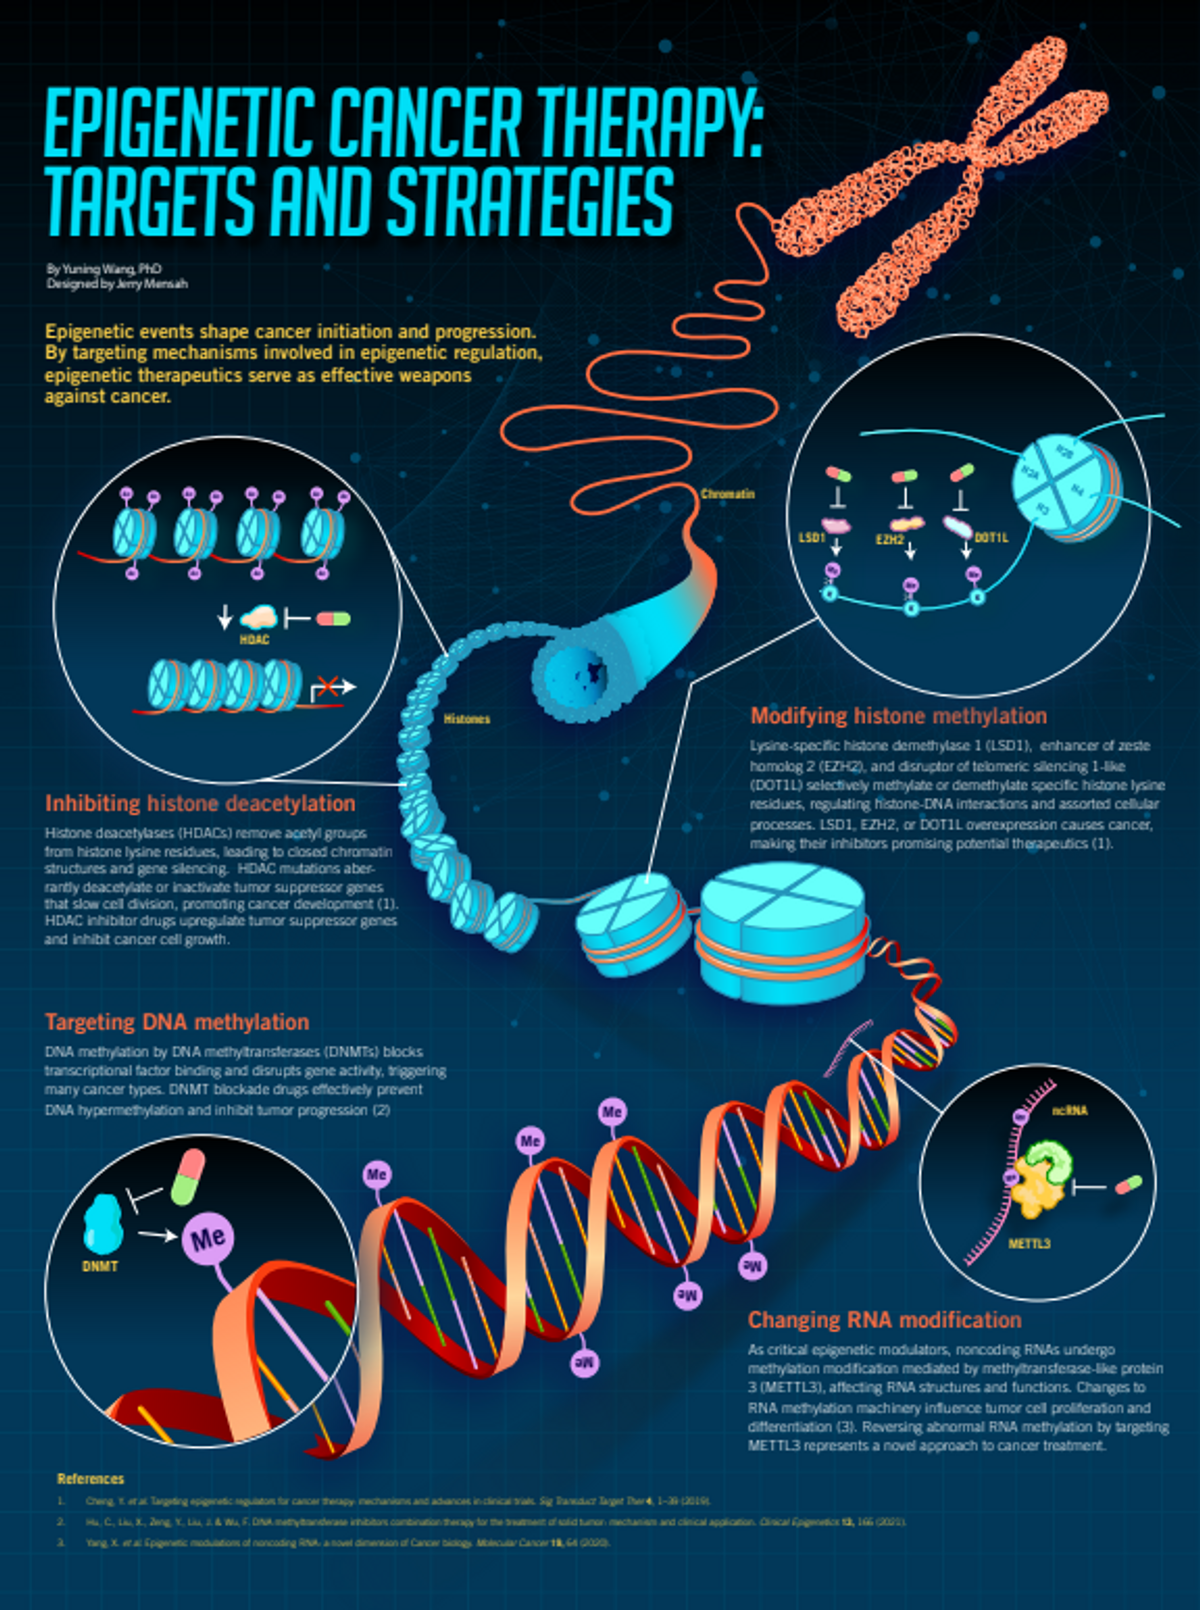
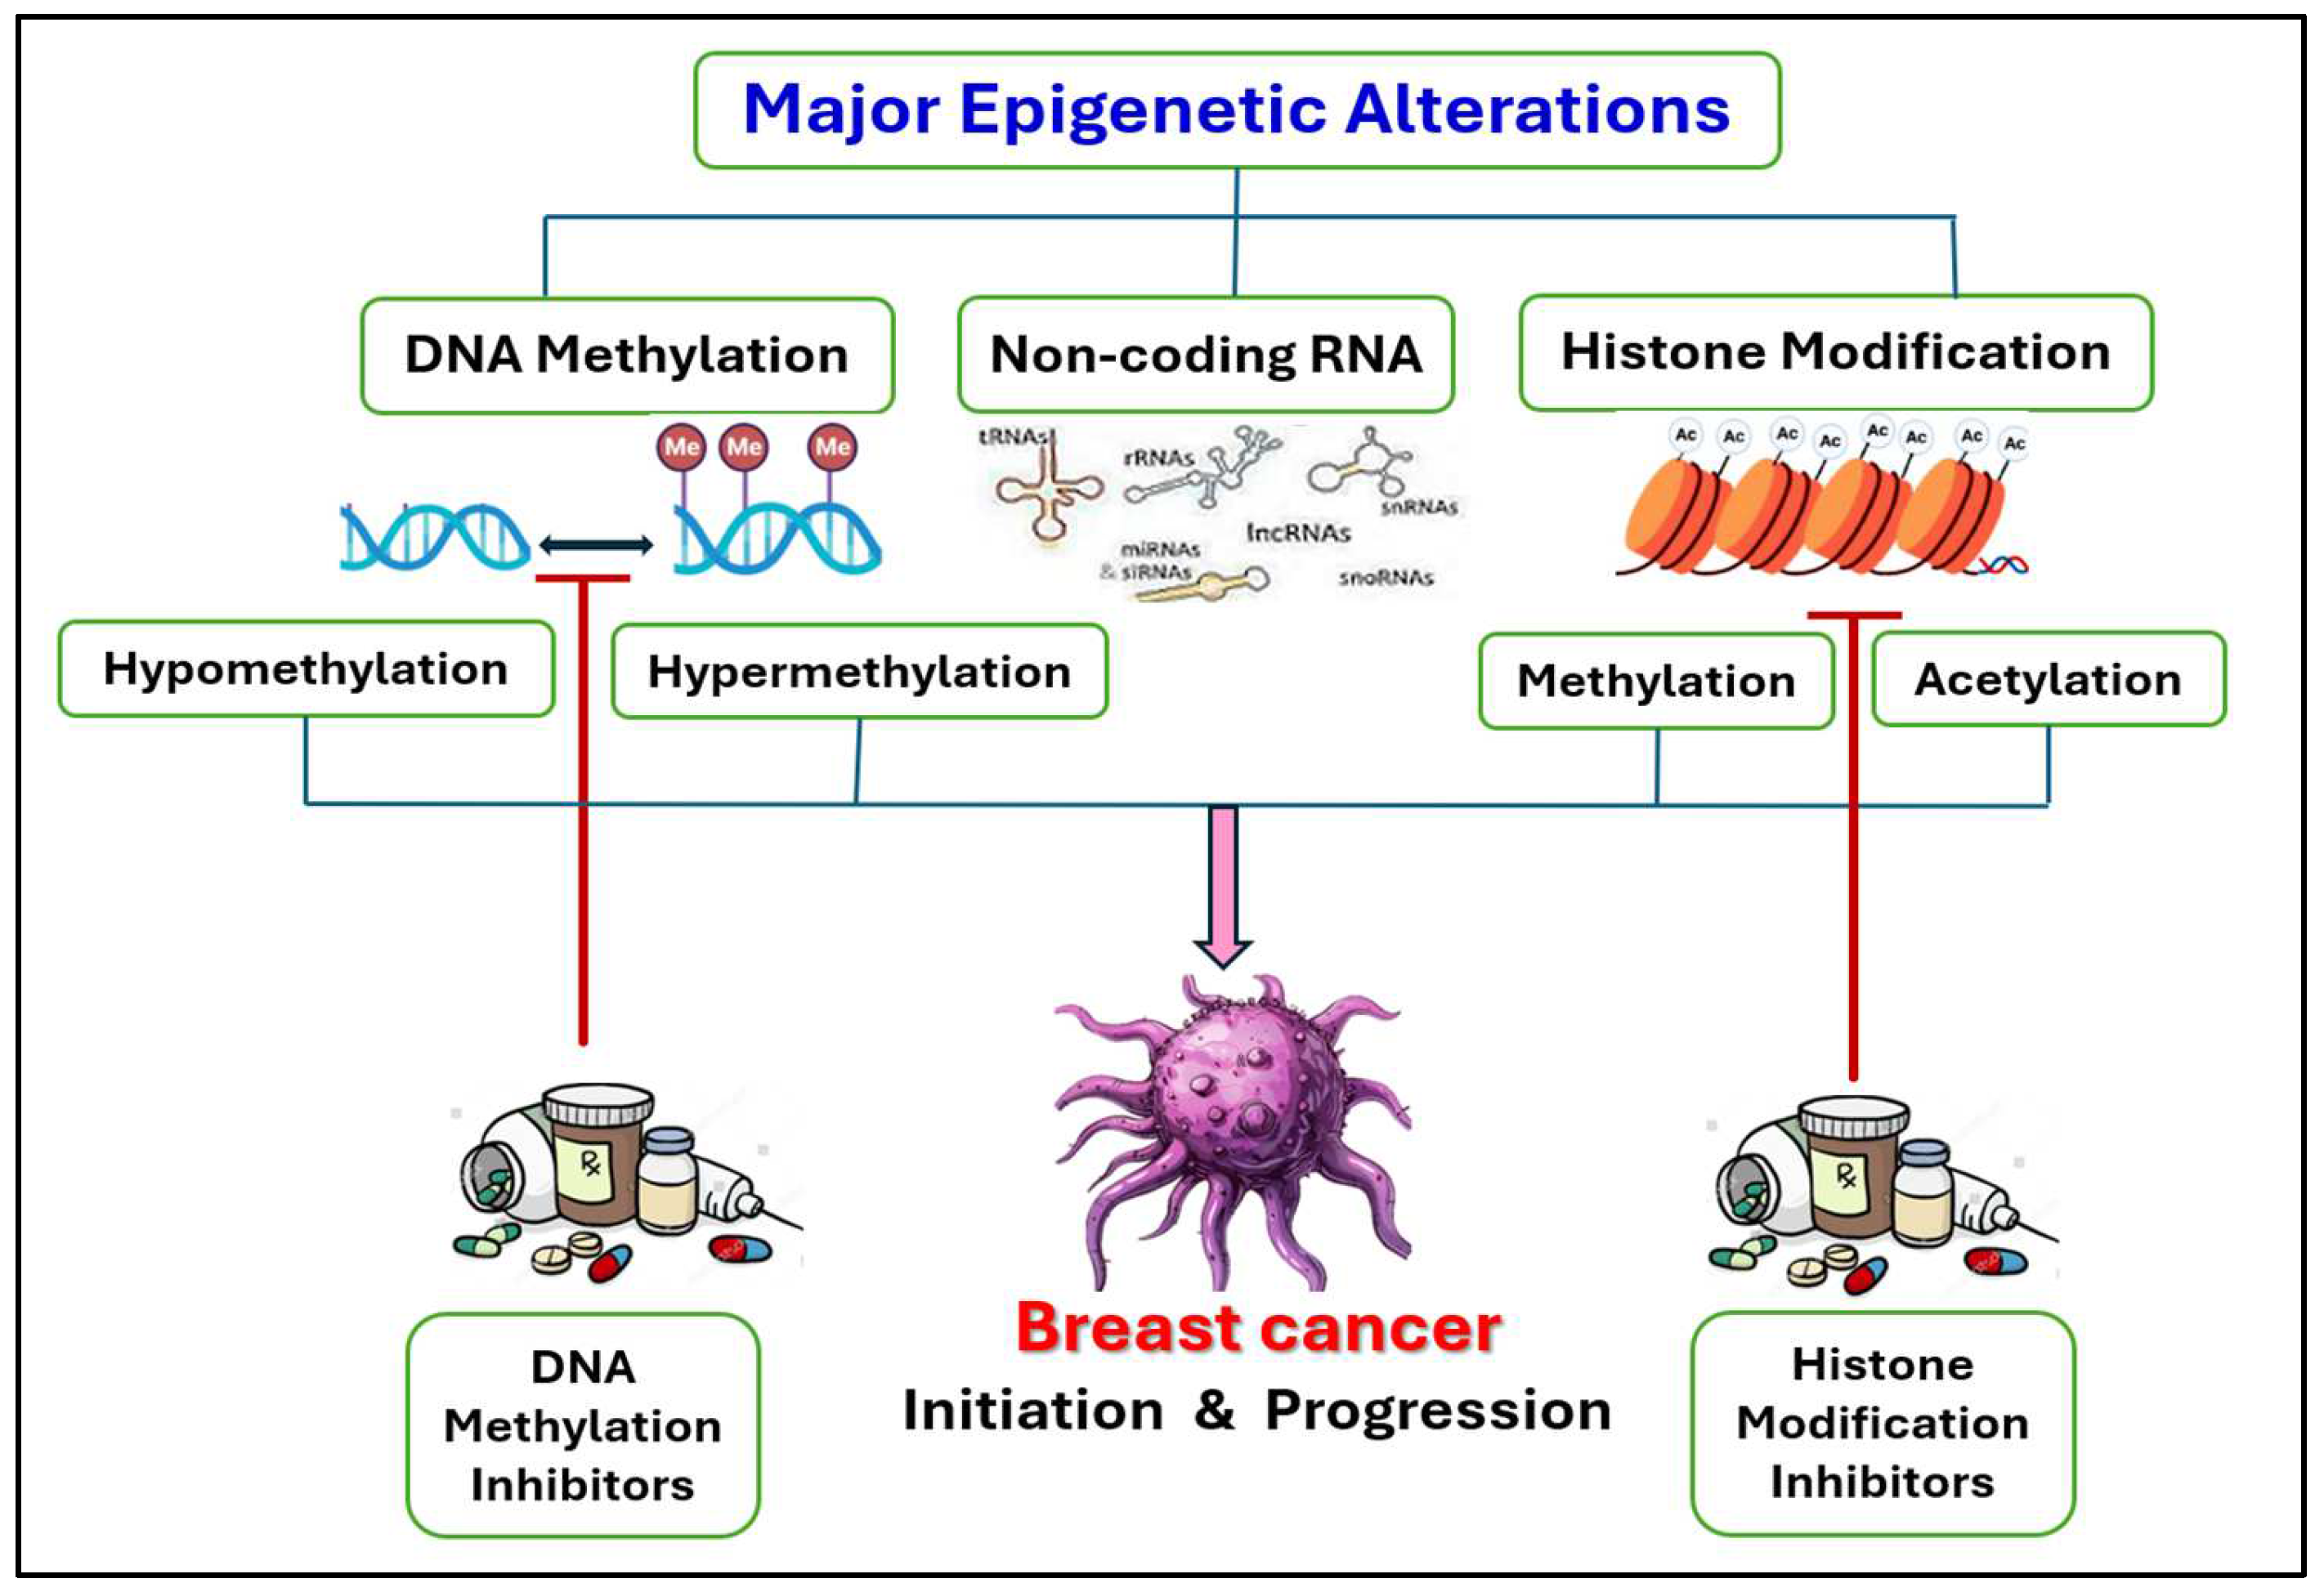
Epigenetic modifications control which genes get expressed without changing the underlying DNA sequence. In cancer, these regulatory mechanisms go wrong. Tumor suppressor genes get silenced through hypermethylation of their promoter regions. Chromatin becomes abnormally condensed. Histone modifications shift in ways that lock down protective gene expression. The result is uncontrolled cell proliferation. Epigenetic therapy aims to reverse those abnormal modifications. The two main drug classes in clinical use are DNMT inhibitors and HDAC inhibitors. DNMT inhibitors like azacitidine and decitabine work by incorporating into DNA during replication and trapping DNA methyltransferase enzymes, leading to passive demethylation over successive cell divisions. HDAC inhibitors like vorinostat and romidepsin block histone deacetylase activity, keeping chromatin in an more open configuration and allowing transcription to proceed. These drugs are not cure-alls. They are disease-modifying agents best suited for certain hematologic malignancies and early-line solid tumor strategies. Their mechanism is fundamentally different from chemotherapy because they do not directly damage DNA. Instead they alter the regulatory landscape that controls gene expression patterns in cancer cells.
How Treatment Actually Gets Administered
Azacitidine for myelodysplastic syndromes follows a standard 7-day subcutaneous or intravenous administration schedule repeated every 28 days. Decitabine typically uses a 5-day IV schedule on the same cycle length. Vorinostat for cutaneous T-cell lymphoma is dosed orally at 400 mg daily with food. Romidepsin is given as a 2-hour IV infusion on days 1, 8, and 15 of a 28-day cycle. The important detail that most patient education materials skip is that these drugs require repeated cycles over months before meaningful clinical response becomes visible. Azacitidine typically needs at least 4 cycles before response assessment. Early cycles may show only cytopenias without any tumor regression. This delay between treatment initiation and observable effect is a common source of unnecessary treatment discontinuation. I have seen clinicians mistakenly interpret early disease progression after 2 cycles as treatment failure and switch to alternative regimens. In reality, the epigenetic remodeling process takes time. The 4 to 6 cycle benchmark for response evaluation is not arbitrary. It reflects the biological timeline of how long it takes for demethylated promoter regions to sustainably reactivate tumor suppressor gene expression and for clinical benefit to emerge.
Combination Strategies and Practical Considerations
Combining DNMT inhibitors with HDAC inhibitors sounds mechanistically sound but produces overlapping toxicity profiles, particularly thrombocytopenia and neutropenia. I stopped recommending this combination after observing that the added toxicity rarely translated into better outcomes beyond what either agent achieves alone. The marginal benefit does not justify the increased hospitalization rates from cytopenic complications. A more productive approach involves combining epigenetic agents with immune checkpoint inhibitors. Hypomethylating agents upregulate endogenous retroviral elements and tumor-associated antigens, making the tumor microenvironment more immunogenic. This combination has shown promise in melanoma and non-small cell lung cancer. The epigenetic drug essentially prepares the terrain. The checkpoint inhibitor then exploits the exposed targets. One practical detail nobody mentions in prescribing guidelines: administer epigenetic therapy with antiemetics that do not strongly inhibit CYP3A4 if you are using vorinostat. Strong CYP3A4 inhibitors like ketoconazole can increase vorinostat exposure by roughly 40 percent. This is a drug interaction that comes up regularly in practice but is easily overlooked when multiple specialists are managing the same patient.
Get the Full Details
Realistic Limitations and When This Approach Fails
Epigenetic therapy does not work for all cancers. Solid tumors with extensive stromal barriers show significantly lower drug penetration compared to hematologic malignancies. The blood-brain barrier further limits efficacy in central nervous system tumors. I have encountered cases where patients with advanced pancreatic cancer received azacitidine with no measurable reduction in methylation markers despite adequate drug levels. The tumor epigenome in those cases had adapted through compensatory mechanisms that the drug could not overcome. Resistance to DNMT inhibitors develops through multiple pathways. One mechanism involves upregulation of nucleoside transporters that pump the drug out of cells more efficiently. Another involves mutations in the DNMT1 gene that reduce drug binding affinity. There is no reliable predictive biomarker yet for identifying which patients will develop resistance, though methylation signature profiling is an active area of investigation. The most significant limitation is that epigenetic drugs affect normal cells too. Systemic demethylation can reactivate oncogenes or disrupt normal tissue-specific gene programs. This is why dose-intensive schedules are generally not recommended. The therapeutic window is narrower than with traditional chemotherapy, and the margin between efficacy and unacceptable toxicity is smaller than many clinicians initially assume.
Biomarker Monitoring During Treatment
Serial monitoring of global DNA methylation levels through methods like liquid biopsy or bone marrow aspiration can track treatment response. However, these tests are not standardized across laboratories. I recommend establishing a baseline methylation profile before starting therapy and using the same laboratory for follow-up testing to ensure comparability. Gene expression profiling of specific markers like CADM1 and RARB demethylation status in myelodysplastic syndrome patients can provide prognostic information about likely response. These assays are available through specialized reference laboratories but add cost and turnaround time that may delay treatment decisions. Use them selectively rather than Routinely.