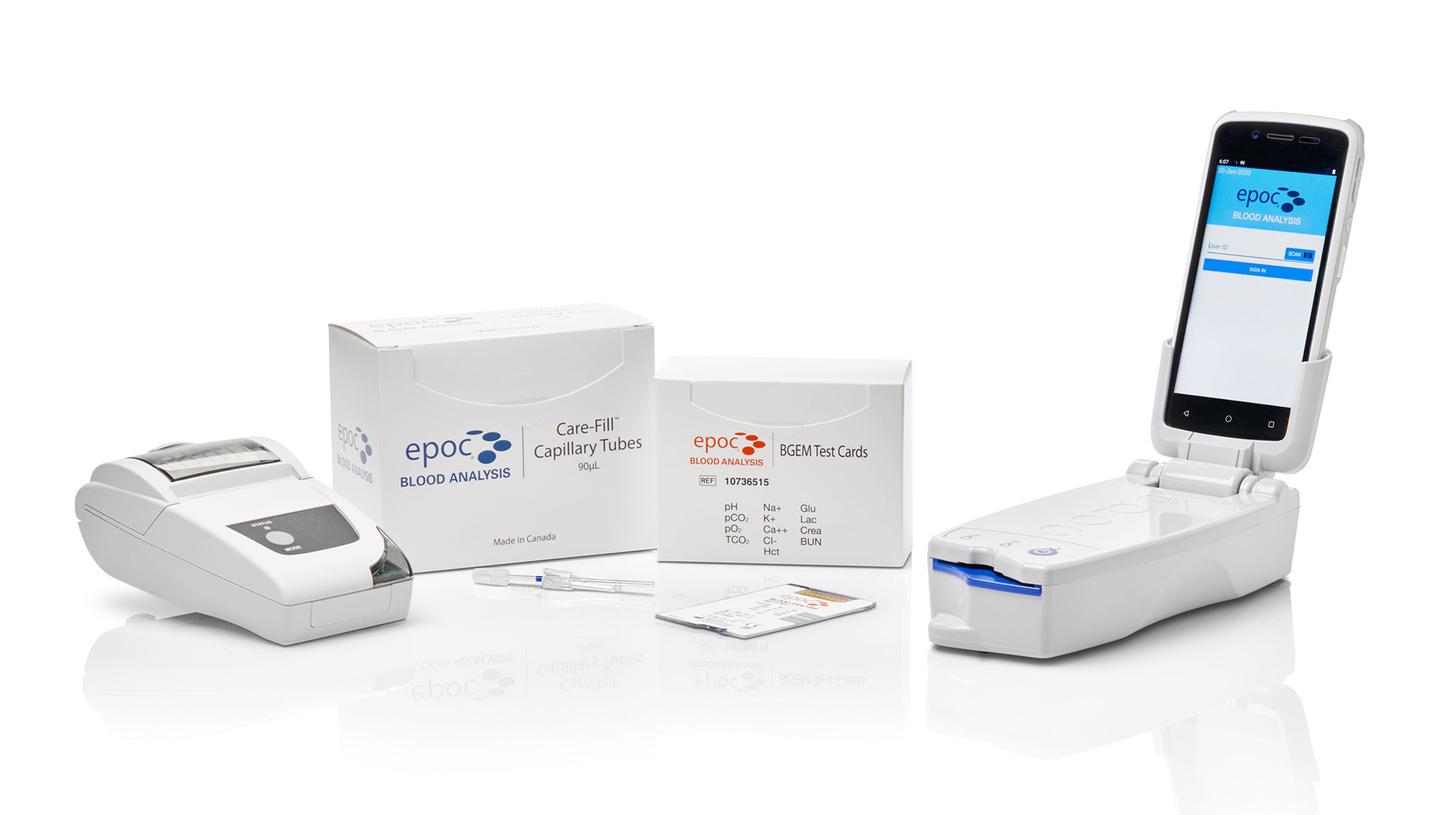
Running an epoc Blood Gas System in a Vet Clinic: What Actually Happens
The epoc system is a point-of-care blood gas and electrolyte analyzer that was originally developed by Radiometer (now part of ABL) for both human and veterinary use. It works by drawing a small whole blood sample into a disposable cartridge called the epoc Card, running the sample through microfluidic channels, and returning results in roughly three to five minutes. In a busy practice, that turnaround time is the main reason people adopted it. Instead of sending samples to a reference lab or waiting for a benchtop chemistry analyzer to cycle, you can have pH, pCO2, pO2, electrolytes, glucose, and hematocrit on the bench before the next client walks in the door. I ran an epoc in a small animal clinic for about four years before we phased it out. Here is what the workflow actually looks like, the things that go wrong, and the workaround I ended up using most days.
Setting Up and Running Epoc Blood Analysis Veterinary Tests
Before you touch a card, you need the epoc Base unit, the software or handheld display, and a current calibration kit. The system requires calibration at least once per day, and more often if the cards are a different lot number or the lab temperature shifts significantly. You open the Base, insert the calibration key, and run the calibration sequence. That takes about ninety seconds. When calibration passes, you are ready for patient samples. Precision matters more than speed. The system asks for heparinized whole blood, ideally collected in a lithium heparin syringe. You need to avoid air bubbles because the microfluidic pathways are small and an air bubble will throw off the pO2 reading and can cause the analyzer to reject the sample. When you draw arterial blood from a dog or cat, prime the needle and syringe with heparin, draw slowly, expel any visible bubbles, and cap the syringe immediately. Venous samples work fine for most parameters except pO2, which will be lower than an arterial value. That is not a machine problem; it is just physiology. To run the test, you load the epoc Card into the Base, attach the syringe, and press start. The machine aspirates the sample automatically. Results print out within three to five minutes. You review them, document them, and discard the card according to your biomedical waste protocol.
The results you get include pH, pCO2, pO2, Na+, K+, Ca2+, glucose, lactate, hematocrit, calculated bicarbonate, base excess, and saturation. Most of those values align reasonably well with reference laboratory chemistry analyzers when the sample quality is good. Hematocrit from the epoc tends to track close to a centrifuged value, though it can drift slightly in severely anemic patients where the machine may struggle with optical readings at very low red cell concentrations.
Get the Full Details

A Real Problem I Faced and How I Worked Around It
Here is the issue that cost me the most time. We had a case with a diabetic cat in a hyperosmolar crisis where the hematocrit result on the epoc was reading around twelve percent, but the centrefuge value from the same draw was twenty-one percent. The pO2 and pCO2 were fine. Electrolytes looked reasonable. The Hct was the outlier. I spent forty minutes troubleshooting the card, recalibrating, and checking the syringe. Nothing resolved it. The workaround was straightforward once I figured it out. In patients with marked hyperglycemia and osmotic shifts, the hematocrit channel on the epoc can read falsely low because the plasma refractive index changes and the optical hematocrit sensor gets thrown off. The fix was to run a concurrent microhematocrit spin from the same syringe sample while waiting for the epoc results. I recorded the epoc Hct as a questionable value and relied on the centrifuge method for clinical decisions. It added two minutes to the workflow and eliminated the guesswork. I never lost another case to a bad Hct reading from the machine in that scenario.
Where the epoc Fails and What to Do Instead
The epoc is not a universal solution. It has clear limitations that anyone running it daily will run into. The sample volume requirement is small, which is convenient, but it also means you cannot reliably re-run a sample if the first attempt fails. You need a fresh draw. That matters in exotics and very small patients where blood volume is already tight. Carrier hemolysis is another common failure mode. If the sample is hemolyzed, the potassium reading will be falsely elevated because the red cells release their intracellular potassium during the run. A+ result of seven or higher on the epoc often turns out to be pre-analytical hemolysis rather than true hyperkalemia. I stopped trusting K+ from an epoc whenever the sample looked visibly pink or red. Instead, I sent that parameter out to the lab or repeated the draw from a fresh site. The other electrolytes and blood gases remain usable in that situation. Lactate accuracy on the epoc is generally acceptable for trending but not precise enough for absolute decision-making in septic shock. I found that epoc lactate values could differ by up to one point five mmol/L compared to a laboratory analyte from an ABL800 or similar benchtop system. For critical care patients where you are making dosing decisions based on lactate clearance, I preferred the benchtop method or at least a second confirmation draw. The epoc lactate is fine for screening and trend monitoring over hours. It is not fine as a single absolute number in a crashing patient.
Reagent cost is another practical bottleneck. Each epoc Card runs roughly twenty to thirty dollars depending on your supplier contract. For a high-volume emergency clinic doing ten to fifteen blood gas panels a day, that adds up fast. We calculated the annual cost at about eight to ten thousand dollars in consumables alone, not including maintenance contracts and calibration keys. When margins are thin, that is a real factor.

Practical Tips That Come From Using the System Daily
Store cards at the recommended temperature. The epoc Card box has a temperature indicator strip. If it has ever shown exposure to heat or cold outside the specified range, discard the entire lot. I have seen degraded cards produce erratic pH readings and strange error codes that waste both time and sample. Cold weather delivery is particularly risky in winter months. Ask your supplier to ship with ice packs only if the carrier guarantees temperature control, otherwise skip it and let the cards acclimate in the office for an hour before loading them into the Base. Keep a log of card lot numbers and calibration dates. The system does not always flag a drifting sensor until you run a patient sample and get a questionable result. A simple spreadsheet with lot numbers, calibration pass/fail, and any error codes lets you trace patterns. When we had a batch of cards that produced consistently high pCO2 values, the lot log caught it before we misinterpreted four separate cases. That saved us from making treatment decisions on bad data. Never force a syringe into the card port. The epoc uses a specific luer connection and the machine applies vacuum suction automatically. Forcing a mismatched connector can damage the port seal and create leaks that lead to rejected runs and occasional calibration failures. If your syringe does not seat smoothly, stop and get the correct adapter or switch to a compatible syringe type. The manufacturer lists approved syringes in the operator manual, and deviating from that list voids the calibration assumption built into each card.
When I Recommend Skipping the epoc Entirely
There are situations where sending the sample to a reference lab or using a benchtop analyzer is simply better. Severe icterus, lipemia, or hemolysis can interfere with multiple optical and electrochemical sensors on the card at once. In those cases, the epoc may return plausible-looking numbers that are systematically wrong. A lab analyzer with different sampling paths and larger sample volumes often handles those interferences more reliably. Large animal patients with very high hematocrits, usually above sixty percent, also present challenges. The optical hematocrit measurement reaches its upper limit and can plateau. I have seen epoc Hct read at sixty-two percent when the actual value was closer to seventy percent in a dehydrated horse. For those cases, a standard centrifuge method or a laboratory chemistry analyzer gives more accurate results. The blood gas values from the epoc remain useful in horses, but I rely on the spin for hematocrit. Cost-conscious practices should do a quick break-even analysis before buying or leasing the system. If you are doing fewer than five blood gas panels per week, the per-test cost likely exceeds what a reference lab charges, and the maintenance burden outweighs the convenience. The epoc shines when you need rapid results repeatedly throughout the day, especially in emergency and critical care settings. It is less compelling as a standalone diagnostic tool in a low-volume general practice.
If you want current documentation, the manufacturer still provides operator manuals and cartridge details on their veterinary resources page, and most distributors maintain updated pricing and compatibility charts for the epoc system. The information there is more reliable than any old forum post, and it will reflect the current software revisions and approved accessories.