Managing Epoprostenol Therapy Side Effects: A Practical Guide for Home Infusion
Epoprostenol (Flolan, Veletri) is the original prostacyclin analog for treating pulmonary arterial hypertension, and managing its side effects is something most pulmonologists and home-infusion nurses learn the hard way. The drug itself is effective, but the side effects are real, persistent, and in some cases dangerous. This guide covers what you actually see in practice, how to manage the common issues, and where the standard advice falls short. Epoprostenol is a synthetic version of prostacyclin (PGI2), a naturally occurring vasodilator. It works by relaxing pulmonary vascular smooth muscle and inhibiting platelet aggregation. The problem is that PGI2 receptors aren't exclusive to the pulmonary circulation. When you infuse it systemically, you get vasodilation everywhere — not just in the lungs. That's why the side effect profile is so broad. One detail that catches people off guard: epoprostenol has an extremely short half-life of about 3 to 5 minutes. Any interruption in the infusion — even for a few minutes during a pump change or catheter disconnection — can result in rapid hemodynamic decompensation. Patients on this therapy need to understand this before they leave the hospital. There is no margin for error with timing.
Most Common Side Effects and How to Handle Them
Epoprostenol Therapy Side Effects That Show Up First
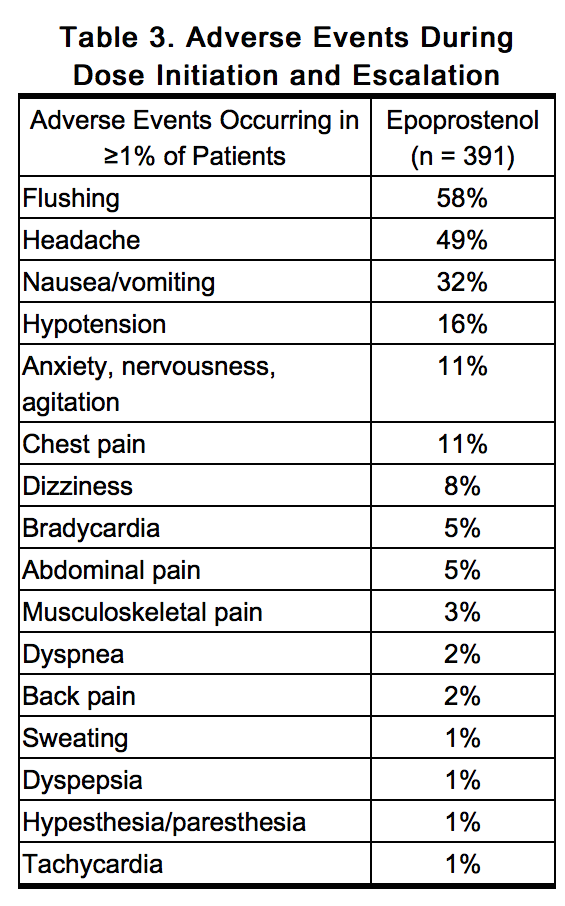
The most frequently reported side effects during initiation and dose escalation include: Flushing and warmth: This affects nearly every patient to some degree. It's caused by peripheral vasodilation. Most patients adapt partially over weeks, but complete resolution is uncommon. For severe cases, splitting the total daily dose into smaller, more frequent adjustments helps. Some patients benefit from taking acetaminophen 30 minutes before dose increases. This doesn't eliminate flushing but reduces its intensity enough that patients can function. Jaw pain and headache: These are classic prostacyclin side effects and often the first reason patients want to stop the infusion. Jaw pain typically occurs during dose escalations and can be quite severe — patients describe it as a deep, aching sensation behind the teeth and jaw. The mechanism involves vasodilation of the maxillary vessels. The practical workaround is slower titration: increase by 0.25 nanograms per kilogram per minute rather than the standard 0.5, and hold for at least 3 to 5 days at each new level instead of the typical 1 to 3 days. It's slower, but it prevents many unnecessary dose reductions later.
Diarrhea: This affects roughly a third of patients and is often underestimated. It can lead to dehydration and electrolyte abnormalities, which then complicate the already delicate fluid balance in PAH patients. Loperamide at standard doses usually helps, but in refractory cases, splitting meals into smaller, more frequent portions and reducing fat intake can make a meaningful difference. One thing I learned from experience: diarrhea on epoprostenol is often worst in the first 2 weeks after any dose increase, then stabilizes. Patients shouldn't assume it's a separate gastrointestinal issue and stop the medication — it's almost always the drug itself, and it tends to improve with continued use at a stable dose. Nausea and vomiting: Ondansetron or metoclopramide before the main daily dose increase can prevent this in many patients. Pre-medication timing matters — give the antiemetic 30 to 60 minutes before the anticipated peak side effect window, which is usually within the first 2 hours after a dose increase. Hypotension: Systemic vasodilation drops blood pressure. This is more common during rapid escalation or in patients who are already volume-depleted. The fix is usually straightforward: ensure adequate oral fluid intake (2 to 3 liters per day unless contraindicated by right heart failure), consider fludrocortisone 0.1 mg daily for persistent orthostatic symptoms, and slow the titration schedule. If systolic blood pressure drops below 90 mmHg with symptoms, hold the next dose increase until it recovers, then resume at the previous tolerated level.
Get the Full Details
Less Common But More Serious Side Effects
Line infections and sepsis: This is the most dangerous complication of long-term epoprostenol therapy. The central venous catheter required for continuous infusion is a permanent foreign body, and biofilm formation is almost inevitable over months to years. Febrile episodes in these patients must be treated as line infections until proven otherwise. Blood cultures from both the catheter and a peripheral site should be drawn before any antibiotics are started. The infection rate in long-term epoprostenol users is estimated at roughly 1 infection per 10 to 20 catheter-days in published series, though proper nursing care reduces this significantly. Pulmonary edema: Epoprostenol increases pulmonary blood flow by reducing pulmonary vascular resistance, and in patients with left heart disease or mitral valve pathology, this increased flow can precipitate pulmonary edema. This is why a thorough echocardiographic workup is mandatory before starting therapy. If pulmonary edema develops, the epoprostenol dose may need to be reduced even though it would otherwise be benefiting the pulmonary hypertension. Bleeding: Epoprostenol inhibits platelet aggregation, which increases bleeding risk. This is usually manageable but becomes clinically significant with invasive procedures, dental work, or concurrent anticoagulation. Many PAH patients are also on warfarin or direct oral anticoagulants for thromboembolism prophylaxis, and the combination requires careful monitoring of INR if warfarin is used.
Subcutaneous reactions at the catheter site: If epoprostenol leaks into the subcutaneous tissue around the catheter insertion site, it causes intense localized pain, inflammation, and tissue necrosis. This is a medical emergency requiring immediate discontinuation of the infusion through that catheter and replacement at a new site. Patients and caregivers should be taught to recognize early signs: increasing redness, warmth, or pain at the insertion site that is disproportionate to what's typical.
A Practical Case: The Night Infusion Crisis
Early in my experience managing PAH patients on epoprostenol, I had a case that changed how I approach this therapy. A 34-year-old female patient was doing well on 10 nanograms per kilogram per minute. She came to the emergency department at 2 AM reporting severe bilateral leg pain and headache. Her dose had been stable for 6 months. She'd been using her home pump without any issues until that night. Initial workup showed normal electrolytes, no sign of infection, and a normal ECG. The leg pain was the key finding — it was bilateral, deep, and associated with mild cyanosis of the toes. I initially thought it was unrelated to the epoprostenol. But on re-examination of her infusion log, I noticed the battery had died around midnight, and she'd been running on backup power from a secondary pump that had been set up hastily. The backup pump wasn't delivering at the exact programmed rate — it was running approximately 30% faster than intended. We suspected that the transient dose increase had caused severe peripheral vasoconstriction followed by reactive changes. The leg pain resolved within 6 hours of returning to her correct infusion rate, and the headache cleared within 12 hours. This case taught me two things: first, to always ask patients to bring their pump logs and infusion history to any emergency visit, and second, to consider infusion delivery accuracy as a potential cause of new or worsening side effects, not just dose-related problems.

Dose Adjustment Protocol: What the Literature Doesn't Emphasize
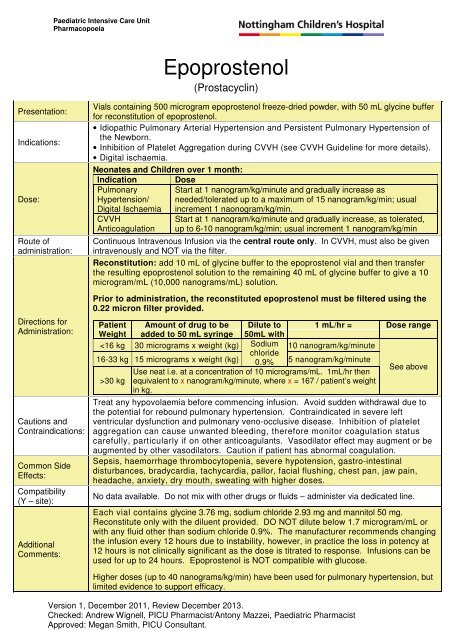
The standard epoprostenol dose adjustment protocol is straightforward in theory: increase by 0.25 to 0.5 nanograms per kilogram per minute every 1 to 3 days until the target dose is reached or side effects become intolerable. In practice, this approach fails for a significant subset of patients who cannot tolerate the standard escalation rate. Here's what works in clinical practice when the standard protocol isn't enough:
- Use 0.25 nanograms per kilogram per minute increments instead of 0.5 for patients who experience significant side effects at each step
- Extend the interval between increases to 5 to 7 days instead of 1 to 3, allowing side effects to fully resolve before the next attempt
- If side effects persist at a given dose, don't immediately reduce — wait 48 to 72 hours. Many side effects, particularly headache and jaw pain, continue to improve even at a stable dose as the body partially adapts
- For patients who cannot tolerate doses above 5 nanograms per kilogram per minute despite optimized side effect management, adding a second-class PAH medication (an endothelin receptor antagonist or PDE5 inhibitor) can allow the epoprostenol dose to remain lower while still achieving therapeutic benefit through combination therapy
Counterintuitive Insights About Epoprostenol Side Effects
Here are a few things that aren't widely discussed in the patient education materials: Paradoxical worsening of hypoxemia at high doses: Epoprostenol is a non-selective vasodilator. At higher doses, it can dilate vessels in poorly ventilated areas of the lung, worsening ventilation-perfusion mismatch and actually decreasing oxygenation. This is why some patients who initially improve on epoprostenol plateau or even show declining oxygen saturations at higher doses. The solution isn't always to push harder — sometimes the optimal dose is lower than you'd expect, and adding a complementary medication is more effective than maximizing the prostacyclin dose alone. The "honeymoon period" is real and it ends: Many patients experience a dramatic improvement in the first weeks of therapy that exceeds what they'll maintain long-term. This is partly due to the initial vasodilatory effect and partly due to placebo and expectation effects. Patients who understand that the initial response may not be sustainable are less likely to become discouraged when symptoms gradually return over months. The disease is still progressing; the drug is still helping, just not as dramatically as in the beginning.
Downloadable Resources
The American Thoracic Society and the European Respiratory Society both publish patient education materials on epoprostenol therapy that cover side effect management in patient-friendly language. The National Organization for Rare Disorders (NORD) also has a detailed guide on prostacyclin therapy that includes a side effect tracking template. Most major pharmaceutical companies that produce epoprostenol products offer patient support programs with printed and digital materials covering infusion management, side effect recognition, and emergency procedures. For healthcare providers, the IPF Foundation and PHAF ( Pulmonary Hypertension Association ) maintain clinical reference guides that include detailed dosing algorithms and side effect management protocols. These are updated periodically as new evidence emerges.

When to Seek Immediate Medical Attention
Certain side effects require urgent evaluation. Fever above 100.4°F (38°C) in a patient on epoprostenol is a line infection until proven otherwise and requires immediate medical assessment. Any signs of catheter site infection — redness, swelling, drainage, or increased pain — should be evaluated the same day. Sudden worsening of shortness of breath, chest pain, or fainting episodes warrant emergency care, as these could indicate either disease progression or a complication of the infusion itself. Patients should also be aware that stopping epoprostenol abruptly can be fatal. The short half-life means that withdrawal effects begin within minutes, and severe rebound pulmonary hypertension can develop within hours. Any planned interruption must be done under medical supervision with a transition plan to another prostacyclin-class medication if needed.
The Bottom Line on Epoprostenol Therapy Side Effects
Epoprostenol remains one of the most effective treatments for severe pulmonary arterial hypertension, but it demands careful management. The side effects are predictable in most cases and manageable in nearly all of them, but they require patience and close communication between the patient, the home-infusion nursing team, and the pulmonologist. The most important thing I can say after years of managing these patients: don't rush the titration, don't ignore persistent side effects, and never stop the infusion without a plan. The drug works, but it works within a narrow therapeutic window that requires constant attention.