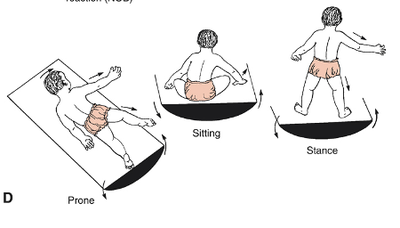
What Equilibrium Reactions Actually Are
Equilibrium reactions are the unconscious postural adjustments your body makes when you lose your balance. They kick in automatically when your center of gravity moves past your base of support, and the whole cascade — muscle activation, joint stiffening, limb extension — happens in roughly 150 to 200 milliseconds. In occupational therapy, we use them as both a functional outcome measure and a training target. People with neurological impairments, developmental delays, or deconditioning often have weak or absent equilibrium reactions, which translates directly to falling when they reach for something, turning too quickly, or getting off a couch without compensating first. I have spent years watching clinicians treat equilibrium as something you just "strengthen" with balance boards. That approach works sometimes. It also fails repeatedly because equilibrium reactions are a neurological coordination pattern, not a muscular one. You can have strong core muscles and still not have functional equilibrium reactions. The pattern has to be practiced in the right positions, at the right perturbation speeds, with enough repetition to actually rewire the response. That is the difference between someone who can stand on a wobble cushion for two minutes and someone who catches themselves when they stumble on uneven ground.
Equilibrium Reactions Occupational Therapy
This is where the real work happens. We break equilibrium reactions down into the three sub-types we assess and train: tilting, lifting, and pulling. Tilting is the first line of defense — it happens before the center of gravity actually leaves the base of support. A patient reaches forward and their trunk leans ahead while their ankles dorsiflex to keep them over their feet. Lifting occurs when one leg is already raised, like when stepping over a threshold and the stance leg stabilizes. Pulling is the most dramatic — it happens when the support surface itself moves, like being on a bus that brakes suddenly, and the whole body shoots back to recapture the base of support. Here is what I did differently when I realized my standard protocol was plateauing with a stroke patient who could perform all three reactions on the therapy table but couldn't stand unassisted in her kitchen. The problem was context. On the flat, predictable table surface, her equilibrium reactions were intact. The moment the environment became unpredictable — cluttered floor, visual distractions, the subtle give of her kitchen tiles — the reactions degraded. I stopped bringing her back to the table for drills and instead trained everything in the actual environment where she needed the skills. I placed her in her kitchen, introduced perturbations by nudging her shoulders at different speeds and directions, and used tactile cues only when she was about to fall. Within six sessions, her independent standing time went from forty seconds to over three minutes. The equilibrium reactions themselves didn't change. The context-dependent reliability of them did.
How to Assess Equilibrium Reactions in Practice
Start with sitting. Have the person sit on a firm surface with feet flat and hips at ninety degrees. Apply a quick lateral push to the shoulders and watch for the hip hiking and lateral trunk flexion on the side opposite the push. That hip hike is the lifting equilibrium reaction. Then do the same in front and behind. A delayed or absent response here usually signals proximal stability deficits or unilateral neglect, depending on which direction is affected. Move to standing. Ask the person to stand with feet together, arms at their sides. Stand behind them and give a quick, gentle forward pull on the shoulders. They should step forward with one foot and swing their arms out to catch themselves. Watch which foot steps first — the unaffected side usually leads. If neither foot steps and they just bend at the knees or trunk, their equilibrium reactions are not intact for that perturbation speed. Try it again slower. Sometimes the reaction is there but the speed of perturbation exceeds their processing threshold. Record the results. Note which directions are impaired, what the latency looks like, and whether they compensate with strategic responses like grabbing for support. Strategic responses are not equilibrium reactions — they are learned conscious strategies. The goal of therapy is to make the unconscious reactions reliable enough that strategic responses are not the only thing keeping someone upright.
Get the Full Details

Training Protocol That Actually Moves the Needle
Progression order matters more than most therapists account for. Start in sitting on a stable surface. Once tilting reactions are consistent in all directions, add an unstable surface underneath the pelvis — a rolled towel under the sit bones, not under the thighs. Then progress to kneeling. Kneeling removes the ankle strategy and forces hip and trunk reactions to carry the load. After that comes standing with feet together, then narrow stance, then tandem stance. By the time someone is doing standing equilibrium reaction training on a foam surface with their eyes closed, they are working at the upper end of what most community-dwelling adults need. Perturbation parameters determine the training effect. Speed matters. A slow push triggers a different muscle recruitment pattern than a fast snap. Start at roughly thirty percent of the person's maximum tolerable perturbation speed and increase by ten percent increments each session. Duration of the perturbation — how long the push lasts — should be held constant at around two hundred milliseconds once you find the working range. Direction should rotate: anterior, posterior, lateral, diagonal. Diagonal perturbations are the most functionally relevant because real-world falls rarely happen in a single plane. Repetition schedule. A typical effective dose is forty to sixty perturbation trials per session, broken into sets of eight to ten with thirty seconds of rest between sets. Doing fewer than thirty trials per session produces negligible adaptation in most clinical populations. More than eighty trials per session tends to cause fatigue-related degradation of the response, which reinforces the wrong pattern. The total program length for meaningful change in an adult stroke population is usually eight to twelve weeks at three sessions per week, assuming the person is also doing weight-bearing and gait work outside of equilibrium reaction training specifically.
Common Pitfalls I See Repeatedly
The biggest mistake is treating all equilibrium reaction training as if it is the same thing. It is not. A person with cerebellar ataxia will have delayed but present reactions that overshoot. A person with hemiparesis from stroke will have absent reactions on the affected side and may overcompensate on the sound side. A child with developmental delay may have the mechanical ability but not the central pattern recognition to trigger the reaction in time. The training approach for each is fundamentally different, and using the same protocol across these populations wastes time and sometimes causes harm. Another issue I encounter constantly is over-reliance on commercial balance equipment. The foam pads and wobble boards are useful as tools, but they are not the intervention. The intervention is the perturbation and the repeat. Someone can stand on a half-foam roller for twenty minutes and still not develop functional equilibrium reactions if no perturbation is being introduced. The equipment creates the conditions for instability. The therapist has to create the actual challenge. I once watched a therapist spend an entire clinic period with a patient on a Bobath ball with no perturbations, just bouncing gently. The patient was engaged and the therapist felt productive. Nothing about equilibrium reaction specificity was being addressed. A third pitfall is testing and training at the same speed every time. If you always push at the same rate, the patient learns to anticipate the push. Anticipation is not equilibrium. It is a voluntary corrective action dressed up as a reflex. Vary the timing randomly. Sometimes push after one second. Sometimes after four. Sometimes not at all and just hold the position. This forces the nervous system to stay in a state of readiness rather than predicting and pre-activating muscles based on rhythm.
When Equilibrium Reaction Training Is Not the Right Move
There are scenarios where pushing equilibrium reaction training hard and fast is counterproductive. Acute stroke patients in the first seventy-two hours often have globally depressed reflexes and altered sensation. Aggressive perturbation training during this window can increase spasticity and does not produce lasting gains. The literature here is clear — early mobilization is valuable, but structured equilibrium reaction drilling should wait until the acute inflammatory phase subsides and some voluntary movement returns. Patients with severe proprioceptive loss from peripheral neuropathy present a different problem. Equilibrium reactions depend on sensory input from the ankles, hips, and vision. If the proprioceptive signal from the lower extremities is gone, training the motor response alone will not fix the underlying deficit. These patients need sensory retraining and environmental modification first. An cane or walker in their daily life will serve them better than ten weeks of perturbation drills on a therapy table. Advanced Parkinson's disease is another population where standard equilibrium reaction training hits a wall. The bradykinesia and rigidity make the speed of perturbation almost always too fast for the patient's motor system to engage. What works better for this group is external cueing — auditory metronomes, visual targets on the floor, rhythmic counting during weight shifts. The cue bypasses the damaged basal ganglia pathway and uses alternative neural circuits to trigger movement. It is not equilibrium reaction training in the strict sense. It is a compensatory strategy that achieves a similar functional outcome.
Documentation That Actually Helps Future Treatment
Most documentation for equilibrium reaction work is too vague to be useful. "Improved balance" tells you nothing. Record the specific reaction tested, the direction of perturbation, the latency observed, the number of strategic substitutions, and the surface condition. Example: "Sitting equilibrium reactions — lifting reaction absent in right lateral direction on foam surface, present on firm surface with visual feedback." That tells you exactly what to address next session and gives you a measurable baseline for the following assessment. Use a simple rating scale alongside the descriptive notes. A five-point scale from absent to normal is standard and works well if you apply it consistently. The scale number alone is meaningless across sessions unless you define what each point looks like in concrete terms. Define it once in your documentation system and stick to it. A three means the reaction occurs but with a visible delay and requires a strategic substitution in fifty percent of trials. That definition should never shift because the patient is improving or because you had a busy day. The data point most therapists forget to record is the directionality of the impairment. A patient who only lacks posterior equilibrium reactions has a different fall risk profile than someone who lacks lateral reactions. Posterior deficiency correlates strongly with backward falls, which are harder to recover from because people do not expect to fall that way. Lateral deficiency correlates with sideward falls and hip fractures in older adults. Note the direction. It changes the safety recommendations you make for discharge.