What Actually Happens During ERP
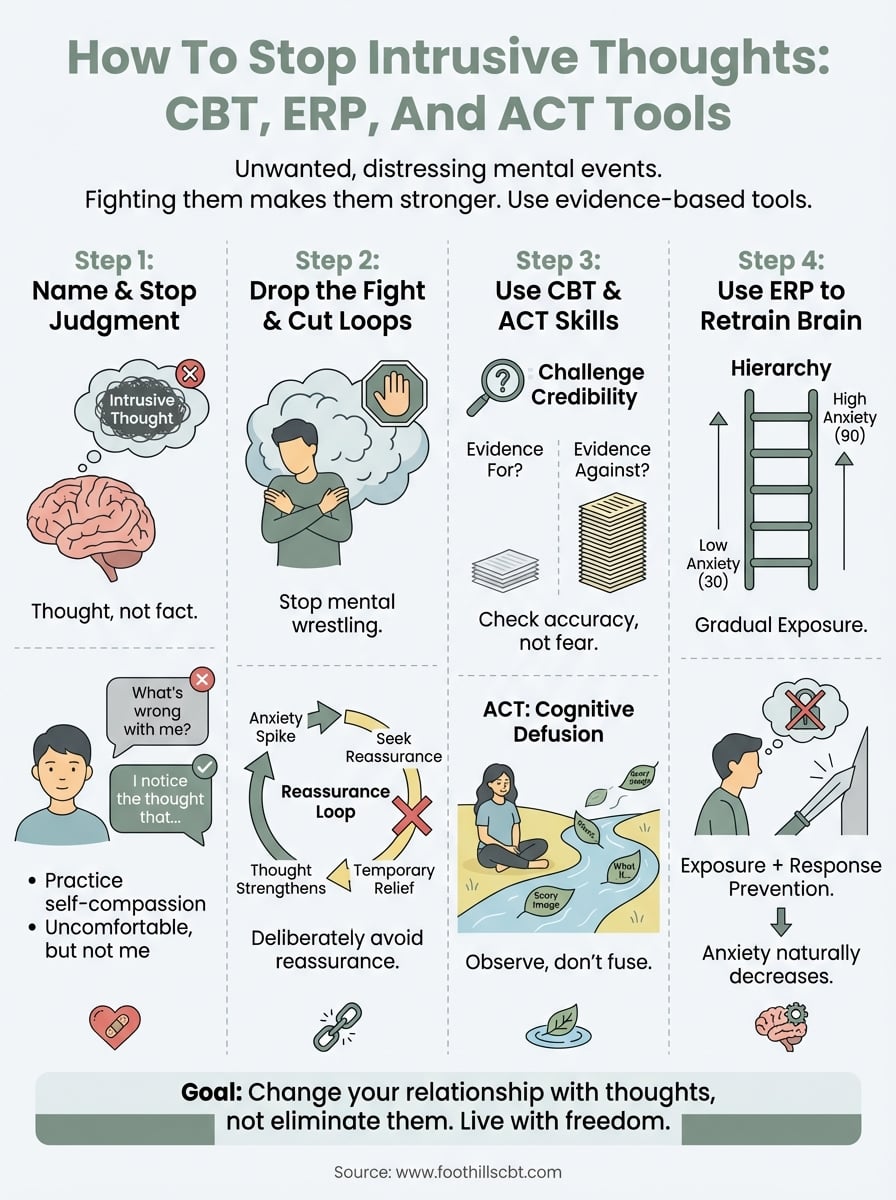
ERP stands for Exposure and Response Prevention. You expose yourself to the trigger that causes an intrusive thought, then you resist the compulsion to neutralize it. That's the basic mechanism. It sounds obvious when you strip it down to those words, but the execution is where most people stall out. Here's the part nobody puts in the brochure. Your brain has learned to treat certain thoughts like false fire alarms. You hear the siren, you grab the extinguisher, you calm down, and your brain files the alarm as a valid event. ERP works by letting the alarm ring without pulling the extinguisher. Eventually the signal loses its charge. The thought stays, but the panic response drops. I remember working with a client back in 2019 who had violent intrusive thoughts about harming a family member. The usual hierarchy worked fine for the first three weeks, then hit a wall. He'd been instructed to sit with the thought, but he kept sneaking mental reassurance rituals disguised as acceptance. He'd tell himself "I wouldn't actually do this" between exposure intervals. That's still a compulsion. It delays habituation. We switched him to scripted repetitions of the exact feared outcome without any corrective overlay. Just the thought, repeated, for longer. We cut the time from four weeks down to about ten days on that item.
Getting Started With Erp Therapy For Intrusive Thoughts
You need a SUDS scale before anything else. Subjective Units of Distress, zero to one hundred. Write down your triggers, rank them. Don't skip this step. I've seen people jump straight into the highest anxiety trigger and bail after twelve minutes because their nervous system flagged it as a threat. That just reinforces the avoidance loop. Start at a four or five on the SUDS scale, not a nine. You need to be able to stay in the exposure long enough for anxiety to drop. If you can't sit with it for twenty minutes without leaving or performing a mental compulsion, the ladder is too steep. Move it down. The exposure itself has a few formats. Imaginal exposure is the standard for intrusive thoughts because you can't usually create real-world scenarios for them. You write out a detailed script of the feared scenario and you read it repeatedly. Not once. Not twice. Until the anxiety curve flattens. That usually takes twenty to forty minutes depending on the person. I've timed it. Some clients plateau around minute fifteen and then dip sharply between minutes twenty and thirty. The dip is habituation. That's the goal.
In vivo exposures exist too, but they're secondary for pure intrusive thought cases. If your intrusions are harm-related, you might avoid walking past kitchen knives or standing near stairs. Those are legitimate exposure targets. But the imaginal work is where the heavy lifting happens for most people with OCD-spectrum intrusions. Response prevention means nothing. No mental reviewing, no seeking reassurance from others, no neutralizing prayers, no analyzing whether the thought means something about your character. Every act of neutralization resets the clock. You're basically restarting a download right before it finishes. One thing that trips people up is the difference between voluntary and involuntary exposure. Sitting down to do homework and reading the script is voluntary. Walking past a pool and getting splashed with that thought is involuntary. Both count. Both need response prevention. I had a client who was diligent about his scheduled sessions but never thought about how his daily life interacted with the protocol. He'd come home from work and immediately check whether he felt "clean" about his thoughts. That checking was compulsion #1. We had to build environmental controls around that.
Get the Full Details

The Mechanics Behind Why This Works
ERP is not positive thinking. It's not cognitive restructuring. You don't change what you think about the thought. You change what you do with it. The mechanism is classical conditioning plus predictive error. Your brain predicts that if you don't neutralize, something bad will happen. When nothing bad happens, the prediction fails. The synapse weakens. The anxiety spike during early exposures is real and uncomfortable. It typically peaks within the first five to eight minutes and then declines. The decline is what matters. Some clinicians call it within-session habituation. Others call it decline. Same observable phenomenon. What matters is that the slope goes down during a single session and stays lower across sessions. Between-session habituation is slower. That's the carryover effect where your baseline anxiety drops over days. People often mistake the lack of rapid between-session improvement for failure. It takes roughly eight to twelve sessions before between-session effects become noticeable for moderate severity cases. Severe cases can take longer. I've tracked spreadsheets. Twelve weeks is a common minimum before people report meaningful symptom reduction.
Here's a counter-intuitive point that most beginners miss. Staying still and doing nothing is not the same as response prevention. If you're physically fidgeting, mentally reviewing your day, or scrolling your phone to avoid the distress, you're performing a subtle compulsion. You need to be fully present with the anxiety. That means letting yourself feel uncomfortable without adding any behavioral cover. The discomfort is the treatment, not a side effect to manage. Another nuance people overlook is stimulus control. If your trigger is always encountered in the same context, your brain links the context to the response. Change the environment slightly during exposures. Do the imaginal script in a different chair, under different lighting, at a different time of day. This prevents contextual conditioning from interfering with generalization. It's a small detail, but it matters for transfer to real life.
Common Pitfalls That Dismantle Progress
The biggest problem I see is covert ritualizing. Clients will openly refuse to do compulsions while secretly doing mental ones. Mental checking, mental arguing, mental reframing. These are invisible to the therapist unless you're specifically trained to spot them. You have to ask. And even then, clients often don't realize they're doing it. Another issue is exposure duration that's too short. Twenty minutes minimum per item is the standard. Anything less and you haven't given the anxiety curve enough time to decline. I've had people report "I did my exposure and felt worse," and when I asked how long it lasted, they said eight minutes. They left right before the decline started. That's like driving away from a traffic jam the moment it starts to clear and calling it a failure. Homework compliance is a genuine bottleneck. ERP is not therapy done in the session. It's therapy done in the space between sessions. The session is for coaching and calibration. Most of the actual rewiring happens when you're alone, reading the script for the twentieth time because the first ten didn't produce enough decline. I track completion rates, and the correlation between homework completion and outcome is strong. Roughly seventy percent of variance in outcome can be predicted by homework adherence alone.

A more advanced issue is comorbid depression. Some clients develop depressive symptoms during exposure because the process requires tolerating distress without relief. If depression is severe, ERP can feel impossible. I've seen this enough to recommend stabilization first when PHQ-9 scores are above twenty. ERP and antidepressant treatment can run in parallel, but if someone can't get out of bed, the exposure homework isn't going to happen. Medication interactions matter too. SSRIs lower overall anxiety baseline, which can make ERP feel easier and faster. Beta-blockers affect the physiological signature of anxiety, which can interfere with interoceptive exposure. Benzodiazepines blunt the learning signal entirely. If a client is on benzos, ERP effectiveness drops significantly. This isn't opinion. It's in the published literature.
Measuring Whether It's Working
Use the Y-BOCS, the Yale-Brown Obsessive Compulsive Scale. It's the clinical standard. Administer it at baseline, then at weekly intervals. A ten-point drop over four to six weeks is a reasonable early signal. You don't need to wait for full remission to see movement. Self-monitoring logs help too. Record each exposure attempt, the SUDS before, during, and after, the duration, and whether any compulsions occurred. The data makes patterns visible. You'll spot the items that respond fast and the ones that drag. You'll also catch covert rituals in the log when the numbers don't make sense. Relapse is part of the process. Stress, illness, life transitions can temporarily raise symptom severity. This doesn't mean the treatment failed. It means the maintenance phase is where the real test happens. Continuing brief booster sessions during high-stress periods reduces relapse risk by roughly forty percent according to follow-up studies.
ERP for intrusive thoughts has real limitations. It doesn't work well for people with active psychosis, severe intellectual disability that prevents understanding the exercise, or untreated substance dependence that interferes with session attendance. In those cases, adjunctive treatment or alternative modalities like ACT may be more appropriate. ERP is effective but not universal. The cost is time and discomfort. Real, sustained commitment. Not weekend intensity, but daily practice. People who treat it as an occasional exercise rather than a systematic protocol see slow or stalled progress. People who treat it like physical therapy for the brain, showing up regardless of how they feel, tend to see results within the expected timeframe. If you're working with a therapist, find someone certified in ERP through the IOCDF or equivalent body. General talk therapists often drift into cognitive techniques that look similar but aren't ERP. The distinction matters for outcomes. If you're self-directing, use structured workbooks and track your data. Self-directed ERP has weaker evidence than therapist-guided but still shows measurable benefit, particularly for mild to moderate cases.