What Actually Works When You Are Learning Human Anatomy
Most anatomy students study wrong. They re-read textbooks, highlight diagrams, and watch lecture videos for hours without ever closing the book to recall what they just saw. This is one of the most expensive mistakes a student can make, because it creates a false sense of competence. You recognize the material when it is right in front of you, but that recognition is not the same as recall. When you sit for your practical exam and a proctor points at a specimen, you have to produce the name from memory, and the pathway between recognition and production is completely different.
The Essential Anatomy Tricks that actually move the needle are not flashy. They are structural changes to how you approach the material. The biggest shift comes from treating every study session as a test rather than an intake exercise. Closed-book recall, done immediately after exposure, is the single highest-yield activity you can do. Close the atlas. Close the book. Draw the brachial plexus from memory on a blank piece of paper. Get it wrong. Look at the atlas. Get it wrong again. The struggle during retrieval is where the learning happens, not the initial reading.
Essential Anatomy Tricks Most Students Skip
Active recall should be your default mode. Flashcards work only if they force you to generate the answer rather than select from options. A card that says "what nerve supplies the diaphragm" with four choices is essentially a multiple choice question, and that is dramatically less effective than a card that forces you to write the answer. Digital spaced repetition systems handle the scheduling for you, so you only review what you are about to forget. But the system is only as good as the cards you create. Cheap cards with trivial details clutter your queue and waste time. Focus your cards on relationships and structures that you genuinely confuse.
Landmark-based learning changes how you orient yourself in space. The body is not a list of names. It is a three-dimensional structure where every named thing sits relative to something else. Instead of memorizing that the radial artery lies lateral to the biceps tendon, you learn to find the biceps tendon first, then move laterally until you feel the pulse. This spatial anchoring makes recall faster and more reliable under exam pressure. When you know where things live relative to each other, you can reconstruct anatomy even when you cannot remember a specific fact.
Clinical correlation prevents dry memorization from becoming forgettable memorization. Learning the branches of the external carotid artery in isolation is tedious and unnecessary. Learning that the external carotid supplies the face and scalp while the internal carotid supplies the brain gives you a conceptual framework. A stroke patient with facial symptoms localizes differently than a stroke patient with homonymous hemianopsia. These connections make the raw data stick because it is no longer arbitrary information. It is information with purpose.
Variations and anomalies deserve attention before you think they do. Standard anatomy textbooks present an idealized version of the human body that exists in roughly half the population. The rest show variations. A recurrent laryngeal nerve that takes a non-recurrent course on the right side, an accessory hepatic artery coming off the left gastric artery, a bifid ulnar nerve at the elbow. These are not trivia. They are the reasons surgeries go wrong and the reasons clinical correlations matter. Learning them early, even at a basic level, prevents shock when you encounter them later in clinical practice.
The Cadaver Lab Approach
Cadaver labs are where textbook anatomy becomes real, and most students leave too much value on the table. The dissection table is not a place to passively watch the instructor. It is a place to touch, probe, and trace structures through their entire courses. Finding the median nerve in the arm, following it down past the biceps, seeing where it crosses in front of the elbow, and then entering the forearm between the two heads of the pronator teres is an experience that no diagram can replicate.
Label as you dissect. Keep a small notebook or take photos with annotations. You will forget the orientation of a structure two weeks later even if you think you will not. Photographing the setup with arrows or labels pointing to key relationships creates a personal reference library. Later, when you are studying from flashcards, you can pull up those photos and reinforce the spatial memory with the visual one.
Working with partners improves retention. Teaching a concept to someone else forces you to organize your thoughts clearly. If you cannot explain why the ulnar nerve is vulnerable at the medial epicondyle in simple terms, you do not understand it well enough yet. Disagreeing with a partner about which structure is which reveals gaps in your knowledge faster than any professor can.
Nomenclature and the Language Problem
Anatomy has its own language, and that language comes primarily from Latin and Greek. Students who struggle with terminology often struggle with the material itself, because the vocabulary is the tool you use to think about the subject. Learning the roots helps. Broncho means lung. Hepato means liver. Nephro means kidney. Once you know these building blocks, compound terms become transparent rather than opaque.
The terminology itself is standardized internationally through Terminologia Anatomica, but that does not mean your textbook uses the same terms. Different traditions exist, and older atlases may use outdated language. Knowing the modern standard term and its synonyms prevents confusion when you encounter different sources.
Mnemonics and Memory Systems
Mnemonics are useful but overrated. They work for lists that have no logical structure, like the cranial nerves and their sensory or motor functions. "On Old Olympus's Towering Tops" gets you the order of the nerves. But mnemonics should not replace understanding. A mnemonic for the branches of the external carotid artery helps you remember the sequence, but it does not teach you why those structures need blood supply or where they are located. Use mnemonics as scaffolding, not as the entire structure.
Visualization works better than verbal repetition for spatial subjects. Mental maps of anatomical regions are more durable than verbal lists. Close your eyes and picture the layers of the abdominal wall from skin to peritoneum. Picture the contents of the femoral triangle. Walk through the structures in your head as if you were tracing them on a specimen.
Common Mistakes and How to Avoid Them
The most consistent mistake students make is confusing structure relationships. The brachial artery is anterior to the humerus in the arm. The radial nerve winds around the humerus in the spiral groove. These facts are easy to mix up when you are studying them in isolation. Grouping related structures and studying their spatial relationships together prevents this kind of confusion.
Another common error is focusing on details before the major structures. Learning the precise attachments of a small hand muscle before you understand the compartments of the forearm and how the nerves and vessels reach the hand is inefficient. Master the major pathways first, then fill in the details. The details matter eventually, but they matter less than the framework they sit within.
Misidentifying structures during practical exams is frustrating but preventable. If you consistently confuse the anterior and posterior divisions of the brachial plexus, you are likely studying them in isolation rather than as part of the whole plexus. Study the entire plexus, understand why it divides where it divides, and the individual components become easier to distinguish.
Modern Tools and Software
Digital anatomy platforms like Complete Anatomy, Visible Body, and eAnatomy have changed how students study, but they have a catch. They make anatomy look too clean. Real specimens are messy. Fascial planes are not always clearly demarcated. Fat obscures structures. Digital models present an idealized version that helps you learn relationships but can mislead you about what structures actually look like in practice. Use these tools for relationship mapping and 3D rotation, but do not rely on them exclusively for understanding surgical or clinical appearances.
CT and MRI correlation adds a dimension that gross anatomy alone cannot provide. Understanding how anatomical structures appear on imaging is clinically essential. The thoracic aorta looks different on a coronal CT slice than it does in a dissection. The liver segments visible on ultrasound are organized differently from the surface anatomy you learn in the lab. Exposure to imaging early in your training helps bridge this gap.
Time Management and Study Efficiency
Focused study sessions beat marathon sessions every time. Two hours of deliberate practice with active recall and spaced repetition is worth more than six hours of passive reading. Your brain consolidates information during rest, not during the initial exposure. Shorter sessions with breaks allow for better retention and reduce fatigue-related errors.
Spaced repetition scheduling matters. Reviewing material the day after learning it, then three days later, then a week later, then two weeks later, moves information from short-term to long-term memory far more effectively than massed practice. Apps like Anki automate the scheduling, but you still need to create the cards and engage with them honestly.
When Standard Methods Fail
Some students find that visual-spatial learning does not come naturally, and that is okay. Auditory learners may benefit from recording themselves describing structures and listening to the recordings. Kinesthetic learners may benefit from building models or using clay to construct anatomical structures. Different people process information differently, and rigidity in your study method is often the problem, not the material.
Students with dyslexia or language processing difficulties may struggle with the heavy terminology load. This is a real obstacle, but it is not insurmountable. Pairing written terminology with audio pronunciation and visual representations creates multiple access points to the same information. The goal is comprehension, not perfect spelling of Latin names.
Quick Reference Facts That Save Time
The brachial plexus roots, trunks, divisions, cords, and branches follow a predictable pattern that can be recalled with a modified mnemonic, but the pattern itself is more important than the mnemonic. Root: C5 through T1. Trunks: superior, middle, inferior. Divisions: anterior and posterior. Cords: lateral, posterior, medial. Branches come off at each level. Understanding this architecture lets you predict missing or extra branches rather than memorizing every variant.
Blood supply to the gut follows clear rules. Foregut drains to the celiac trunk. Midgut to the superior mesenteric artery. Hindgut to the inferior mesenteric artery. The boundaries are at the ampulla of Vater for foregut-midgut and at the splenic flexure for midgut-hindgut. These landmarks matter clinically because they determine which structures are affected in vascular occlusion or inflammatory conditions.
Lymphatic drainage follows similar territorial patterns. Upper limbs drain to axillary nodes. Lower limbs to inguinal nodes. testes to para-aortic nodes despite their abdominal origin. This last point is the one students miss most often, and it is the one that matters most clinically because it explains why testicular cancer metastasizes to retroperitoneal lymph nodes rather than inguinal nodes.
The autonomic nervous system has a straightforward organization that is often overcomplicated. Sympathetic outflow is thoracolumbar. Parasympathetic outflow is craniosacral. The preganglionic fibers are long in parasympathetic and short in sympathetic. Postganglionic fibers run the opposite way. This pattern explains why sympathetic stimulation produces widespread effects while parasympathetic stimulation is more localized.
Gallery Essential Anatomy Tricks
Basic Concepts and Tricks in Anatomy | PDF
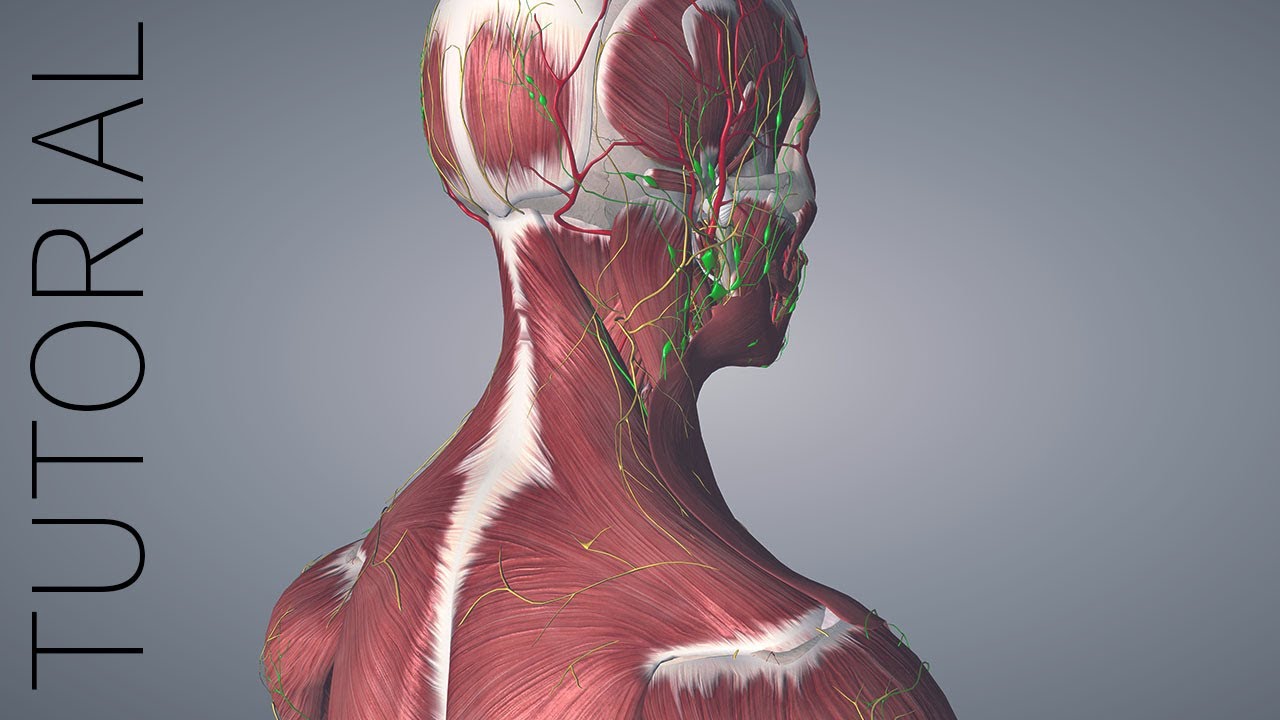
Getting Started with Essential Anatomy 5 - YouTube
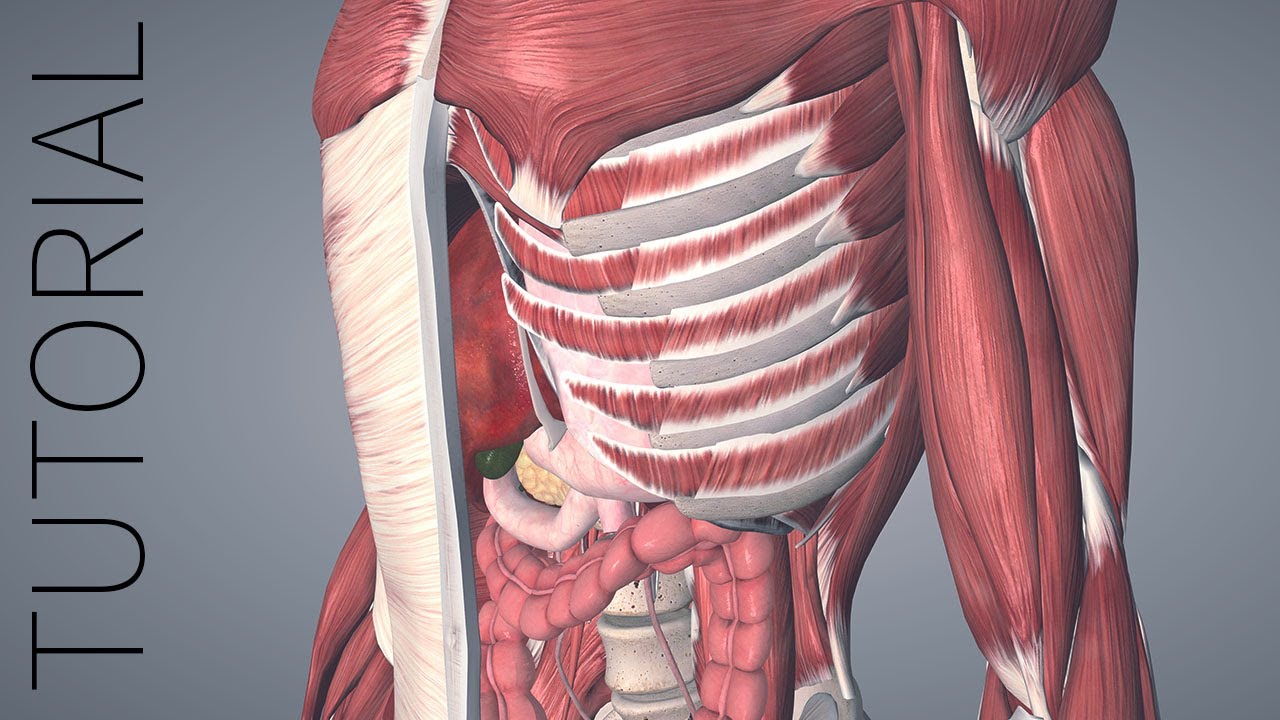
Multiple Selection - Essential Anatomy 5 Tutorial - YouTube
Essential Anatomy พื้นฐานที่จำเป็นเกี่ยวกับกายวิภาคศาสตร์ - CAMPHUB
Essential Anatomy - Extract from my Online Course #anatomydrawing #figureanatomy #drawingcourses ...