Why Your Nursing Logbook Actually Matters
Most people treat the nursing logbook as a bureaucratic box-checking exercise. They're not entirely wrong. But the logbook is also the most useful document you'll keep from nursing school into your career, and knowing how to use it properly separates people who get through residency smoothly from the ones who spend three weeks panic-documenting patient encounters before their preceptor shows up. I've seen students hand in logbooks that read like grocery lists. "Patient with pneumonia. Gave meds. Vitals stable." That's not documentation. That's a note you'd write for yourself and then forget within an hour. A proper logbook entry needs enough detail that someone else reading it six months later can reconstruct what actually happened, why decisions were made, and what the outcome was. Start with that mindset and everything else gets easier.
Essential Nursing Logbook: What It Should Actually Contain
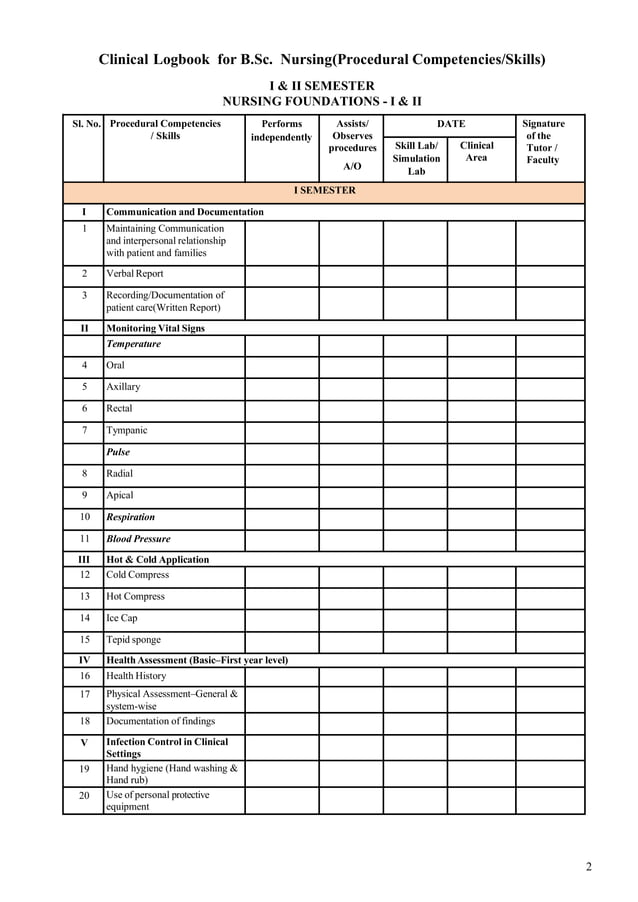
The core of an Essential Nursing Logbook breaks down into a few sections. Patient identifiers and encounter details come first — date, time, diagnosis, and setting. Then the nursing interventions, medications administered with doses and routes, assessments you performed, and any changes in condition. The critical part that most people skip is the reflection section. Write down what went wrong, what surprised you, what you'd do differently next time. That's the section that actually builds competence. I keep a simple template for every entry. Date and shift. Patient acuity level. Number of patients assigned. Procedures performed. Medications given. Patient education provided. Complications or concerns. Reflection notes. This took me about ninety seconds to fill out per shift after I stopped trying to make it literary. The trick is writing entries the same day, not at the end of the week. Memory fades fast. I learned this the hard way during my med-surg rotation when I realized I couldn't recall whether I'd given a specific antibiotic at 0800 or 0900 because I'd batch-written three days of entries on Sunday night. Accuracy matters more than completeness, and accuracy requires recency.
How to Build an Effective Logbook System
There are two approaches: digital or paper. Digital is faster to search and harder to lose. Paper is faster to write in during a busy shift and doesn't require battery life. I used a notebook for my clinicals and switched to a structured spreadsheet after graduation. The spreadsheet lets me filter by procedure type, diagnosis, or unit, which becomes valuable when you're compiling a skills checklist for graduation or job applications. Here's the system that actually works. After each shift, spend ten minutes going through your notes. Expand abbreviations. Add the reflection component. Check for completeness. Do this daily while the shift is fresh. A typical logbook entry for a standard medical-surgical shift runs about three to five minutes once you have the habit. If you're spending twenty minutes per shift, you're probably over-documenting or reorganizing too much. Trim it down. The counter-intuitive insight here is that a smaller, more frequent logging habit beats a large weekly session every single time. Your brain retains procedural memory and decision-making context far better when you capture it immediately. By the time Friday rolls around, the rationale behind your interventions has already dissolved. I've compared my entries from day-one versus day-five of the same clinical rotation, and the difference in quality is striking. Day-one entries have nuanced reasoning. Day-five entries are vague summaries that don't help anyone evaluate my actual clinical judgment.
Get the Full Details

Common Mistakes That Undermine Your Logbook
The biggest mistake is treating it as a punishment rather than a professional tool. If you write entries like you're filling out a form to get it over with, you're wasting your own time. The second biggest mistake is ignoring the reflection section entirely. That's where the learning happens. The third is inconsistency. Sporadic logbook keeping creates gaps that become problems during skills verification or when you need documentation for a competency review. Another issue I see repeatedly is the failure to document complications or near-misses. Students tend to skip entries for difficult patients or mistakes because they feel ashamed. Don't. Documenting a medication error you caught before it reached the patient and the corrective action you took is actually stronger evidence of clinical growth than documenting a perfect shift. The preceptors and instructors who matter want to see that you can recognize and process mistakes, not that you never make any. I once had a student who omitted an entire shift because a code blue happened and she felt she'd "failed." When we reviewed her logbook, that gap was the only thing that stood out negatively. She should have written about what she observed, what role she played, and what she learned from it. Instead, the blank space spoke louder than any entry ever could.
Edge Cases and Workarounds
ICU and emergency department placements create unique logbook challenges. Patient throughput is higher, acuity is extreme, and documentation requirements are heavier. You might see twelve patients in a twelve-hour shift, some of them brief. Logging every single encounter in detail becomes impractical. I developed a shorthand system for these settings. For each patient, I recorded only the key intervention, critical assessment finding, and outcome. This reduced my logging time from forty-five minutes post-shift to roughly fifteen minutes while preserving the essential clinical information. Pediatric and psychiatric units present another edge case. In pediatrics, parental education becomes a significant portion of your nursing interventions. If you don't explicitly document what you taught the family and how they responded, your logbook will miss an entire category of clinical work. In psychiatric nursing, the interventions are often communication-based rather than procedure-based, which makes them harder to quantify in a traditional log format. I found that recording the therapeutic communication techniques used, the patient's response, and any risk assessments performed gave me enough structure without forcing mental health nursing into a procedural box where it doesn't fit.
Limits and When This System Fails
No logbook system covers everything. If you're rotating through multiple short placements, the overhead of maintaining separate entries for each unit can become burdensome. In those cases, a single running document with clear unit labels is more practical than separate binders or spreadsheets. If your program requires specific formatting for accreditation purposes, adapt the system to meet those requirements rather than fighting them. The content matters more than the container. The logbook also cannot substitute for real clinical experience. Writing about a skill you observed someone else perform does not make you competent at that skill. The logbook documents experience; it doesn't replace it. Similarly, if you're using a logbook for credentialing or licensing purposes, check the specific requirements of your board or institution beforehand. Some require minimum numbers of certain procedures, and your logbook is the evidence for those counts. Make sure your documentation style satisfies those audit requirements. If you want to download a starter template for your Essential Nursing Logbook, most nursing programs provide one through their clinical coordinators. If yours doesn't, a simple spreadsheet with columns for date, shift type, patient acuity, procedures, medications, assessments, complications, and reflections will cover the essentials. Start filling it in from day one. The version you submit at graduation will be infinitely more useful than the one you construct retrospectively in the final week.