
Working With Essential Pharmacology Planner
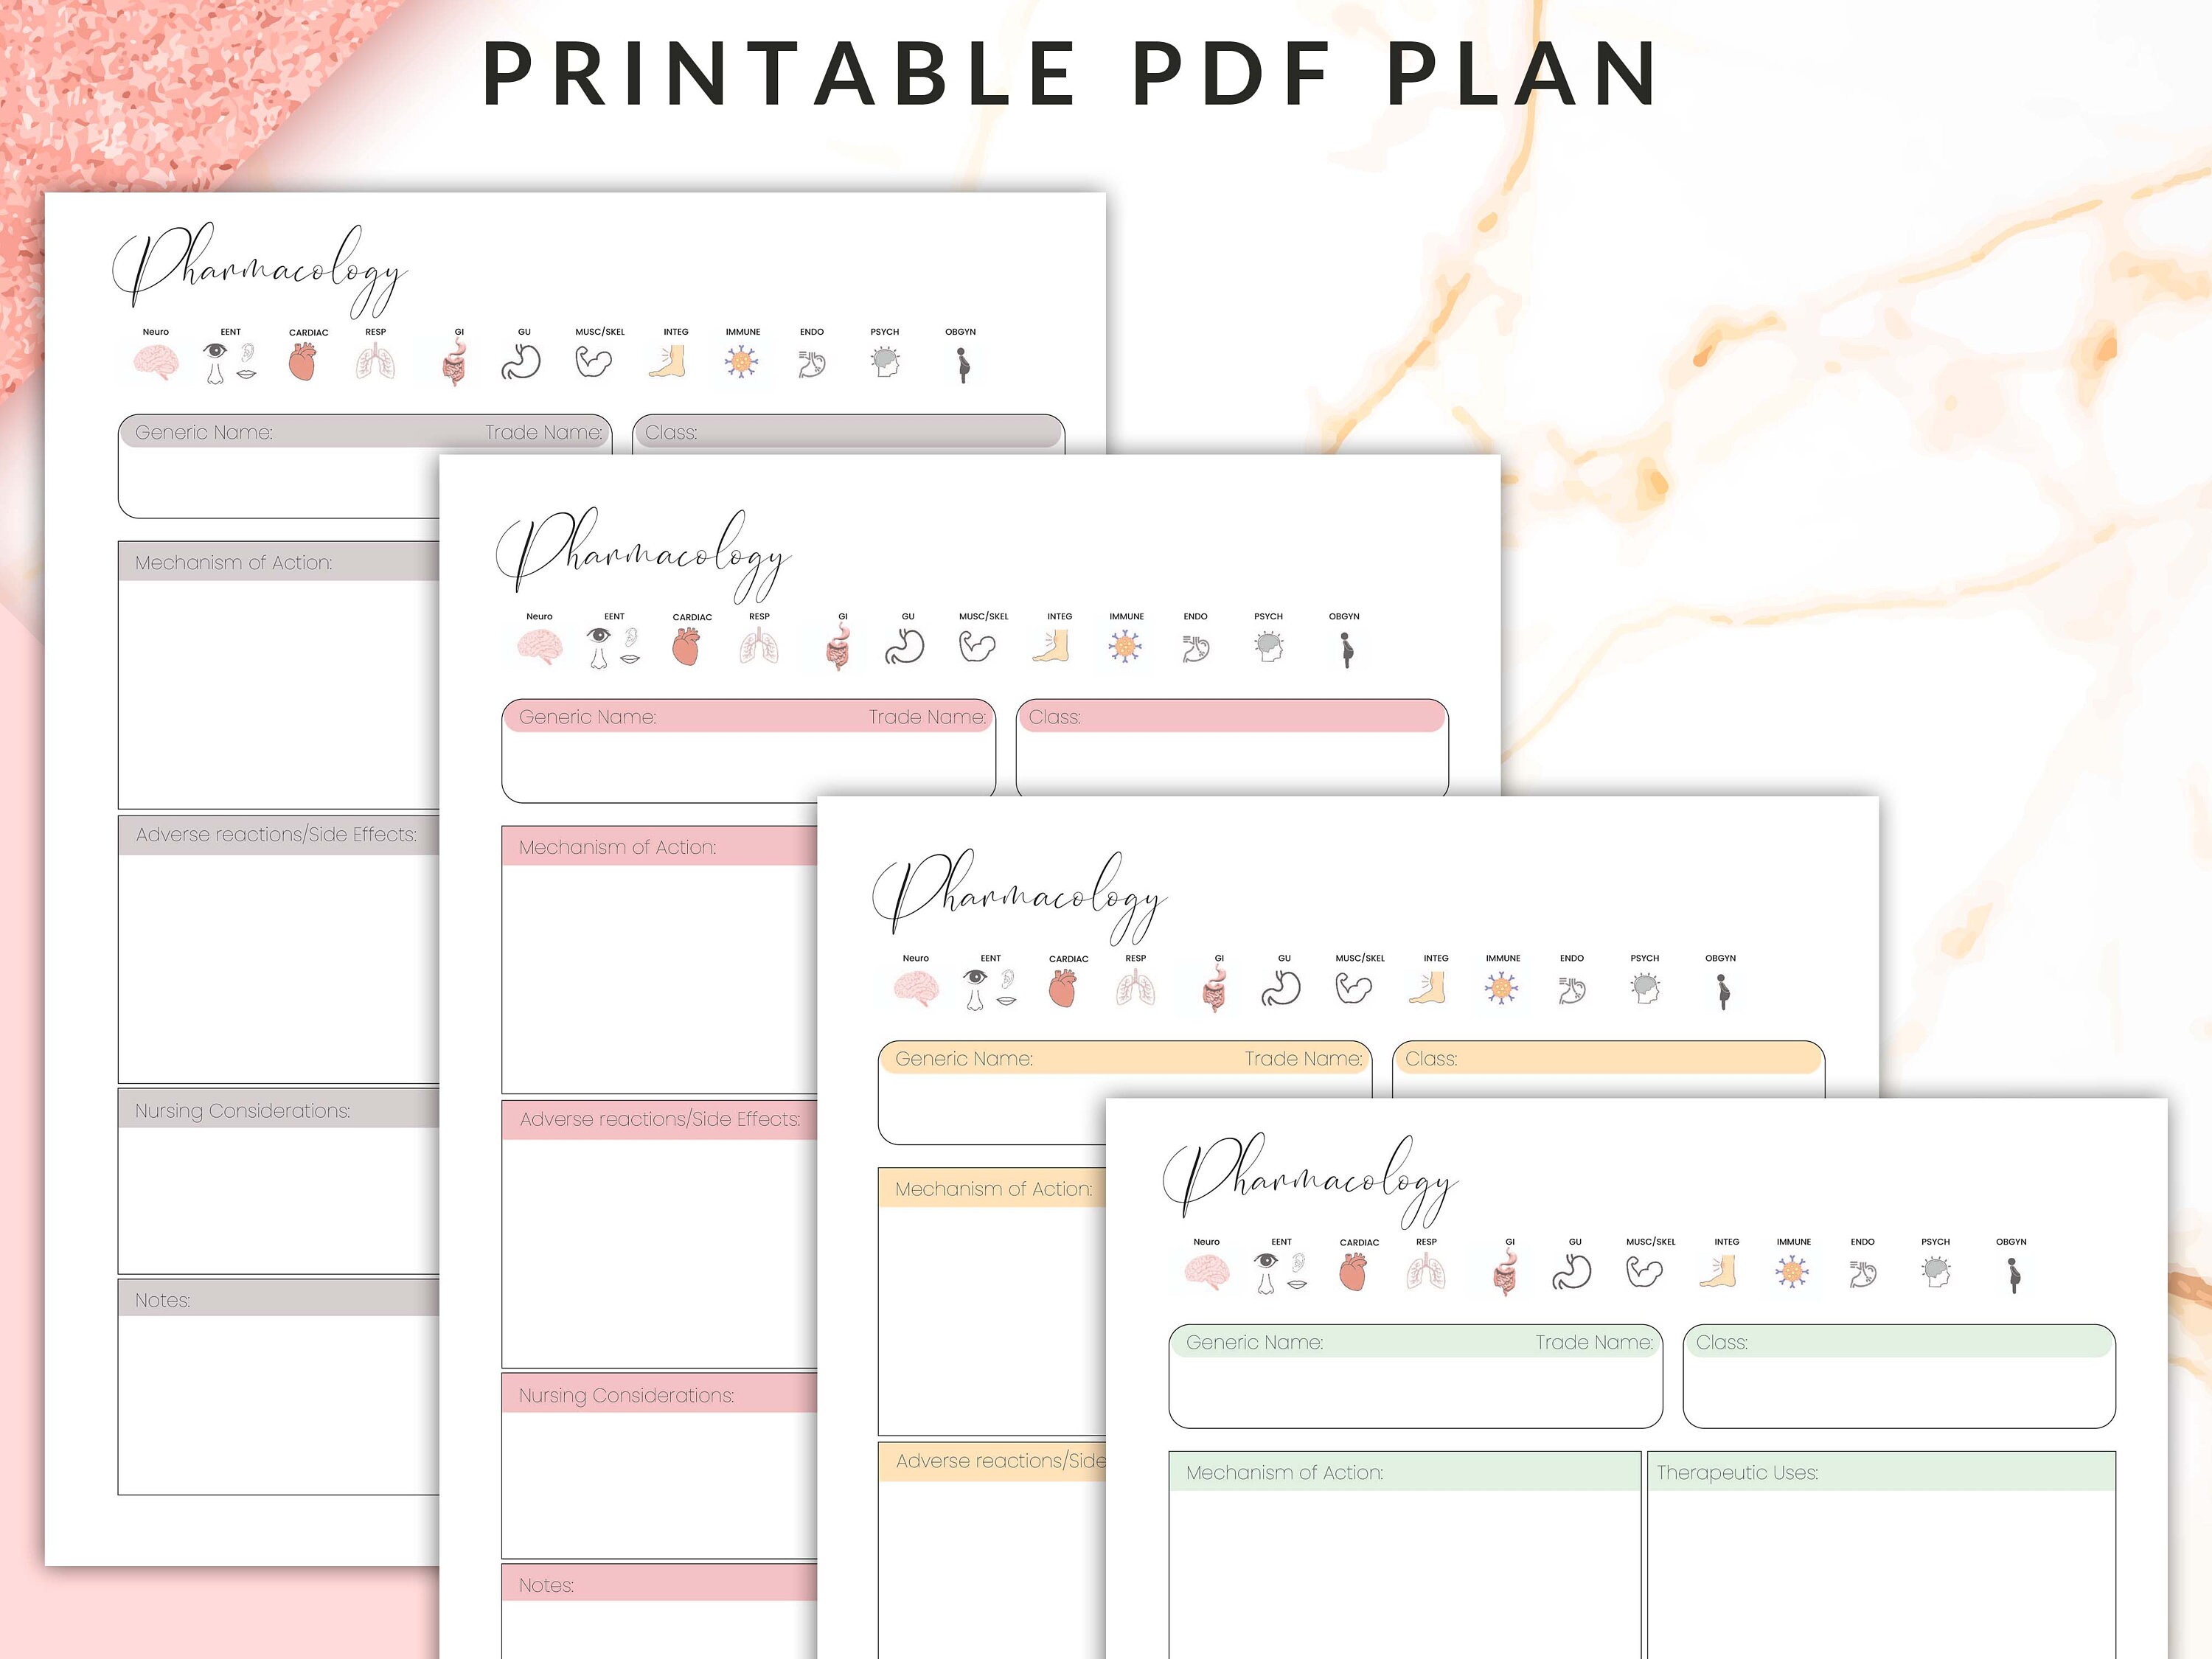
The Essential Pharmacology Planner is basically a structured scheduling and reference system designed around drug classes, mechanisms, and dosing protocols. I've used versions of it across pharmacology rotations, lab work, and clinical prep. It's not flashy. It's a spreadsheet or notebook framework with categories for pharmacokinetics, therapeutic indications, adverse effects, and drug interactions. Here is how it actually functions in practice. You pick a drug class and break it into its core components. Name, class, mechanism of action, primary indication, half-life, hepatic or renal clearance, common side effects, and significant interactions. You fill in the table, then cross-reference against your formulary or reference material. The planner forces you to be systematic. That is its main value.
Setting Up the Essential Pharmacology Planner
Start with a blank grid or document. Columns should include drug name, generic and brand, class, MOA, onset, peak, duration, elimination pathway, dose range, contraindications, and key interactions. Rows are individual agents. I keep five columns for monitoring parameters because that is where most mistakes happen during implementation. I organize by organ system first. Cardiovascular, renal, endocrine, CNS, infectious disease. Within each section, I sort by half-life and route of elimination. That ordering matters because it tells you immediately which drugs will accumulate in renal impairment or hepatic dysfunction. You do not need to look it up twice. One practical detail that most people skip: add a column for formulation availability. IV, oral, IM, subQ, transdermal. I learned this the hard way during a residency rotation when a patient needed a medication switched from IV to oral and the planner had no route column. I spent twenty minutes tracking down bioavailability data that should have been right there.
Using the Planner During Study or Clinical Workflow
When studying, you go drug by drug. Fill in every cell before moving to the next agent. Incomplete rows become blind spots on exams and in clinical practice. A missing elimination pathway means you will not recognize a dosing error when you see one. The planner only works if it is complete. During clinical work, the planner serves as a quick reference when new medications are ordered. You glance at the MOA column to confirm mechanism, check the interaction column for anything standing out, and verify renal or hepatic adjustments. It usually takes thirty to forty-five seconds per drug. That is faster than opening five different reference sites. The cross-referencing step is where most people underuse the tool. When you encounter a new drug, scan your existing entries for that same mechanism or class. If metformin is already listed under biguanides, adding empagliflozin beside it highlights the SGLT2 distinction immediately. Pattern recognition builds faster this way than memorizing each drug in isolation.
Get the Full Details
A Real Case Where the Planner Almost Failed Me
I ran into a problem with drugs that have active metabolites. Standard planners track the parent drug half-life. They do not always account for metabolites with significantly longer half-lives. I was managing a patient on morphine who had worsening sedation despite standard dosing. The planner showed morphine half-life at two to three hours. It did not flag morphine-6-glucuronide, which has a half-life of four to six hours and accumulates in renal impairment. My workaround was simple but not obvious upfront. I added a sub-column under elimination for active metabolites, including their names, half-lives, and accumulation risk. I color-coded any drug where the metabolite half-life exceeded the parent by more than double. That warning system prevented at least two dosing errors in my next quarter of clinical work.
What the Planner Does Not Handle Well
It does not handle dynamic information. Dosing guidelines change. Black box warnings get added. The planner becomes outdated unless you set a review schedule. I recommend updating entries monthly during active study periods and quarterly once you move into practice. Static planners are worse than no planner because outdated information creates false confidence. Another limitation is scope. The planner works well for core pharmacology. It breaks down for highly specialized areas like oncology agents, biologics, and research compounds. Those categories have too many exceptions and rapidly evolving protocols. For those, a separate reference system is necessary. Trying to force everything into one planner creates clutter and reduces usability. If you are a student preparing for board exams, the Essential Pharmacology Planner is worth the initial time investment. Expect to spend three to four hours building your first complete version covering the major drug classes. After that, maintaining it takes about twenty minutes per week. The return on time spent is real, but only if you actually fill every row and update regularly.
The tool itself is straightforward enough that you can build one from scratch. Several online templates exist if you prefer a pre-formatted starting point. The structure matters more than the platform. A printed notebook works as well as a digital spreadsheet. The critical factor is consistency in how you fill and review the entries.




