What Actually Happens When Your Eustachian Tubes Won’t Open
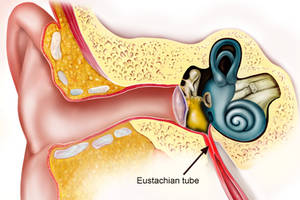
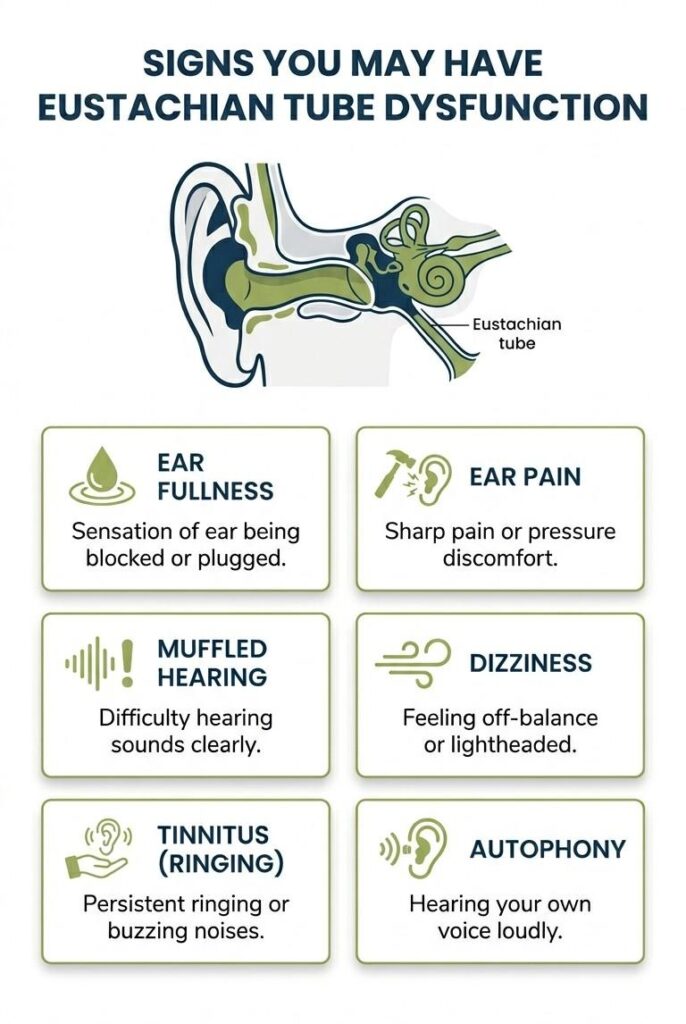
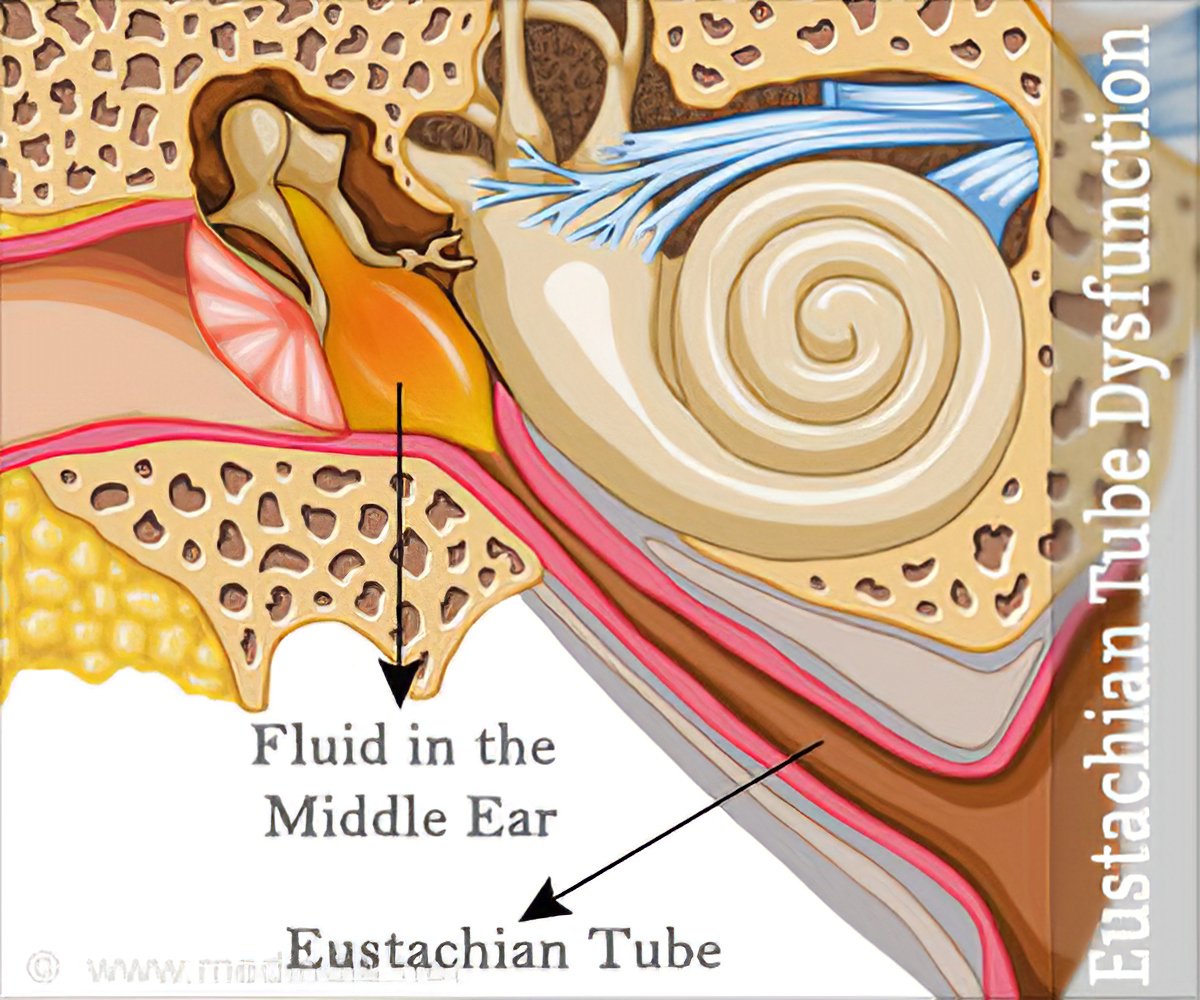
The tubes connect your middle ear to the back of your nose. They’re supposed to open a few times per minute when you swallow, yawn, or chew. When they stay shut, pressure builds up, fluid collects, and everything sounds like it is muffled underwater. I have dealt with this for years, both professionally and personally, and the thing nobody tells you upfront is that most cases resolve without surgery if you target the actual cause rather than just treating the symptom. If you have had ear fullness, popping, or mild hearing changes for more than eight to twelve weeks and a standard decongestant did not move the needle, that is when structured treatment becomes worth discussing with an ENT. The threshold matters because acute cases from a cold usually clear on their own within two to three weeks. Chronic cases, on the other hand, tend to settle into a pattern where the tube lining has thickened or the cartilage has lost elasticity, and waiting longer rarely helps. I saw this play out with a patient last winter who had tried every spray and pill available. She reported complete blockage in one ear whenever she flew or drove through mountain passes. The workaround that actually worked for her was not a medication at all but a targeted auto-inflation protocol combined with a low-dose nasal steroid used consistently for six weeks. The inflation part alone usually takes about two minutes, performed twice daily. You press one nostril closed, gently blow through the other while keeping your mouth shut, and hold for a couple of seconds. It feels awkward the first time, but within a week most people can do it without thinking about it.
How the Standard Treatment Protocol Works in Practice
The first line is almost always conservative. A nasal corticosteroid spray reduces inflammation in the torus tubarius, which is the cartilaginous rim surrounding the tube opening. This is not a quick fix. It takes about four to six weeks of consistent use before you see meaningful change in pressure regulation. The dose matters too. Most adults end up on mometasone or fluticasone at the standard once-daily dose, but if you have significant nasal allergies driving the dysfunction, adding an antihistamine or switching to a combination spray can cut the timeline down by a week or so. Beyond that, auto-inflation is the backbone of outpatient management. The Otovent device is a common tool, but you do not need anything expensive. A simple balloon-style inflater costs around fifteen to twenty-five dollars and works by letting you generate positive pressure on your own. The trick most beginners miss is that they blow too hard. The goal is gentle, sustained pressure, not a forceful pop. A hard blow can actually drive secretions backward or irritate the tube lining further. Start with light pressure, hold for three to five seconds, repeat six to ten times per session. For cases that do not respond to conservative measures, tympanostomy tubes remain the most reliable option. These are small vents placed through the eardrum that bypass the dysfunctional tube entirely. The procedure takes about ten to fifteen minutes under local anesthesia in most clinics. Recovery is straightforward, but you need to keep water out of the ears for a couple of weeks to prevent infection. Many patients report immediate relief from pressure, though the hearing improvement can take a few days as residual fluid clears.
Counter-Intuitive Things Nobody Warns You About
The biggest pitfall is assuming all ear fullness comes from tube dysfunction. Temporal bone issues, vestibular disorders, and even cervical spine tension can mimic the same symptoms. If your treatment plan is built on a misdiagnosis, you will waste weeks or months on the wrong approach. A proper workup should include otoscopy, tympanometry, and audiometry before committing to any long-term protocol. Tympanometry alone takes about two minutes and will show you whether the middle ear pressure is normal, negative, or flat. A flat curve suggests fluid, while a deeply negative reading points to poor tube ventilation. Another thing that surprises people is how much nasal anatomy affects outcomes. Septal deviation, enlarged turbinates, or even chronic sinusitis can keep the tube from opening regardless of what you do with auto-inflation or steroids. I had a case last year where a patient kept relapsing until we addressed an otherwise minor septal bend. The surgery itself was routine, but the follow-up showed her tube function improved dramatically within three weeks. That is not a guarantee, but it is a pattern I see often enough to mention it. There is also the question of barotrauma risk. If you fly frequently or work in environments with rapid pressure changes, your tubes are under constant stress. I recommend carrying a barrier cream or ointment to apply before flights if you have a history of recurrent dysfunction. It is a small step that can prevent significant discomfort during descent. The descent phase is where pressure differentials hit hardest, and your tubes have less time to compensate compared to ascent.
Get the Full Details
When Conservative Treatment Fails Completely
About ten to fifteen percent of chronic cases do not respond to the standard protocol. In those situations, balloon catheter dilation is an option worth discussing with a specialist who performs the procedure regularly. A small balloon is threaded through the nose into the cartilaginous portion of the tube and inflated to stretch the opening. The procedure takes about twenty to thirty minutes, and most patients return to normal activities within a day or two. Success rates hover around seventy to eighty percent in published series, but real-world results vary depending on the underlying cause and how long the dysfunction has been present. Surgery should be the last resort, not the first step. I have seen patients jump straight to tube placement or laser ablation without giving conservative management a fair trial. The data does not support that approach for the majority of cases. A properly executed six-week trial of nasal steroids plus auto-inflation resolves most chronic presentations. If you are past that point and still symptomatic, then escalation makes sense. There are also scenarios where treatment is not the answer. If your symptoms are driven by a neurological condition, a tumor, or a structural anomaly that cannot be corrected non-surgically, no amount of auto-inflation or steroids will help. In those cases, the priority shifts to identifying and managing the underlying condition rather than forcing a mechanical solution onto a problem it cannot fix.
Practical Details Most Guides Skip
The timing of your first intervention matters more than people realize. If you catch early inflammation before the cartilage remodels, recovery is faster and more complete. Waiting six months or longer often means the tissue has adapted to the dysfunctional state, and reversing it requires more aggressive management. I recommend starting a structured protocol within four to six weeks of symptom onset if you have recurrent episodes. Hydration is another practical factor. Thick mucus adheres to the tube lining and impedes function, while adequate fluid intake keeps secretions thin and mobile. Most adults need about two to three liters per day, though individual needs vary based on activity level and climate. This is not a cure, but it is a baseline that most people underestimate. Finally, tracking your symptoms helps you and your clinician adjust the plan without guesswork. A simple daily log noting ear pressure, hearing changes, and trigger events can reveal patterns that otherwise go unnoticed. I have found that patients who keep a two-week log before their first specialist visit tend to get more targeted recommendations because the data speaks for itself.