The Initial Assessment Nobody Does Right
Most people think a physical therapy evaluation is just filling out a form and checking range of motion. That is not what happens in practice. The evaluation is the entire foundation of the treatment plan, and when it is rushed or done incorrectly, the rest of the therapy stalls out within three weeks. I have watched PTs spend forty-five minutes on goniometry and then skip the functional movement screen because they were behind on charts. That is a bad trade. The numbers from a handheld goniometer mean very little if the patient cannot execute a basic squat pattern without compensating at the lumbar spine. Start with function. Then measure.
What You Are Actually Looking For During Evaluation Physical Therapy
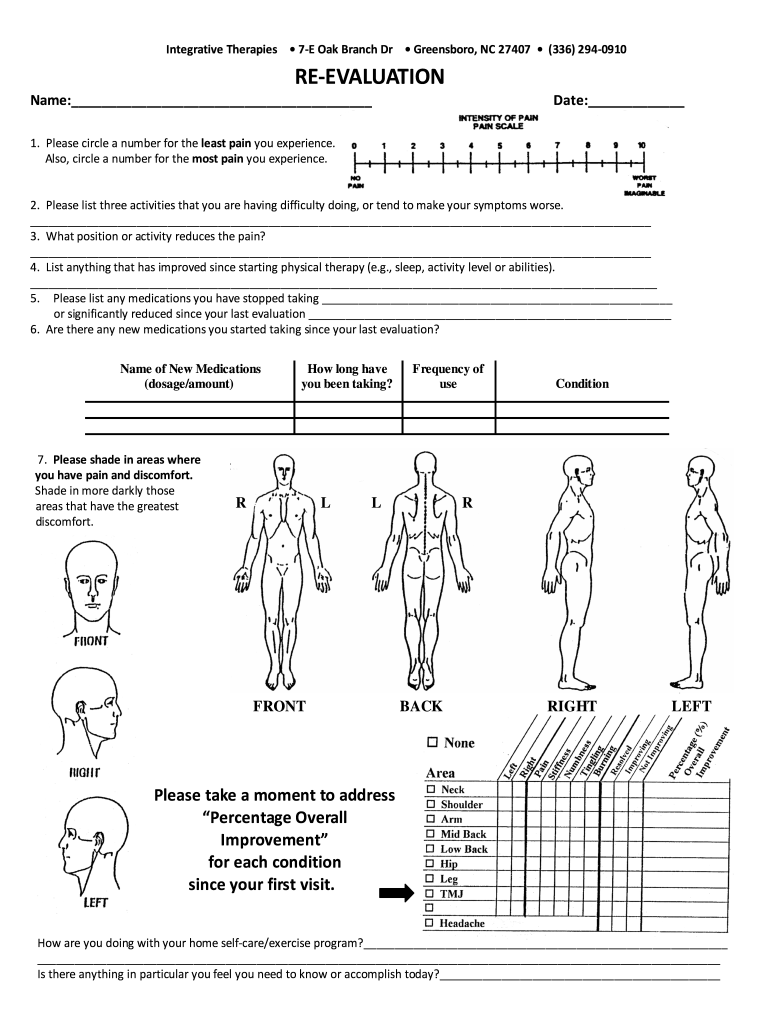
The standard components are the subjective interview, observational analysis, palpation, special tests, and objective measurement. But the order matters more than most clinicians admit. Here is how I run it. First, the subjective portion. This is where you spend time asking about the mechanism of injury, which is not always as clear as it sounds. A patient will tell you they hurt their back lifting a box. The real question is what position their trunk was in, whether they rotated while load bearing, and what their symptom distribution was during and after the event. I ask them to draw me the pain on a body map. It sounds basic. It catches patterns you would otherwise miss. Radicular symptoms often trace paths that do not match any single dermatome cleanly because the irritation is at the nerve root but the referral follows myotomal and sclerotomal patterns as well. Next, I move to observation before I touch the patient. Standing posture, gait into the room, the way they sit down. I watch the transverse plane rotation during ambulation. Most evaluators skip this entirely and go straight to supine testing. A patient who cannot safely lower themselves to a chair without using their hands is not ready for a hamstring flexibility test. Prioritize what matters for function first.
Palpation comes after observation. Temperature changes, tissue texture, specific tenderness. I do not press hard just to find pain. Pressing hard on everything gives you noise. I look for focal point tenderness over known structures first, then expand my search if the clinical picture does not fit yet. The special tests section is where things get interesting. And where most people go wrong. A positive special test is not a diagnosis. It is a probability indicator. The SLR test has high sensitivity for disc issues but low specificity. That means a positive result tells you disc involvement is possible but not certain. A negative result is actually more useful in most cases because the sensitivity is good. Clinchers like the Slump test add specificity when combined with the SLR. Using a battery of three tests with varying sensitivity and specificity profiles is better than relying on any single one. I encountered a specific edge case a couple years ago that illustrates why the standard approach sometimes fails. A patient presented with lateral knee pain that reproduced on Ober’s test and had tight IT band signs across the board. Everyone assumed IT band syndrome. I treated the hip abductors andiliotibial band for six sessions with minimal change. The workaround came from going back to the evaluation. I noticed the patient had a slight genu varum posture and excessive subtalar pronation on single leg stance. The lateral knee pain was not the IT band at all. It was referred from the L5 nerve root, and the hip findings were secondary compensation for altered lower extremity mechanics. I re-evaluated the lumbar spine with seated rotation and extended prism positioning, and yes, the disc provocation tests came positive. The treatment plan shifted entirely from soft tissue work to centralizing neurological irritability. It took three sessions of directional preference work before the lateral knee pain dropped from seven out of ten to two out of ten.
Get the Full Details

That case is not rare. It is just overlooked because the evaluation stopped at the obvious structure.
Counter-Intuitive Things I Have Learned
Range of motion numbers can be misleading in ways that are not obvious. End feel classification matters more than the degree of motion. A patient might have full knee extension numerically but with a hard, bony end feel that indicates joint capsule restriction versus normal ligamentous end feel. The number looks identical on paper. The tissue quality difference changes everything about prognosis and treatment approach. Another thing beginners consistently miss is that muscle strength testing should happen after fatigue-inducing movements, not before. If you test manual muscle grading first and then have the patient perform repeated squats, the strength scores are irrelevant. The nervous system has already taxed itself. I always test strength in the fresh state, then use functional movement patterns to see how that strength translates under load and fatigue. The gap between the two states is where the real impairment lives. There are also scenarios where a formal evaluation simply cannot proceed effectively. Patients with severe cognitive impairment, acute psychiatric episodes, or uncontrolled pain that prevents any movement assessment fall into this category. In those cases, pushing through the standard protocol generates bad data. The workaround is modified subjective evaluation only, gathering information from collateral sources, and deferring the hands-on portion until the patient is stabilized medically or pharmacologically.
Documentation is another area where shortcuts create real problems. The CMS guidelines and insurance reviewers want to see measurable goals established at the initial evaluation, not vague statements like patient will improve function. Goals need to be quantified with baseline numbers and target numbers. If your baseline single leg squat score is two out of ten due to pain, the goal should reference a specific improvement, like reaching a six out of ten by session ten. Without that specificity, your plan of care is vulnerable to review denial. The evaluation phase typically takes between forty-five and ninety minutes for a new patient depending on complexity. If you are finishing in under thirty minutes consistently, you are probably skipping steps. The tradeoff is that a thorough initial evaluation usually reduces total treatment sessions by three to five visits on average because the treatment plan targets the actual impairment rather than guesswork. There is no shortcut download or software that replaces this process. Any tool claiming to automate physical therapy evaluation is generating templates, not clinical reasoning. The evaluation is a thinking process, not a data entry exercise.