What Actually Happens During a Pap Smear Exam
The speculum goes in, you see the cervix, and then you scrape it. That's the short version. The longer version is where things get complicated, and where most people who have never done this before struggle. I'm going to walk through the mechanics, the mistakes I see constantly, and the things that aren't in the patient handout.
Exam During Pap Smear: Positioning and Visual Access
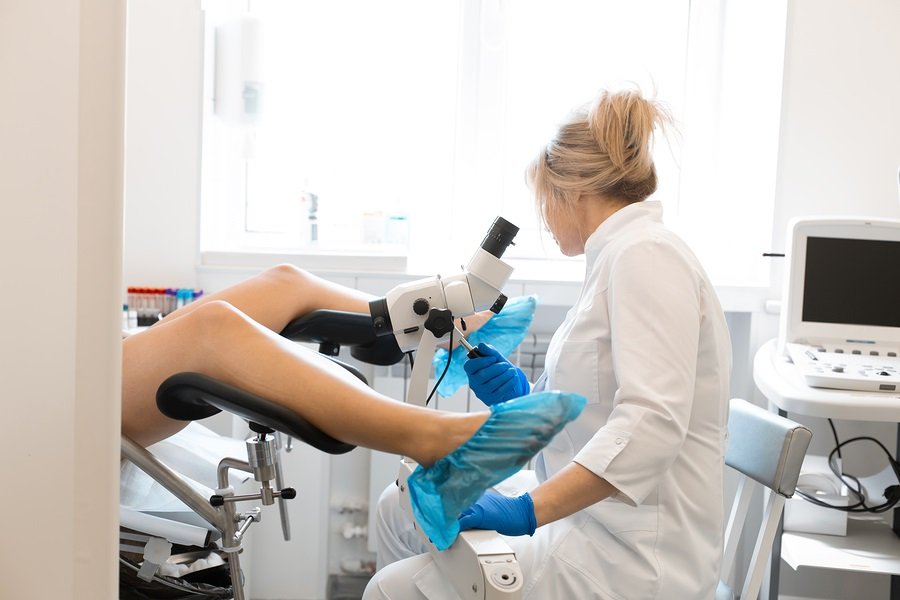
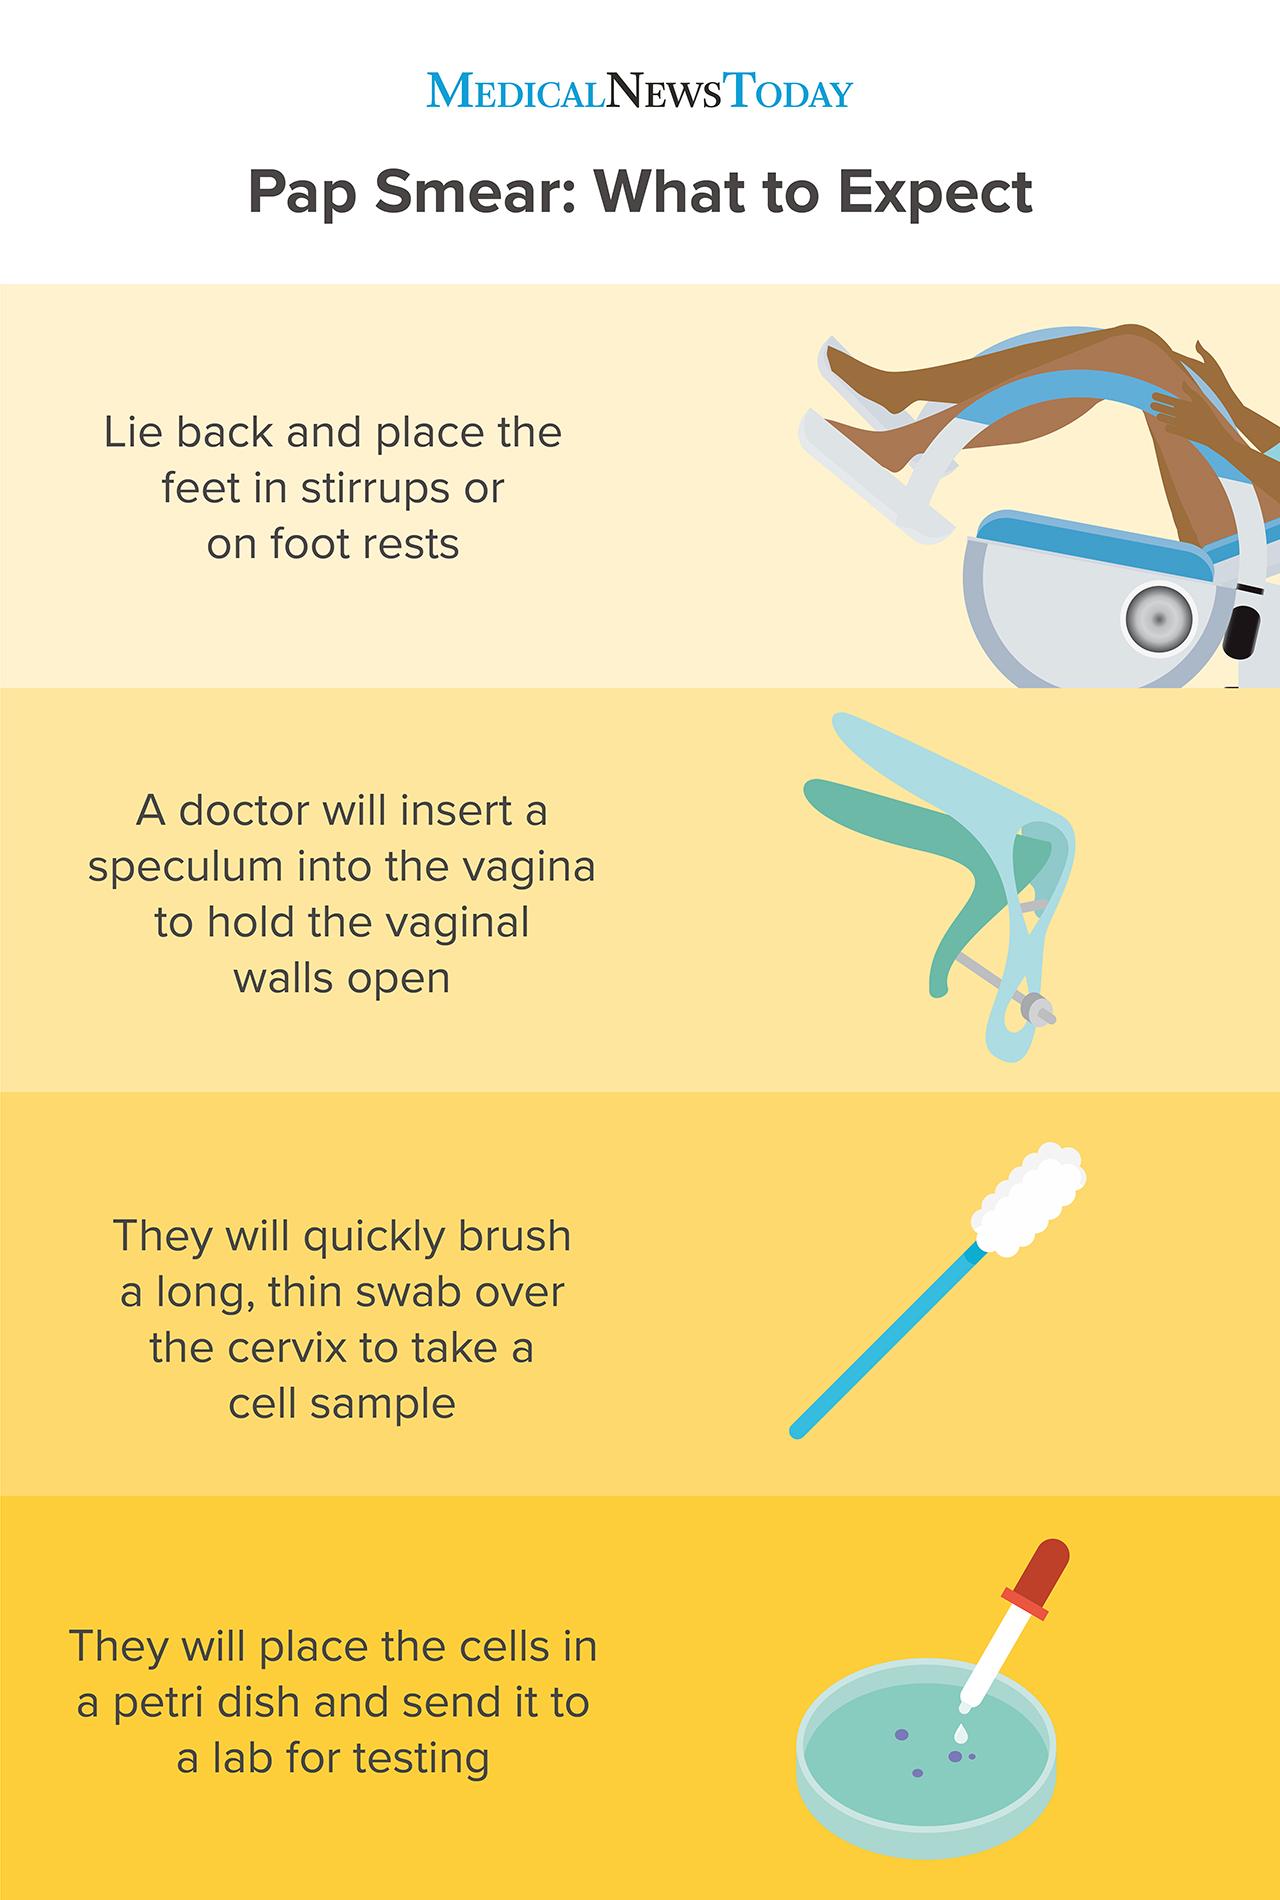
You start with the patient in lithotomy, feet in stirrups, hips at the edge of the table. If the table is too high they tense up. Too low and your wrists angle uncomfortably. Most exam tables settle somewhere around hip height for the clinician, but every room is different. I adjust before I even open the speculum. The speculum choice matters more than people realize. A narrow speculum works for patients with less vaginal laxity or those who report pain. A Graves speculum gives better visualization of the ectocervix. The Sims is for posterior wall access, which you rarely need for a routine Pap, but I keep one nearby because anatomy varies and sometimes the cervix sits lower or more posterior than expected. Insertion technique: close the blades, apply water-based lubricant to the tip only, not the shaft. Compress the labia apart with your non-dominant hand, angle the speculum at roughly 45 degrees downward toward the sacrum, not straight in. You're following the vaginal axis. It meets a bit of resistance at the introitus from the perineal body. Gentle pressure, ask the patient to bear down if they're tight, and advance until the external os is visible.
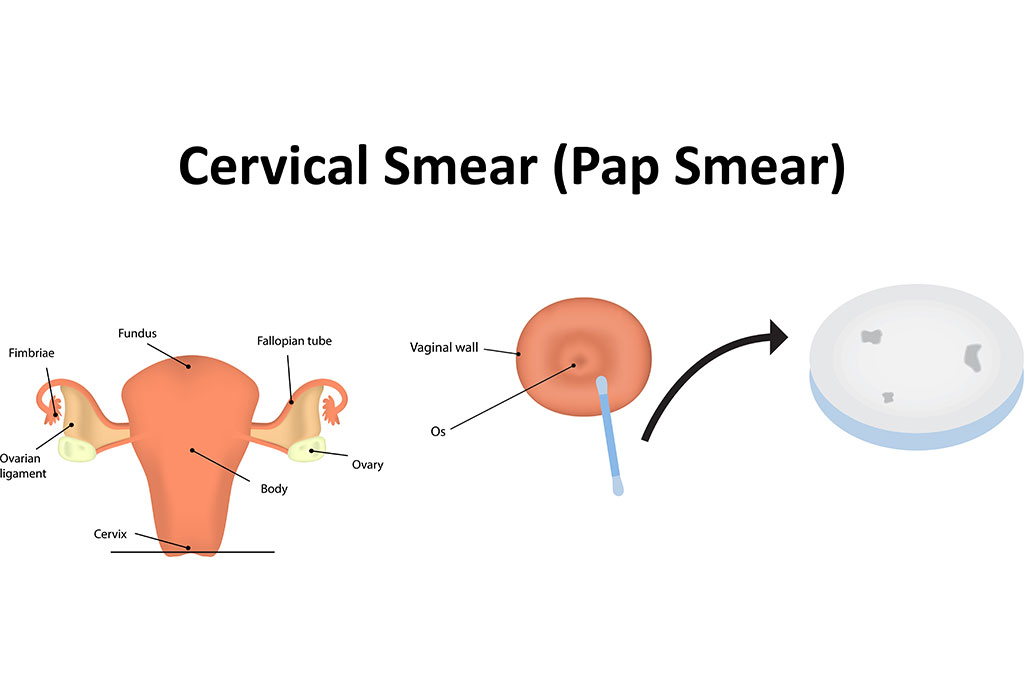
Once the cervix is in view, open the blades slowly. If you can't see the squamocolumnar junction, you're not going to get a useful sample. Rotate the speculum slightly or adjust the. I've had cases where a small amount of mucus or blood was obscuring the transformation zone, and simply waiting 30 seconds for the cervix to settle after blade insertion cleared the view.
Get the Full Details
Sample Collection: The Actual Mechanism
There are two main collection tools. The cytobrush for the endocervical canal and the spatula or broom device for the ectocervix. The old L-combo device combines both, but the single-use broom devices have largely replaced them because they reduce cross-contamination between the endocervical and ectocervical components. The technique with a broom device: insert the central prongs into the endocervical os, rotate the entire device 360 degrees against the os and canal walls for about 10 seconds, then pull it out and swipe it across the ectocervix. One motion. Don't separate the steps or you lose cellular integrity. With a cytobrush alone: insert the bristles into the canal about 1 centimeter, rotate 90 to 180 degrees, and withdraw. The brush should come out with a slight pink tint from capillary bleeding. If it's completely bloodless, you might not have reached the active transformation zone. If it's heavily bloody, the sample may be compromised for liquid-based cytology. I've seen samples rejected more than once because the blood content exceeded the acceptable threshold for ThinPrep processing.
Now the fixative. If you're using liquid-based cytology, which is the standard in most US labs now, you rinse the brush or broom immediately into the vial. Flick it against the sides to dislodge cells, cap it, and vortex or shake for 10 seconds. Direct smears, the old school method where you paint the slide immediately, are less common but still used in some settings. They require more skill to avoid air-drying artifacts, and I've watched technicians waste slides because the smear was too thick and the cells overlapped beyond readability.
Common Pitfalls That Ruin Results
The #1 reason for inadequate samples: missing the transformation zone. If the patient is perimenopausal or postmenopausal, the squamocolumnar junction migrates up into the endocervical canal. A standard ectocervical scrape will miss it entirely. In those cases, I extend the brush deeper into the canal and sample more thoroughly. Some clinicians use an endobrush for this, which is specifically designed for endocervical sampling when the SCJ isn't visible. The #2 mistake I see: contaminating the sample with lubricant. Regular K-Y jelly and many personal lubricants contain spermicides or other agents that interfere with slide preparation. Only use water-soluble, non-spermicidal lubricant on the speculum, and only on the very tip. If you get lubricant on the cervix itself, you need to wipe it away with saline before sampling, or the lab may flag the specimen. A third issue is sampling during heavy menstruation. Blood dilutes the cellular sample and obscures interpretation. It doesn't always make the sample unreadable, but it increases the likelihood of an unsatisfactory result. I schedule Pap smears for the window between days 10 and 20 of the menstrual cycle when possible, and I tell patients to call if their period starts unexpectedly on appointment day so we can reschedule rather than waste a visit.

I also encountered a case once where a patient had a cervical stenosis from prior cone biopsy, and I literally could not advance the brush past the external os. The sample came back negative for ectocervical cells but showed nothing from the canal. I noted the stenosis in the requisition, and the lab processed it as such. The takeaway: document anatomical variations on the lab form. The pathologist needs to know why the endocervical component is absent so they don't flag it as inadequate without context.
After the Sample Is Collected
Close the speculum blades before withdrawing. You don't want to scrape the vaginal wall on the way out. Remove the speculum, dispose of it if it's single-use, and have the patient rest for a minute before sitting up. Light spotting is normal. Advise them that a small amount of brownish discharge is expected as the fixative and any minor bleeding exits over the next day or two. Label the vial at the bedside. Patient name, MRN, date, time of collection, and your initials. Put the requisition form details clearly: last menstrual period, reason for screening, prior abnormal results, HPV co-testing status. The lab can't work with vague paperwork, and rushed labeling is how samples get mismatched.
What the Lab Actually Looks At
When the slide or vial arrives, the cytotechnologist screens for abnormal squamous cells, glandular cells, and any other pathology. The reporting system is the Bethesda System. You'll see terms like NILM, ASC-US, LSIL, HSIL, AGC, and so on. If the sample is satisfactory for evaluation but doesn't meet minimum cellular criteria, it's flagged as satisfactory but limited. The patient gets a recall interval, usually three months, depending on the reason. For liquid-based prep, the machine spreads the cells in a thin, uniform layer. Less blood and mucus obscuring the view. For conventional smears, the tech has to read through overlapping cells and sometimes discard parts of the slide. Both methods have comparable sensitivity when performed correctly, but liquid-based has become the dominant standard because it produces more consistent slides and leaves residual fluid for HPV testing if needed.
HPV Co-Testing and Risk-Based Management
If you're doing HPV co-testing alongside the Pap, the same broom or brush specimen is used for both. The vial already contains the preservative fluid. The lab separates the cellular sample from the fluid. The fluid goes to PCR for HPV DNA or mRNA detection. The cellular component goes to cytology review. You don't need a second sample. This matters because some patients assume two swabs are taken when co-testing is ordered, and explaining that upfront reduces anxiety. The screening guidelines have shifted toward risk-based management. A negative Pap with negative HPV at age 30 pushes the next screen to five years. HPV-positive with a negative Pap means a one-year follow-up, not an immediate colposcopy, unless the HPV type is 16 or 18, which typically triggers direct referral. The algorithm isn't straightforward, and the nuances matter clinically. But that's the screening pathway, not the exam mechanics.
Hardware Considerations
There's no downloadable software for this procedure. It's a clinical skill. If you're looking for educational tools, most medical training programs use simulation models and video libraries. The ACOG has procedural videos. The ASCP offers cytology reference materials. What you won't find is a shortcut app or a replacement for hands-on practice under supervision. The physical supplies are straightforward: speculums (sizes 34mm and 28mm cover most patients), cytobrushes, endocervical brushes, broom devices, vials of preservative fluid, slides if doing conventional smear, fixation spray, and a speculum warmed to body temperature if the patient reports sensitivity. Cold metal in a cold room is an unnecessary source of vasospasm and discomfort. Some clinics use automated speculum insertion devices. They're available from a few medical suppliers, but the clinical consensus is mixed. The devices provide consistent depth, but they remove tactile feedback that experienced clinicians rely on. Most staff prefer manual insertion after the first few procedures. The learning curve for manual technique is about three to five supervised exams before confidence sets in.
Bottom Line
The exam itself is quick, maybe two to three minutes once you're proficient. The preparation and positioning take longer than the actual scraping. The biggest factor in getting a good sample isn't speed, it's understanding where the transformation zone is and making sure your tool reaches it without contamination. If you're new to this, do at least ten supervised procedures before you're comfortable solo. The first handful will feel awkward. That's normal. After that, it becomes routine.