Looking at Chromosome Spreads Under the Microscope
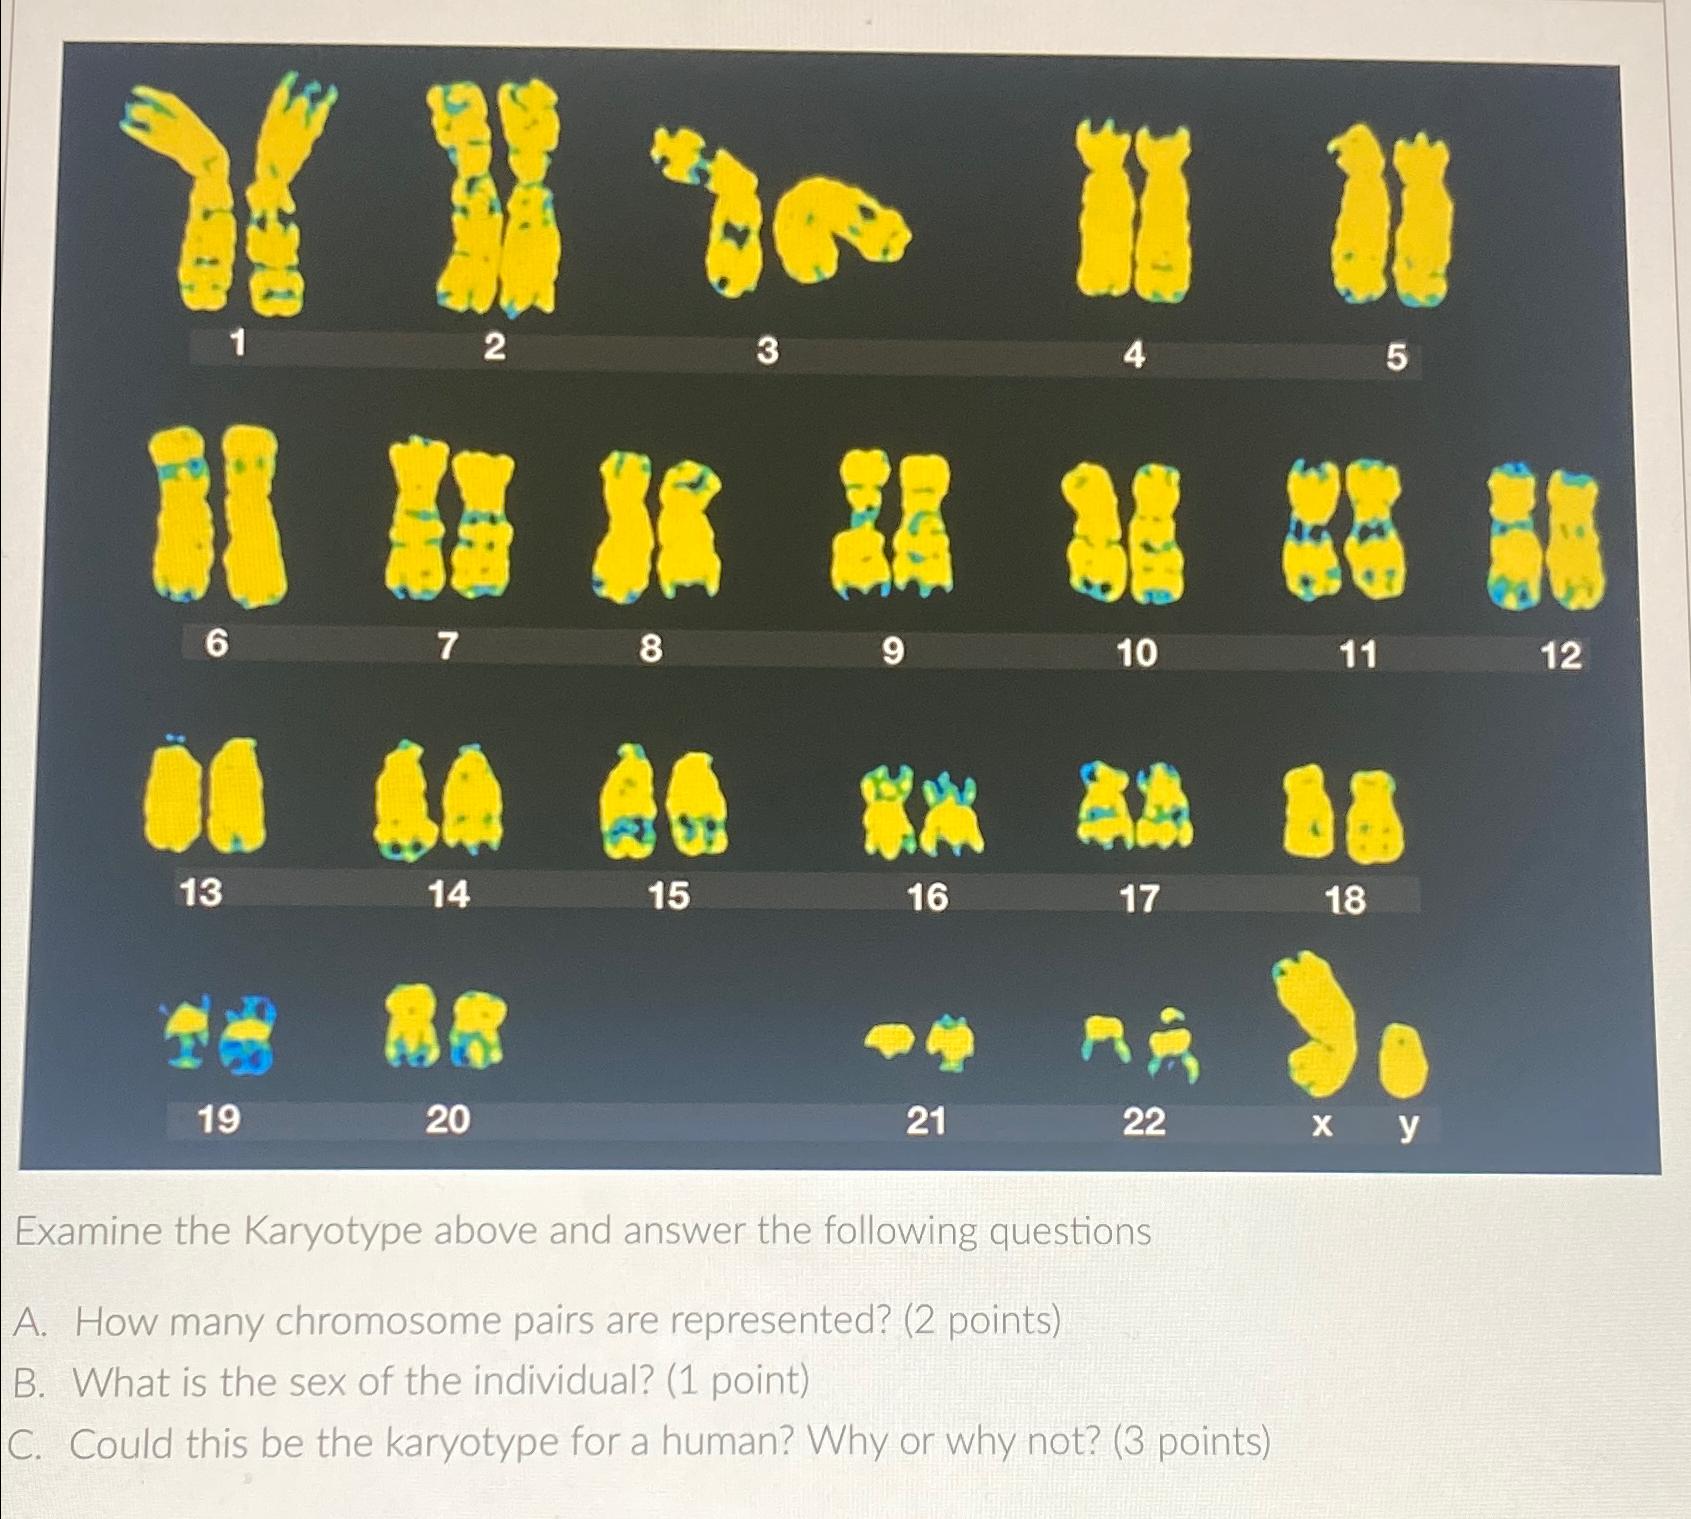
Karyotype analysis is one of those techniques that sounds straightforward until you actually have to do it. You take a cell sample, arrest it in metaphase, spread it on a slide, stain it, and look for 23 pairs of chromosomes. The idea is simple enough. The reality involves a lot more squinting, re-focusing, and dealing with messy spreads than most textbooks let on. When someone asks you to examine each karyotype and answer the questions, they are usually referring to a standard clinical or academic exercise where you need to identify chromosomal abnormalities from a prepared spread. The workflow goes through several stages. First, you verify that the metaphase cells are well-spread — not overlapping, not folded, and ideally showing clearly separated chromosomes. Then you scan for the number of chromosomes. A normal human karyotype has 46. Anything fewer or more raises immediate flags for aneuploidy or polyploidy. After counting, you arrange the chromosomes into their standard groups from largest to smallest, which is where the identification work really begins. The tricky part is not the counting. It is the identification under less-than-ideal conditions. Banding patterns matter. G-banding gives you light and dark bands along each chromosome arm, but the quality varies wildly depending on the banding protocol. I have seen slides where the bands were so faint you could barely distinguish chromosome 8 from chromosome 9. In those cases, you rely on centromere position and relative length. That works most of the time. It does not work when you are dealing with small structural rearrangements like microdeletions.
Here is something people do not always expect. Not every abnormality is visible at the resolution of a standard light microscope karyotype. If you are looking for a deletion smaller than about 5 to 10 megabases, you are likely going to miss it unless you are working with high-resolution bands or switching to a microarray. I ran into this directly when analyzing a patient's karyotype that looked entirely normal by conventional standards. Clinical symptoms strongly suggested a deletion on chromosome 4, so we pulled the sample back and ran FISH probes against that region. The deletion was there, right in the expected area, just invisible at standard metaphase resolution. Karyotyping is a powerful tool, but it has hard limits built into the physics of light microscopy.
Step-by-Step Process
Metaphase arrest comes first. You treat the cell culture with colcemid or colchicine to halt division at metaphase when chromosomes are most condensed. This typically takes between one and two hours depending on the cell type. The cells swell and chromosomes separate a bit more, which is actually helpful for spread quality. Next is hypotonic treatment. You immerse the cells in a low-salt solution, usually potassium chloride at 0.075 M, for about 15 to 20 minutes. This causes the cells to take up water and swell, which pushes the chromosomes apart. Overdo this step and the cells lyse completely. Underdo it and the chromosomes stay clumped together. I usually check a drop on a slide after ten minutes under low magnification to gauge whether the swelling looks adequate before committing to the full time. After that comes fixation. You add fresh fixative — three parts methanol to one part glacial acetic acid — slowly while gently mixing. You centrifuge and resuspend the pellet in fixative at least twice. This removes water and preserves the chromosome structure. Skipping the second fixation leaves residual salts that interfere with staining later on.
Get the Full Details

The slide dropping step is where spread quality is decided. You take a small drop of the cell suspension and let it fall from a height of about six to eight inches onto a clean, frosted glass slide. The impact spreads the cells. The humidity of the room matters more than most protocols mention. On humid days the drops spread too much and the chromosomes flatten into unrecognizable smears. On dry days they land compact and well-separated. I keep a small humidity chart on the bench and note the day's conditions next to every slide batch. It has saved me from spending hours trying to interpret a mess I could have prevented by just waiting for better weather or using a humidity-controlled room. Banding follows. G-banding uses trypsin digestion followed by Giemsa stain. The trick is getting the trypsin exposure time just right. Too short and the bands are pale. Too long and you lose the chromosomes entirely. Most labs use a stock trypsin solution and test a few drops on a scrap slide before committing the real sample. I time each trial in five-second increments and watch closely under the microscope. Once the slides are ready, analysis begins. You locate well-spread metaphase plates and capture images. Each chromosome pair gets numbered from one through 22, plus the sex chromosomes. You look for extra or missing chromosomes, large deletions, duplications, translocations, inversions, and ring chromosomes. The ISCN nomenclature is the standard way to report findings. It is precise but dense. A typical report line might read something like 46,XY,der(13)t(13;14)(q10;q10), which means a balanced translocation between chromosomes 13 and 14 involving the long arm regions near the centromeres.
Common Pitfalls
One of the most frequent mistakes beginners make is assuming that a normal karyotype means normal genetics. It does not. Karyotyping cannot detect single nucleotide mutations, small insertions or deletions, or most copy number variants below the resolution threshold. If the clinical question involves a gene-level disorder, karyotyping alone is not going to give you the answer. You need sequencing or microarray work to fill in the gaps. Another issue is mosaic detection. If an abnormality is present in only a fraction of cells, you need to analyze enough metaphases to have confidence. Standard practice is to count at least 20 to 30 metaphases. Some laboratories go higher, especially when low-level mosaicism is suspected. If you only look at five cells and they all happen to be normal, you have not proven anything. You have just looked at too few cells. Sample contamination is less dramatic but more common than you might think. I once spent an afternoon puzzled by a karyotype that showed a mix of male and female cells in what was supposed to be a single patient sample. The cause turned out to be a cross-contamination from a neighboring culture dish that had been left uncovered for too long during media changes. It sounds like something that would only happen in a messy lab. It happened in a lab that was clean by most standards. I now seal every culture dish immediately after media exchange and label them with date and time. The extra ten seconds per dish prevents confusion later.
When Karyotyping Is Not Enough
Chromosomal microarray analysis has largely replaced karyotyping for many diagnostic applications because it catches submicroscopic abnormalities that standard banding misses. For developmental delay, intellectual disability, autism spectrum disorders, and multiple congenital anomalies, the microarray is often the first-line test now. Karyotyping still has value, though. It detects balanced translocations and inversions that microarrays cannot see. It gives you a global view of the genome in a single experiment. And for certain conditions like chronic myeloid leukemia, where the Philadelphia chromosome t(9;22) is a hallmark finding, karyotyping remains the go-to method because the structural rearrangement is large and easily visible. If you are studying karyotypes for academic purposes, the exercises are straightforward. You are given pre-made karyotype images or spreads and asked to identify abnormalities. The learning curve is mostly in pattern recognition. At first, every chromosome looks like every other chromosome. After examining maybe twenty or thirty karyotypes, the size and banding differences start to click. Chromosome 1 is obviously large with a metacentric appearance. Chromosome 21 is small and near the bottom of the list. The Y chromosome is unmistakably the smallest. These associations build up over time and are hard to rush. The practical advice that actually helps is to work through the karyotypes systematically. Check the total count first. Then scan for obvious structural issues like extra material on a chromosome arm or missing segments. Only then do you worry about subtle things like paracentric inversions or small deletions. If you start with the fine details you will miss the big picture. The eye tends to get drawn to whatever anomaly is most visually striking, which means you can overlook a simple numerical abnormality hiding right in plain sight because your attention was already elsewhere.

Karyotyping is not glamorous work. It is repetitive, it requires patience, and it demands that you accept its limitations honestly. But when you catch a translocation that explains a patient's history, or confirm a trisomy that changes the management plan, it is worth the time spent squinting at blurry chromosome images on a worn-out microscope.