What People Get Wrong About Isotonic Solutions
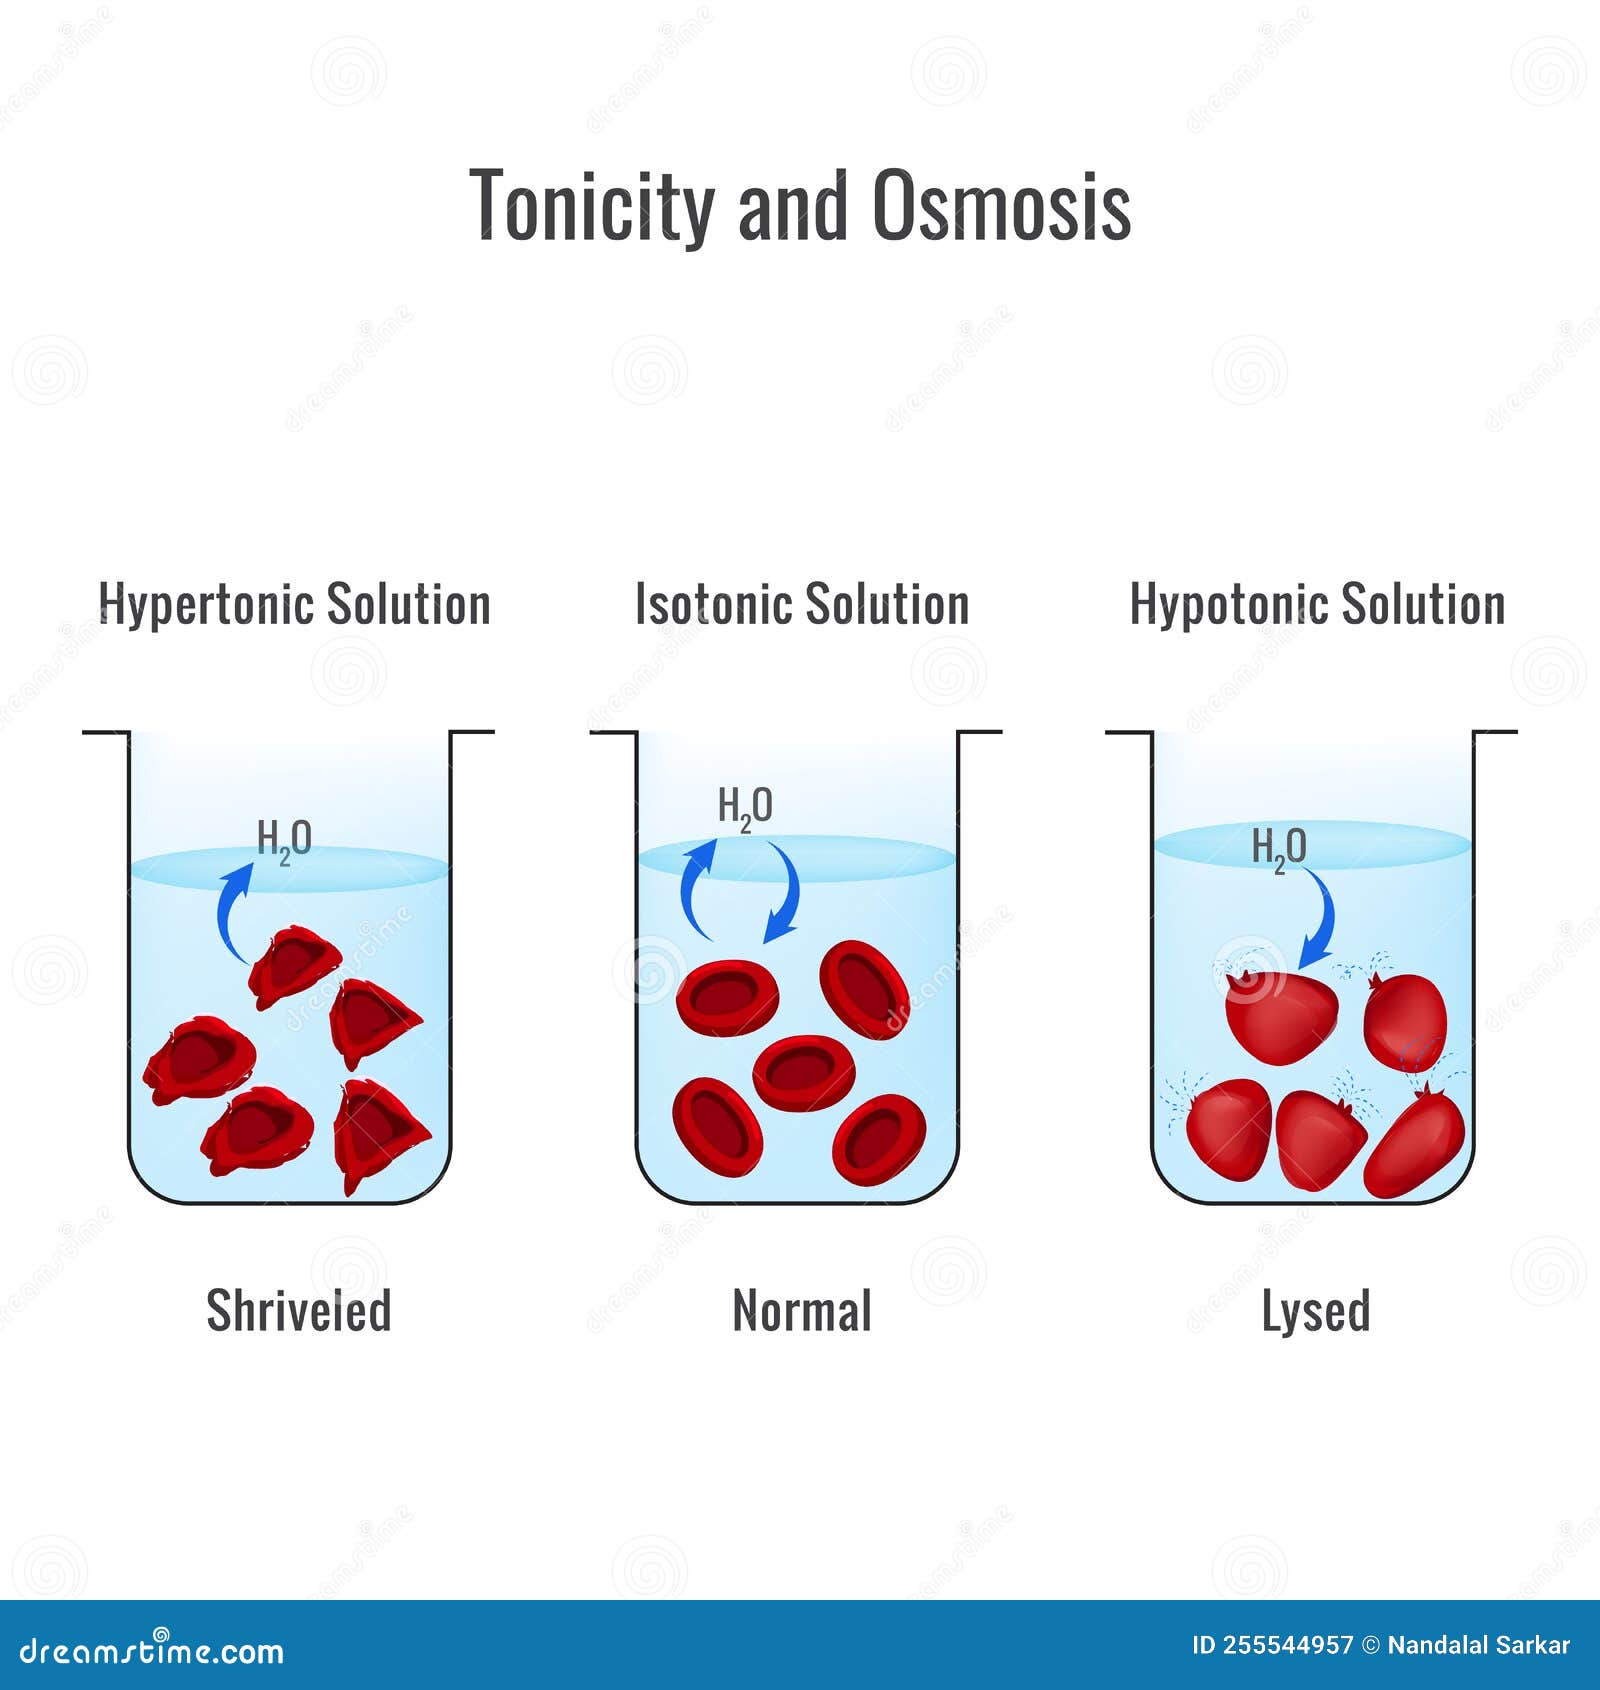
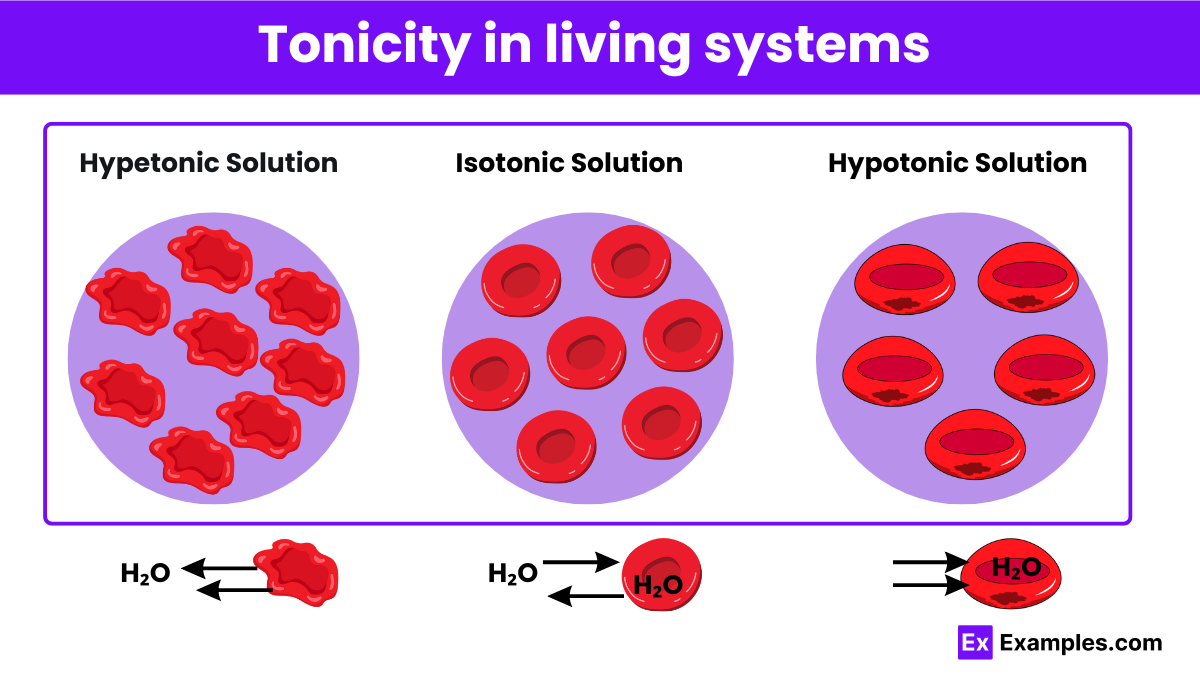
I used to make the same mistake every time I was preparing IV fluids in the lab. People treat isotonic like it is just a neat little box you check off. It is not. It is a whole system of balances that can throw you for a loop if you are not paying attention. An isotonic solution is one where the osmotic pressure matches that of a reference fluid, typically blood plasma. When the pressures are equal, there is no net movement of water across a semipermeable membrane. That is the textbook definition. The practical reality is messier. The most common example is normal saline, which is 0.9 percent sodium chloride by weight in water. It has an osmolarity of about 308 milliosmoles per liter, which is close enough to human plasma that red blood cells stay intact when exposed to it. Other examples include 5 percent dextrose in water before the sugar metabolizes, and lactated Ringer's solution for more complex electrolyte balancing.
Example For Isotonic Solution
Here is how I actually calculate these things when the textbook numbers are not cutting it. You start with the osmolarity you need to match. For blood, that is roughly 285 to 295 milliosmoles per liter. Then you figure out how much solute gets you there. The formula is straightforward enough: Osmolarity equals the van't Hoff factor multiplied by molarity multiplied by 1000. For sodium chloride, the van't Hoff factor is about 1.8 because the ions do not fully dissociate in solution. So if you need 300 milliosmoles per liter, you divide by 1.8 and by 1000 to get your molarity, which comes out to roughly 0.167 molar. Multiply that by the molecular weight of NaCl, which is 58.44 grams per mole, and you get about 9.75 grams per liter. Round it to 9 grams per liter and you have your normal saline.
I learned this the hard way during a formulation project back in 2019. We were making a custom isotonic eye drop with multiple active ingredients, and the pH was fine, the sterility was fine, but the osmolarity kept drifting. It turned out the buffer system we chose was contributing significantly to the total ion count, and the textbook calculations did not account for that interaction. The drops were hypertonic at room temperature but shifted as the temperature changed during storage. The workaround was to measure osmolarity directly using a freezing point depression osmometer rather than relying on calculated values. We ended up adjusting with purified water in small increments after the final fill, which gave us a target of 290 milliosmoles per liter. That is the kind of thing nobody warns you about until you are staring at a batch rejection notice. There are a few things beginners consistently miss. One is that temperature matters. Osmolarity is not a fixed number the way a mass is. It shifts with temperature because the volume of the solvent changes. If you are working in a warm lab and calibrating at room temperature, your solution might be slightly hypotonic by the time it reaches body temperature. It is a small difference, maybe two or three milliosmoles, but it matters when you are working at the edge of the isotonic range.
Get the Full Details
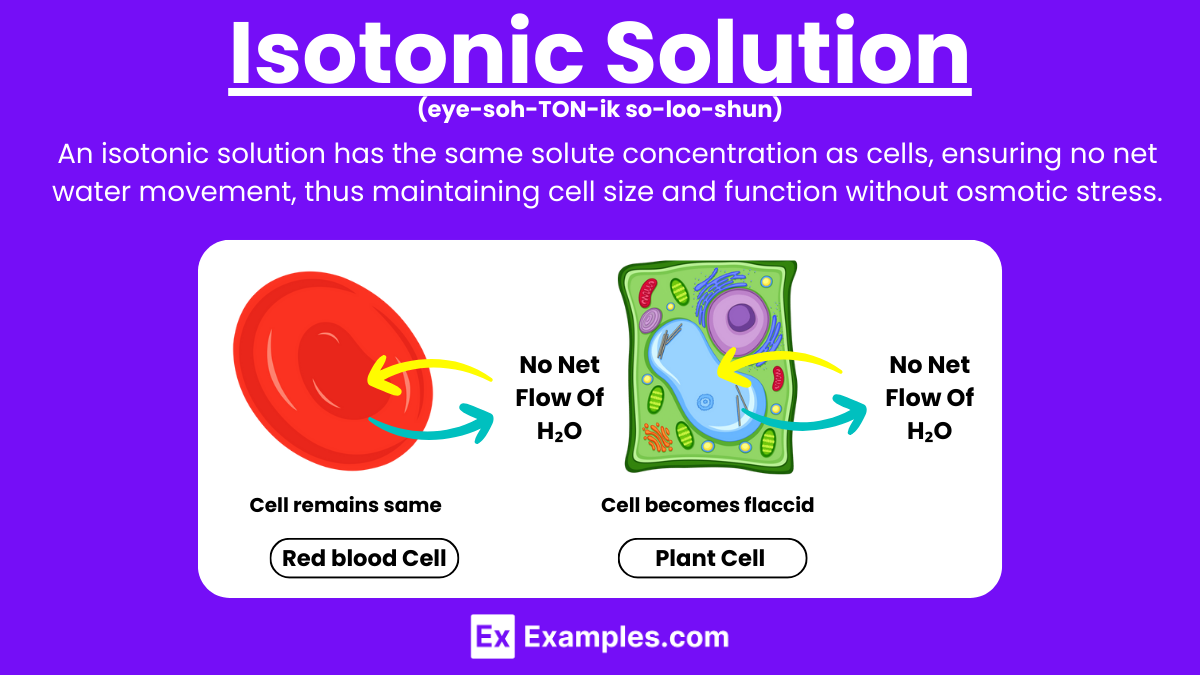
Another thing is that not all solutes behave the same. Glucose does not dissociate into ions, so its van't Hoff factor is 1. Sodium chloride splits into two particles, roughly. Calcium chloride splits into three. These differences matter when you are building a solution with multiple salts. You cannot just add up their masses and expect the right result. You have to account for the particle count each one contributes. There is also the question of whether you want iso-osmotic or isotonic. These are not identical. A solution can be iso-osmotic, meaning it has the same osmotic pressure as plasma, but still cause hemolysis if the solute can cross the cell membrane. Urea is the classic example. It is iso-osmotic at the right concentration, but it freely enters red blood cells and pulls water in with it. The cells swell and burst anyway. Isotonic requires that the solute cannot cross the membrane, so there is truly no net water movement. This distinction is important in pharmaceutical work and often gets glossed over. I once saw a lab use urea as an osmoticum in a cell culture medium and wonder why their cells kept popping. The osmolarity reading looked perfect on the meter. Nobody had checked permeability. It took two weeks and a lot of confused phone calls before someone figured it out.
If you are preparing isotonic solutions for actual use rather than just calculations, here is a practical workflow. Make up your solution with all the solutes dissolved. Measure the osmolarity with a proper instrument, not a calculation. Adjust with water or concentrated stock solutions until you hit your target. Then verify pH and clarity. If you need it sterile, filter it through a 0.22 micrometer filter after the osmolarity adjustment, because sterilization can change things slightly. The biggest bottleneck I have seen is people trying to calculate everything and skipping the measurement step. You can get close with math, but close is not good enough when you are putting something into a patient or running sensitive experiments. A basic freezing point depression osmometer costs somewhere in the range of two to five thousand dollars. That is expensive for a small lab, but cheaper than dealing with a recall or failed clinical batch. Another option if you do not have access to an osmometer is to use the sodium chloride equivalent method. This involves looking up the E-value for each ingredient, which tells you how much NaCl each gram of that substance is equivalent to in terms of osmotic effect. You sum up all the equivalents and adjust with NaCl to reach the target. It is less precise than direct measurement but acceptable for many pharmaceutical compounding scenarios where the stakes are lower.
I should say this bluntly: isotonic solutions are not a set-and-forget thing. They drift. Storage conditions, container materials, and even the order in which you add ingredients can affect the final osmolarity. I have had batches that looked fine at preparation but shifted during stability testing because a component precipitated out slowly over time, reducing the particle count in solution. That is not something you catch at the beginning of the process. If you need a reliable reference, the United States Pharmacopeia has detailed chapters on osmolarity and tonicity testing. The European Pharmacopoeia covers similar ground. For general chemistry purposes, standard textbooks like Harris's Quantitative Chemical Analysis have solid explanations with worked examples. But the real learning happens when you are the one holding the pipette and the meter reads the wrong number. The bottom line is that understanding isotonic solutions requires both calculation and measurement. Numbers give you a starting point. Instrumentation tells you where you actually are. The gap between those two is where most problems show up, and the people who learn to bridge that gap are the ones who stop wasting time on failed batches.