Understanding Cephalosporins: A Practical Guide
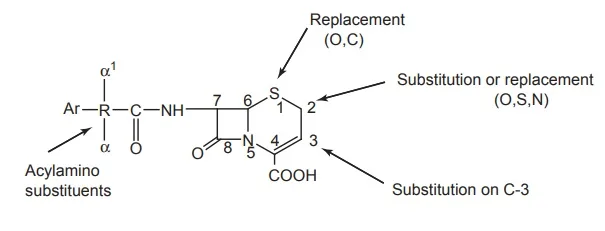
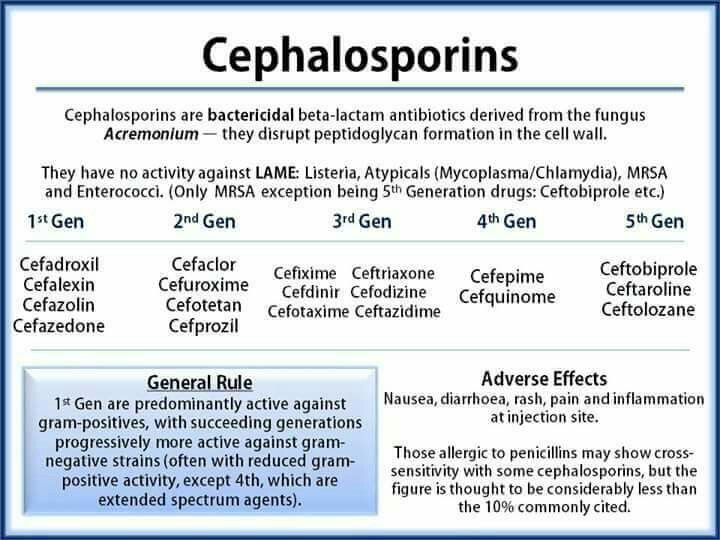
Cephalosporins are beta-lactam antibiotics derived from the fungus Acremonium. They work by inhibiting bacterial cell wall synthesis, specifically targeting penicillin-binding proteins. This mechanism is similar to penicillins, but cephalosporins have a different core structure that gives them distinct spectrum and resistance properties. There are five generations of cephalosporins, each with different coverage profiles. First-generation agents like cefazolin and cephalexin target gram-positive organisms well, including methicillin-sensitive Staphy Aureus. Second-generation drugs like cefuroxime and cefoxitin add some gram-negative coverage. Third-generation cephalosporins such as ceftriaxone and cefotaxime shift the balance toward gram-negative bacteria, including many Enterobacteriaceae. Fourth-generation agents like cefepime cover both gram-positive and gram-negative organisms more broadly. Fifth-generation ceftaroline adds activity against MRSA.
Example Of A Cephalosporin In Clinical Practice
One common example you will encounter frequently is ceftriaxone. It is a third-generation cephalosporin with a long half-life that allows once-daily dosing. I use it often for community-acquired pneumonia, meningitis, and certain sexually transmitted infections. The dosing is straightforward: 1 to 2 grams intravenously or intramuscularly once daily, adjusted for renal impairment only in severe cases since it has dual biliary and renal elimination. Here is a scenario I ran into recently that illustrates something important about cephalosporin use. A patient came in with a complicated urinary tract infection caused by Escherichia coli. We started empiric ceftriaxone, but the culture returned showing an extended-spectrum beta-lactamase producer. Ceftriaxone failed clinically despite apparent in-vitro susceptibility on standard testing. The workaround was switching to ertapenem, a carbapenem, which covered the ESBL-producing organism effectively. This is a critical point: standard susceptibility reports for cephalosporins can sometimes be misleading with ESBL producers due to the inoculum effect and ambiguous breakpoint interpretations. When you suspect an ESBL, do not rely on cephalosporin therapy regardless of what the report says. Carbapenems remain the treatment of choice. Another example of a cephalosporin worth discussing is cefazolin. It is a first-generation agent commonly used for surgical prophylaxis. The standard preoperative dose is 2 grams IV administered within 60 minutes before incision. For patients weighing over 120 kilograms, I use 3 grams. The timing matters more than most people realize. If you administer cefazolin too early, tissue concentrations drop below therapeutic levels by the time the incision happens. If you give it too late, you miss the window entirely. I have seen protocols where anesthesia induces the patient before the antibiotic is even hanging, which defeats the purpose.
There is a nuance with cephalosporins that beginners frequently miss. The generation numbering does not simply mean each successive generation is strictly better. A first-generation cephalosporin like cefazolin is actually superior to third-generation agents for gram-positive coverage, including staphylococci and streptococci. Using ceftriaxone for a skin and soft tissue infection caused by MSSA is an example of choosing broader spectrum when narrower would be more appropriate. This is a common prescribing error that drives resistance without improving outcomes. Cross-reactivity between penicillins and cephalosporins is another area where outdated information causes problems. The old teaching was that there was a 10 percent cross-reactivity rate. More recent data suggests the actual rate is closer to 1 to 2 percent for most cephalosporins, and even lower for later generations. The side chain structure matters more than the core beta-lactam ring. Cefazolin, cefuroxime, and ceftriaxone have side chains that are structurally distinct from penicillin, making cross-reactivity unlikely. Only cephalexin and a few others share significant side chain similarity with amoxicillin. If a patient has a documented penicillin allergy, consulting an allergy specialist for clarification or testing often reveals they can safely receive most cephalosporins. Adverse effects with cephalosporins are generally mild but not negligible. Diarrhea occurs in roughly 5 percent of patients, and Clostridium difficile infection is a real risk with all broad-spectrum antibiotics. Cefoperazone and cefotetan carry a higher risk of hypoprothrombinemia and bleeding due to their N-methylthiotetrazole side chain, which interferes with vitamin K metabolism. I always check coagulation parameters in patients on these agents, especially those who are malnourished or on anticoagulants. Supplemental vitamin K is sometimes necessary during prolonged courses.
Get the Full Details
Ringed false positives with some glucose monitoring systems is an obscure but important interaction. Cefditoren and a few other cephalosporins can cause falsely elevated blood glucose readings with certain point-of-care glucometers that use glucose dehydrogenase pyrroloquinoline quinone. This happened to a colleague of mine who was managing a diabetic patient on cefditoren. The blood sugars looked wildly elevated, and the diabetes regimen was adjusted unnecessarily before we traced the discrepancy back to the antibiotic. Switching to a different glucometer technology resolved the issue immediately. If your patient is on cephalosporins and their glucose readings seem inconsistent with their clinical picture, consider this interference before making treatment changes. Dosing adjustments deserve attention. Most cephalosporins require modification in renal impairment, but the degree varies. Ceftriaxone is the notable exception that rarely needs adjustment. Cefepime accumulates significantly in renal failure and can cause neurotoxicity including seizures and encephalopathy if not properly dose-adjusted. I have personally managed a patient who developed reversible myoclonus and confusion after cefepime accumulation, and it took nearly a week to resolve after discontinuation. Checking creatinine clearance before prescribing and adjusting accordingly is essential, not optional. Administration considerations also matter in practice. Many cephalosporins are incompatible with calcium-containing solutions. Ceftriaxone precipitates with calcium in the neonatal population, and this combination has caused fatal events. Never co-administer ceftriaxone with calcium gluconate or parenteral nutrition containing calcium in neonates under 28 days old. This is a hard rule with zero exceptions.
The cost and availability of cephalosporins varies considerably. Generic cefazolin and cephalexin are among the cheapest antibiotics available, often costing less than a dollar per dose. Ceftriaxone is also relatively inexpensive. Later-generation and newer agents carry higher price tags, which can influence formulary decisions in hospital settings. The therapeutic advantage of a more expensive cephalosporin must justify the incremental cost in most cases.