Working Through an OLDCART Assessment in Practice
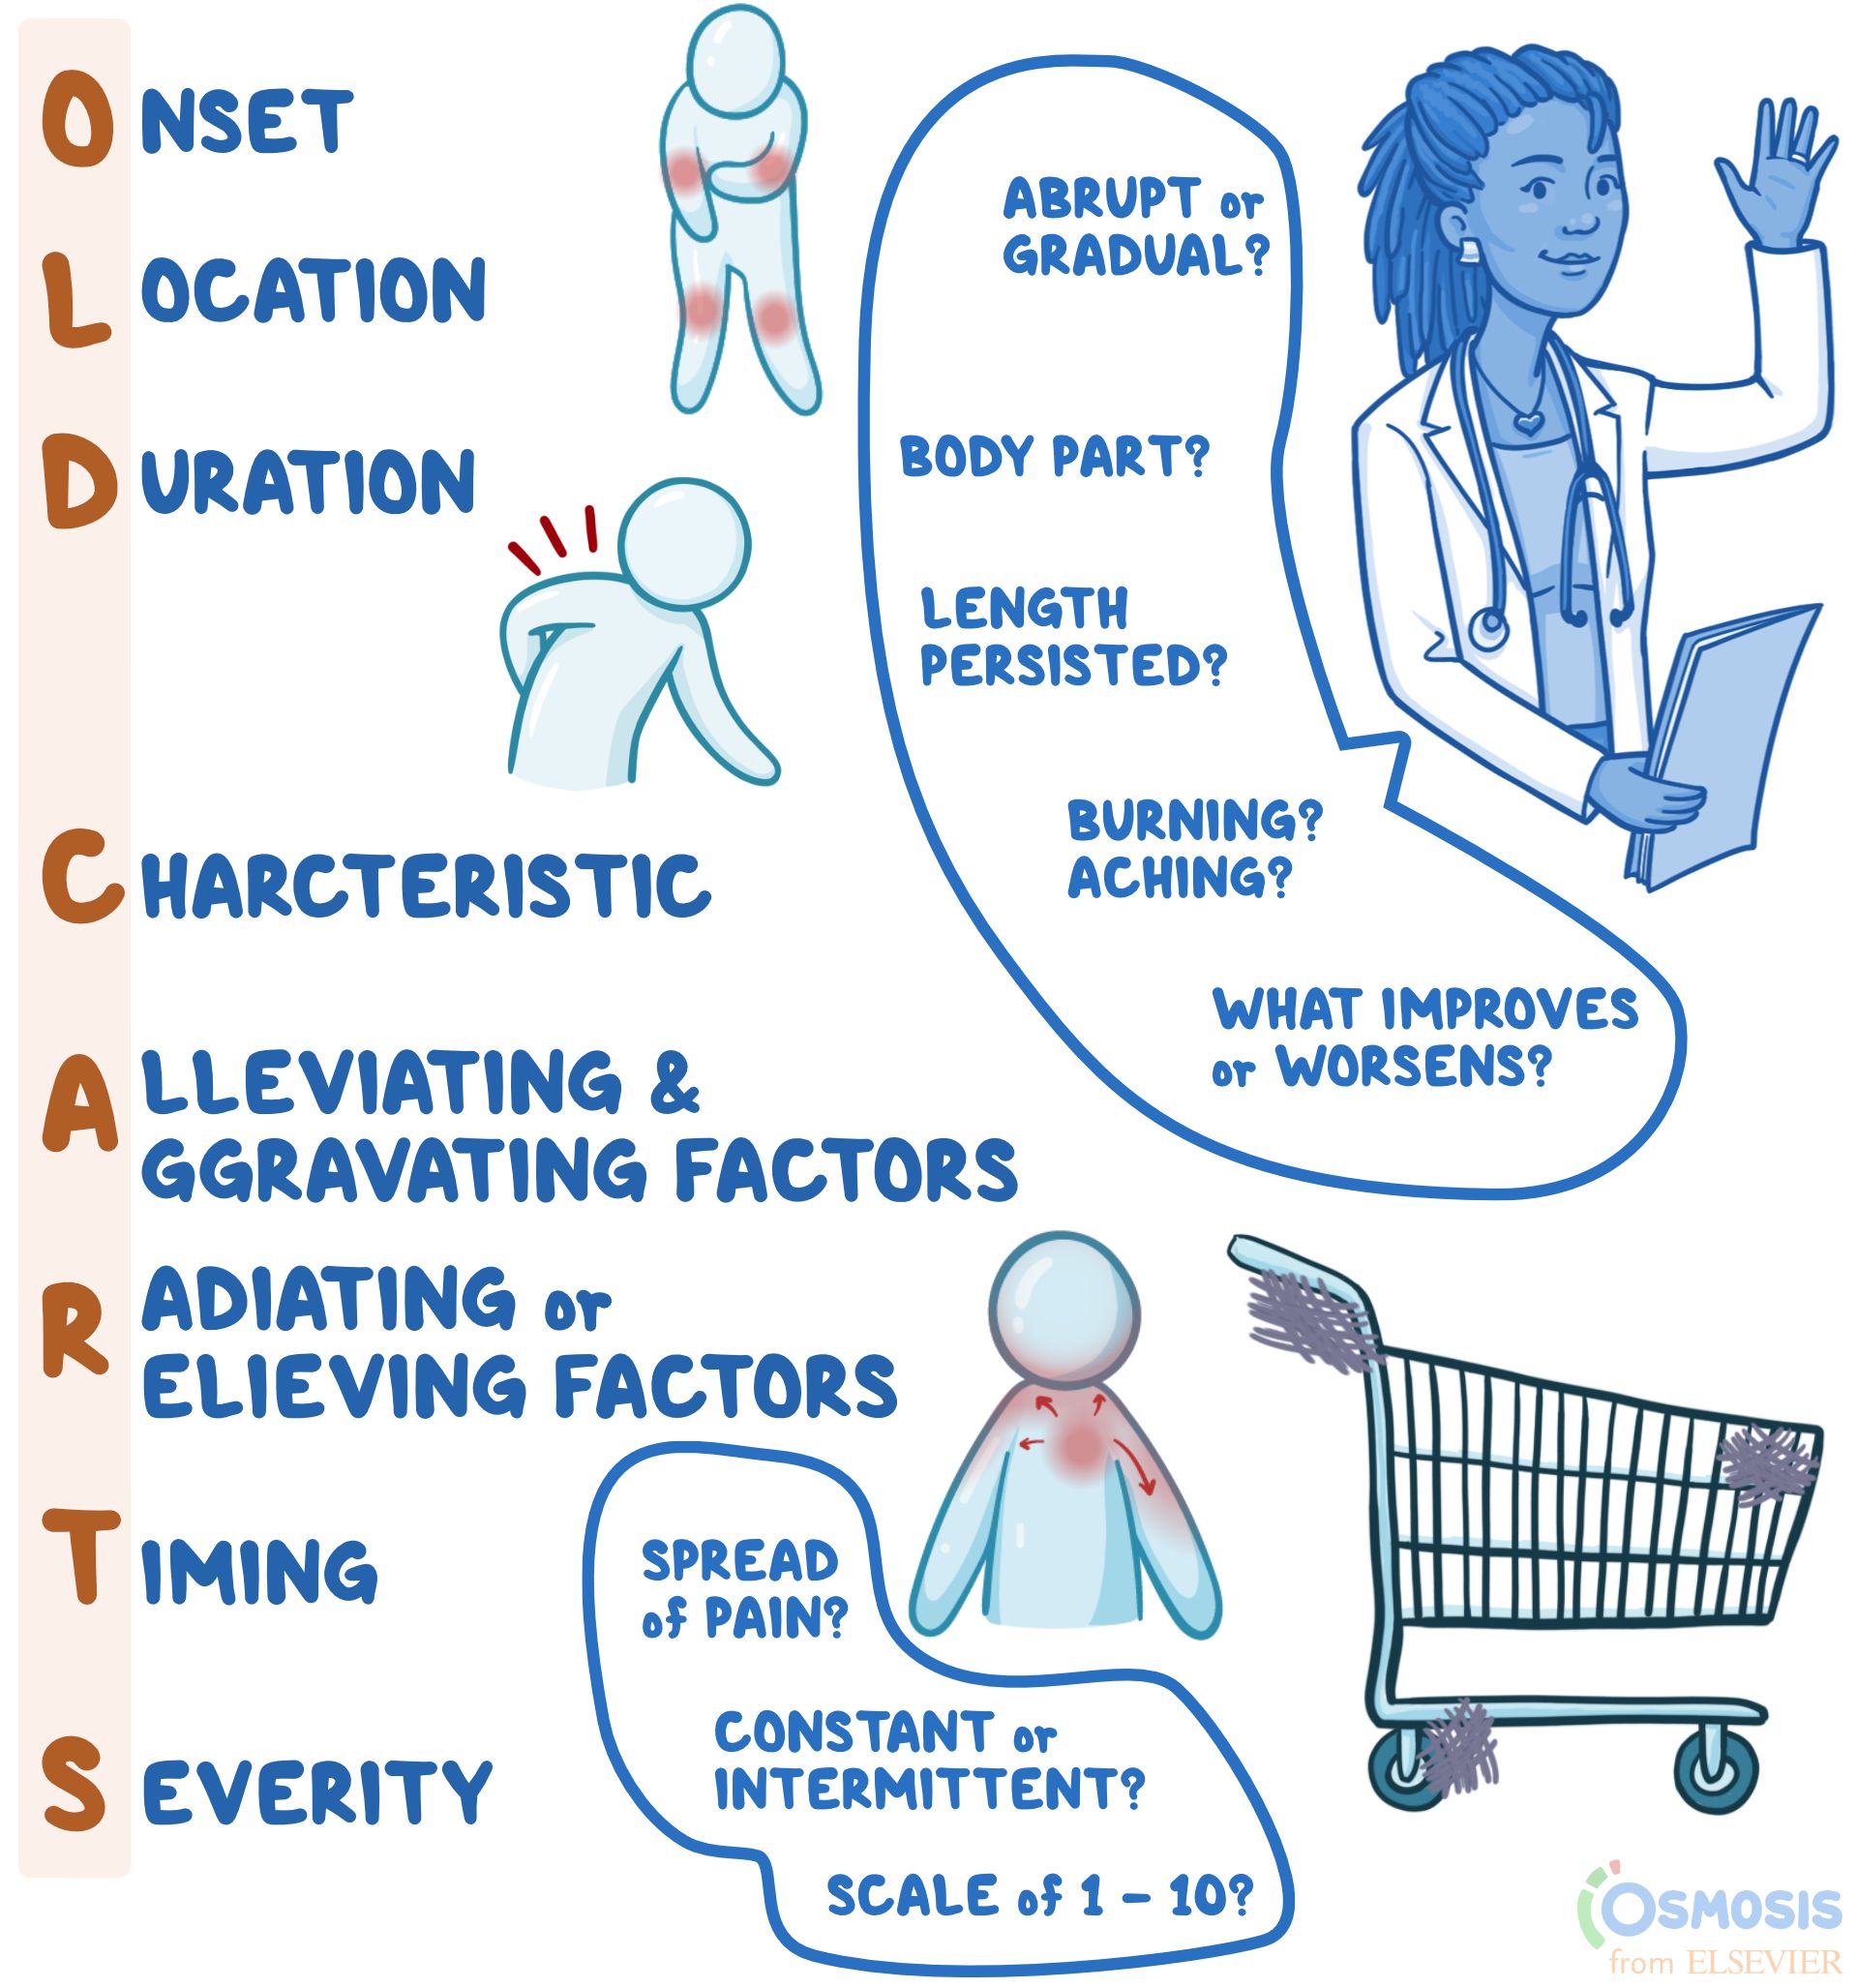
I used to dread the assessment portion of clinical rotations. Not because the content was hard, but because students tend to memorize the mnemonic and then go blank when a real patient starts talking. The OLDCART framework — Onset, Location, Duration, Character, Aggravating/Alleviating factors, Radiation, and Timing — is straightforward in theory. It falls apart the moment a patient describes their pain as starting "a while ago" and you have no idea how to redirect them without sounding like a robot. The trick most people miss is that OLDCART is not meant to be read off like a checklist. It works best when you weave the questions naturally into conversation. I learned this the hard way during my third year of nursing school. I sat across from a 72-year-old man with abdominal discomfort and literally asked him "what's the onset?" He looked at me like I'd lost my mind. I had to backtrack and rephrase everything. That took about ten minutes I didn't have.
Example Of Oldcart Assessment in a Real Clinical Setting
Here is a concrete example from a shift I remember clearly. A patient presented with chest discomfort. Instead of firing off questions rapidly, I started with location and let the conversation unfold from there. Onset: I asked when he first noticed the symptom, and specifically what he was doing at the time. He said it began while he was raking leaves. That detail mattered — exertional onset changes the differential entirely compared to onset at rest. Location: I had him point with one finger. He pointed to the center of his chest, slightly left of midline. Not diffuse. This helped narrow things away from musculoskeletal causes which tend to be more localized and reproducible with palpation.
Duration: Each episode lasted roughly 5 to 10 minutes. This was useful information because cardiac ischemic pain typically lasts under 30 minutes unless it progresses to infarction. Longer duration would have raised different concerns. Character: He described it as "pressure," not sharp or burning. Pressure-type chest pain is classic for cardiac origin. Burning might have pointed toward GERD. Sharp and pleuritic would suggest pulmonary causes. The word choice he used carried diagnostic weight. Aggravating and Alleviating factors: The discomfort worsened with activity and improved with rest. This is textbook angina. If it had been relieved by antacids, we would have been looking at a GI workup instead. He also mentioned smoking two packs a day, which is a significant risk factor worth flagging early.
Get the Full Details

Radiation: No radiation to the arm, jaw, or back. This is notable because absence of radiation doesn't rule out cardiac issues, but it does make the presentation less typical. Some patients present atypically, especially women and older adults. That's a common pitfall — assuming no radiation means no cardiac concern. It doesn't mean that at all. Timing: The episodes had been happening for about three weeks, increasingly frequent. Timeline context like this helps determine urgency. Three weeks of progressive symptoms is very different from a single isolated episode. That assessment took me about eight minutes once I stopped rushing through it. The first few times I tried it, it took 20. The difference was letting the patient talk and using their own words as anchors for the next question.
One thing nobody teaches you about OLDCART is how much it overlaps with other assessment frameworks. If you are doing a full nursing assessment, the OLDCART details slot into the subjective data section alongside vital signs and past medical history. But here is the counter-intuitive part: patients often volunteer aggravating and alleviating factors before you even ask. I have found it more efficient to let them describe the symptom freely first, then use OLDCART as a verification net rather than an interrogation script. Another nuance that trips people up is duration versus frequency. Duration is how long each episode lasts. Frequency is how often episodes occur. Both matter. A patient might have brief episodes (2 minutes each) that happen twenty times a day, or rare episodes (30 minutes each) that happen once a week. These present very differently clinically. I once missed the frequency component in an initial assessment and had to go back to the patient the next day to fill in the gap. It was awkward and delayed the care plan. The main limitation of OLDCART as a standalone tool is that it focuses almost entirely on symptom characterization. It does not address psychosocial context, functional status, or medication review. If you are working with elderly patients specifically, you need to pair it with a broader geriatric assessment that includes cognition, mobility, polypharmacy, and social support. Relying solely on OLDCART in that population gives you a narrow picture of a complex problem.
For documentation purposes, I structure my notes around the mnemonic headings so nothing gets missed during handoff. The format looks something like this: Onset: sudden vs. gradual, what patient was doing at start
Location: specific anatomical area, patient-pointed
Duration: how long each episode lasts
Character: patient's own descriptive words
Aggravating/Alleviating: what makes it better or worse
Radiation: any spread of symptoms
Timing: frequency, pattern, progression over days or weeks It is not glamorous. It is also one of the most reliable ways I have found to gather consistent subjective data across different types of presentations. Once you stop treating it like a form to fill out and start using it as a conversation guide, it becomes almost automatic. The first few months are clunky. After that, your brain starts organizing the information on its own.