.png)
How to Actually Write Therapy Goals That Work
Therapy goals are simply measurable, time-bound objectives a client and clinician agree to work toward during treatment. They appear in intake documentation, clinical notes, and insurance billing records. Most people don't realize that the same document also serves as legal evidence if anything is ever challenged. That changes how you write them.A poorly written goal looks like this: "Client will improve communication skills." That's not a goal. That's a wish with a verb attached. Insurance reviewers reject statements like that constantly. The client gets no clarity. The therapist has no measurable endpoint. Everyone wastes six sessions circling around it. The fix is straightforward. You need a behavior, a frequency, a condition, and a timeframe. "Client will initiate a difficult conversation with their partner using 'I' statements at least three times per week over eight weeks, as measured by self-report and session review." That gives you something to track. It gives you something to adjust.
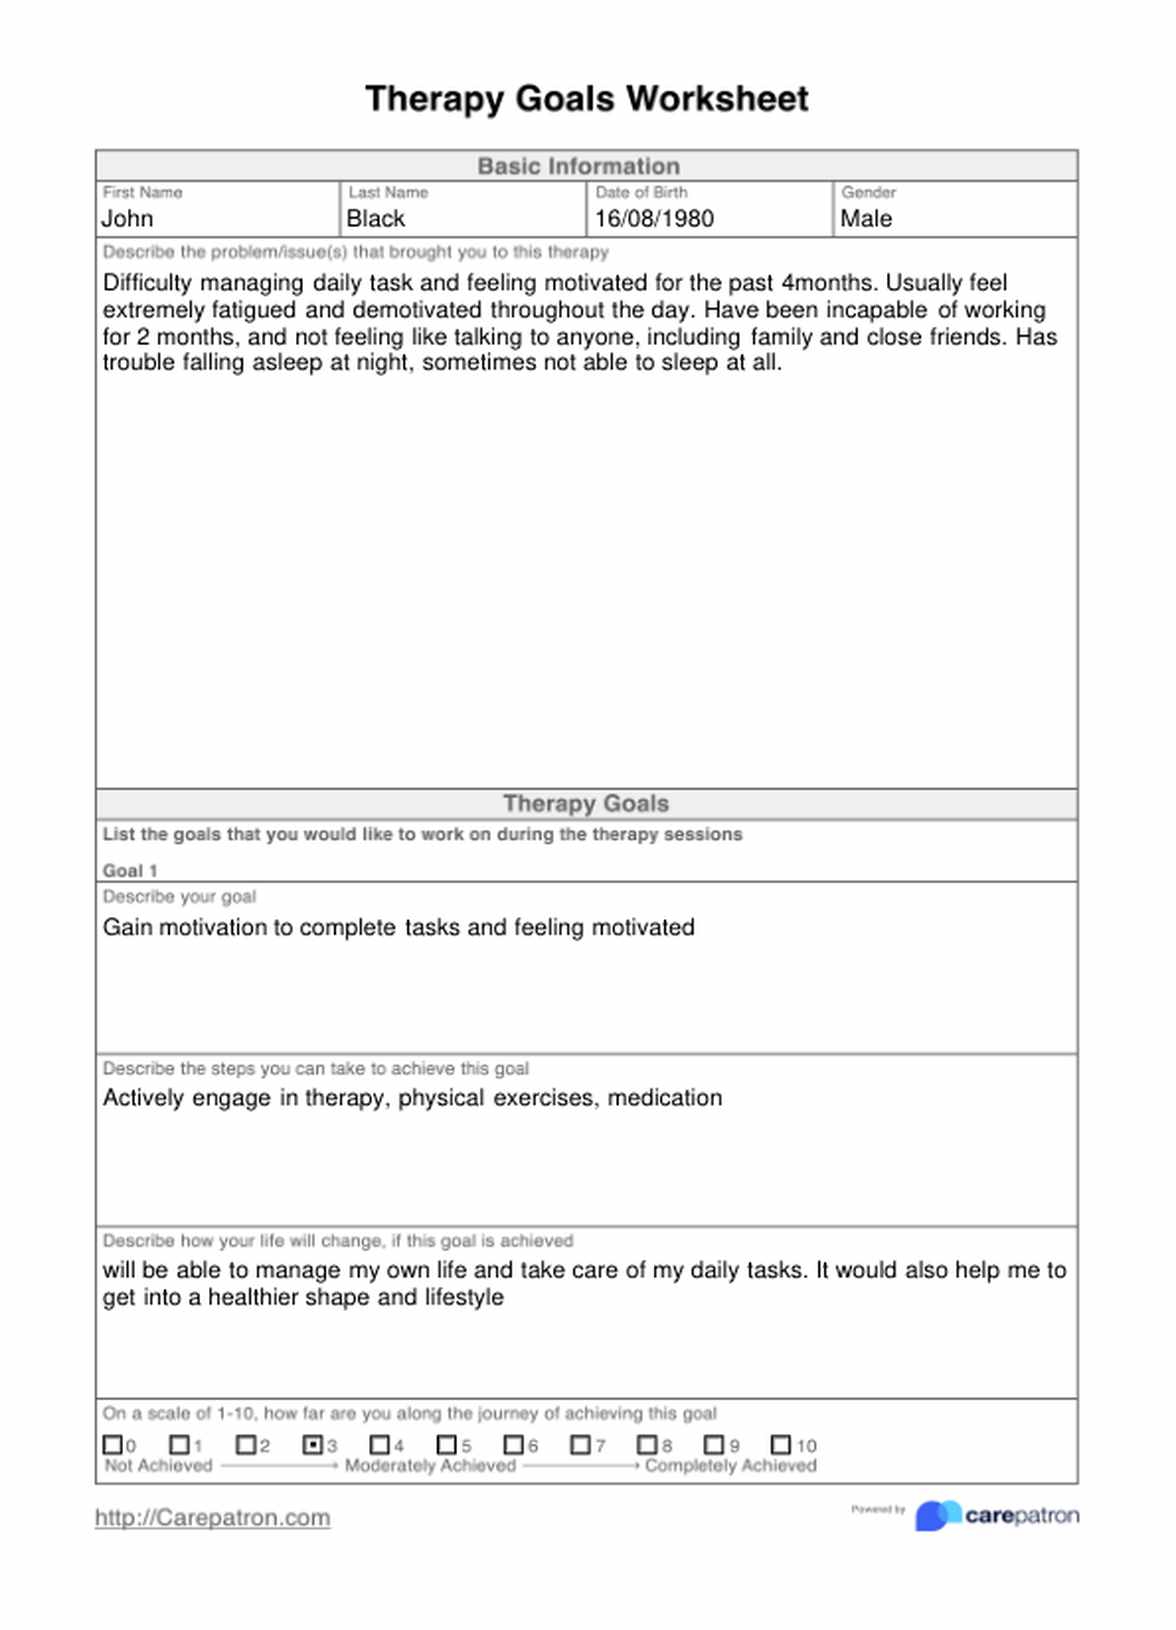
Example Of Therapy Goals
I see this question come up constantly on clinical forums, usually from grad students who have never dealt with a denied claim. Here is a realistic set from a common anxiety case: Goal 1: Client will reduce panic attack frequency from five per week to two or fewer per week within twelve weeks, as measured by a panic diary. Goal 2: Client will complete seven graded exposure exercises targeting avoided situations, documented through session notes and behavioral logs.
Goal 3: Client will demonstrate two Coping Anxiety With Behavioral Experimentation (CABE) techniques independently in session by week ten, rated at least 6 out of 10 on a clinical scale. These are specific enough that another clinician could pick them up and continue the work without losing the thread. That matters more than people admit. Here is a practical edge case I ran into that most guides never mention. A client was assigned a goal to "reduce social avoidance through exposure exercises." By week four, the client was completing the exposures but reported a significant increase in rumination afterward. The goal was technically being met. The outcome was getting worse. I pulled the goal entirely and rebuilt it around post-exposure processing instead of just the exposure count. We added a 30-minute buffer requirement after each exercise for cognitive processing and grounding. The session notes flagged the original goal as amended with a date and rationale. This is not some rare anomaly. It happens regularly with anxiety protocols where the behavioral piece outpaces the cognitive piece. The fix is rewriting the goal, not pushing harder on the old one.
Get the Full Details

One thing beginners consistently miss is that therapy goals and treatment objectives are not interchangeable, even though your EHR platform might use the labels differently. A goal is the broad outcome you are working toward. An objective is a specific milestone that contributes to that goal. Think of it as the difference between "get to the top of the mountain" and "reach the ridge camp by Tuesday." You can have multiple objectives under one goal. You can also have goals without clear objectives, which is how therapy drifts for weeks without anyone noticing. SMART criteria get cited everywhere, but they are incomplete for clinical work. SMART goals fail when the client's condition makes the "measurable" part unreliable. Trauma clients, for example, often have disrupted episodic memory. Asking them to count panic attacks accurately over eight weeks produces garbage data. The workaround is switching to clinical observation as the primary measure and using client self-report as a secondary source. Write the goal to reflect that. "Clinician will document client's observable avoidance behaviors across seven sessions, with client self-report serving as supplementary data." That is honest and it actually works in practice. Another limitation worth stating plainly: therapy goals can become self-fulfilling constraints. I had a client whose goal was framed entirely around reducing symptoms of depression. The entire treatment plan locked into that frame. Six months in, we realized the client's core issue was not the depression itself but the relational patterns maintaining it. We spent half a year treating the symptom instead of the structure. Had we written the goal around "identifying and modifying relational patterns that reinforce depressive episodes" from the start, the trajectory would have been different. Goals shape the therapy. That is why precision matters more than speed when you are writing them.
Documentation standards vary significantly by setting. In private practice, you are writing for yourself, the client, and possibly an insurance reviewer who has never read a full clinical file. In a hospital or community mental health center, your goals become part of a team handoff document. If you write "client demonstrates improved coping," the next clinician learns nothing. If you write "client utilized distress tolerance skills from DBT module four on three occasions during crisis situations in the past two weeks," the handoff is functional. Timeframe selection is another area where people guess. Twelve weeks is the most common standard for insurance authorization, but it does not match all conditions. Acute trauma processing usually needs sixteen to twenty weeks. Adjustment disorder goals can often be contained in eight to ten. Writing a twelve-week timeframe for complex PTSD is a sure way to get a treatment plan that falls apart at week six and requires a complete rewrite. The actual process of writing goals takes most clinicians about ten to fifteen minutes once they know the format. The first time, it usually takes longer because you are second-guessing whether each word is precise enough. After about six or seven treatment plans, it becomes routine. The bottleneck is usually not the writing. It is the client collaboration step, where you need to make sure the goal reflects what the client actually wants rather than what you think they should want. Skipping that step produces compliance without engagement.
There are free templates available from major psychology organizations and state licensing boards. The APA provides a basic treatment plan template. Many university counseling training centers publish their own versions online. The specific format matters less than consistently including the behavioral descriptor, the condition, the measurement method, and the timeframe. Any template that omits one of those four elements is incomplete. When you share an Example Of Therapy Goals with other clinicians, include the amendment history. Notes that show how a goal evolved based on client response are more educational than static examples. They reveal the clinical reasoning. They also protect you. If a complaint or audit ever surfaces, documentation that shows active adjustment and clinical judgment reads very differently from a treatment plan written once and never touched again.