
ABA Therapy Techniques That Actually Work In Practice
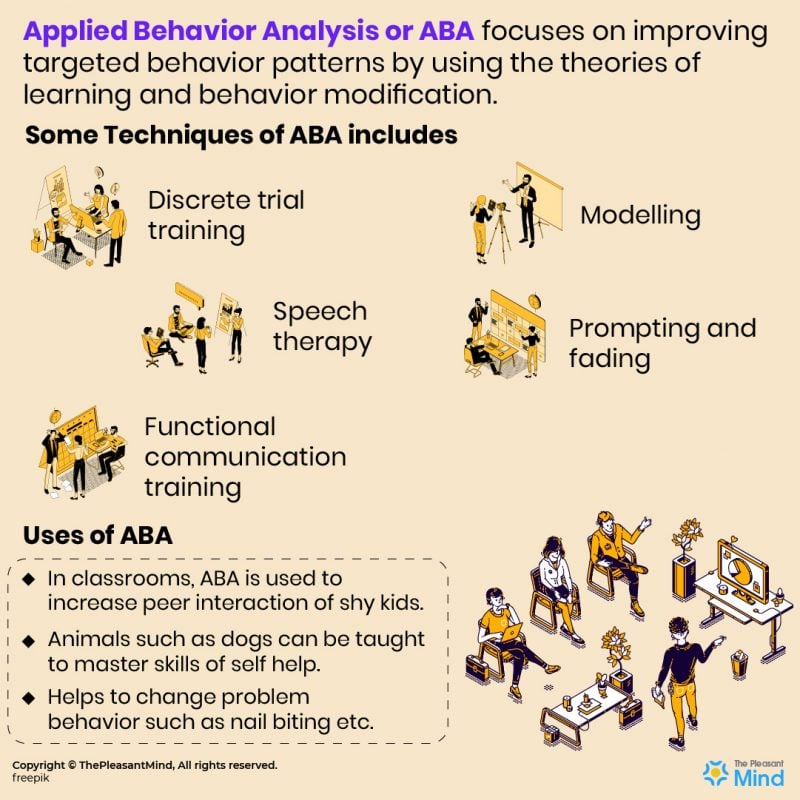
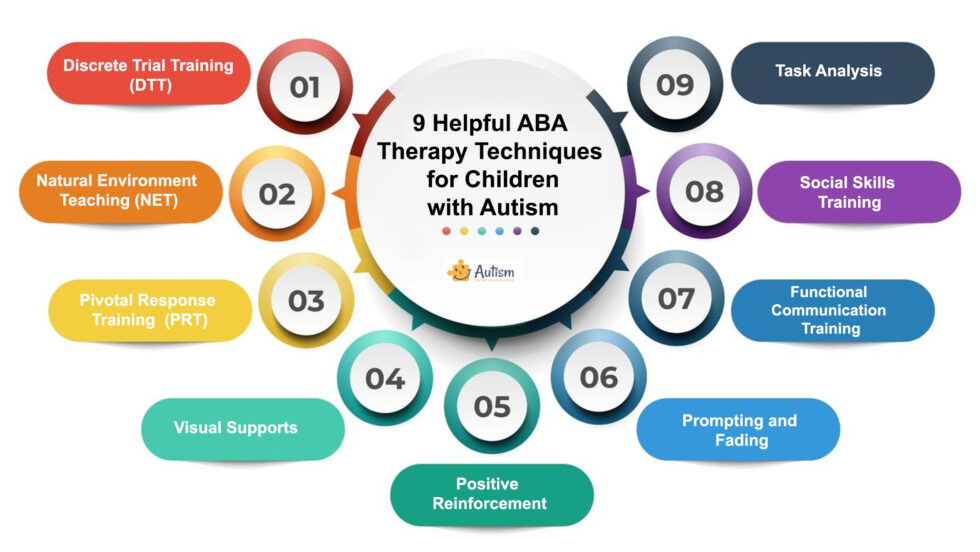
Most people looking for Examples Of Aba Therapy Techniques end up reading dry textbook definitions that don't tell you what it feels like to actually run a session. I'm going to skip the academic preamble and just lay out the techniques, how they're applied, where they break down, and what I've learned from doing this work for years. This is the bread and butter of ABA and probably the first technique you've heard about. It breaks skills into small discrete components and teaches them through repetition with clear beginnings and endings. The therapist presents a clear instruction, the child responds, and then there's a consequence—reinforcement or correction. That's it. Simple structure. In practice, a DTT session might look like this: the therapist says "touch blue" and holds out four colored cards. The child touches the blue card. The therapist says "good job" and hands over a small piece of cereal. That's one trial. You might run 10 to 20 trials per skill in a row before moving on. The data is recorded after each trial—correct, incorrect, or no response. This granularity is what makes DTT powerful for tracking progress, but it's also where people get it wrong.
The problem I see most often is over-reliance on DTT for generalization. A child can discriminate colors in a structured table setting and then completely fail to point to blue when you're at the grocery store and they need to grab the blue box of crackers. The skill exists in the training context but hasn't transferred. The workaround is mixing in naturalistic teaching early—don't spend months in DTT before introducing any natural environment practice. Even 20 percent of your sessions should be outside the table from the beginning.
Natural Environment Teaching (NET)
NET is the counterbalance to DTT. Instead of structuring the environment, you use whatever the child is already doing as the teaching opportunity. If the child reaches for a bubble container, you wait for them to look at you and then model the word "more" before blowing again. The reinforcer is built into the activity. No cereal on a tray. No flashcards. Just the natural flow of play. What people miss about NET is that it requires more skill from the therapist than DTT. You have to be observant enough to catch teachable moments in real time and flexible enough to pivot when the child's interest shifts. I once had a case where the child was stimming with a spinning top and I tried to use it for mand training for three weeks with zero progress. The child had no motivational connection to the top at all. I switched to using a fan instead—same sensory input, completely different approach—and we got a mand for "spin" within two sessions. The material didn't matter as much as the child's actual engagement with it.
Get the Full Details
Incidental Teaching
Incidental teaching is a specific structured version of NET. You position the environment so the child has to communicate to get what they want, you wait for an initiation from the child, and then you scaffold their response to be more complex than what they originally produced. If a child points at a juice box, you don't just hand it over. You wait for a vocalization or a gesture, then model "juice" or "I want juice" before giving it. The key is the wait time. Most therapists rush in too fast and accidentally reinforce the less complex response. You need to hold the item, maintain eye contact, and wait at least five seconds. Five seconds feels like an eternity when you're sitting across from a child who is looking at you expectantly, but that pause is what creates the opening for a more advanced response. If the child doesn't respond in five seconds, you prompt—model the word or gesture, give the item, then try again on the next opportunity.
Pivotal Response Treatment (PRT)
PRT is different from the other techniques because it targets pivotal areas—motivation, self-initiation, and response to multiple cues—rather than specific discrete skills. The theory is that if you improve these pivotal behaviors, other skills will improve as a cascading effect without directly teaching every single one. It's an ambitious approach and the research supports it for certain outcomes, particularly around motivation and communication initiation. One PRT technique I use regularly is following the child's lead. Instead of directing the session toward my agenda, I observe what the child is focused on and build the teaching opportunity around that. If they're stacking blocks, the pivotal response might be taking turns rather than just teaching colors or shapes. The reinforcer is intrinsic—the fun of the activity itself—rather than external rewards like tokens or food. This tends to produce more generalized and maintained behaviors because the child isn't learning to work only for a specific reinforcer.
Functional Communication Training (FCT)
FCT is probably the most important technique for families dealing with challenging behavior. The basic idea is that many problem behaviors serve a function—escape, attention, access to tangibles, or automatic sensory reinforcement. FCT replaces the problem behavior with a functionally equivalent communication response. If a child hits to escape a demand, you teach them to say or sign "break" instead and then honor that request. The behavior drops out because the communication works better than hitting ever did. The tricky part is making sure the new communication response is easier than the problem behavior. I worked with a nonverbal child who would throw himself on the floor and bang his head whenever asked to do a therapy task. We taught him to hand me a "break" card. But at first, he'd still throw the card and bang his head anyway because head-banging was getting him breaks faster. So we made handing over the card the absolute minimum requirement—any contact with the card, even a brush, earned the break. Within a week, the head-banging had decreased by about 80 percent. Then we gradually increased the requirement until he was consistently handing me the card cleanly.
Antecedent-Based Interventions
Before you even get to teaching a replacement behavior, you should be adjusting the environment to prevent the problem behavior from occurring in the first place. This is called an antecedent-based intervention and it's often more effective than trying to manage behavior after it happens. Common ABI strategies include providing choices, using visual schedules, offering preferred activities, and breaking tasks into shorter segments. I've seen teams spend hundreds of hours on reinforcement schedules for a behavior that could have been eliminated by simply presenting the next activity visually instead of verbally. A child who ramps up every time you say "okay, after snack we're doing math" might not escalate at all if you show them a visual schedule where they can see snack is already checked off and they can point to what comes next. The visual removes the anxiety of the unknown. This single change cut that child's median task refusal duration from about twelve minutes to under two minutes within the first week.
Task Analysis and Chaining
When teaching complex skills like dressing, handwashing, or using utensils, you break the skill into a sequence of steps. That's a task analysis. Then you teach those steps in order using chaining—either forward chaining where you start with the first step, or backward chaining where you start with the last step and work backward. Backward chaining is often more efficient because the child gets the natural reinforcer at the end of the chain every time. If you're teaching shoelace tying and you do all the steps except the final knot, the child gets the satisfaction of a finished shoe on every trial. The pitfall here is assuming your task analysis matches the child's actual needs. I once wrote a ten-step handwashing procedure that looked perfect on paper. The child couldn't manage the roll-up sleeves step and kept having to re-start the whole chain. We simplified to a five-step version that omitted the sleeve step entirely and taught sleeve management as a separate skill later. The child completed handwashing independently in two weeks with the simplified version versus making no progress for a month with the longer one. Fewer steps beats more steps when the extra steps are barriers, not building blocks.
Video Modeling
Video modeling uses recorded videos as the instructional stimulus. The child watches a video of someone—could be a peer, a sibling, or themselves—performing a target skill, and then practices that skill. It's particularly effective for social skills and pragmatic language because it allows repeated exposure to a modeled behavior without the social pressure of a live model. Research shows video modeling can produce generalization to untrained settings, which is something traditional DTT struggles with. The limitation is that not all children engage with video the same way. Some kids will watch the video but then completely fail to imitate from it. I had a case where a 7-year-old would watch peer modeling videos for turn-taking with zero transfer to actual playground interaction. We switched to video self-modeling—recording him already doing the behavior correctly and then editing it so it looked like he was performing it smoothly—and that's when the generalization happened. The self-model removed the gap between "someone else does this" and "I can do this." It took about three extra hours of filming and editing but cut three months off the typical timeline for that skill acquisition.

Common Mistakes When Implementing ABA Techniques
The biggest mistake I see is treating these techniques as mutually exclusive. A good program weaves DTT, NET, FCT, and ABI together throughout the day. A child might have a 15-minute DTT block for academic skills, use NET during snack time for mands, practice FCT during transitions, and have an ABI in place for a known trigger like loud noises. The techniques aren't competing options. They're tools for different contexts. Another mistake is failing to collect meaningful data. You can run a hundred DTT trials and if you're not tracking correct, incorrect, and no-response rates, you have no way of knowing whether the child is actually learning. I've seen programs run for months without anyone updating a single data sheet. The child makes no measurable progress and the team assumes it's a motivation issue when it's really just poor documentation. Keep the data simple—frequency counts per session, duration for behavior, percentage correct for skill acquisition. Anything more complex than that usually ends up incomplete because it's too tedious to maintain. The third mistake is not fading prompts quickly enough. A child might be using a physical hand-over-hand prompt for three months on a skill that they could have been doing with a gestural prompt within two weeks. The longer you leave a prompt in place, the harder it is to fade later. Set a rule for yourself: if a child can perform a skill with a gestural or visual prompt alone for three consecutive sessions, the physical prompt is no longer necessary. Move on. Prompt dependency is one of the most common reasons skills don't generalize outside of therapy.
When ABA Techniques Don't Work Well
It's worth being honest about where ABA falls short. Children with severe intellectual disabilities or significant neurological differences may not respond to traditional reinforcement-based approaches in the same way. DTT, in particular, can be frustrating and ineffective for children who struggle with joint attention or have limited symbolic understanding. In those cases, pairing ABA with developmental approaches like DIR/Floortime or SCERTS often yields better outcomes than sticking rigidly to one model. Another limitation is the potential for burnout. High-intensity ABA programs often call for 20 to 40 hours per week. That level of intensity works for some children and families, but it's unsustainable for others. I've seen siblings of autistic children report strained relationships because the family's entire life revolved around therapy hours, data collection, and generalization practice. The child learned the skills, yes, but the family system took a real toll. Sometimes a lower-intensity program with a focus on quality of life and family wellbeing produces better long-term outcomes than a high-intensity program that exhausts everyone. If you're looking for resources, the Behavior Analyst Certification Board website has a list of certified practitioners and published guidelines. The Association for Behavior Analysis International maintains a directory of professionals and some free educational materials. BACB also publishes the ethics code and the professional and ethical compliance guidelines, which are useful for understanding what qualified ABA services should look like. There are also several YouTube channels run by BCBA practitioners that walk through technique demonstrations, though I'd always verify that the credentials shown are current.


