The mess you make when you first try concept analysis
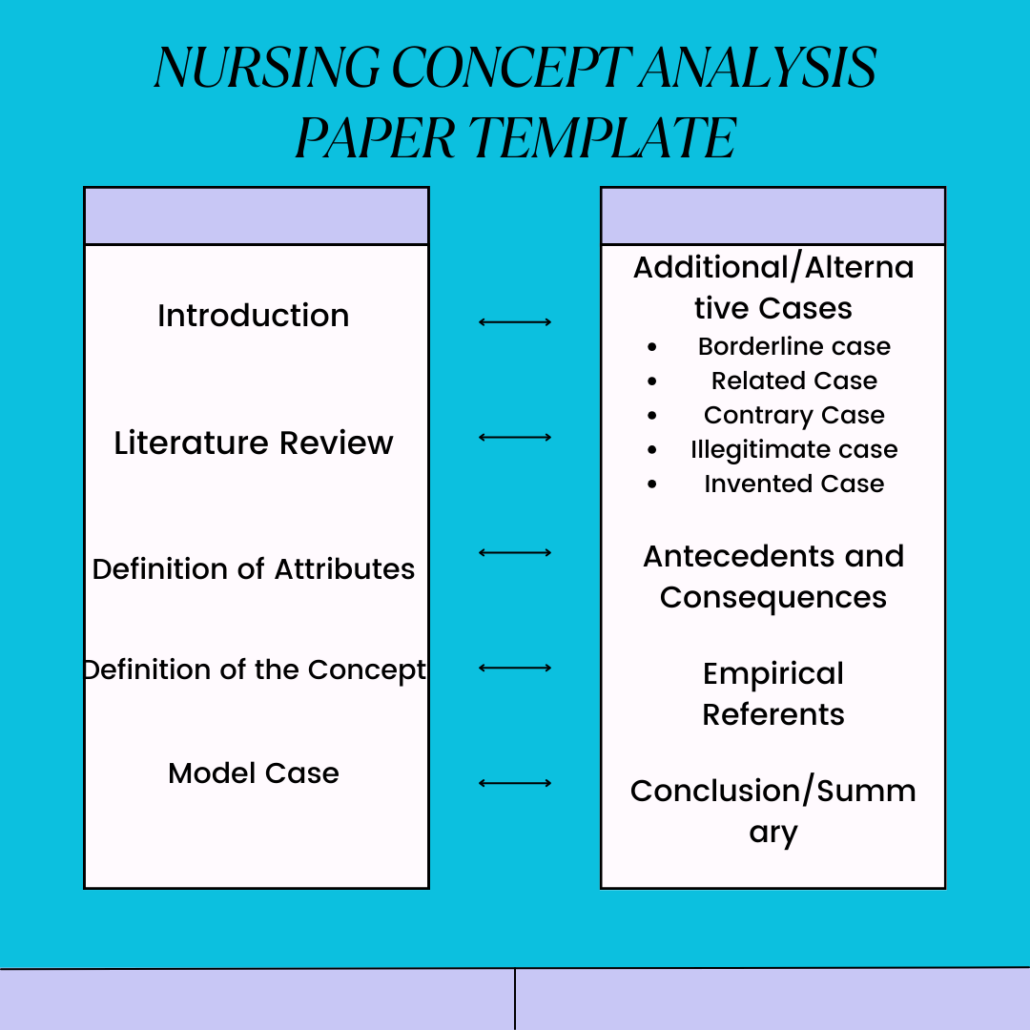
I spent three years as a PhD advisor before I stopped pretending I enjoyed reading first drafts of concept analyses. The method itself is straightforward. Walker and Avant's nine-step framework has been the standard since 1983. You pick a concept, define its attributes, identify a model case, build borderline cases, determine antecedents and consequences, and finish with empirical references. Most nursing students nail the mechanics in the template but produce something that reads like a dictionary entry padded to 4,000 words. The problem isn't the steps. It's that students treat concept analysis like a fill-in-the-blank exercise rather than an argument about what a concept actually means in practice. You are not cataloging synonyms. You are mapping the boundaries of a term that clinicians use every day without realizing they are using it loosely. The gap between textbook definition and clinical usage is where your paper lives or dies.
What actually happens when you work through Examples Of Concept Analysis In Nursing
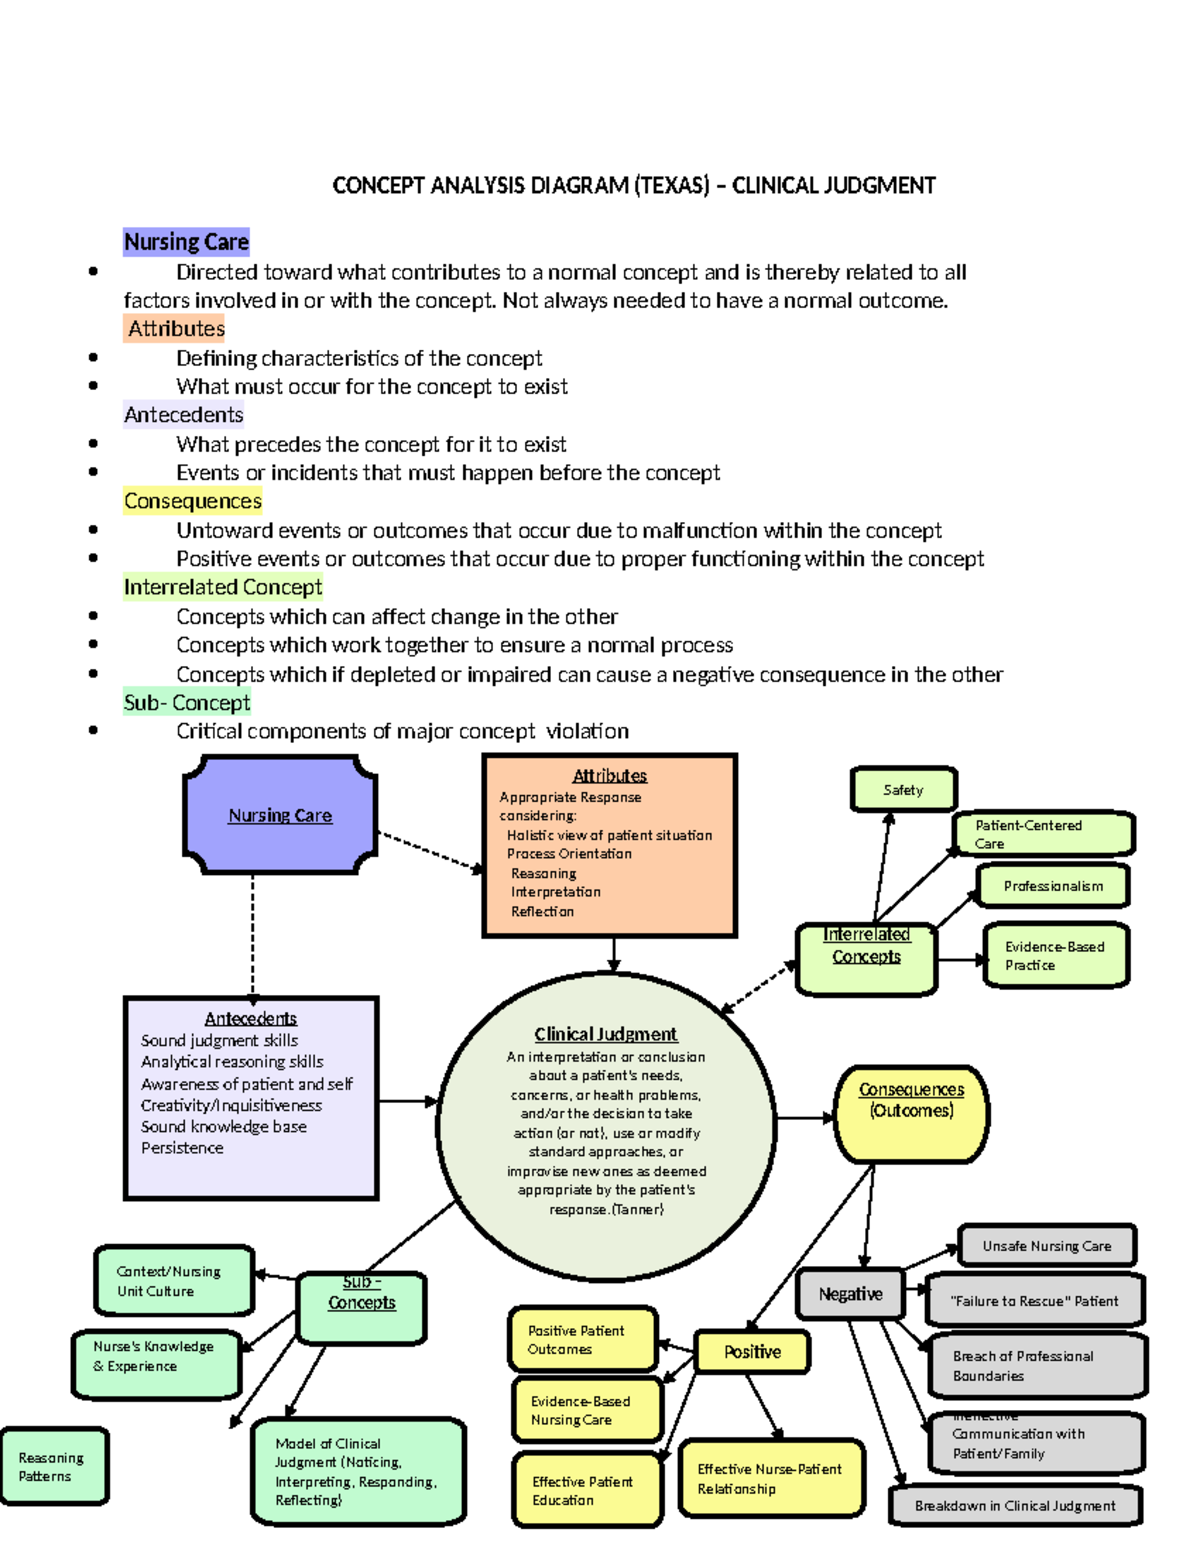
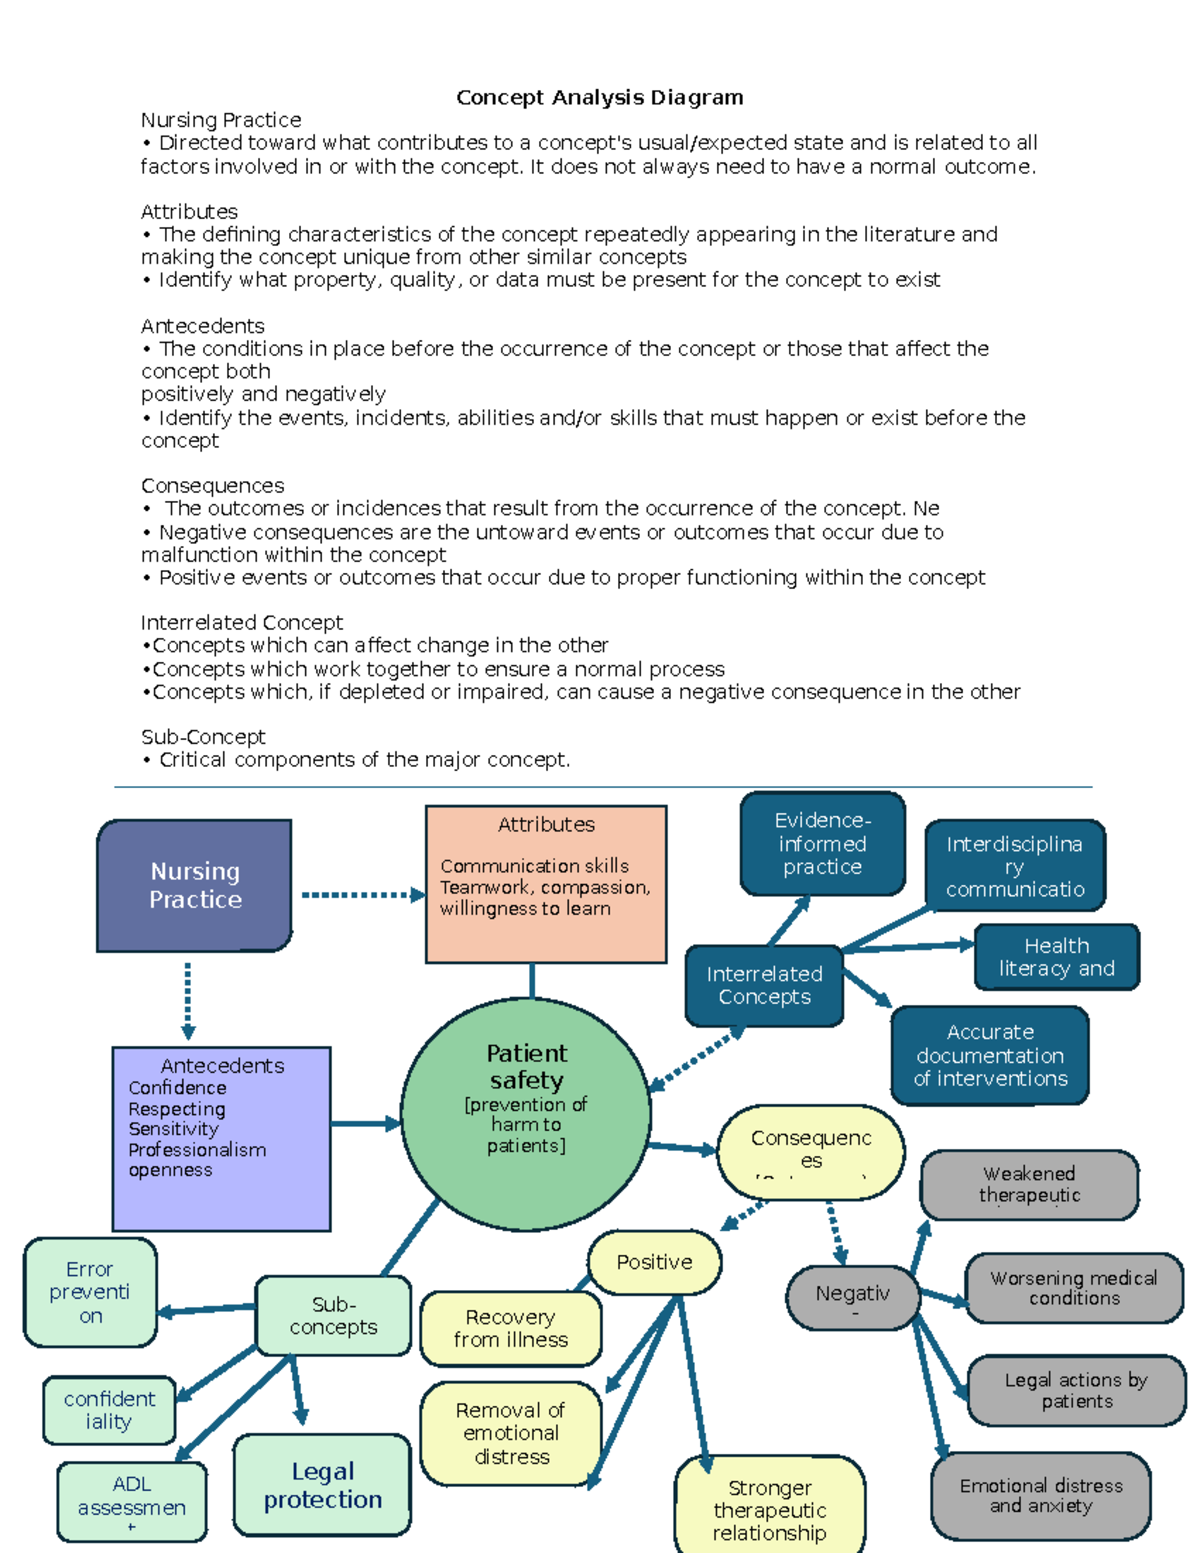
Take the concept of resilience in critical care nursing. A surface-level analysis lists protective factors and calls it a day. A working analysis distinguishes between psychological resilience, which maps onto established personality constructs, and clinical resilience, which describes the capacity of nurses to maintain functioning after repeated traumatic exposures. These are overlapping but not identical. If you conflate them, your literature search pulls from positive psychology journals when you actually need studies on burnout and post-traumatic growth in ICU settings. I have seen two thesis students lose six weeks because they started from a single source definition of resilience without first clarifying which version they were analyzing. Here is the step I wish more programs emphasized: the preliminary work. Before you open Walker and Avant, you need to understand how the concept functions in your discipline. That means skimming recent nursing literature, not for citations, but for patterns. When do authors use the term? What assumptions are baked into that usage? Which related terms appear nearby? This takes about two to three hours for a standard topic and usually reveals that your initial concept choice is either too broad or already thoroughly analyzed by someone else. Attributes are the core of the whole exercise. They are the empirical markers that allow you to recognize the concept when you encounter it. A common mistake is turning consequences into attributes. Caring leads to patient satisfaction. That is a consequence, not an attribute of caring. Attributes describe the concept itself. Consequences describe what follows from it. Mixing these two categories is the single most frequent error I see in student papers, and it corrupts everything built on top of it.
Why the standard framework leaves things out
Walker and Avant give you structure. They do not give you a solution for concepts that resist clean boundaries. Moral distress is one of those. The attributes shift depending on whether you are reading from a bioethics lens or a frontline nursing lens. The same term describes something quite different in each tradition. I encountered this directly when advising a student who was stuck for weeks. She could not nail down attributes because the existing literature used the same word to describe two different phenomena. The workaround was simple but easy to miss: she reframed the concept not as moral distress broadly but as moral distress among new graduate nurses. The narrower scope collapsed the ambiguity enough to produce actual attributes she could work with. It also made the resulting analysis more useful for its intended audience. Another practical issue worth mentioning: the model case. Students often write a vignette that is so perfectly aligned with every attribute that it stops being realistic. A model case should demonstrate the concept without dramatizing it. If your case requires a nurse to exhibit every attribute simultaneously under impossible conditions, you have built a fantasy, not an illustration. I usually tell students to write the borderline case first. The borderline case forces you to identify which attributes are essential and which are optional. Once you know what can be missing without the concept dissolving, the model case writes itself. Antecedents and consequences are where concept analysis connects to actual research. This is the part that turns your paper from a philosophical exercise into something useful for nursing practice. If you are analyzing nurse-sensitive outcomes, your consequences should map onto measurable indicators. If you are analyzing a process concept, your antecedents should point toward conditions that trigger the phenomenon. Antecedents are what precede the concept. Consequences are what follow. Keeping this directional relationship clear prevents the circular reasoning that shows up in too many published analyses.
Get the Full Details
Pitfalls that waste time and ruin credibility
Definitions without citation are a red flag. Every definition you include needs a source. Paraphrasing a definition and omitting the reference is academically careless, not creative. I reject papers on sight when the author presents their own definition as if it carries authority without backing it up. Concept analysis is supposed to clarify meaning, not invent it. Your analytical definition at the end of the paper should synthesize what the literature says, not introduce a brand new interpretation that appears without warning. Another trap is the literature review that is too narrow. Some students search one database and stop. That works for well-established concepts. It fails for emerging ones. If your concept is relatively new or contested, you need multiple databases, interdisciplinary sources, and possibly gray literature. The scope of your review should match the state of the field. A concept like therapeutic presence has enough literature that a single database search might suffice. A concept like diagnostic momentum in nursing assessment does not. I usually suggest a baseline search across CINAHL, PubMed, and Scopus, then expand only if the attribute list looks thin or contradictory. The empirical referent step is where most students struggle. An empirical referent is the observable indicator that demonstrates the concept exists. For abstract concepts like hope, this is difficult. For concrete concepts like pain, it is relatively straightforward. I had a student analyze the concept of dignity in palliative care and get completely stuck on this step. The workaround was to shift from searching for a single universal indicator to identifying a set of context-dependent indicators. Dignity means different observable things in oncology, geriatrics, and emergency care. Acknowledging that variation actually strengthened the paper rather than weakening it.
A practical workflow that does not feel like busywork
Start by writing a working definition in one paragraph. Do not submit it to a source yet. Just write what you think the concept means based on your initial reading. This becomes your baseline. When you encounter conflicting definitions in the literature, you can see exactly where your intuition diverges from the scholarship. That divergence is data. It tells you what is contested and what needs further investigation. Then build your attribute list from the literature, not from your intuition. Go through relevant sources, highlight every descriptive phrase that answers the question "what does this concept look like when it is present?" Group similar descriptors. Remove outcomes and antecedents. What remains should be the core attributes. This process typically takes four to six hours for a standard concept if you are working carefully. Rushing it produces a list that is either too generic to be useful or too narrow to capture the concept's actual meaning in nursing practice. Case development follows the attributes. Write a model case that contains every attribute. Write a borderline case that omits one or two key attributes. Write a contrary case that resembles the concept but lacks its essential features. These three cases together test the robustness of your attribute list. If your model case also fits the contrary case description, your attributes are not discriminating enough. Go back and sharpen them. This iterative testing is the part of concept analysis that most programs skim over, and it is also the part that determines whether your analysis holds up under scrutiny.
The analytical definition at the end should be tight. One or two paragraphs maximum. It synthesizes the attributes, acknowledges the scope, and distinguishes your conceptualization from competing definitions. Students tend to pad this section with summary statements about why the concept matters. The definition stands on its own. Let the reader draw the significance. Over-explaining significance here comes across as defensive and weakens the overall argument.

When concept analysis is the wrong tool
I want to be blunt about this because it matters for your grading and for your actual research program. Concept analysis is not a substitute for systematic review. It does not answer questions about intervention effectiveness. It does not establish causality. If your research question is "does X improve Y," concept analysis will not help you. It helps when the question is "what do we actually mean by X in this context?" The distinction is important and not always respected in nursing programs that assign concept analysis as a generic writing requirement. There are also concepts that resist analysis altogether. Highly operationalized terms like blood pressure or dosage do not benefit from this approach. They already have precise, standardized definitions. Using Walker and Avant on such terms produces redundancy, not insight. Save the method for concepts that are theoretically rich but clinically fuzzy. Terms like caring, empowerment, cultural humility, and self-efficacy are solid candidates. Terms that are already locked into measurement tools are not. If you are working with a concept that has extensive quantitative measurement literature, consider a scoping review instead. It covers similar conceptual ground but provides more structured synthesis and better visibility into how the concept has been operationalized across studies. Concept analysis and scoping review are complementary methods. They are not interchangeable. Knowing which one fits your question is itself a sign that you understand what you are doing.
The examples that work best in nursing tend to share a few characteristics. They are clinically relevant, theoretically contested, and empirically observable in some form. The analysis should produce something a practicing nurse can use to think more clearly about the concept, not just something a grader can check off. That balance between academic rigor and practical clarity is harder to achieve than the nine steps suggest. But it is the only reason the method survives this long in nursing education.