Root Cause Analysis Is Just Asking Why Too Many Times Until Something Breaks
I have spent more years than I care to admit chasing down problems that looked like symptoms on the surface but turned out to be structural issues buried deep in process design. The most common mistake I see people make is stopping the analysis too early. They find the obvious cause and call it a day, then wonder why the same problem shows up three months later. That is not root cause analysis. That is a guess with extra steps. Let me walk through a few real scenarios. A mid-sized logistics company had a 40% error rate on their warehouse picks during overnight shifts. The easy answer was "train the staff better." That fixed it for about six weeks before the numbers drifted back up. The actual root cause, which took three weeks and two failed investigations to uncover, was that the barcode scanner mounts had been positioned at an angle that forced workers to contort their wrists into positions that were mechanically awkward. Fine motor control drops significantly when your wrist is bent past 30 degrees, and the pick verification step requires fine motor work. The fix cost $200 in hardware and repositioned the scanners. Error rate went to under 2% and stayed there for eighteen months. Another case involved a software company whose customer support tickets related to login failures spiked every Tuesday at 10 AM. Random, right? It turned out their backup system was running automated credential rotation scripts at 9:45 every Tuesday, but the new credentials were not being pushed to their API gateway until 10:03. There was an 18-minute window where the primary auth servers had rotated keys but the gateway was still validating against the old ones. The workaround was not to change the script timing. It was to add a health check that prevented the gateway from serving traffic until the rotation was confirmed complete on both sides. This eliminated the failure window entirely.
Here is a less glamorous example from my own work. A manufacturing client kept having unexpected downtime on their CNC lines. The pattern was inconsistent, which is the worst kind of pattern. I walked the floor and noticed something nobody had documented: the compressed air supply had a micro-leak in line 4 that only manifested when the main compressor cycled on under load. The pressure drop was barely noticeable at the machine gauge because the gauge was mounted five feet downstream from the leak point, and the local reservoir cushioned the drop. But the controller saw it. When pressure dipped below 85 PSI, the CNC would throw an alarm and shut down as a safety measure. The leak was from a cracked fitting on a valve manifold that had been vibrating loose since 2019. I found it by listening. I did not need any fancy diagnostic tool. I used a screwdriver as a stethoscope against the manifold while someone cycled the compressor. The hissing was audible through the steel. Replacing the fitting cost eleven dollars. The repeated downtime was costing them roughly four thousand dollars per week in lost throughput.
The Methods People Actually Use
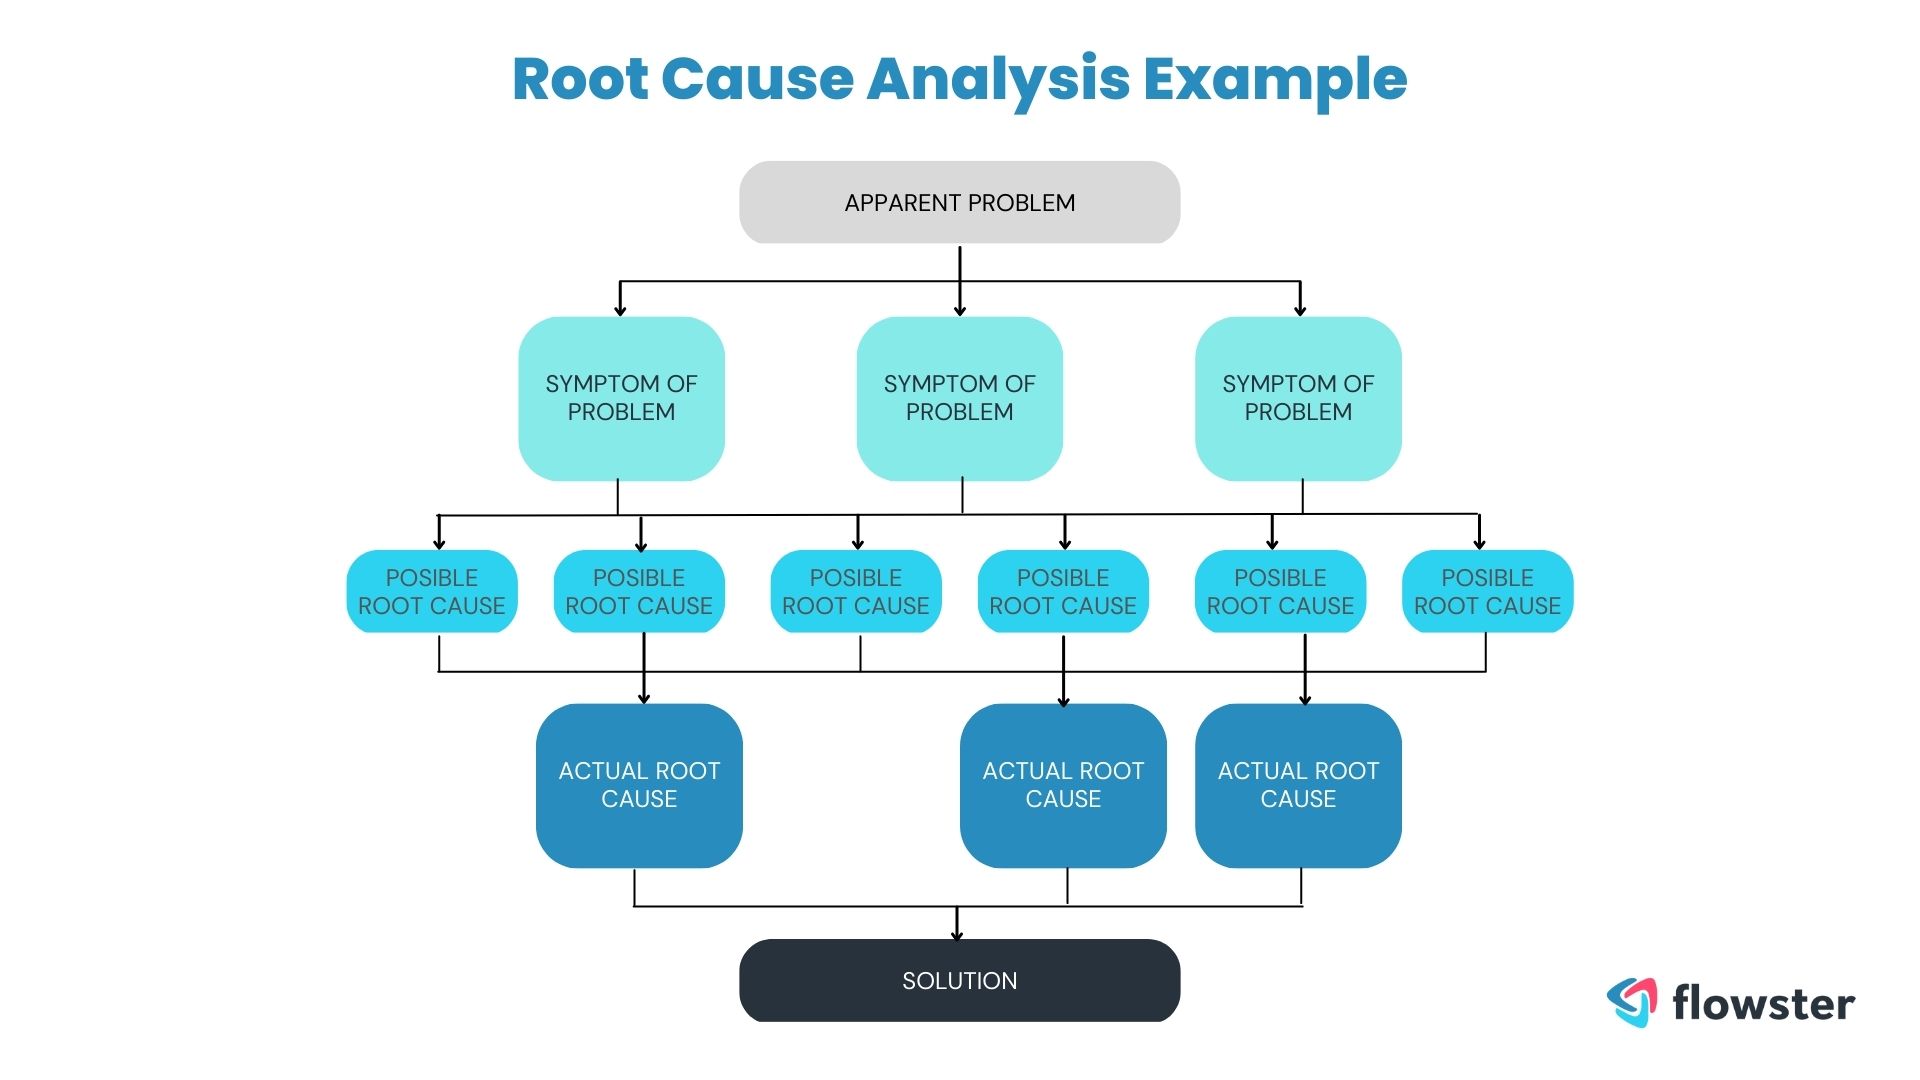
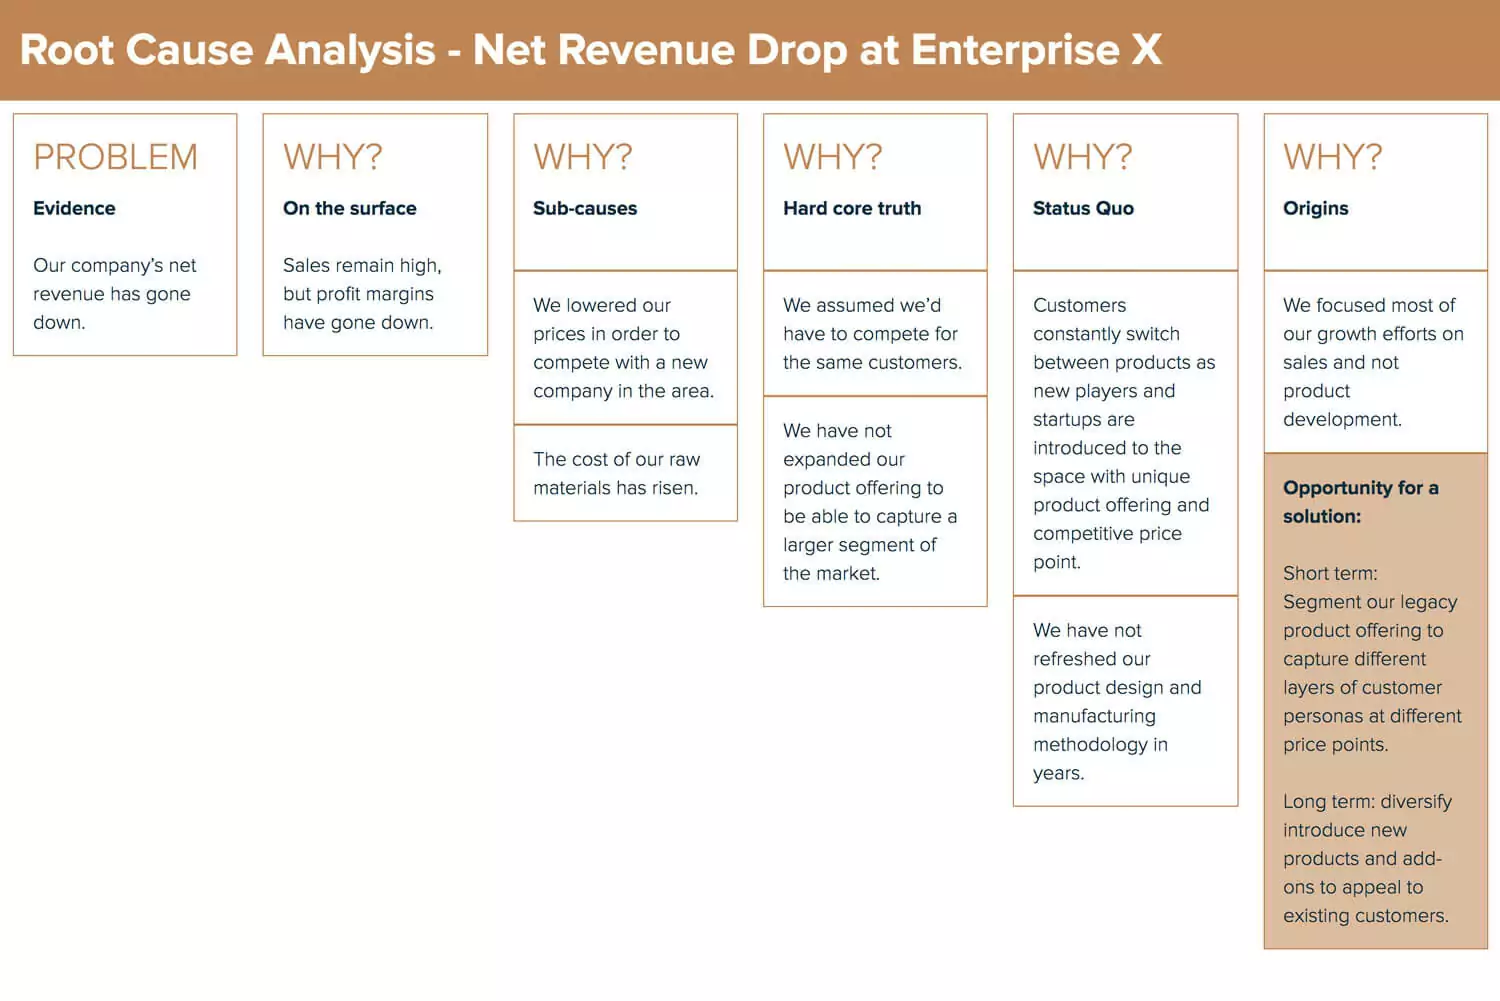
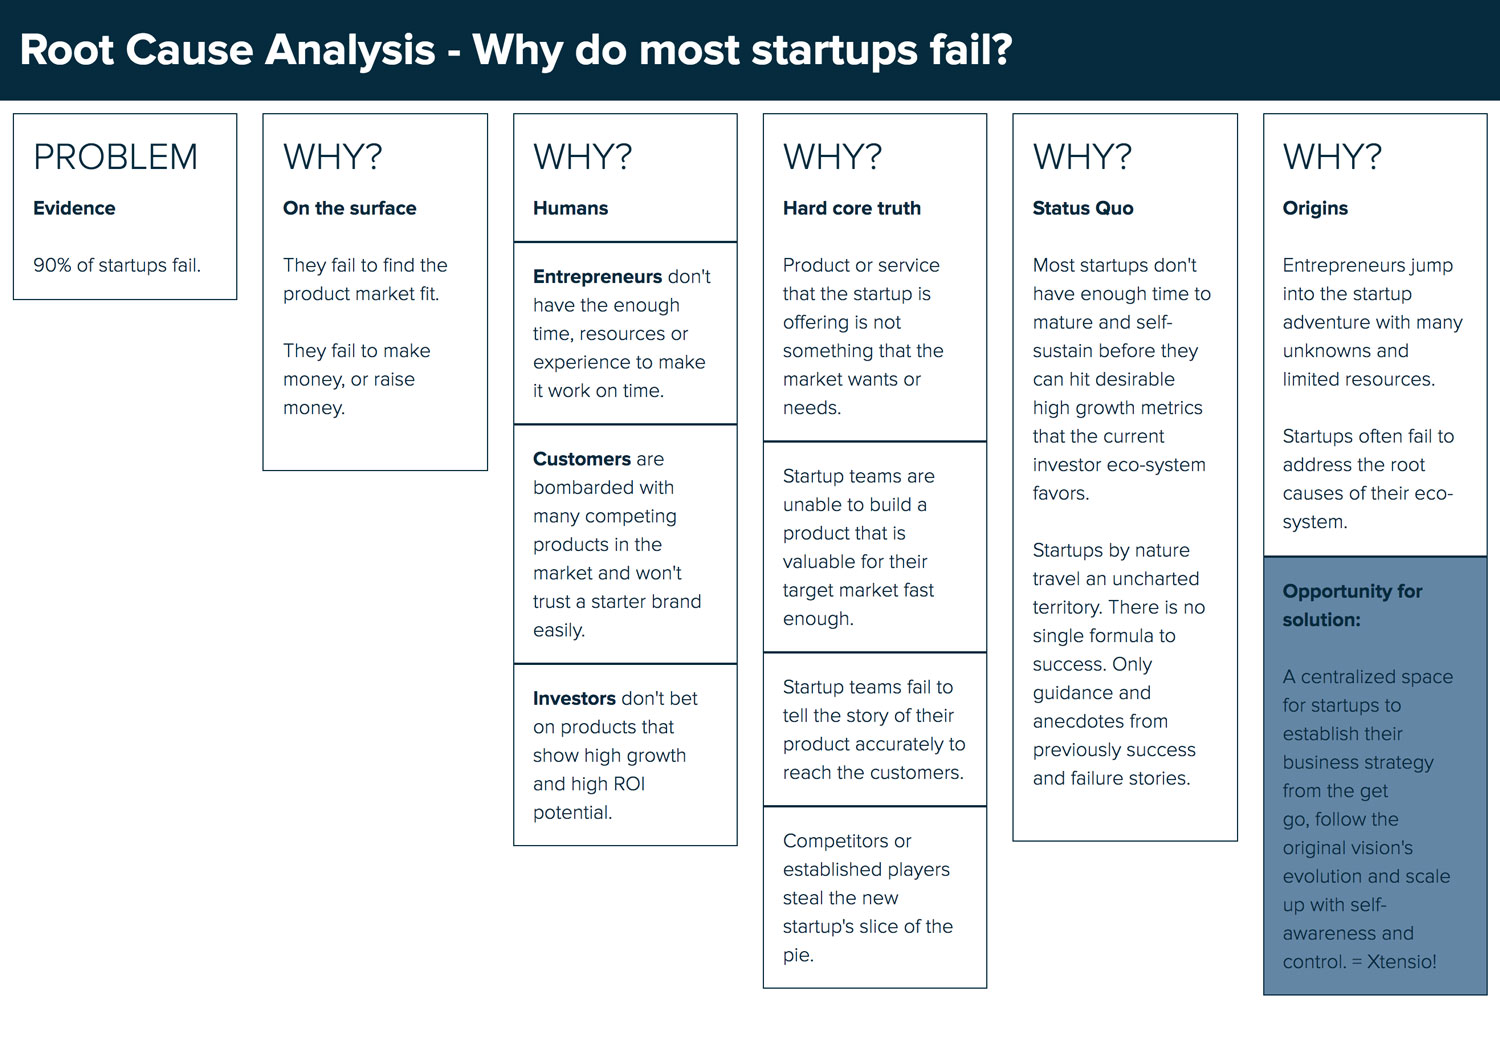
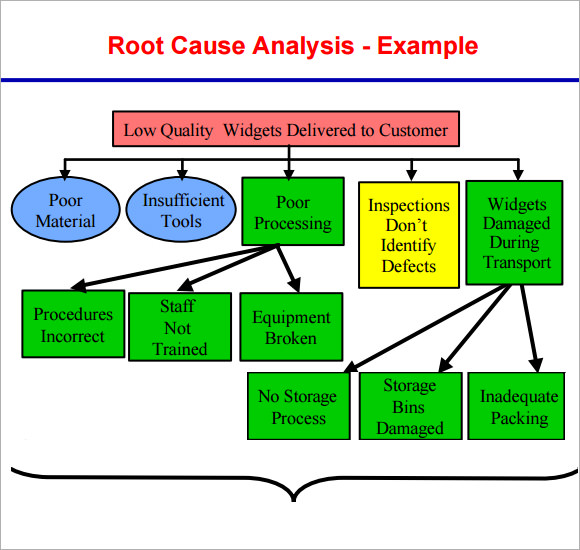
There are several approaches, and most of them are overcomplicated in the consulting world. The core methods are the Fishbone Diagram, the 5 Whys, Failure Mode and Effects Analysis, and the Is/Is Not matrix. Each has a use case. The 5 Whys is the fastest and most misunderstood. People treat it like a child's game instead of a disciplined interrogation of causality. The Fishbone diagram forces you to categorize potential causes, which prevents the tunnel vision that happens when you have a favorite theory. FMEA is the heavy artillery, best used when you have a complex system with multiple failure points and need to prioritize which ones to investigate first. The Is/Is Not matrix is underrated. It works by narrowing the problem space: here is what the problem is, here is what it is not, and the intersection points to the likely cause. One thing beginners miss: root cause analysis is not a solo activity. If you are the only person doing it, you will almost certainly miss at least one causal chain. The person who operates the machine, the person who maintains it, and the person who designed the process will each see different causal factors. A proper RCA session should include representatives from operations, maintenance, engineering, and quality. Even if they disagree, the disagreement surfaces assumptions that a single analyst would never question.
Get the Full Details
Where It Fails
Root cause analysis does not work well in environments where data is unreliable or incomplete. If your incident logs are inconsistent, or if your team writes incident reports with vague language like "malfunction" or "error" without any specifics, you are building an analysis on sand. Another failure mode is organizational pressure to produce a quick answer. When leadership demands a root cause within 24 hours, you do not get a root cause. You get a plausible story. In those situations, it is more honest to state the limitation upfront rather than present speculation as fact. I have seen analysts pad their reports with unnecessary jargon to make a thin analysis look deeper. It does not work. Someone who knows the system will spot it immediately. A scenario where RCA completely breaks down is when the root cause is external and uncontrollable. If your supply chain disruption is caused by a geopolitical event, or a supplier goes bankrupt due to market conditions outside your influence, no amount of root cause analysis will give you a preventive fix. In those cases, the exercise shifts from prevention to response planning. The framework is the same, but the deliverable changes from a corrective action plan to a mitigation strategy. Sometimes the root cause is human behavior, and treating that like a system problem is where most organizations stumble. Yes, you can design processes to be error-resistant. But if the root cause is a culture that penalizes reporting mistakes, no amount of process redesign will help because nobody will tell you about the mistakes in the first place. I worked with a company where the real root cause of their quality issues was that floor supervisors were hiding defects to protect their team's metrics. The numbers looked fine on paper. The product failed in the field. Fixing it required changing the incentive structure before any technical RCA could be effective.