
Breaking The Chain
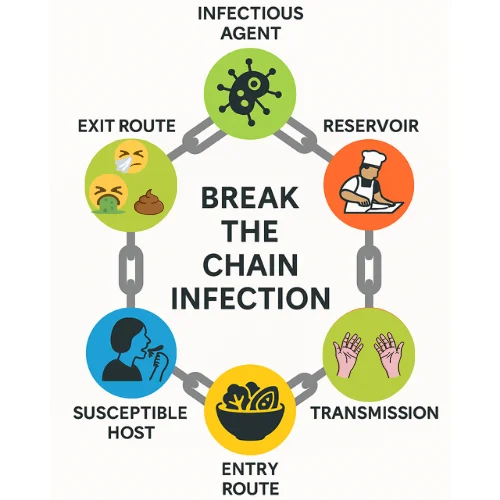
The chain of infection is the framework epidemiologists use to track how diseases move from one person to another. It has six links, and if you break any single one, the transmission stops. Most people learn this in nursing school and then forget about it until something actually goes wrong on the floor. I spent years in infection control, and the thing nobody tells you is that the chain isn't always clean. In practice, links overlap and some pathogens skip steps entirely. But the model still works as a diagnostic tool if you stop treating it like a rigid list and start treating it like a flowchart you can interrogate.
Examples Of The Chain Of Infection
Here's the basic structure. The infectious agent is the pathogen itself, whether that's a bacterium, virus, fungus, or parasite. The reservoir is where it lives and multiplies, which could be a human host, an animal, soil, or contaminated water. The portal of exit is how it leaves the reservoir, like coughing, bleeding, or defecation. The mode of transmission covers everything from direct contact to airborne particles to vectors like mosquitoes. The portal of entry is where it gets into the new host, usually through mucous membranes or broken skin. And the susceptible host is someone whose immune system can't fight it off effectively. A practical example. C. difficile in a hospital setting. The agent is Clostridioides difficile. The reservoir is the gastrointestinal tract of an colonized patient who may not even be symptomatic. The portal of exit is feces. The mode of transmission is primarily contact, via contaminated hands of healthcare workers or surfaces like bed rails and bathroom fixtures, because the spores survive for months on dry surfaces. The portal of entry is the mouth, since hand-to-mouth contact or contaminated food introduces spores. The susceptible host is someone who has recently taken antibiotics, which disrupts normal gut flora and allows C. diff to take over. Another example, something more familiar. Influenza. The agent is the influenza virus. Reservoir is the respiratory tract of an infected person. Portal of exit is respiratory droplets from coughing or sneezing. Mode of transmission is both droplet and contact, since people touch contaminated surfaces and then their faces. Portal of entry is the conjunctiva, nasal mucosa, or oral mucosa. Susceptible host is anyone without recent vaccination or prior immunity to that specific strain.
I remember one outbreak that kept us up for three weeks. It was VRE, vancomycin-resistant Enterococcus, moving through a surgical ward. The initial assumption was hand hygiene failure, which it always is until proven otherwise. We tracked every case, mapped the rooms, did environmental cultures. The breakthrough came when we realized the reservoir wasn't just colonized patients, it was the shared blood pressure cuffs. Every patient encounter used the same cuff, wiped down with alcohol wipes between patients, but alcohol doesn't kill VRE. We switched to single-patient-use cuffs and the transmission dropped to zero within four days. The link we broke was the mode of transmission, but only after we identified the actual fomite carrying it. Here's the part that trips people up. You don't need to identify all six links before you can intervene. In fact, waiting for a complete chain analysis delays response. Break the weakest link you can find, preferably the one that's cheapest and easiest to fix. Hand hygiene compliance is almost always a leverage point. Isolation precautions are the next easiest. Environmental cleaning comes after that because it's labor-intensive and harder to verify. Advanced nuance. Some chains have what I call ghost links, reservoirs you never detect because standard surveillance doesn't look for them. The classic case is asymptomatic carriers. A nurse colonized with MRSA in her nose doesn't know it. She touches a patient's wound, transfers the organism, and the infection takes hold. The reservoir was never identified through routine culturing because she showed no symptoms. The workaround is targeted screening in high-risk units, not universal screening, which is expensive and rarely cost-effective. Focus on patients being admitted to ICUs, transplant units, and oncology wards. You catch more cases per dollar spent.
Get the Full Details
Another counter-intuitive point. Breaking the chain sometimes creates a worse problem downstream. Widespread use of prophylactic antibiotics to protect susceptible hosts can select for resistant organisms, effectively making the next chain harder to break. I've seen this play out with fluoroquinolone prophylaxis in neutropenic patients. The initial infection rate dropped, but subsequent C. diff rates spiked at three times the baseline. The chain was broken for one pathogen and rebuilt for another. You have to weigh the trade-off explicitly rather than assuming intervention is net positive. Common pitfall. People conflate the portal of exit with the mode of transmission. They're different. The portal is how the pathogen leaves the reservoir. The mode is how it travels to the new host. A tuberculosis patient coughing is the portal of exit. Airborne transmission across a room is the mode. Confusing the two leads to wrong interventions. You'll put a patient on contact precautions when they need airborne, which wastes resources and leaves everyone else unprotected. One more edge case. Vector-borne chains don't fit neatly into the six-link model because the vector acts as both reservoir and mode of transmission simultaneously. Malaria is the textbook example. The Plasmodium parasite reproduces in the Anopheles mosquito, making the mosquito a reservoir, but the mosquito also carries the parasite to the next host, making it the mode. Don't force these into the standard framework. Use it as a starting point, then adjust for the biology of the specific pathogen.
The model breaks down completely for prion diseases and some chronic viral infections where the incubation period spans decades. Hepatitis B is borderline, with carrier states lasting decades, but it still fits if you're generous with the timeline. Prions don't fit at all because the reservoir and the agent blur together, and there's no clean exit or entry you can isolate. For those, you need a different mental model entirely. Practical takeaway. Learn the six links cold. Use them to structure your thinking when an outbreak hits. But don't worship the model. Real infections are messier than the diagram, and the people who break chains fastest are the ones who stop looking for perfection and start looking for the easiest point of intervention. That's usually hand hygiene. Sometimes it's a blood pressure cuff. Rarely is it the susceptible host, because changing a patient's immune status isn't something you can do on short notice.


