Working Through Axial Skeleton Identification in the Lab
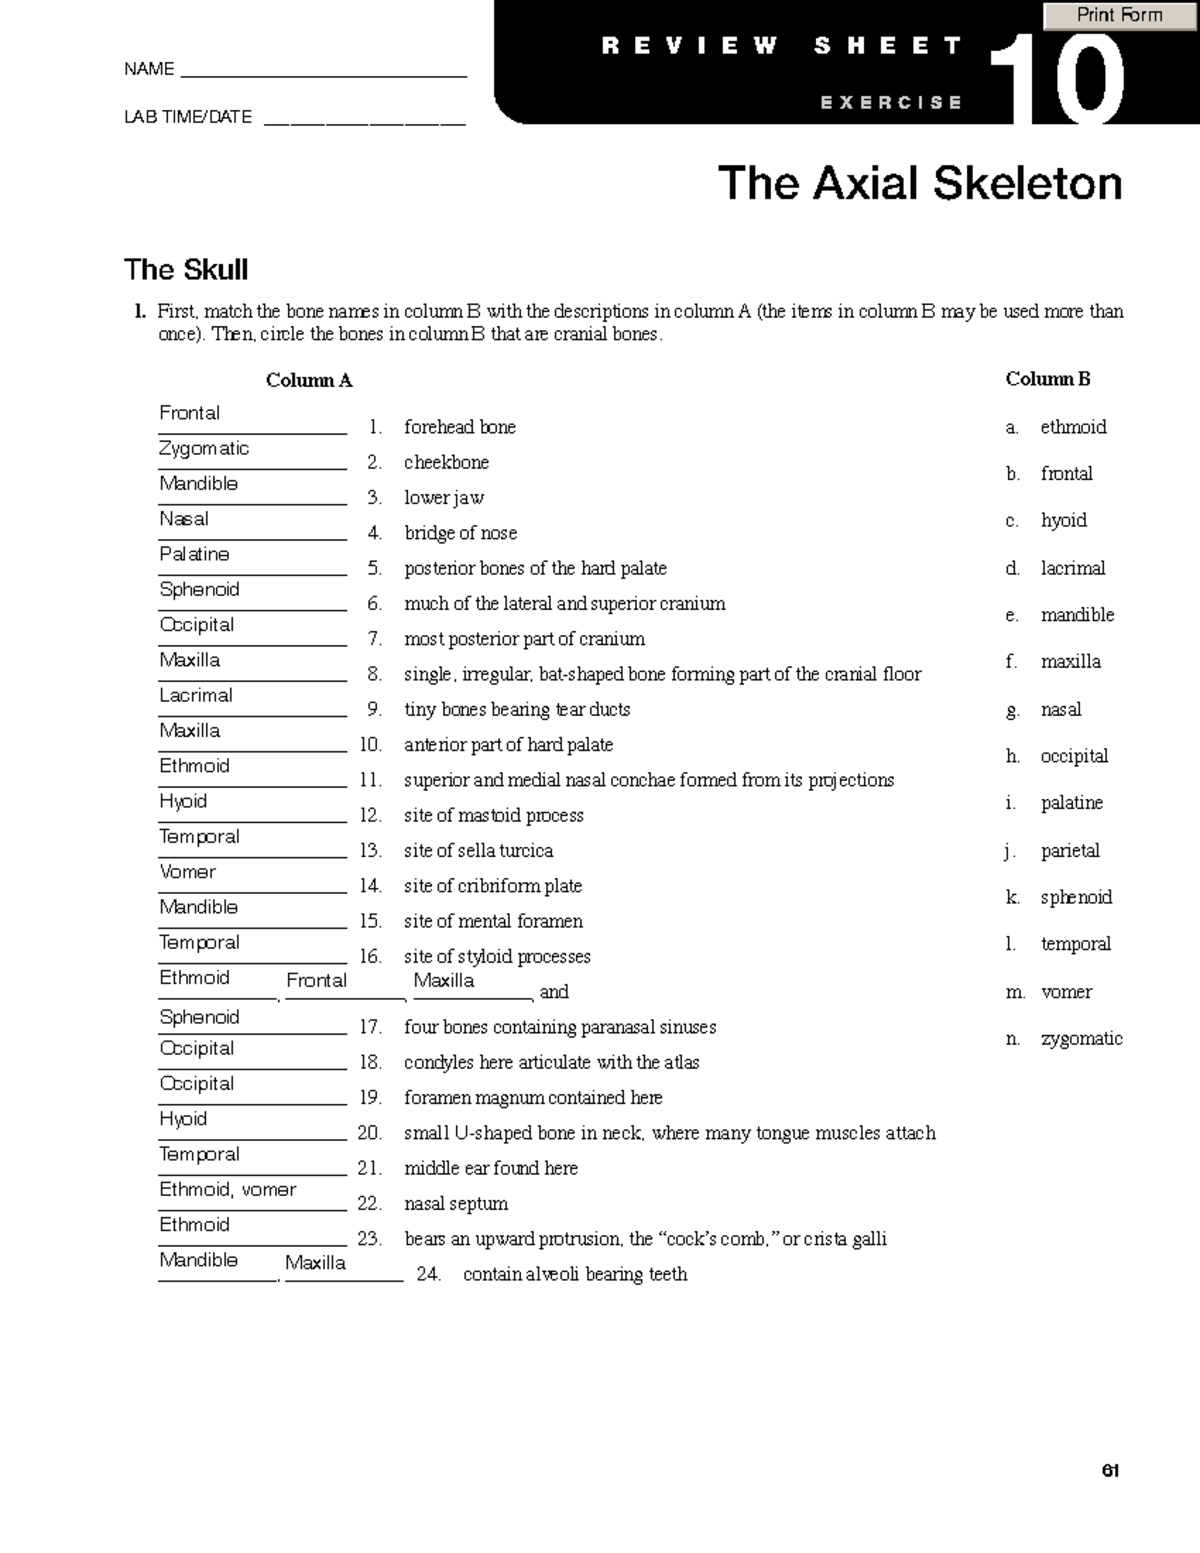
The axial skeleton breaks down into three main regions: the skull, vertebral column, and thoracic cage. That's the textbook version. In practice, Exercise 10 The Axial Skeleton is where students usually start struggling because the skull alone has twenty-six bones and telling a frontal bone from a parietal bone matters less than recognizing which features are reliable identifiers under exam conditions. Start with the vertebral column. Most people learn the order C1-C7, T1-T12, L1-L5, sacrum, coccyx. But here's the thing that doesn't get enough attention: vertebrae identification isn't about memorizing the order. It's about recognizing transitional morphology. The real test comes when you're looking at a specimen and need to determine whether a vertebra is cervical, thoracic, or lumbar without counting from the top. The trick is costal facets. Thoracic vertebrae have them on the body for rib articulation. If you see a full facet on the side of the vertebral body plus a half-facet at the pedicle-transverse junction, you're looking at a typical thoracic. No facets at all and a massive kidney-shaped body? Lumbar. I had a student once spent twenty minutes arguing with a lab partner over whether a specific vertebra was T1 or C7 because they were counting from the wrong end of the column. T1 has a full costal facet on the body that's easy to miss if the specimen is worn. C7 lacks a rib articulation entirely but has an unusually long spinous process. They were using the spinous process as their primary identifier, which is exactly backwards. The skull is where the real time goes. Sutures look straightforward on diagrams. On actual specimens, especially drier ones, they're often fused or irregular. The key landmarks are the superior temporal line, the external occipital protuberance, and the mastoid process. If you can't distinguish the petrous part of the temporal bone from the occipital bone at the skull base, you're going to have a rough time orienting anything. The foramen magnum is your anchor point. Everything else radiates from there.
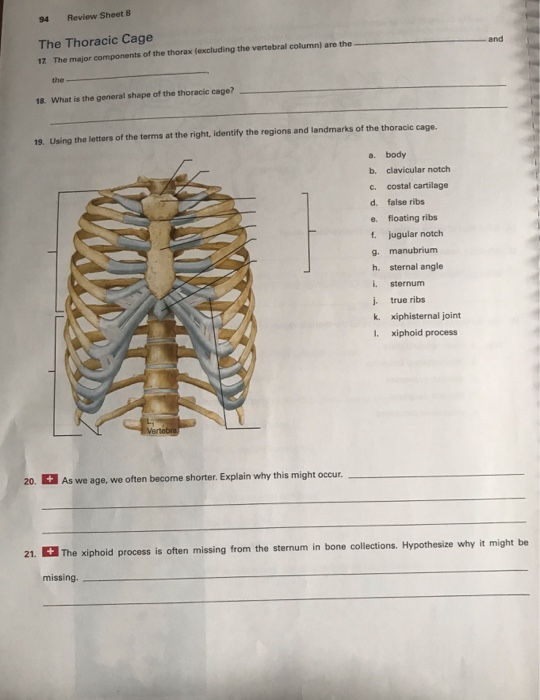
For the thoracic cage, most students handle the sternebrae fine. What trips people up is remembering that the true ribs are only pairs 1 through 7. Pairs 8 through 12 are false ribs, and 11 and 12 are floating. The clinical significance here is basic but worth knowing: fractured floating ribs rarely cause internal organ damage the way a broken lower true rib can. A fractured 9th or 10th rib on the right side sits right above the liver. On the left, you're thinking spleen. This comes up in practical exams more often than you'd expect. When I grade lab identification, I use a point system. The skull gets the most weight because it's the hardest region. Within the skull, the facial bones get more points than the cranial bones because students can identify a cranium by elimination but they consistently mix up the vomer and the perpendicular plate of the ethmoid. I make them handle both bones separately and point to the nasal septum. That separates people who actually know the anatomy from people who just memorized a list. One workaround I found that actually helps is having students trace suture lines with their fingertip instead of just looking. You learn the texture and the elevation changes that diagrams completely flatten out. It takes longer in the moment but it sticks better during recall. I also tell them to skip the hyoid bone on first pass. It's a single U-shaped bone with no articulations to other bones, which makes it look deceptively simple. Students waste time on it when they should be solidifying their vertebral column work first.
The main limitation of this exercise format is that most lab collections are incomplete. You'll get a skull missing several facial bones, or a vertebral column where the sacrum is separated from the coccyx and labeled vaguely. Some programs use plastic replicas instead of real specimens. Replicas are fine for learning proportions but they erase the very features you need to distinguish between similar-looking bones. If your program relies heavily on models, plan to spend extra time with actual cadaver specimens before your practical exam. The difference in texture and wear patterns is not something you can replicate from a diagram. A couple of the bone names change depending on which atlas you're using. The carpal bones, for instance, aren't part of the axial skeleton at all, but students routinely include them when listing components. The axial skeleton is strictly skull, vertebral column, and thoracic cage. Appendicular is everything else. Getting that boundary wrong costs easy points on any written section. If you're preparing for the practical, the highest-yield review is the vertebral column transitions. Know what C2 looks like versus C3. Know how T12 differs from L1. Those are the bones where morphology overlaps enough to cause real confusion, and they're the ones professors love to put on identification rounds.
Get the Full Details