Lab Setup and Procedure Basics
Exercise 21 Human Reflex Physiology is typically part of an undergraduate A&P lab sequence, testing the major reflex arcs and recording response times or presence/absence of various stimuli. Most labs use a wooden reflex hammer, a tuning fork for the Achilles test, and simple tools like a tongue depressor or the pointed end of a reflex hammer for the plantar response. The core tasks involve the patellar, Achilles, triceps, biceps, and plantar reflexes, with documentation of the reflex arc components for each. Start with the patellar reflex. Have your subject sit with legs dangling freely off the edge of the lab table. The thigh muscles should be completely relaxed. If the subject is tense, the reflex will be blunted or absent, which has happened to me multiple times with nervous students. The strike goes just below the kneecap on the patellar tendon, not on the bone itself. Tap briskly but don't mash into the tissue. A normal response is knee extension. I once spent ten minutes trying to elicit a response from a subject who kept clenching his quadriceps unconsciously. The fix was having him cross his arms and pull apart at the same time as the tap, which distracts the motor cortex and lets the spinal reflex fire normally. That's the Jendrassik maneuver, and it works by general facilitation of the reflex arc through ascending reticular activation. For the Achilles reflex, the subject lies prone or sits with the foot hanging off the table. Dorsiflex the foot gently and strike the Achilles tendon. Normal response is plantar flexion. Here's the counter-intuitive part most students miss: a brisk dorsiflexion before the tap actually sets up a more robust stretch. Don't just tap a floppy foot. The muscle needs to be at a slight stretch to trigger the muscle spindle afferents properly.
The triceps and biceps reflexes follow the same logic. Strike the tendon distal to the muscle belly. For the triceps, the arm hangs loosely and you tap the olecranon region. For the biceps, support the arm and strike the biceps tendon in the antecubital fossa. In both cases, the subject should not be trying to help or resist. Even mild voluntary contraction changes the response threshold significantly. The plantar reflex uses a blunt stimulus dragged along the lateral sole from the heel forward to the base of the toes, then curving medially across the ball of the foot. A normal adult response is downward curling of the toes. Upward toe extension — the Babinski sign — indicates upper motor neuron dysfunction. This is one of the most clinically significant tests in the entire lab and appears on practically every neurology board exam. I've seen students consistently miss this because they press too hard and the subject lifts their foot away before the stimulus completes its path. Use light, steady pressure and commit to the full sweep.
Recording and Analysis
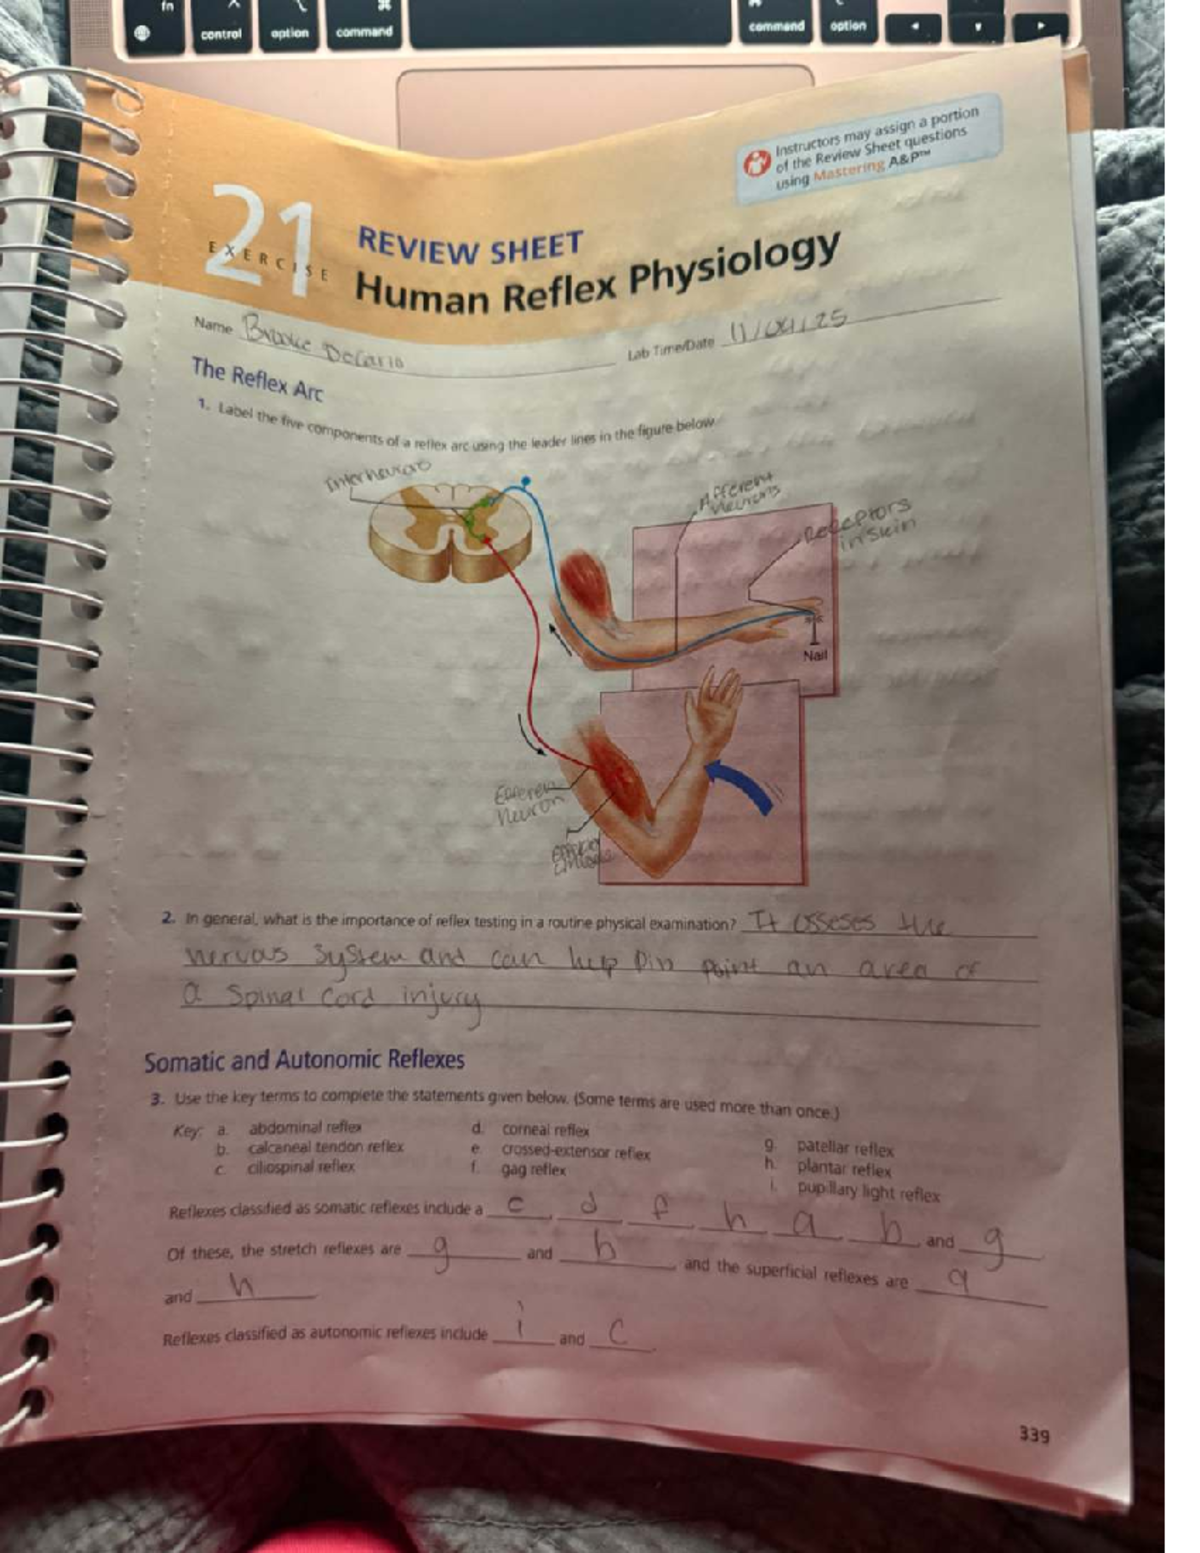
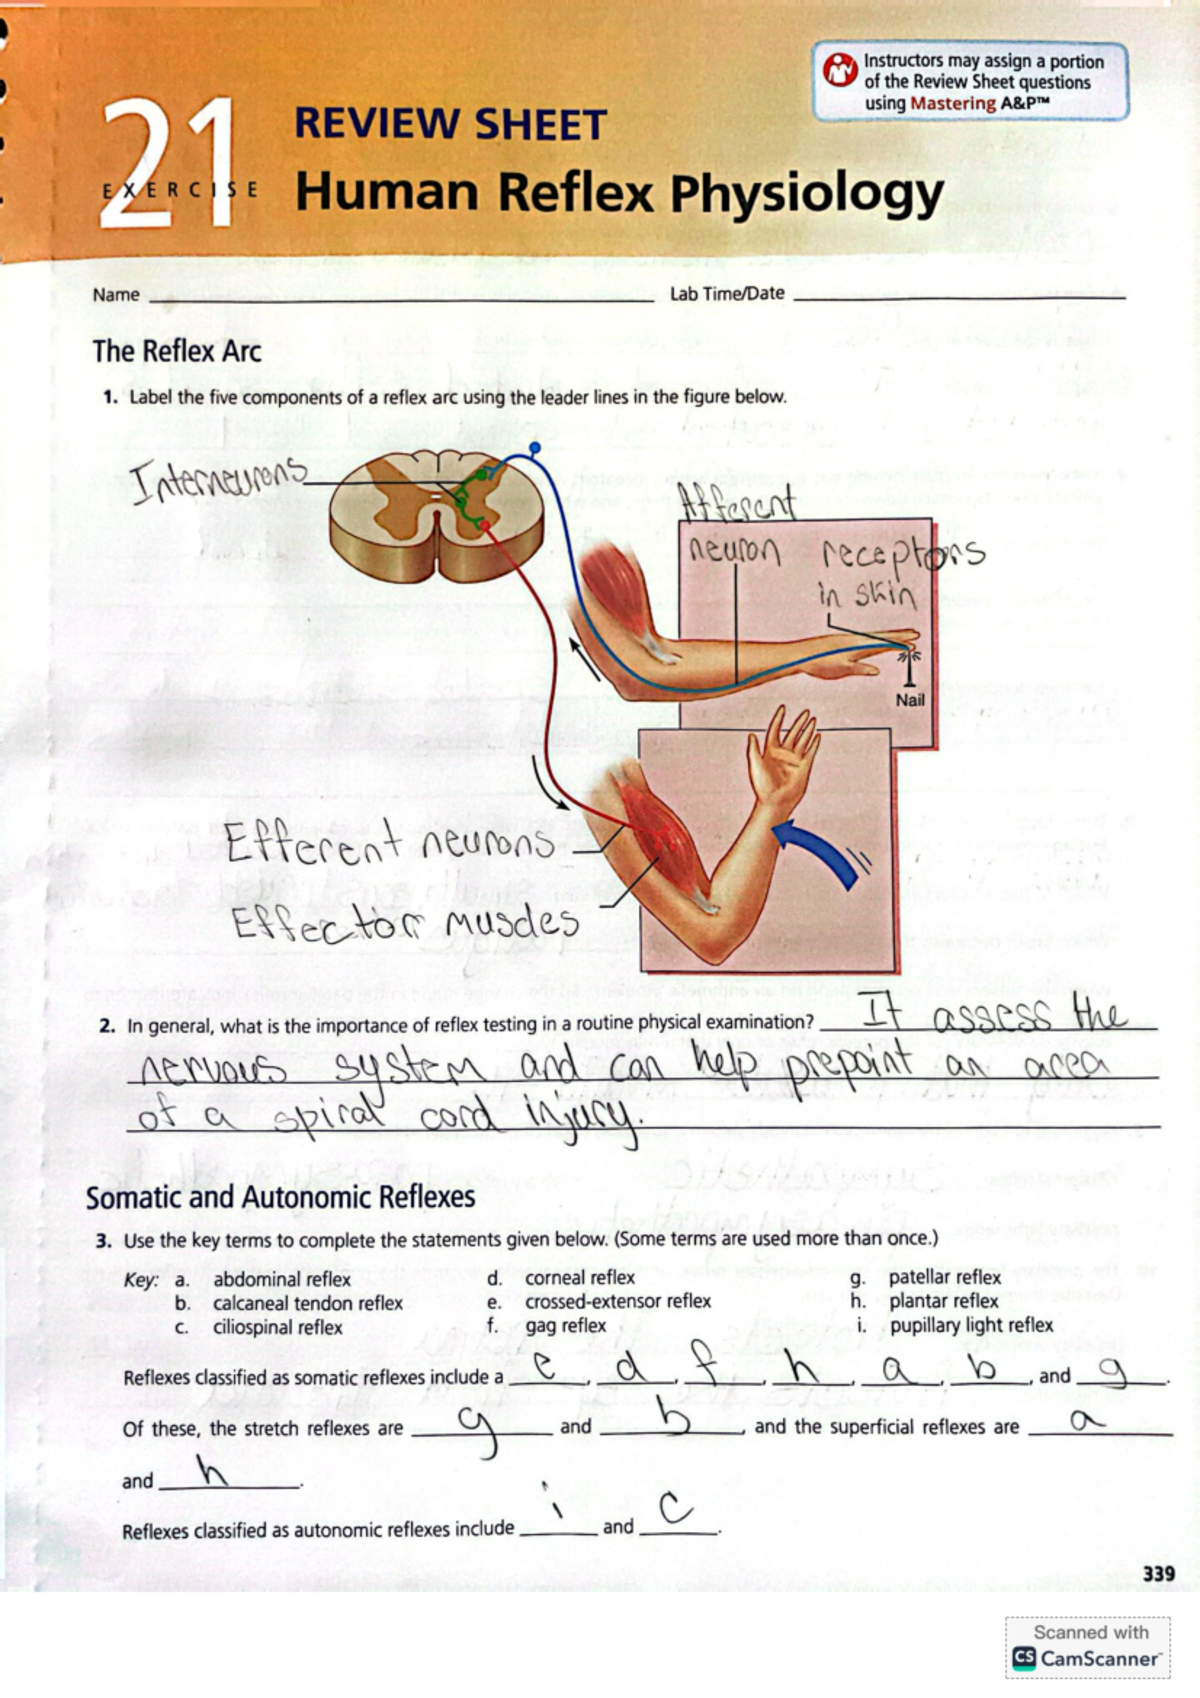
Your lab manual will ask you to identify the stimuli, receptors, afferent neurons, integration center, efferent neurons, and effectors for each reflex. The patellar reflex arc runs through L2-L4, the Achilles through S1-S2, and the triceps through C7-C8. The integration center for all monosynaptic stretch reflexes is the spinal cord itself — there is no brain involvement in the reflex loop. The brain becomes aware of the response after it has already occurred. This is why you can't voluntarily suppress a patellar reflex once the tap lands, even though you can raise the threshold beforehand through tension or distraction. Reaction time exercises often accompany this lab, where subjects respond to visual or auditory signals. These are fundamentally different from reflexes because they involve cortical processing. A simple reaction time to a visual stimulus averages 200-250 milliseconds, while an auditory reaction time is closer to 150-180 milliseconds. The difference exists because the auditory pathway has fewer synapses before reaching the motor cortex. Don't confuse reaction time with reflex time on your lab report. They measure completely different things.
Get the Full Details
Common Problems and What to Do About Them
Not everyone has easy-to-elicit reflexes. Some people are naturally hyporeflexive, especially if they have higher baseline muscle tone or anxiety. If you get inconsistent results on the patellar reflex, try the Jendrassik maneuver properly — the subject interlocks their fingers and pulls apart hard while you tap. This is the single most effective technique for enhancing diminished reflexes. I had a lab partner who could not produce a visible patellar response without it, and his reflexes were genuinely normal when tested properly. Another issue is the subject's position. If the leg isn't hanging freely, gravity is working against the extension. Same thing with the ankle — the foot needs to be unsupported. I've seen entire labs fail because the subject's other foot was planted on the floor, creating postural tension that suppressed the reflex arc. Have them swing both legs over the edge and let them dangle. For the triceps reflex, some subjects have particularly prominent olecranon processes that make the tendon hard to hit. In those cases, angle the hammer strike slightly more toward the posterior aspect of the elbow. You're aiming for the triceps insertion, not the bone.
Limitations and What This Lab Won't Tell You
This exercise demonstrates normal reflex arcs under controlled conditions, but it doesn't assess reflex quantity on a clinical scale from 0 to 4+. It doesn't test for clonus, which is a series of rhythmic contractions indicating hyperreflexia. It doesn't differentiate between upper and lower motor neuron lesions beyond the Babinski sign. If you're looking for a comprehensive neurological exam, this lab is just the introduction. Real clinical assessment requires testing for proprioception, vibration sense, and coordination — none of which appear in Exercise 21. The lab also can't account for individual anatomical variation. Some people have insertions that make certain reflexes nearly impossible to elicit through standard techniques. This doesn't necessarily indicate pathology. I once worked with a subject whose Achilles reflex was completely unresponsive despite normal neurological function, and it turned out his Achilles tendon inserted higher on the calcaneus than typical, making the standard tap location ineffective. If your lab includes the accommodation reflex or the pupillary light reflex, make sure the room lighting is stable. A dark room dilates pupils and makes the light reflex more dramatic, but inconsistent lighting between trials introduces error. Keep ambient light constant and have the subject fixate on a distant object before shining the light into one eye. The consensual response — constriction in the opposite eye — should also be noted and documented separately.
Key Takeaways for Your Lab Report
Focus on the distinction between reflex and reaction. Reflexes are involuntary, stereotyped, and mediated by the spinal cord or brainstem. Reactions are voluntary and require cortical processing. This distinction matters more than students usually realize, and it's a common exam question. Also remember that the stretch reflex is monosynaptic — one synapse between the sensory and motor neuron — while the withdrawal reflex is polysynaptic with interneurons involved. The patellar and Achilles are stretch reflexes. The withdrawal reflex comes into play when you step on something sharp, pulling the limb away through a multi-synaptic circuit that involves flexor muscles and reciprocal inhibition of extensors. Know your dermatomes and myotomes. L2-L4 for the patellar, S1-S2 for the Achilles, C5-C6 for the biceps, C7-C8 for the triceps. Mix these up on a midterm and you'll lose points fast. The somatic reflexes covered in this exercise are all part of the peripheral nervous system's rapid response machinery, and they exist to protect the body and maintain posture without requiring conscious input. That's the main point your instructor wants you to walk away with.