Why Most Students Mess Up the Cardiovascular Physiology Lab
I've watched dozens of students stumble through the same cardiovascular lab exercises over the years, and the problems are almost always predictable. The equipment is fussy, the timing is tight, and if you don't know what you're looking at on the ECG tracing, you're just guessing. I'm going to walk through Exercise 33 Human Cardiovascular Physiology the way I wish someone had shown me when I first ran this lab myself. The first thing that goes wrong in almost every session is the resting pulse and blood pressure readings. Students rush through them because they seem boring, then wonder why their data looks garbage three hours later. Sit for five minutes before taking any resting measurements. Not two minutes. Five. Your heart rate stabilizes differently depending on whether you just walked across the room or climbed stairs. When you measure blood pressure manually with a sphygmomanometer, listen for Korotkoff sounds. The first tapping you hear is systolic. The point where the sound disappears entirely is diastolic. There's an intermediate phase where the sound changes quality, and some people mistakenly record that as the diastolic reading. That's wrong. The sound muffling indicates turbulent flow returning to laminar, not the end of flow. Note it down separately if you want, but use the disappearance point for your recorded value.
I once had a student whose systolic readings varied by forty millimeters of mercury between trials. Turns out she was holding the cuff pump bulb in her hand the entire time the cuff inflated. The rhythmic compression from her thumb was actually occluding the brachial artery before the cuff even reached that pressure, making the gauge read artificially high. She wasn't even aware she was doing it. Squeeze the bulb, let go, and keep your hand completely still or off the arm entirely during inflation and deflation.
The ECG Tracing Section
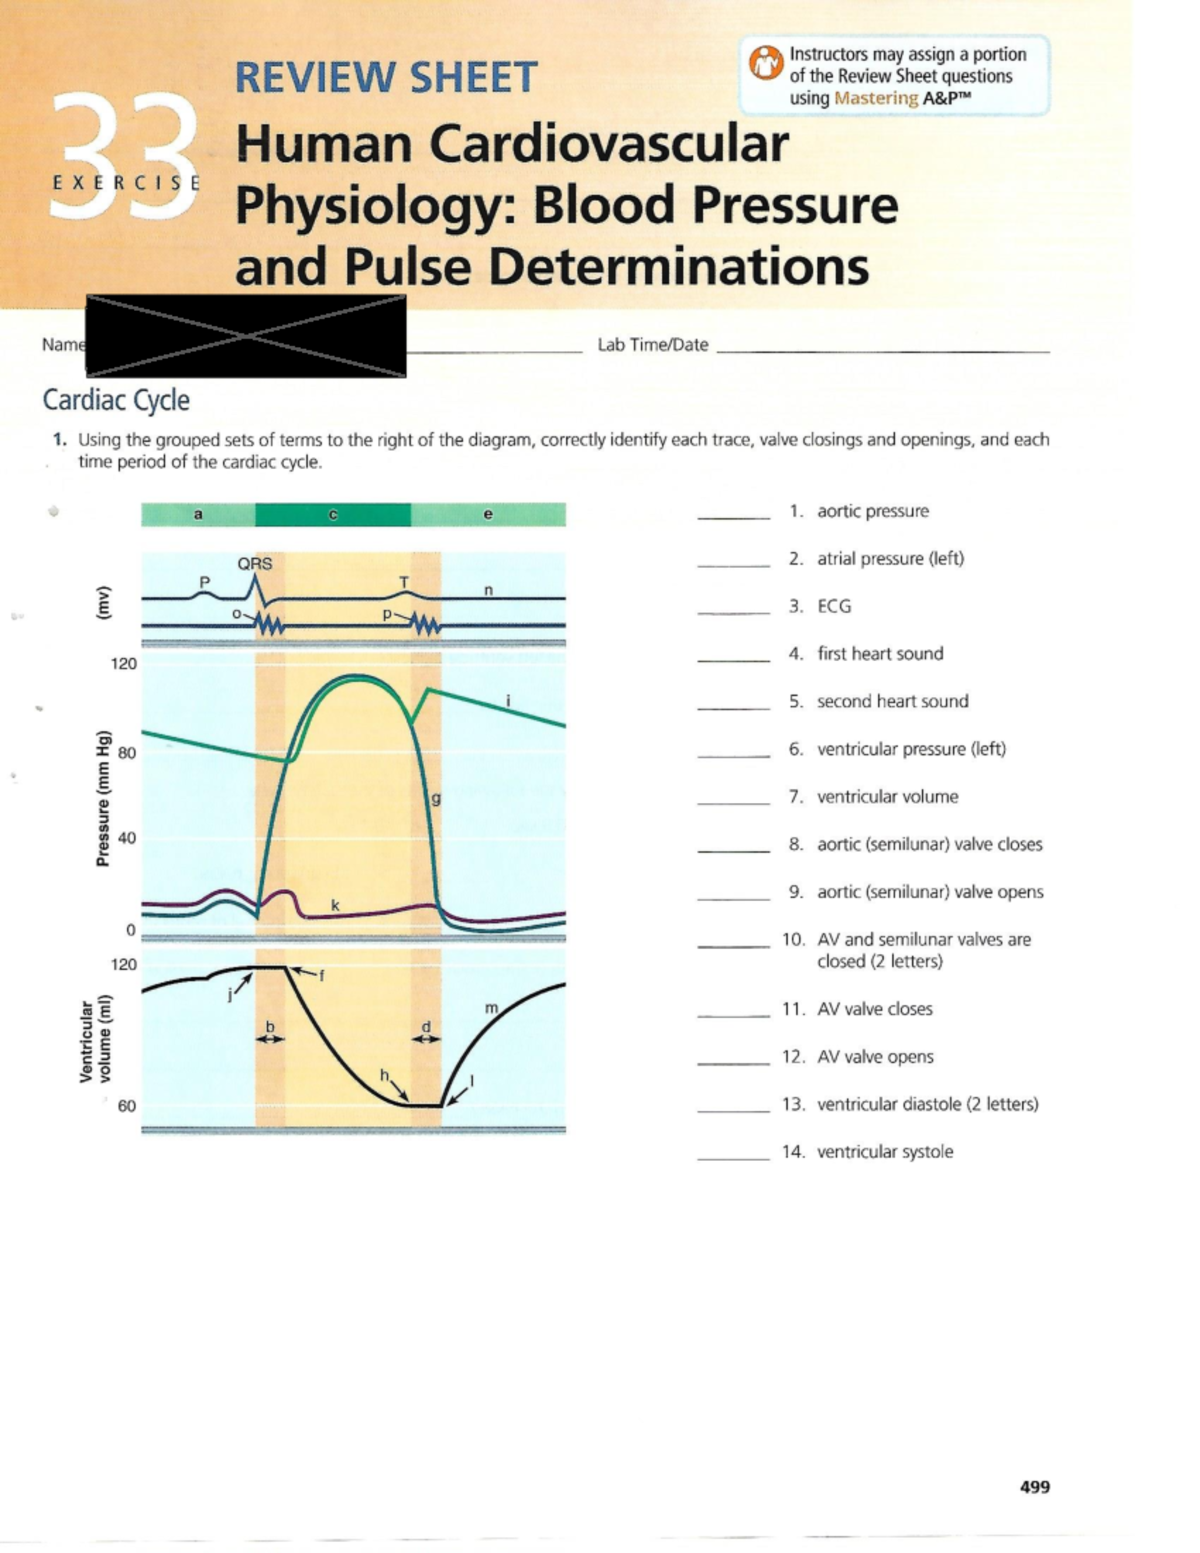
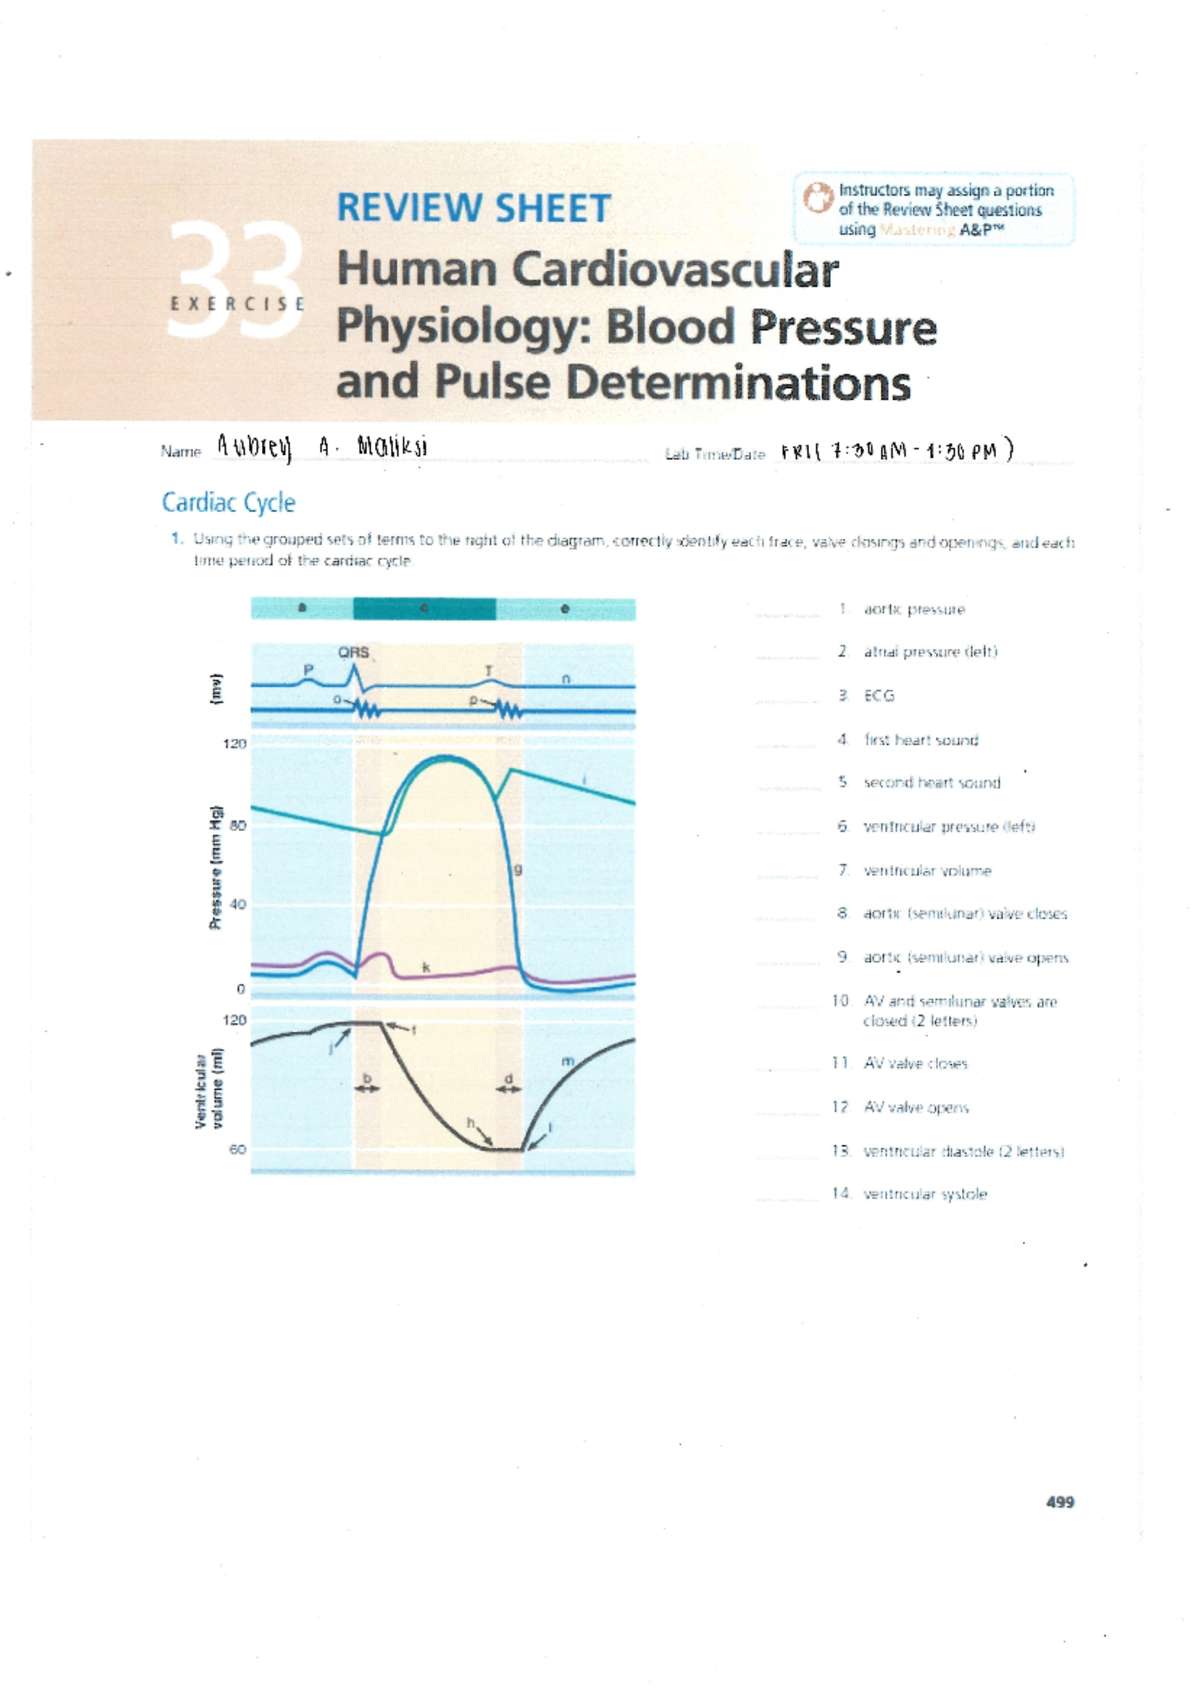
This is where most groups start falling behind. You need to record at least four leads during a resting state, usually labeled I, II, III, aVR, aVL, and aVF depending on your equipment. Lead II typically gives the clearest P-QRS-T complex, which is why it's the standard monitoring lead. If your tracing looks messy, check the electrode placement first. A loose lead wire or dried gel on the adhesive pad will introduce baseline wander that makes interpretation nearly impossible. Measure the intervals correctly. The PR interval runs from the beginning of the P wave to the beginning of the QRS complex. It should fall between 0.12 and 0.20 seconds on standard paper speed of 25 millimeters per second. If your graph paper uses different calibration, convert accordingly. The QT interval is trickier because it varies with heart rate. Use Bazett's formula to correct it: QT divided by the square root of the RR interval in seconds. A corrected QT above 0.44 seconds in men or 0.46 seconds in women flags potential repolarization issues, though exercise and electrolyte imbalances can push it higher temporarily without indicating pathology. I learned the hard way that ambient electrical interference from fluorescent lights overhead or ungrounded lab equipment can add a 60-hertz noise pattern directly onto your ECG trace. The waveform doesn't flatten out; it gets this fuzzy thickening across every deflection. One time I spent twenty minutes troubleshooting a student's supposedly arrhythmic tracing before I realized the problem was a nearby power strip vibrating against the metal table leg. Moving the setup to an outlet on a different circuit cleared the artifact immediately.
Get the Full Details
Pulse Rate During and After Exercise
For the exercise portion, most protocols call for a series of jumping jacks or step-ups, usually for thirty seconds to one minute, followed by immediate pulse measurement. The key is speed. You need the pulse count within fifteen to thirty seconds of stopping activity. Any longer and your heart rate begins recovering, which skews the comparison data. Count the radial pulse for exactly fifteen seconds and multiply by four. Some programs ask for thirty seconds multiplied by two. Either method works, but be consistent across all time points in your trial. Don't mix methods mid-experiment because the rounding error compounds when you're comparing pre-exercise baseline to post-exercise recovery curves. Recovery heart rate is actually more diagnostically interesting than the peak exercise number. A healthy cardiovascular system should drop at least twenty beats per minute in the first minute after stopping exercise. If the decline is slower, it could indicate deconditioning, dehydration, or simply that the subject wasn't resting adequately before the baseline measurement. The exact threshold varies by age and fitness level, but that twenty-beat-per-minute benchmark in the first recovery minute is a useful quick check.
Blood Pressure Response to Exercise
Systolic blood pressure should rise with exercise intensity. Expect an increase of roughly twenty to forty millimeters of mercury above resting values for moderate exertion. Diastolic pressure stays relatively stable or decreases slightly due to vasodilation in the working muscles. If you see diastolic climbing sharply alongside systolic, that's unusual and worth repeating the measurement under controlled conditions before recording it as valid data. I once processed a lab report where a student's diastolic jumped from eighty to one hundred and ten after exercise. We retried it twice. Third time we realized the cuff was placed over the antecubital fossa crease itself, and the flexion of the arm during the measurement was compressing the artery below the cuff site. That anatomical occlusion artificially elevated both numbers. Proper placement is about two centimeters above the antecubital fossa, never directly over the joint flexion point.
Data Interpretation and Common Pitfalls
Your final write-up needs to connect the numbers to actual physiological mechanisms. When exercise increases cardiac output, it's primarily driven by increased heart rate up to a point, then stroke volume contribution plateaus. The Frank-Starling mechanism explains why stroke volume increases initially with greater venous return, but beyond a certain intensity the curve flattens. Don't just state that heart rate goes up. Explain the sympathetic stimulation, the decreased parasympathetic tone, and the catecholamine release from the adrenal medulla that drives the response. Similarly, when interpreting ECG changes, distinguish between sinus tachycardia and other supraventricular rhythms. Sinus tachycardia shows a normal P wave before every QRS complex with a rate above one hundred. The P wave morphology stays consistent. If the P waves become abnormal or disappear, you're looking at something else entirely, and labeling it as normal exercise response is incorrect. One detail most rubrics don't emphasize enough is temperature's effect on enzymatic conduction in cardiac tissue. Warmed extremities conduct better, meaning electrode contact impedance drops. Cold hands or a cold lab environment can artificially slow conduction velocity slightly and distort wave amplitudes. If your lab room runs chilly, have students rub their hands together or warm their wrists before placing chest or limb electrodes. It's a small adjustment that meaningfully improves signal quality.
Recording and Formatting Your Results
When you document Exercise 33 Human Cardiovascular Physiology results, include every raw number even the ones that look wrong. Instructors can tell when data has been smoothed or selectively edited. A few anomalous readings with a brief note about what might have caused them demonstrate better scientific honesty than perfectly clean numbers that raise suspicion. I've seen entire lab reports rejected because the baseline and recovery measurements were mathematically identical to an example in the textbook, which is statistically impossible in real human physiology. Include your calculation work. Show how you derived the cardiac output from heart rate and estimated stroke volume. Show the Bazett correction. Show the pulse pressure calculations. These intermediate steps are where partial credit lives if your final answer is off due to a transcription error, which happens more often than you'd think when you're rushing through a timed lab session. The apparatus calibration sheets matter too. Some courses require you to note the calibration settings on the recording device at the start of each session. If the paper speed was set to fifty millimeters per second instead of the standard twenty-five, every interval measurement doubles in duration value. That's an easy mistake to make and nearly impossible to catch without checking the calibration documentation after the fact.
What to Do When Your Data Doesn't Make Sense
Sometimes it just happens. A subject's heart rate barely changes during exercise. Blood pressure readings are inconsistent. The ECG trace is unreadable. This isn't necessarily failure. First, verify that the subject followed instructions about avoiding caffeine and vigorous activity for several hours before the lab. Stimulants can blunt the expected heart rate response significantly. Then repeat the measurement after a proper rest period rather than moving forward with compromised data and trying to explain it away later. If you consistently get poor electrode contact despite replacing pads and cleaning skin with alcohol wipes, try lightly abrasing the skin surface with gauze before applying the electrode. This removes the outer dead cell layer that insulates the skin and improves conduction. Don't scrub hard. A gentle abrasion is sufficient. When writing your conclusion, address the discrepancies directly. State what deviated from expected values and propose plausible physiological or technical explanations. A well-reasoned discussion of why your data looked unusual scores better than a conclusively wrong analysis presented with confidence. Cardiovascular physiology varies considerably between individuals, and your instructor expects you to recognize and articulate that variation rather than pretend every trace matches the textbook ideal perfectly.