Working Through Exercise 7 The Integumentary System in Practice
When I first assigned this lab, I assumed students would breeze through the gross anatomy of skin layers and move on. What actually happened was the opposite. The epidermis strata are straightforward on paper, but getting them right under a compound microscope is a different problem. Most students confused the stratum corneum with the stratum lucidum because the keratinized dead cells just looked like blank space at 400x. I spent an entire lab period re-teaching how to adjust the iris diaphragm so you can actually see cell boundaries instead of washed-out white blobs. The integumentary system isn't just skin. That's the textbook shorthand, and it's technically correct but practically useless. Hair follicles, nail beds, sudoriferous and sebaceous glands, the subcutaneous hypodermis with its adipose and connective tissue matrix — they're all part of the organ system because they share embryological origin, vascular supply, and innervation. If you're studying for a practical exam, memorizing the five epidermal layers gets you a C. Understanding why the palm has no hair follicles but thick epidermis and why the back has dense sebaceous glands but thinner dermis is what separates people who pass from people who ace it.
How I Actually Approach Exercise 7 The Integumentary System
Here's the sequence I use when I'm working through this alone or with students who need to internalize it rather than survive a quiz. First, look at the gross specimen. Hold the skin flap up to the light. Note where the dermis tears differently depending on whether you're pulling along Langer's lines or across them. This matters because surgical incisions follow those lines precisely, and examiners will ask you to identify them. The epidermis peels away from the dermis relatively easily at the stratum basale junction — that's the basement membrane zone, and it's where hemidesmosomes anchor the basal cells to the lamina densa. Then slide into the histology slides. Start at low power, 40x, find the dermo-epidermal junction. It should look wavy — those rete ridges and dermal papillae increase surface area for nutrient exchange because the epidermis has no blood vessels. Capillary loops sit in the papillae. If your slide shows a flat junction instead of wavy, you're looking at mucous membrane, not skin. That distinction comes up frequently on practical exams and almost nobody catches it. The stratum corneum thickness varies wildly by location. Plantar skin can have a stratum corneum up to 160 cell layers thick. Facial skin might have only 10 to 15. This isn't trivia — it's clinically relevant. A topical steroid applied to the forearm absorbs through the stratum corneum roughly 10 times faster than the same application on the sole. I remember a case where a student applied hydrocortisone cream to treat a contact dermatitis rash on their foot and ended up with pronounced skin atrophy three weeks later because they didn't account for the slower absorption rate of thick plantar skin. That's why dosage guidelines specify weaker concentrations for thicker skin regions.
Glandular Anatomy and Common Misconceptions
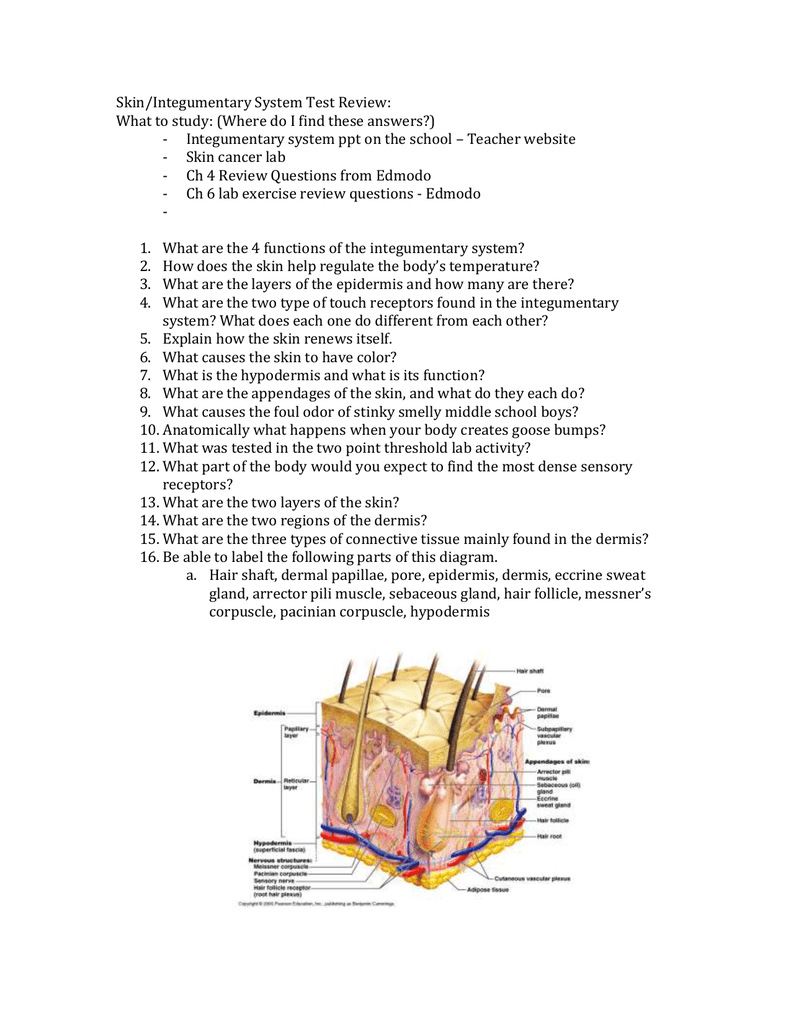
Merocrine, apocrine, and holocrine sweat glands are standard curriculum, but the naming convention trips everyone up. Merocrine means the secretory product is released by exocytosis without losing any cytoplasm. Apocrine involves pinching off the apical cytoplasm — yes, the name literally describes the mechanism, which should have been a hint. Holocrine means the entire cell disintegrates to release its product, which is exactly what happens in sebaceous glands. The sebocyte is essentially a lipid-filled bag that ruptures and becomes sebum. Here's something textbooks don't emphasize enough: apocrine glands are not the primary thermoregulatory sweat glands. Eccrine glands handle thermoregulation. Apocrine glands activate at puberty and respond to emotional stress and hormones. Their secretion is viscous, protein-rich, and practically odorless until cutaneous bacteria break it down. The old myth that apocrine glands produce body odor is backwards — bacteria produce the odor, apocrine glands produce the substrate. Confusing this during an exam costs points, and it's one of those details professors love to test because it reveals whether students actually read or just memorized headings. The arrector pili muscle attachment point is another frequently missed anatomical landmark. It anchors from the papillary dermis to the hair follicle sheath, not the epidermis. When it contracts during cold or fear, it pulls the follicle upright and creates goosebumps. But the hair itself doesn't stand up effectively in humans because our follicles aren't angled correctly and the hairs are too fine. In animals with thicker fur, the same mechanism traps a layer of insulating air. That's an evolutionary comparison that shows up on essay questions more often than you'd expect.
Get the Full Details

Wound Healing and Skin Regeneration
This is where Exercise 7 The Integumentary System transitions from rote memorization to actual clinical reasoning. Superficial wounds that only involve the epidermis heal by re-epithelialization. Basal keratinocytes migrate from the wound edge and from residual follicular epithelium to close the gap. No scar forms because the dermal matrix wasn't disrupted. Deep wounds that penetrate the reticular dermis heal by granulation tissue formation and collagen deposition. Fibroblasts lay down type III collagen initially, which gets remodeled into type I over months. The result is a scar — denser, less elastic, no hair follicles or glands within the repaired tissue. I ran into a real edge case last year that I still think about. A student was examining a healing incision slide and insisted the dense collagen bundle they saw in the dermis was normal reticular dermis. It wasn't. It was a keloid — excess collagen deposition that extends beyond the original wound boundary. The difference between a hypertrophic scar and a keloid is purely clinical: hypertrophic scars stay within the wound margins and often regress over time. Keloids grow beyond them and never fully resolve. On a histology slide, they look almost identical — thick, haphazardly arranged collagen bundles with sparse fibroblasts. The only reliable distinguishing feature is the clinical history, which means if a question asks you to identify the lesion without context, it's deliberately ambiguous. I tell students to flag that and move on rather than waste points second-guessing. Vitamin A deficiency is another angle worth mentioning because it connects nutrition to skin pathology. Without adequate vitamin A, keratinization becomes abnormal — the epithelial cells keratinize too aggressively instead of maintaining their differentiated state. This causes follicular hyperkeratosis, the rough bumpy skin texture people call frog skin. It's reversible with supplementation, but chronic deficiency leads to permanent structural changes in the stratum corneum. I bring this up because it demonstrates that the integumentary system doesn't operate in isolation. Systemic nutrition, hormonal status, and even psychological stress directly affect skin integrity.
Practical Exam Preparation
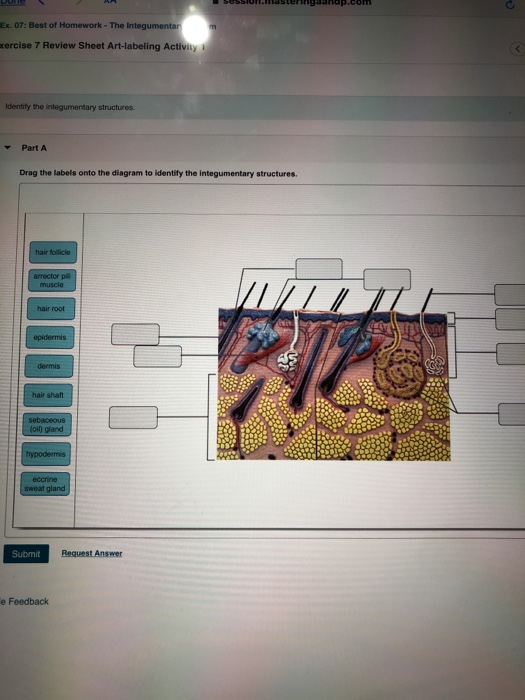
If you're preparing for a practical on this material, focus on three things: identification, relationship, and function. Don't just label the stratum spinosum — know why it's called that (the spiny appearance is an artifact of cell shrinkage during fixation, the actual desmosomal connections are what give it structural integrity). Don't just identify a sebaceous gland — know it drains into the hair follicle above the arrector pili insertion point, not into a duct that opens on the skin surface like eccrine glands do. Memorize the nerve supply. The dermis contains Meissner's corpuscles in the papillae (light touch, densely packed in fingertips and lips), Pacinian corpuscles in the reticular dermis and hypodermis (pressure and vibration), free nerve endings throughout (pain and temperature), and Ruffini endings (skin stretch). These aren't optional details. They're the difference between knowing the integumentary system as a passive covering and understanding it as the primary sensory interface between the body and the environment. The nail unit deserves attention too. The nail matrix produces the keratinized nail plate. The lunula is the visible whitish area where the matrix is thickest and the underlying capillaries are obscured. The eponychium is the living tissue at the nail base — the cuticle is the dead tissue that overlaps it. People confuse these constantly, and the confusion carries over into practical exams where labeling diagrams requires precision. A missed label on the proximal nail fold versus the cuticle can cost a full point on a 50-station practical, which is the difference between a B and a C in most grading schemes.
What This Material Doesn't Cover Well
Most introductory courses treat the integumentary system as a collection of static structures. They don't adequately address dynamic functions like thermoregulatory vasoconstriction and vasodilation, the role of Langerhans cells in immune surveillance, or the synthesis of vitamin D3 from 7-dehydrocholesterol upon UV exposure. These are higher-yield topics for medical and nursing students but get glossed over in general biology. If you're in a health sciences track, you'll need to supplement this material with dermatology and immunology references. The base curriculum gives you the architecture, but the physiology lives outside the standard lab manual. Burn classification is another area where the standard material falls short. First-degree burns affect only the epidermis. Second-degree partial thickness involves the epidermis and dermis — the distinction between superficial and deep partial-thickness determines whether the burn heals by re-epithelialization or requires grafting. Third-degree full-thickness burns destroy the entire dermis and all appendages. Fourth-degree extends into subcutaneous tissue, muscle, or bone. Coursework rarely drills this distinction with clinical images, so students can identify the histological layers but can't map them onto real injury presentations. I recommend looking at burn classification charts from the American Burn Association alongside your lab slides. The visual correlation makes the anatomy stick.