What Exercise Physiology Actually Looks Like in Practice
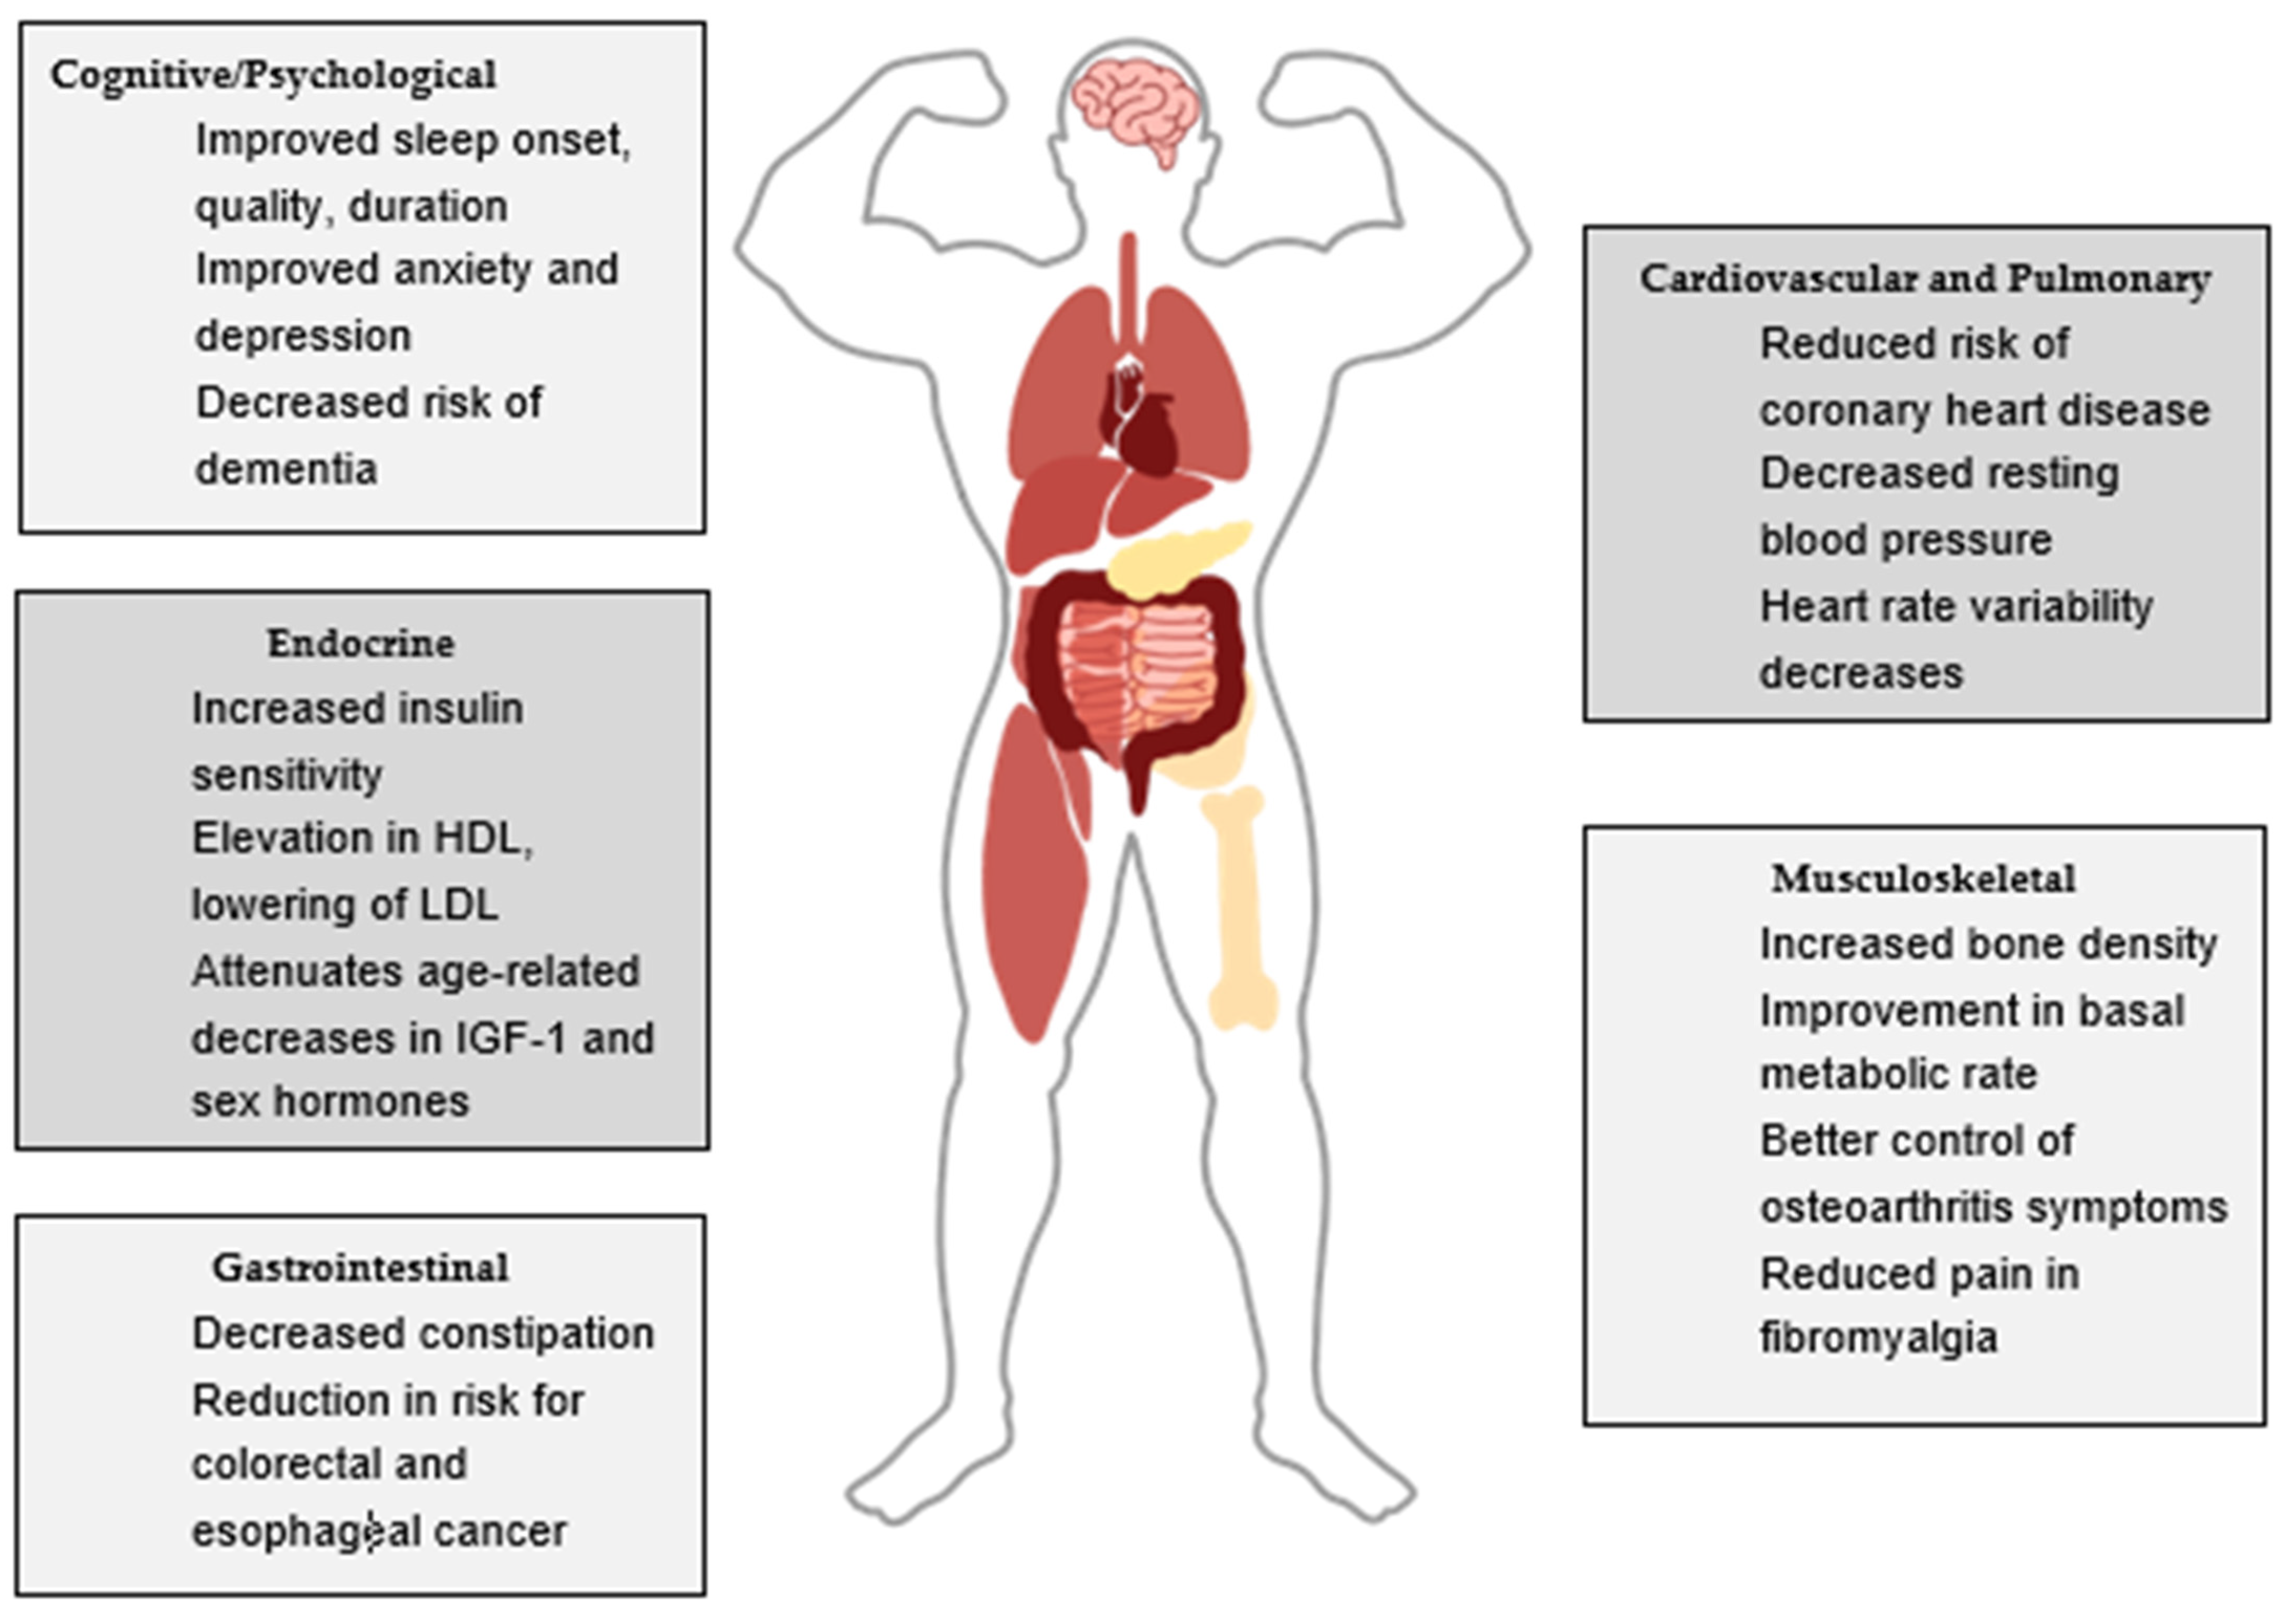
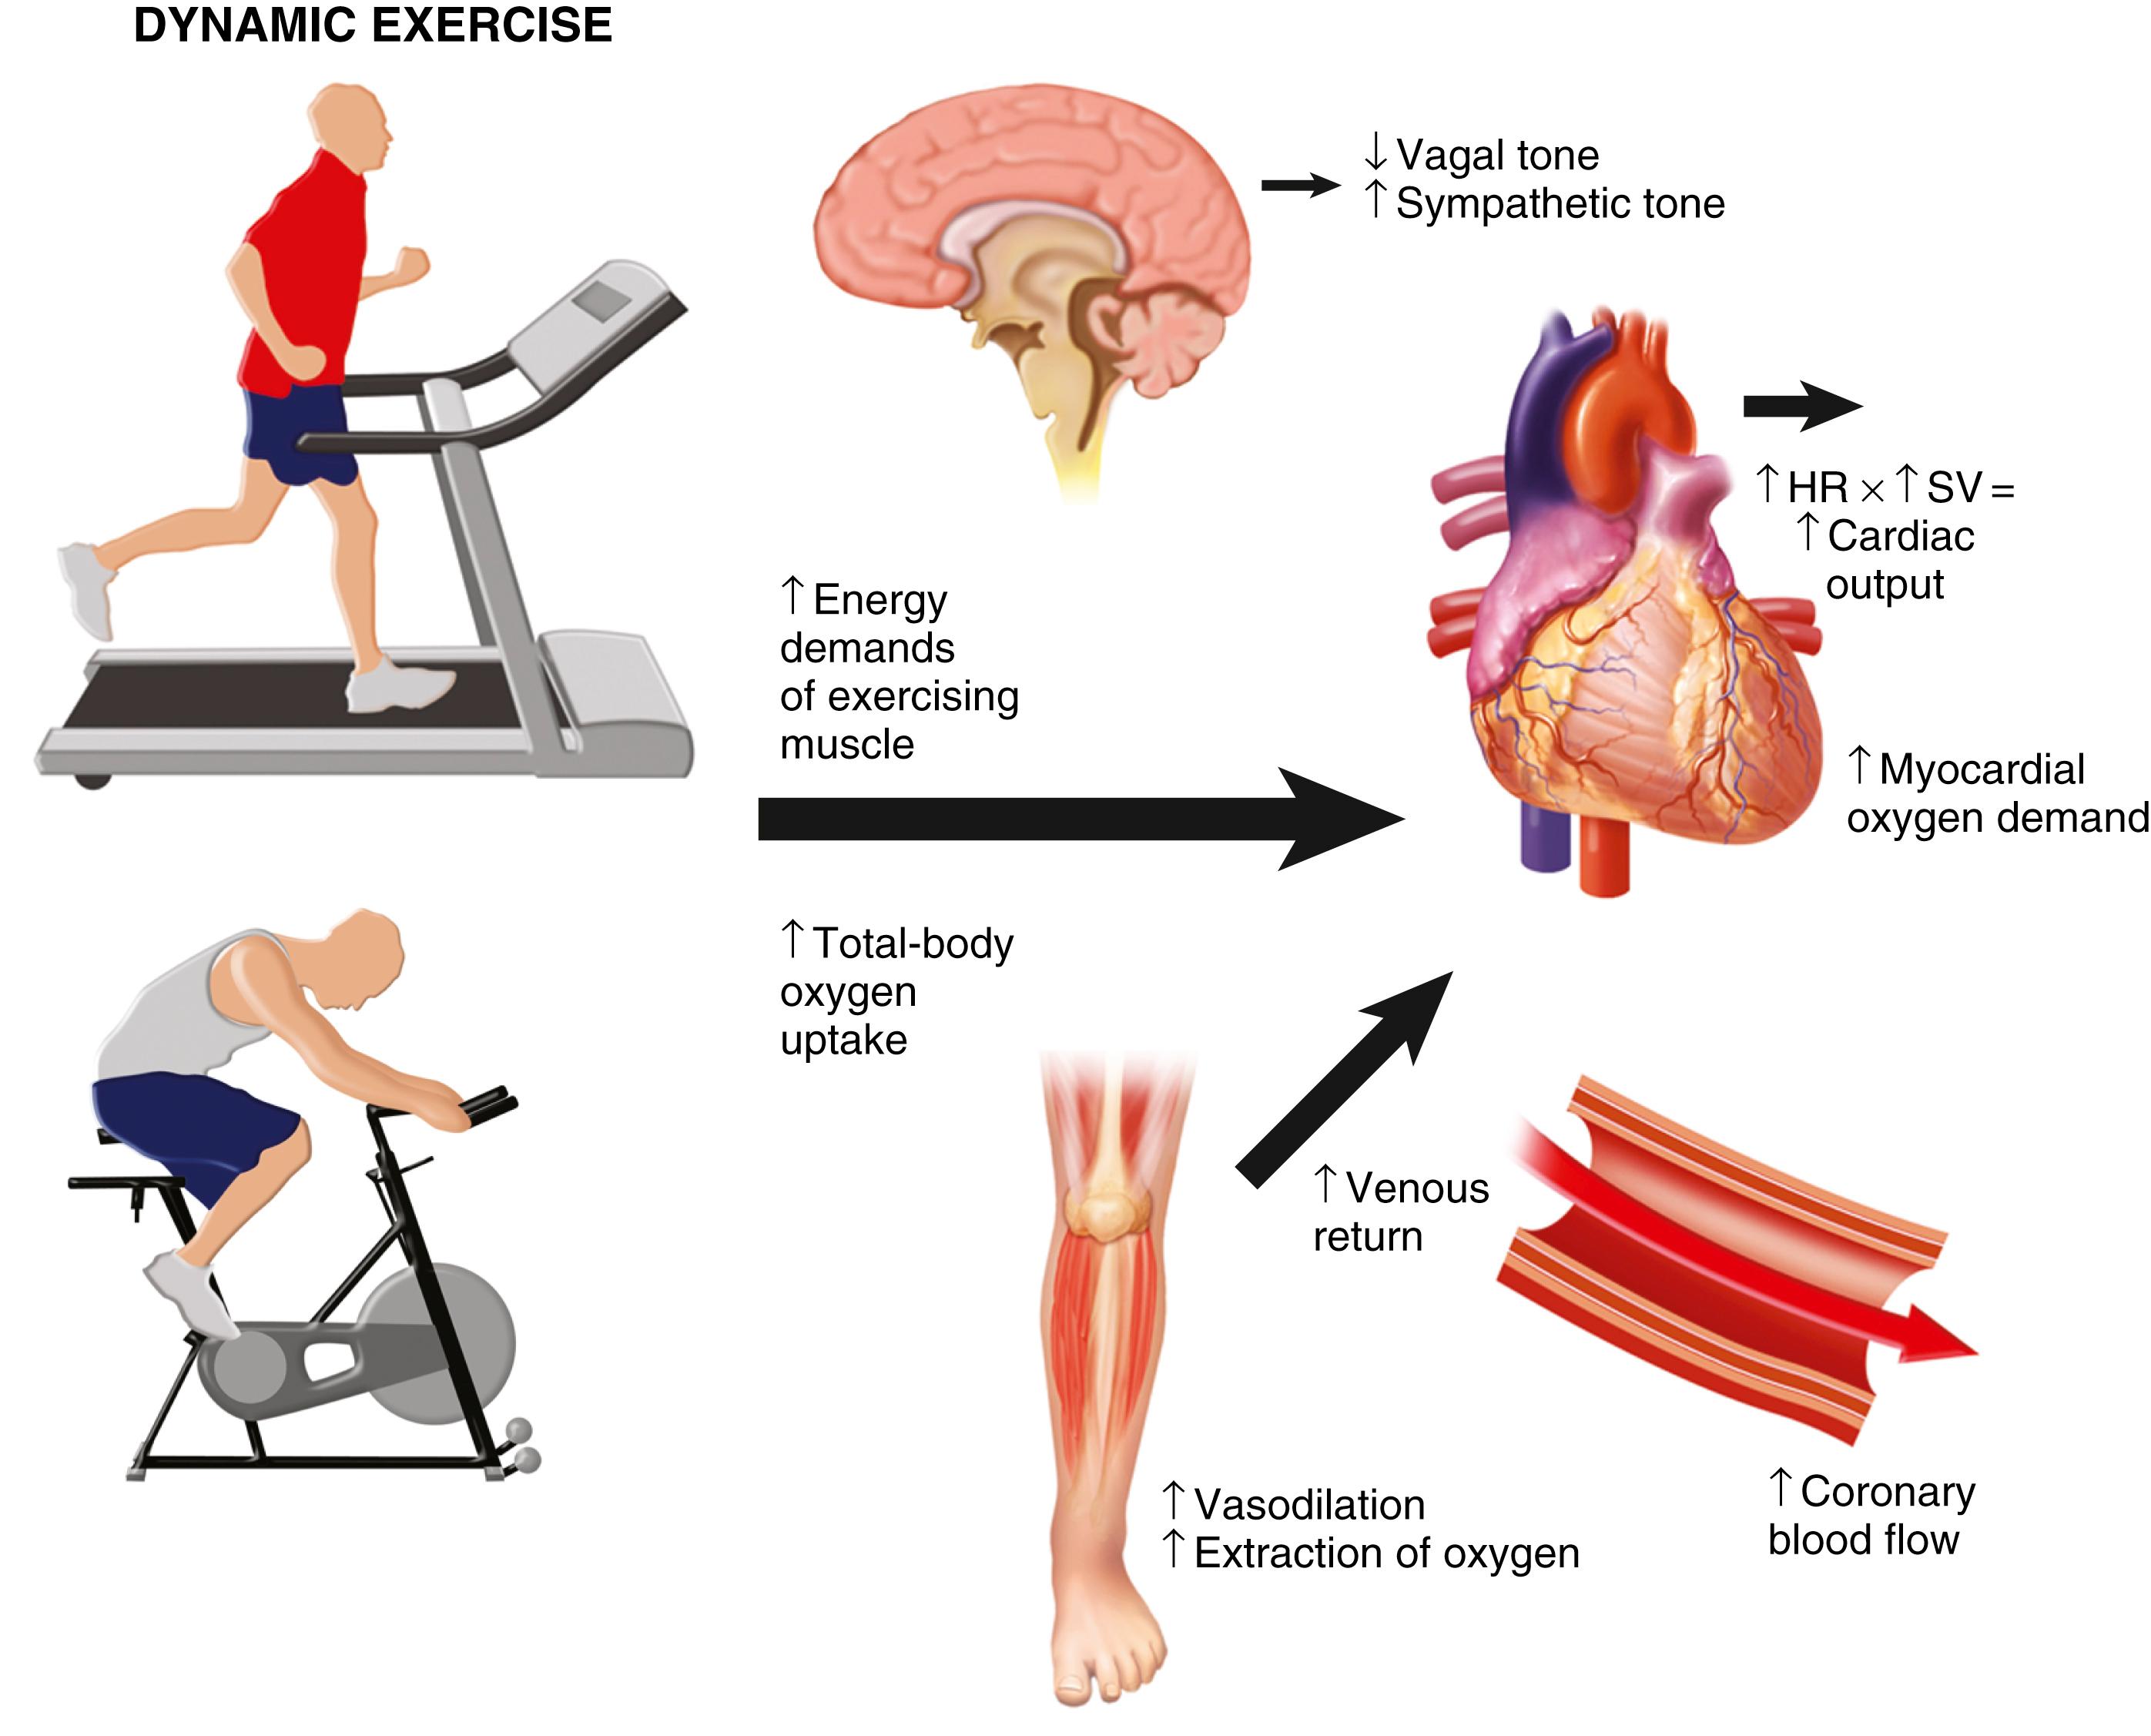
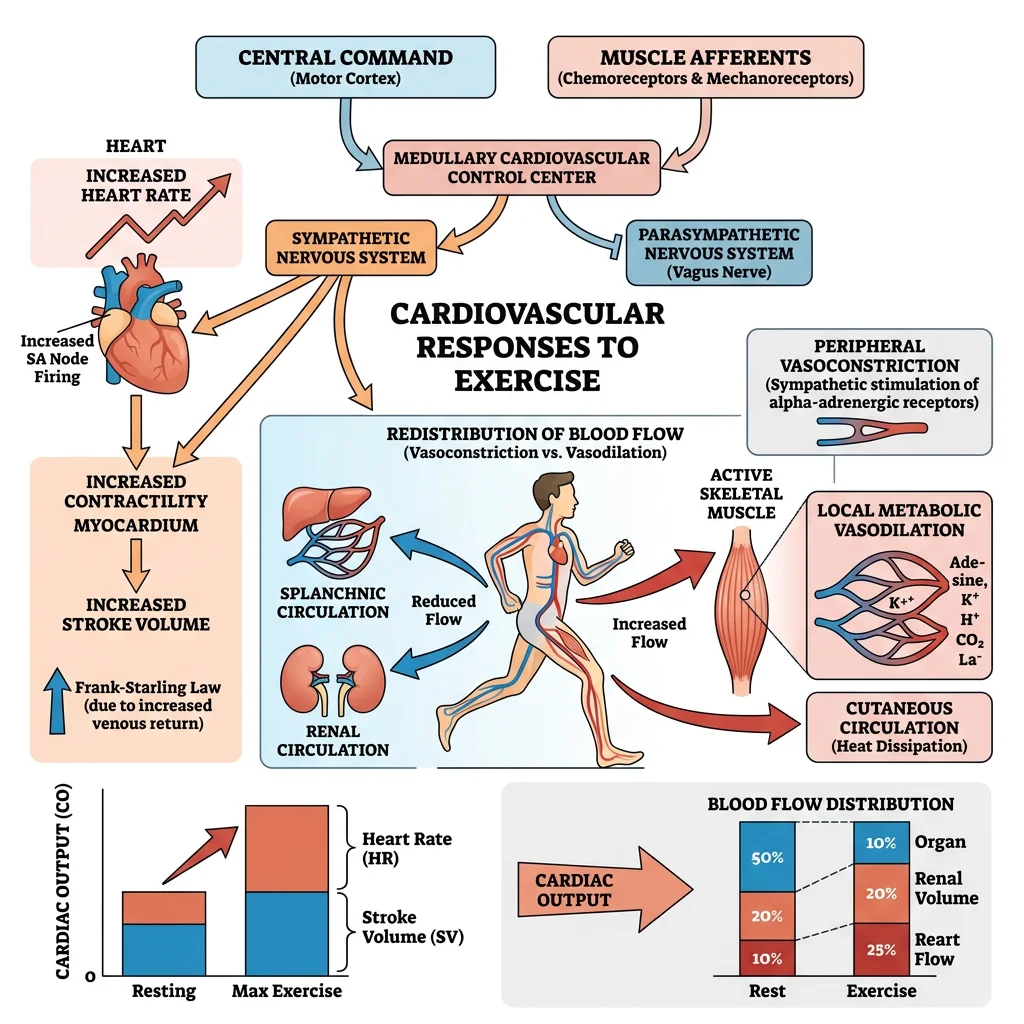
People tend to treat the Exercise Physiology Definition as something you pull from a textbook and memorize for an exam. It isn't that. The field covers how the cardiovascular, respiratory, muscular, and endocrine systems respond and adapt to acute and chronic physical stress. That's the formal line. The actual work is messier. When I run testing protocols, I'm looking at lactate thresholds, VO2max curves, cardiac output dynamics, and muscular fatigue patterns across sessions, not just single data points. The definition says it's the science of body function during physical activity. What that means on a Tuesday morning is deciding whether a subject's elevated heart rate at submaximal workload is dehydration, poor sleep, or a genuine training adaptation. The book answer doesn't help you there. I've seen too many practitioners skip the context and just plug numbers into standard equations. That produces reports that look correct on paper and fall apart when applied to actual athletes or clinical patients. The gap between the textbook definition and working knowledge comes from handling edge cases where the models break down.
One specific example. A client came in with what looked like a normal VO2max result on gas analysis. Thirty-two years old, recreational runner, nothing flagrant in the screening. But her heart rate recovered abnormally slow post-exercise, and her lactate clearance between intervals was inconsistent. The standard definition would have me call it a solid aerobic profile. I ran a separate metabolic cart calibration check and found the oxygen sensor was drifting by about four percent over the test duration. The numbers looked fine until I cross-referenced them with blood lactate and heart rate variability data. After recalibrating and redoing the protocol with a shorter warm-up to stabilize readings, her actual VO2max dropped roughly twelve percent from the initial reading. The definition didn't change. The application did.
How the Definition Translates to Testing Protocols
Aerobic capacity testing, anaerobic power assessment, metabolic rate measurement, and musculoskeletal function evaluation are the main categories. Each one has accepted methodologies. The issue is that accepted doesn't mean universal. Different labs use different protocols for the same measurement, and results aren't always interchangeable between them. Incremental exercise testing is the standard for determining ventilatory and lactate thresholds. I usually run a ramp protocol starting at fifty watts for cycling or eight kilometers per hour for treadmill, increasing by twenty to twenty-five watts or point five kilometers per hour every minute. The goal is reaching volitional exhaustion in eight to twelve minutes. Anything faster skews the lactate data. Anything slower introduces fatigue from prolonged effort rather than true maximal capacity. Anaerobic testing commonly uses the Wingate protocol or vertical jump measurements with force plates. The Wingate is a three-minute all-out cycle against a fixed resistance. It's brutally simple and notoriously inconsistent between subjects because it depends heavily on leg strength and motivation. I've found that pairing it with a countermovement jump test gives a more complete picture of anaerobic contribution without relying solely on cycle Ergometry.
Get the Full Details
Body composition and metabolic screening through indirect calorimetry and skinfold measurements remain part of the definition but are often overvalued. Resting metabolic rate tests are useful for tracking changes over time, but a single RMR measurement tells you very little about exercise performance. The error margin on portable metabolic carts can be three to five percent depending on calibration quality and subject compliance.
Common Misunderstandings About the Field
One persistent problem is treating exercise physiology as purely descriptive. It's not. The field makes predictions. You should be able to take a baseline set of physiological markers and project how an individual will respond to a given training load within a specific timeframe. When your projections consistently miss by more than fifteen percent, you're either measuring the wrong variables or your model is too simplified for the population you're working with. Another blind spot is the assumption that lab-grade equipment always produces better answers than field tests. It doesn't. A well-executed field test with proper protocols often produces more ecologically valid data than a lab test that isolates the athlete from real-world conditions. I've had athletes who tested poorly on a treadmill VO2max test but showed strong aerobic metrics during outdoor sport-specific assessments. The difference wasn't in their physiology. It was in how their body responded to different movement patterns and environmental factors. Gender differences also get simplified in ways that create practical problems. Hormonal cycle variations affect lactate threshold, core temperature regulation, and perceived exertion in women. Standard protocols designed around male physiology can produce misleading results when applied without adjustment. This isn't a minor footnote. It changes how you interpret the data enough to alter training recommendations.
Where the Definition Falls Short
The formal Exercise Physiology Definition works well for healthy, young, asymptomatic populations. It breaks down noticeably with older adults, clinical patients, and athletes with chronic training loads. Cardiovascular responses in hypertensive patients don't follow the same linear patterns. Respiratory compensation in COPD patients skews ventilatory threshold calculations. Overtrained athletes show paradoxical drops in submaximal heart rate that can be mistaken for improved fitness. The definition also doesn't account for inter-individual variability in mitochondrial density, capillary network development, or fiber type distribution beyond broad categorization. Two people with identical VO2max values can have completely different metabolic profiles and fatigue resistance. The numbers look the same. The physiology underneath is different. If you're building programs or making decisions based purely on standard exercise physiology testing, I'd recommend supplementing with subjective markers like RPE scales, sleep quality logs, and hormonal panels when working with competitive athletes or clinical populations. The quantitative data tells you what's happening. The qualitative data tells you why it's happening and whether it's sustainable.