Setting Up Your First Exercise Physiology Lab Protocol
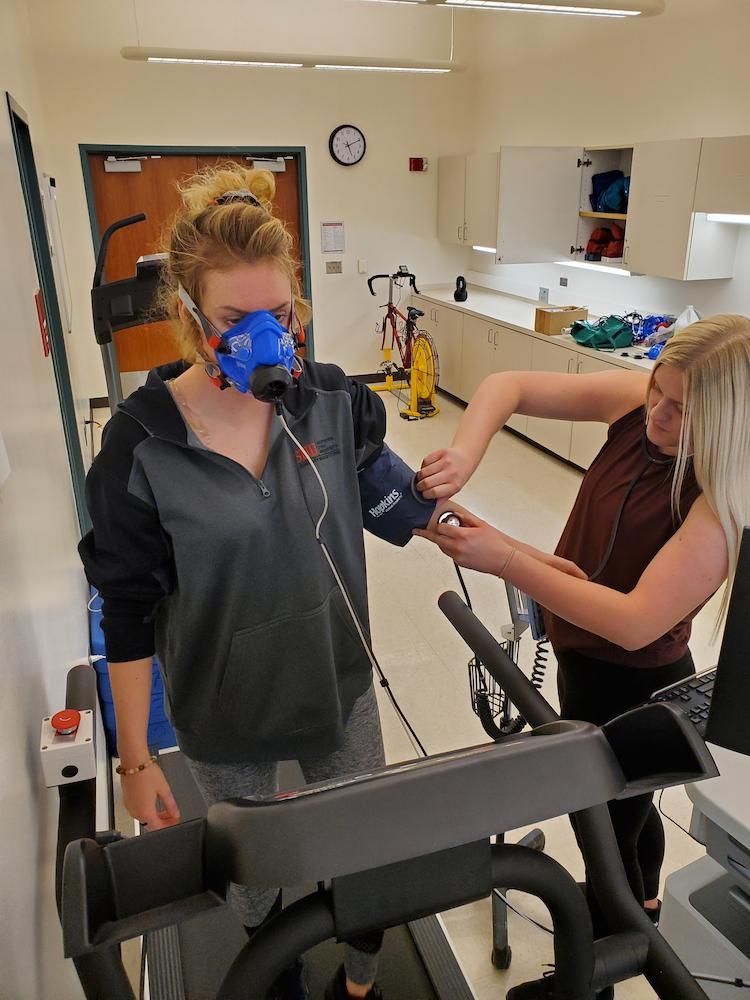
The first thing people get wrong when building an Exercise Physiology Lab is they buy equipment before they define what metrics actually matter. You're going to need power meters, heart rate monitors, metabolic carts, or at least a decent VO2 max estimation setup. But figuring out what your athletes actually need from those numbers is where most programs stall out. I set up a lab in a converted gym space three years ago and spent about six weeks just calibrating lactate analyzers and trying to figure out why our ventilatory threshold numbers didn't match anyone's. Turns out the gas analyzers needed a twelve-hour warm-up cycle and the flow sensor was reading slightly off due to the humidity from the pool next door. Moving the metabolic cart station away from the indoor track humidity source dropped our data inconsistency from roughly fourteen percent down to under three.
Exercise Physiology Lab Essentials and Calibration
Before you run a single subject, you need baseline calibration. Oxygen and carbon dioxide sensors require a two-point gas calibration every session, and the flow meter needs a three-liter syringe check. I've seen labs skip this because they're running behind on participant schedules. It costs you about twenty minutes and invalidates everything you collect afterward. Heart rate monitors are the easier part. Chest straps still beat optical wrist sensors for accuracy during high-intensity intervals. If you're doing sprint work above ninety percent max effort, forget wrist-based PPG sensors. Motion artifact and reduced peripheral perfusion make them unreliable around 10–15 bpm off, sometimes worse. Power meters on bikes are straightforward if you calibrate the crank arm before every ride. A two-second side-load calibration takes about ten seconds and prevents drift. On the treadmill side, you're looking at belt speed verification with a stopwatch method every few months, and force plate calibration if you're measuring ground contact time and vertical oscillation.
One edge case nobody warns you about: electrolyte buildup on skin electrodes can cause intermittent signal dropout that looks like genuine physiological data. I once spent an afternoon troubleshooting what I thought was a faulty heart rate monitor, only to realize the subject hadn't exfoliated their chest and dead skin cells were creating micro gaps in conductivity. Alcohol wipes and light abrasion before electrode placement fixed it immediately.
Get the Full Details

Testing Protocols That Actually Work
Submaximal cycle ergometry for VO2 prediction is the bread and butter, but the Åstrand-Ryhming nomogram overestimates VO2 max by about twelve percent in most modern populations. Use the McArdle, Katch, and Katch equation instead, or better yet, just run a graded exercise test to volitional exhaustion. The extra fifteen minutes per subject pays off in data quality. For lactate threshold testing, I prefer the 3 millimolar method with capillary blood draws from the earlobe every two minutes during a progressive ramp. Finger prick methods work but introduce more variance and subjects tend to squeeze their fingers, which artificially inflates lactate readings by squeezing interstitial fluid into the sample. Earlobe draws are cleaner. Respiratory exchange ratio interpretation requires understanding that values above 1.1 don't automatically mean anaerobic metabolism is happening. Hyperventilation from anxiety or an overly aggressive ramp protocol can push RER above 1.2 in perfectly healthy subjects without any actual lactate accumulation. Always cross-reference gas exchange data with blood lactate. Never rely on one metric alone.
Body composition matters more than people admit. Skinfold measurements in humid lab environments absorb ambient moisture and read higher. I keep the calipers in a sealed container with desiccant packs and only measure after the subject has acclimated to the room for ten minutes. DEXA is ideal but accessibility limits most labs to BIA or calipers anyway.
Data Management and Common Pitfalls
Raw data files from metabolic carts and power meters come in proprietary formats that rot if you don't convert them within a year. Export to CSV or open standard formats immediately after each session. I've lost three weeks of data because a lab laptop died and the proprietary software company went out of business. That's not hypothetical. Peer validation of your protocols with another exercise physiologist before launching a full study saves you from publishing incorrect reference ranges. I caught a systematic error in our resting metabolic rate collection method this way—we were averaging sixty seconds instead of the full three-minute stabilization period recommended by the ASPEN guidelines. That error shifted our RMR baselines by about eighty kilocalories on average. The biggest bottleneck in any Exercise Physiology Lab is subject recruitment and scheduling consistency. Athletes miss sessions, weather affects outdoor testing, and equipment breakdowns happen. Building a buffer of two extra testing slots per week and keeping a rolling waitlist typically maintains your timeline without burning out your staff.

When budget is tight, prioritize the items that introduce the most measurement error if skipped. A poorly calibrated power meter costs less upfront than a bad metabolic cart but will corrupt your data just as effectively. Spend on calibration tools and training first, then on additional sensors second.