What Actually Helps When Your Lower Back Disc Is Bulging
A slipped disc usually means the nucleus pulposus has pushed through a tear in the annulus fibrosus and is irritating nearby nerve roots. Most of these resolve on their own within six to twelve weeks without surgery. The exercises I am about to walk through are not curative — they manage symptoms and help you regain function while the body does what it needs to do. If you have bowel or bladder dysfunction, progressive weakness, or numbness in the saddle area, stop reading and go to an emergency room. That is cauda equina syndrome and it is a surgical emergency. The most evidence-backed exercise for a lumbar disc issue is directional preference-based movement. This is basically testing which positions reduce your symptoms and which make them worse. Most people with a posterior or posterolateral disc herniation find that extension — bending backward — centralizes the pain. That means the pain retreats from your leg back toward your spine. I cannot stress this enough: if a movement sends pain further down your leg, stop doing it immediately. That is peripheralization and it is the opposite of what you want. Here is the standard McKenzie press-up protocol. Lie face down. Keep your hips on the ground. Place your hands under your shoulders and press your upper body up while keeping your pelvis glued to the floor. Hold for two seconds, then lower. Start with ten repetitions. If your leg pain stays the same or moves closer to your spine, continue. If it worsens or spreads further down, this direction is wrong for you and you should try a different approach.
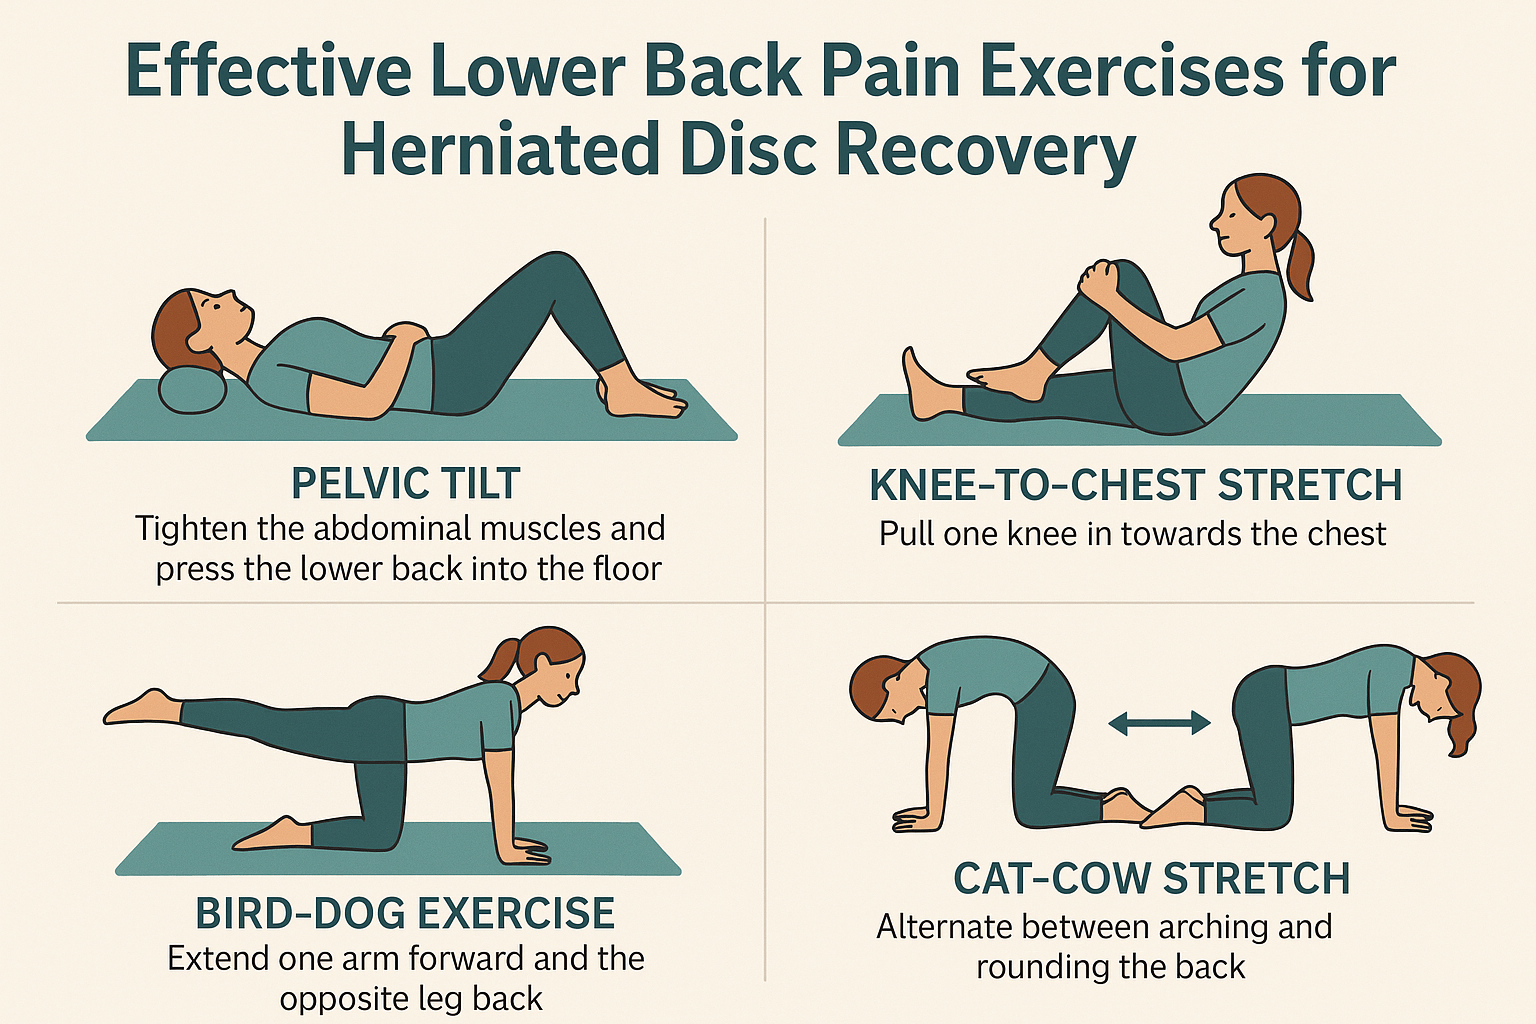
After you establish that extension works, you progress to standing extensions. Stand with your hands on your hips. Gently lean backward, keeping your legs straight but not locked. Return to neutral. Do ten reps. This mirrors the prone version and transitions you from rest position to upright function. The second category of exercises targets core stabilization without spinal flexion. Dead bugs, bird dogs, and planks are all reasonable options. The key constraint is that your spine must stay in a neutral position throughout. If your lower back arches excessively or rounds during any of these movements, the exercise is happening at the wrong spinal segment and you are just grinding the irritated disc against itself. I once had a patient who could do a thirty-second plank without any increase in leg pain, but as soon as she moved into a full plank with hips slightly elevated, she got immediate radiculopathy flare-up within forty-five seconds. The workaround was keeping the knees bent on the floor for planks and sticking to forearm planks instead of straight-arm versions. Modified load, same muscle recruitment, zero radial force on the disc. Nerve gliding exercises, sometimes called neural flossing, are worth mentioning but they are controversial in how they are applied. The seated sciatic nerve glide involves sitting on a chair, straightening one knee while dorsiflexing the ankle, then bending the knee and plantarflexing the ankle. The movement should be smooth and pain-free. I see people do this aggressively and end up irritating the nerve more than they help it. The correct approach is gentle oscillation through a comfortable range, not pushing into pain. Ten slow repetitions is plenty. Any more than that and you are just causing inflammatory collateral damage.
Aerobic walking is one of the most underrated components of recovery. Walking keeps blood flowing to the affected area, reduces stiffness, and prevents deconditioning without loading the spine in any meaningful way. Start with ten to fifteen minutes on flat ground. If that is pain-free, gradually increase duration before you worry about intensity. Cycling can work too, but only if it is an upright bike. A recumbent bike with a forward-leaning posture often puts more pressure on the lumbar discs and makes symptoms worse. I learned this the hard way with a client who switched from walking to a recumbent elliptical machine and ended up bedbound for three days afterward because his leg pain escalated significantly. Hip flexor stretching matters more than people realize. Tight hip flexors pull the lumbar spine into anterior tilt, which increases lordosis and loads the posterior elements of the disc. The half-kneeling hip flexor stretch is effective. Kneel on one knee, tuck your pelvis slightly, and lean forward until you feel a stretch in the front of the hip of the kneeling leg. Hold for thirty seconds. Three sets per side. Do not force this. A mild stretch is useful. A painful stretch will just increase muscle guarding and make everything worse. Hamstring stretching is similarly useful but again, direction matters. The supine hamstring stretch with a strap is far safer than standing forward folds because it keeps the spine in a supported neutral position rather than loading it under gravity while flexed. Lie on your back, loop a strap around one foot, and gently straighten the knee until you feel a stretch behind the thigh. Keep your lower back flat on the floor the entire time. If it lifts off, the strap is pulling too hard or your hamstrings are too tight to stretch safely in this position. Reduce the tension.
Get the Full Details
2.jpg)
The glute bridge is another staple. Lie on your back with knees bent and feet flat. Drive through your heels to lift your hips until your body forms a straight line from shoulders to knees. Squeeze the glutes at the top. Lower with control. Ten to twelve repetitions for two to three sets. This strengthens the posterior chain without spinal compression. The main mistake I see is people hiking their hips too high and ending up in excessive lumbar extension at the top of the movement. That hyperextension can pinch the facet joints and aggravate the same nerve root the disc herniation is already irritating. Stop at mid-range, not max range. I want to address something that comes up constantly and almost nobody gets right. People with a disc herniation often develop a fear of movement, which is called kinesiophobia. They avoid bending, lifting, twisting, and eventually even walking because they are convinced any movement will make it permanently worse. This is not rational. Avoiding movement leads to muscle atrophy, joint stiffness, and increased pain sensitivity from deconditioning. The research is clear that graded exposure to movement, done within a pain-tolerable range, produces better outcomes than complete rest. Rest is useful for the first few days of an acute flare, but after that, controlled movement is the treatment. There are scenarios where these exercises fail completely. If you have a sequestered disc fragment that is causing severe neurological deficit, no amount of extension exercises is going to fix it. If you have spinal stenosis rather than a disc herniation, extension exercises may actually make things worse because narrowing the spinal canal further reduces space for the nerves. If your pain is primarily axial without any leg radiation, the diagnosis might not be a disc problem at all. It could be a facet joint issue, sacroiliac joint dysfunction, or myofascial pain. In those cases, the extension protocol is not going to help and you need a different strategy.
Timeframe expectations matter. You should start seeing some improvement in two to four weeks of consistent exercise. If you are doing the right movements correctly and there is absolutely no change after four weeks, you need to reevaluate. Either the diagnosis is wrong, the exercises are not appropriate for your specific presentation, or there is a structural issue that requires medical intervention beyond physical therapy. Imaging like an MRI can clarify the situation, but imaging findings do not always match symptoms. Plenty of people have large disc herniations on MRI with no pain at all. Clinical correlation is everything. The single most important factor in recovery is consistency, not intensity. Doing gentle exercises daily produces better long-term results than doing aggressive sessions twice a week. Your tissues need repeated mechanical loading at low intensity to adapt. High intensity loading on an irritated disc is how you create a chronic problem from an acute one.


