Stroke Rehabilitation Is Not a Quick Process
I've spent years watching therapists work with people who've had strokes, and I've picked up enough firsthand knowledge to know that the rehab landscape is full of half-measures and outdated routines. Most people don't realize that exercise after a stroke isn't just about building strength back up. It's about neuroplasticity, motor relearning, and dealing with spasticity that can actively fight you at every step. The term Exercises For A Stroke Victim covers a pretty wide range of interventions, from basic range-of-motion work to task-specific training and constraint-induced movement therapy. The problem is that most sources give you a generic list without explaining which patients actually benefit from which approach. Let me break it down the way I've seen it play out in real clinical settings.
Exercises For A Stroke Victim: What Actually Works and When
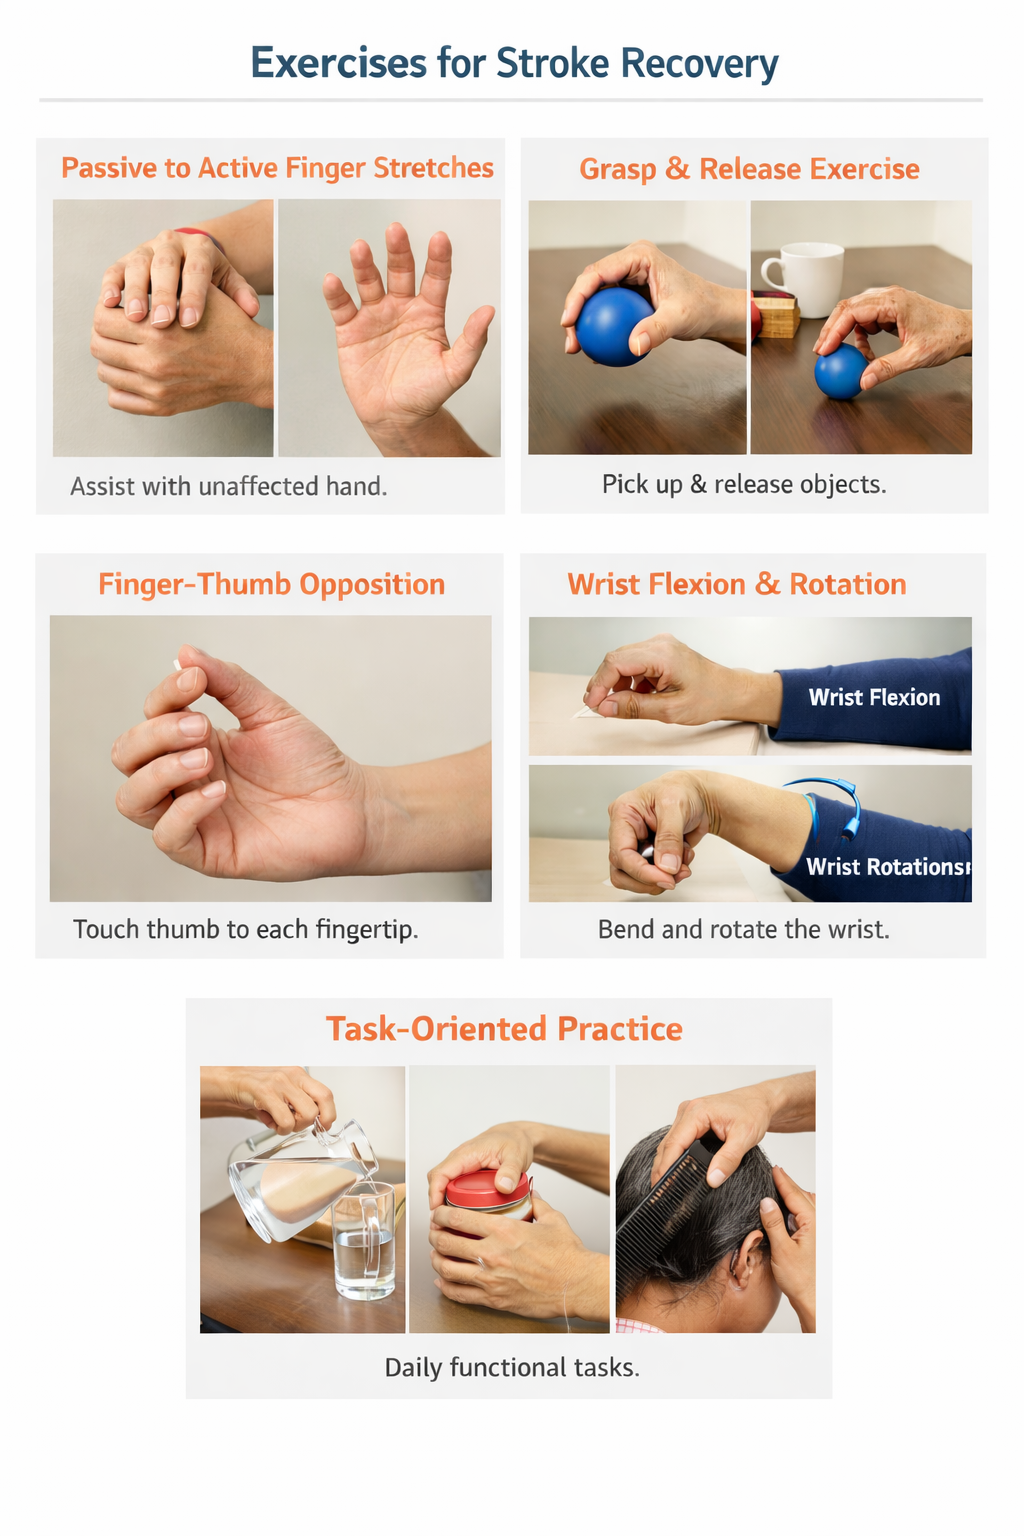
Range of motion is where almost everyone starts, and for good reason. After a stroke, the affected limbs tend to tighten up fast. If you don't keep moving the joints through their full arc, you're going to develop contractures within weeks, maybe even days in severe cases. I had a patient once who refused to do passive range of motion because it felt pointless compared to the strength work. Six weeks later, his shoulder was stuck in a fixed position and we lost months of progress. Passive range of motion should be done at least twice daily, ideally three times, for all major joints on the affected side. Task-specific training is where you see real functional improvement. This means practicing actual activities the person wants to do, not just random exercises. If someone wants to feed themselves again, you have them practice with utensils repeatedly. The key here is repetition at scale. I'm talking hundreds of trials per session, not the ten or twelve you might see in a typical outpatient session. A study published in the Stroke journal found that patients who did more than 100 repetitions of a upper extremity task showed measurably better outcomes than those who did fewer. The brain needs that volume of practice to rewire. Constraint-induced movement therapy, often called CIMT, is one of those approaches that sounds extreme but works well for the right patients. You restrain the unaffected arm and force use of the affected side for several hours a day over multiple weeks. It was developed specifically for stroke patients who have some finger and wrist movement but don't use their arm functionally in daily life. The mechanism is called learned non-use, and it's one of the most overlooked concepts in stroke rehab. After a stroke, patients learn to compensate with their good side and essentially abandon the affected side. CIMT reverses that.
The Practical Reality of Getting Started
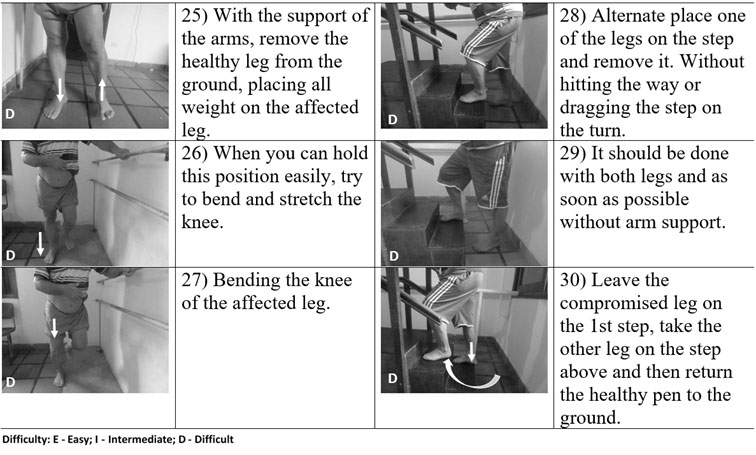
Here's what nobody tells you about starting exercises after a stroke: the biggest barrier is usually not physical limitation, it's depression and apathy. Up to a third of stroke survivors develop post-stroke depression within the first year. They don't resist exercise because they can't do it. They resist because nothing feels worth the effort. This is different from hemineglect or spatial awareness issues, which are neurological. Depression is treatable, and addressing it can make the difference between a patient who does their exercises and one who doesn't. Balance training is another area that gets short-changed. People focus so much on arm and hand recovery that they neglect the core and lower body work that prevents falls. I've seen too many patients regain decent arm function only to end up in the hospital after a fall at home because nobody emphasized balance during rehab. Sit-to-stand exercises, weight shifting, and single-leg stance work on both legs should be part of the routine from early on, assuming the patient is medically stable. One counter-intuitive point that surprises most people: exercises that feel difficult are often more effective than easy ones. The old advice to "start slow and build up" doesn't always apply here. What matters more is error-based learning. The brain needs to detect mistakes to correct them. If a patient can perform a movement perfectly on the first try every time, they aren't learning anything new. A good therapist will set tasks at a difficulty level where the patient succeeds about 50 to 70 percent of the time. That's the sweet spot.
Get the Full Details

A Specific Problem and How I Handled It
I ran into a persistent issue with a patient a few years back who had moderate right-sided weakness from a left hemisphere stroke. His hand function was improving slowly, but every time we introduced resistance training, his spasticity would flare up within hours. The elbow would flex involuntarily, making it impossible to do the exercises properly. Standard protocol would have been to reduce intensity or switch modalities entirely. Instead, I had him do relaxation techniques and gentle stretching for about twenty minutes before each exercise session, and I scheduled the stronger resistance work at the end of the day when his spasticity was naturally lower from the repeated movement throughout the day. This timing adjustment alone resolved the issue within two weeks without any medication changes. Let me be clear about the limitations here. Exercises For A Stroke Victim will not reverse severe damage. If a large area of the brain has been damaged and there's minimal residual function in a limb, no amount of exercise will restore that limb to pre-stroke function. The same applies to cognitive rehabilitation through physical exercise alone. If someone has significant aphasia or cognitive deficits, they need speech therapy and cognitive rehabilitation from qualified professionals, not just a gym routine. There's also a window of opportunity that closes over time. The highest rate of spontaneous recovery happens in the first three to six months after a stroke. Intensive exercise during this period yields the best results. That doesn't mean recovery stops after six months, because it doesn't. But the efficiency of rehabilitation declines significantly, and you need more effort for less return. Some people find this discouraging, but the alternative—doing nothing—is far worse.
The biggest risk with unsupervised exercise programs after a stroke is pushing too hard on the affected side without proper support. A patient with shoulder weakness and poor scapular control can easily injure their shoulder if they start doing overhead exercises without first building up the stabilizing muscles. Shoulder pain affects a large percentage of stroke survivors, and much of it is preventable with proper progression and attention to movement quality over quantity.
Building a Sustainable Routine
The exercises that matter most are the ones people will actually do consistently. A routine that's too ambitious will be abandoned. One that's too simple won't drive adaptation. Most stroke survivors benefit from a structured routine of about 45 to 60 minutes per day, split into two sessions if fatigue is an issue. Fatigue is enormous after a stroke, and it's not just normal tiredness. It's neurological fatigue that doesn't improve with rest in the usual way. Progressive overload does apply, but more gradually than in typical strength training. Increasing resistance or repetitions by about five to ten percent per week is a safe guideline. Anything faster tends to trigger spasticity flare-ups or compensatory movement patterns that undo the progress. The bottom line is that recovery after a stroke is highly individual, and what works for one person may not work for another. The evidence supports task-specific repetition, constraint-induced therapy for appropriate candidates, balance training, and managing depression as part of the overall program. Anything beyond that tends to be hype or unproven.