
Working Through Popliteal Tendonitis: What Actually Helps
The popliteus tendon sits right behind your knee, anchoring into the lateral femoral condyle and running down to insert on the posterior tibia. When it gets irritated, the pain tends to localize deep and posterior, sometimes radiating slightly along the back of the knee. Most people describe it as a dull ache that sharpens when they're going downstairs or when they start extending their leg from a bent position after being seated for a while. I dealt with this myself about three years ago after ramping up trail running volume too quickly. The pain was worst on the downhill sections, which makes sense because the popliteus is heavily loaded during deceleration and eccentric control of the knee. What surprised me was how much it bothered me going up inclines too, not just down. It took about six weeks of modified loading before it stopped being a constant background issue.
Exercises For Popliteal Tendonitis That Actually Move the Needle
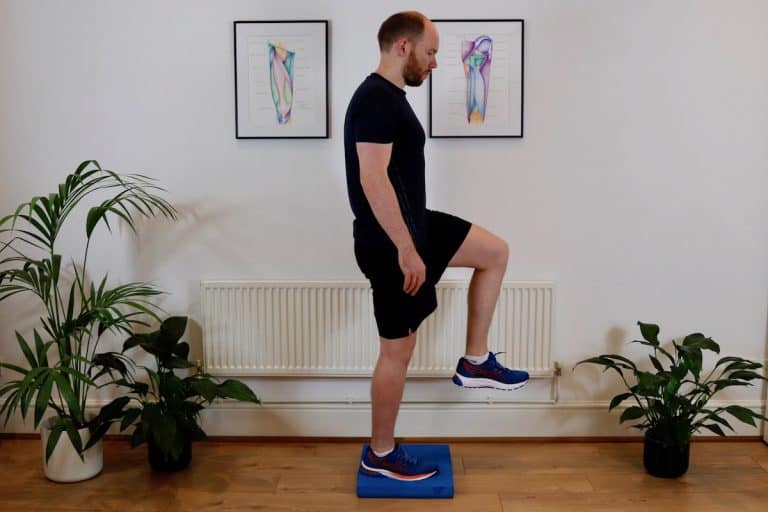
Start with isometric holds. They're the least irritating way to load a tendinopathy without aggravating it further. A practical option is a seated knee extension hold: sit on the floor with your legs straight out, press the back of your knees down into the ground, and hold for 30 to 45 seconds. You should feel it working behind the knee without sharp pain. If it hurts, reduce the hold time or the intensity. Three sets of that, once or twice a day, is a reasonable starting point. This usually takes about ten minutes total. From there, move into slow eccentric loading. Single-leg Romanian deadlifts are one of the better choices because they load the entire posterior chain—the hamstrings, glutes, and calf—while also challenging the popliteus's role in stabilizing the knee during single-leg stance. Start with bodyweight only. Perform the lowering phase over three to four seconds, pause briefly at the bottom with a slight knee bend, and then return up. Ten reps per side, three sets. Do this every other day. If the tendon feels stiff the next morning, you did too much. Cut the volume in half and rebuild slowly. Wall slides are another exercise people overlook. Lie on your back with your calves resting on a wall, knees bent at roughly 90 degrees, and then slowly slide one leg down until the knee is nearly straight, then slide it back up. The key is keeping your core braced so your lower back stays flat against the floor the entire time. You're basically teaching the popliteus to control terminal extension under load. Start with the leg that feels better and work your way to the more irritated side. Six to eight slow reps per side, two to three sets.
Hamstring curls on a stability ball work well too, but I want to flag something most guides don't mention: if you have significant IT band tightness or a stiff iliotibial band, these can actually make things worse. The IT band runs right next to the popliteus and when it's hypertonic, it can compress or irritate the tendon further during flexion and extension. I learned this the hard way. After adding ball curls to my routine without addressing my IT band first, my symptoms spiked for about two weeks. The workaround was spending ten minutes on my IT band with a foam roller and doing cross-body hip stretches before each workout session. That resolved the irritation and the curls became effective again. Calves matter more than you might expect. Gastrocnemius tightness changes the mechanics of the knee during gait, and the popliteus shares some of that loading burden. Standing calf raises with a slow three-second eccentric phase, done both with straight knees and bent knees, help address both the gastrocnemius and soleus. Twelve to fifteen reps, three sets, three times per week is a solid baseline.
Get the Full Details
What Nobody Tells You About Recovery Timelines
Tendon loading protocols are deceptively simple on paper. The issue is that people tend to escalate too fast. A common mistake is increasing volume or intensity when the pain during exercise drops, thinking that's a sign to push harder. Pain reduction during exercise is not the same as tendon healing. The tendon is still structurally compromised even if it feels fine while you're moving through the exercise. The real marker of progress is whether next-day stiffness decreases over consecutive sessions. If you do a set of exercises on Monday and Tuesday feels stiffer and more painful than Monday did, you escalated too aggressively. Drop the load by about 30 percent and rebuild from there. Another counter-intuitive thing: rest is not the answer for chronic popliteal tendon issues. Complete rest for more than a week or two tends to make tendinopathy worse because the tendon adapts to lower loads and then struggles when you return to normal activity. The tendon needs progressive mechanical stress to remodel properly. That's why the isometric-to-eccentric progression I described matters. You're giving it controlled stimulus without overwhelming it. There are also scenarios where these exercises won't help much. If your pain is coming from a meniscal issue rather than tendinopathy, or if there's significant Baker's cyst involvement, loading the tendon aggressively can worsen things. Red flags include swelling that's visible and persistent, locking or catching of the knee, and pain that's sharply localized to the joint line rather than diffuse in the posterior aspect. If any of those are present, see a physical therapist or sports medicine doctor before continuing with a self-directed program.
For most people with straightforward popliteal tendonitis though, the combination of isometric holds, slow eccentrics, wall slides, and targeted calf work, done consistently over four to eight weeks, will produce meaningful improvement. The timeline varies based on how long you've had the issue, your training background, and how well you manage the load progression. Being patient about that progression is what separates people who recover from people who cycle through the same irritation repeatedly.




